Projective Exercise 5: Antibody to a Public Antigen

As a transfusion medicine physician, I must know if I can trust my staff’s interpretation of immunohematology testing.  I may be called at night and they will provide me with results and I must use these to make a medical judgment.  If their interpretation is flawed, I might make a decision that harms the patient.

I really don’t like multiple-choice questions, but nowadays this is often the norm.  For my staff, especially senior staff and those who want to be promoted to senior staff, I have developed a series of projective exercises to help me understand their thought processes.

Here is another exercise, usually given to physicians.  I give them the following scenario:

There is a major trauma on an unidentified young adult male patient.  We do not know the transfusion, medical, or medication history.  They need six units RBCs STAT.

What blood type do you select?  How do you release the blood?

You give the 6 units and receive a specimen back.  The patient’s typing reactions are:

Forward type:  Anti-A, anti-B both negative

Reverse type:  4+ reaction with A1 and B cells

About 15 minutes later, your technologist tells you that the antibody screen is 4+ in all cells and all panel cells react 4+ both at AHG and enzyme phases.  What do you tell the treating clinician?  What do you do?

The technologist in panic has been performing AHG crossmatches but all 4+ incompatible.

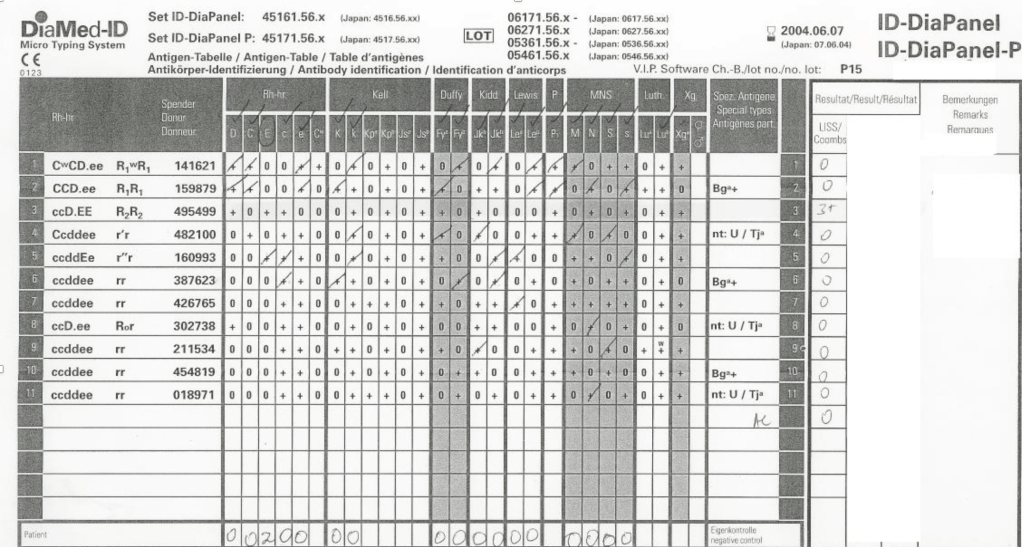
Here is the panel:
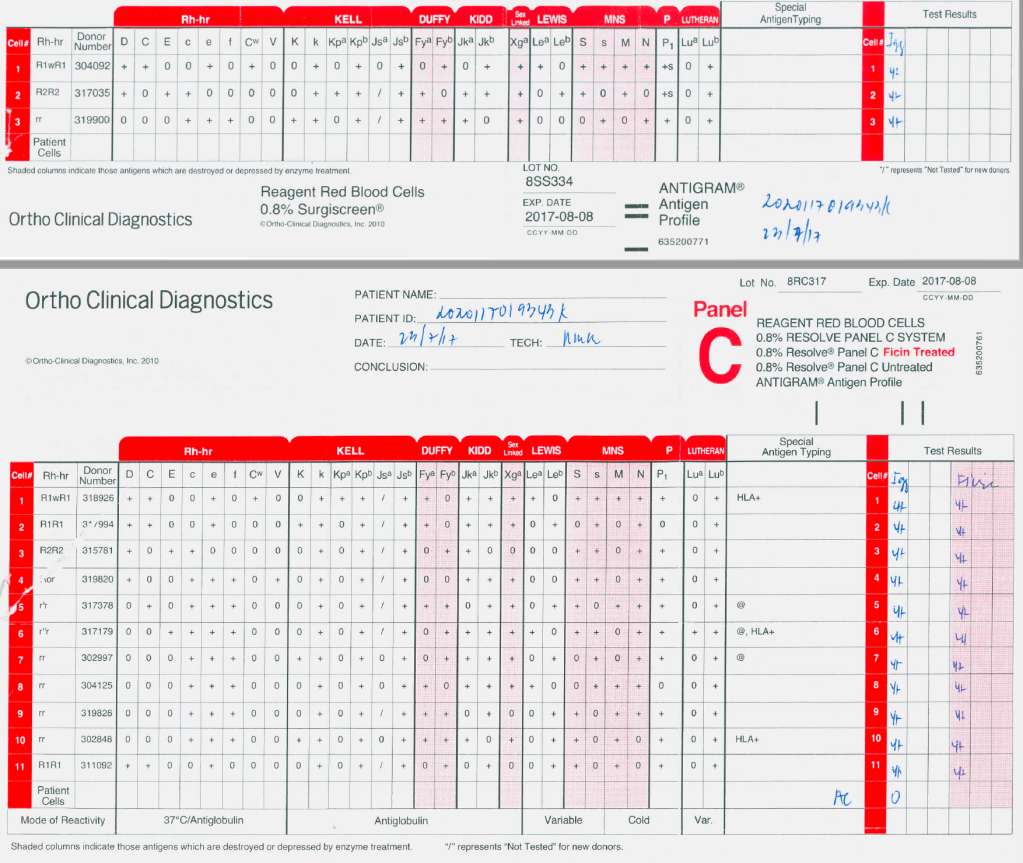
I have them review this panel and tell me to interpret it

  1. What further testing would you do, if any?
  2. What blood type do you release now?
  3. What is the significance of the negative autocontrol when there is panreactivity?
  4. What if the enzyme panel results are all negative?
  5. What if the autocontrol is 4+?

The smart ones will ask for a full extended phenotype (e.g. Diamed/Biorad’s three profile cards) and for anti-H.

I tell them the clinician is very angry and demands you release more group O blood immediately?  How do you respond?

5/9/20
Sample Resident Examination for Donor Center

Reading Assignments:

  • Chapters 5-9:  Blood Donation and Collection in Technical Manual, 16th Edition
  • Standards for Blood Banks and Transfusion Services, AABB, 25th Edition

Study Questions:

  1. Which of the following candidates is acceptable for donation?
    1. Saudi, visited Sudan 11 months ago as part of National Guard exchange
    2. Saudi former student lived in UK for 2 years from 1993-95
    3. Normotensive taking amlodipine and valsartan
    4. Psoriatic using Tegison
    5. Male adult using ibuprofen for lower back pain
    6. Female 4 weeks post-partum
    7. Husband of patient with recent onset of hepatitis B infection
    8. Male stopped taking ampicillin one week ago for acute pharyngitis
    9. Donor with WBC count 12000/cmm but otherwise normal
  2. Which of the following donors is suitable for autologous donation?
    1. Cataract surgery patient
    2. Well, but had gastroenteritis 3 days ago
    3. Pregnant with Hgb 11 g/dl
    4. CGL patient with Hgb 13 g/dl
    5. Hodgkin’s disease patient Hgb 12 for exploratory laparotomy
    6. Patient with rare antibody anti-Tja, Hgb 13 for cholecystecomy
  3. How do you handle the following events?
    1. Donor draw fills bag with bright red blood in 30 seconds
    2. Donor faints when needle is shown
    3. Lipemic serum during donor plateletpheresis session
    4. Donor with numbness and tingling of extremities during donor apheresis session
  4. How would you handle the following therapeutic phlebotomy requests?
    1. Hgb 22 g/dl, suspected polycythemia rubra vera
    2. Hgb 13, suspected hemochromatosis patient
    3. Hgb 16, renal failure patient post-erythropoietin treatment
    4. Unstable angina, Hgb 9
  5. What is the final volume of each of the following blood components?
    1. Whole blood
    2. Packed RBCs—state hematocrit as well
    3. Washed RBCs
    4. Irradiated packed cells
    5. Platelet pool—state number of platelets
    6. FFP
    7. Cryo-poor plasma
    8. Cryoprecipitate
  6. What are the outdates of each of the following components?
    1. Packed RBCs
    2. Platelet pool
    3. FFP frozen at -35C
    4. Granulocyte concentrate
  7. Which donor units are acceptable for transfusion?
    1. HBsAg negative, HBcAb positive, HBsAb > 20 IU/liter
    2. HCV Ab positive, RIBA-3 negative, HCV-RNA negative
    3. Syphilis positive, FTA-ABS negative

Revised:

29/8/20

Processes and Software Building 40: Reveos Detailed Settings

A major advantage in using a specific blood bank computer software is to enforce the Good Manufacturing Processes.  Medinfo is merciless:  there are no exceptions without authorization and that is restricted by the security policies.

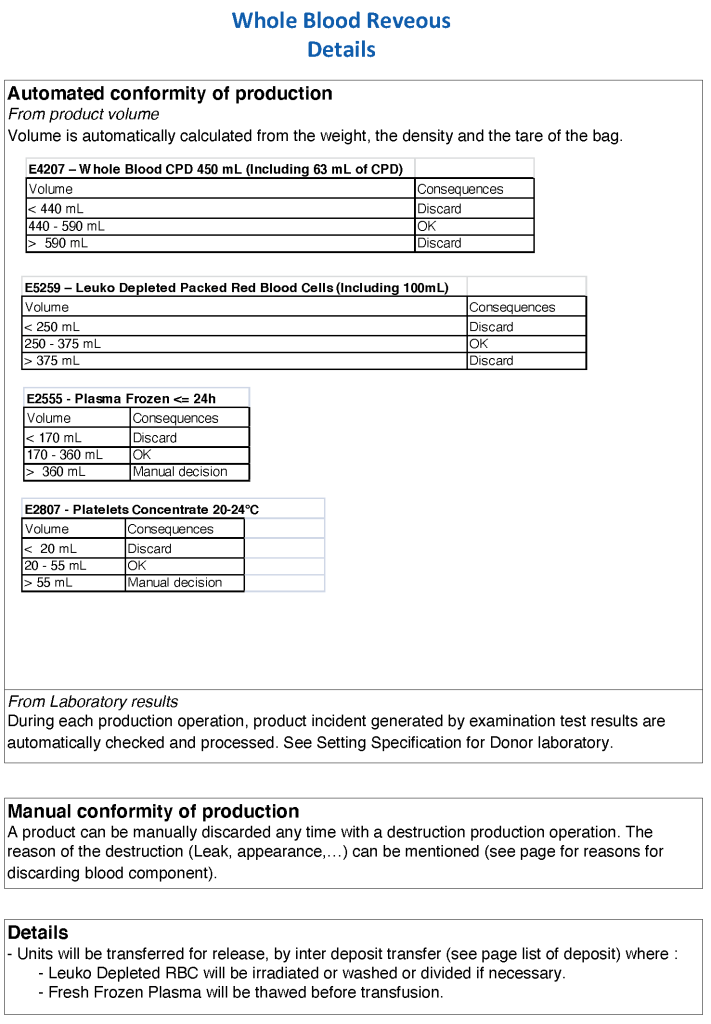
The following tables show the values established at HMC Doha during my tenure.  These values were recommended by the Terumo BCT Reveos engineer after his direct, hands-on set-up of the equipment.

The minimum and maximum volumes for platelets are specifically designed to work for pooling the buffy coats before Mirasol pathogen inactivation.  There are different settings for platelets suspended in plasma versus those suspended in platelet additive solution PAS.

Similarly, there are specific volume ranges for plasma so that pathogen inactivation can be performed according to Terumo BCT recommendations.

To Be Continued:  4/9/20

Advanced Hematology Resident Training in Immunohematology

Objectives:

  1. Theoretical:
    1. ABO system and discrepancies
    2. Rh system and discrepancies
    3. Other blood groups (Kell, Kidd, Duffy, MNSs, Gerbich)
    4. Direct antiglobulin test
    5. Comparison of gel and tube methodologies
    6. Transfusion reactions
    7. Drug-related hemolysis
    8. Inventory management
    9. Emergency blood release
    10. Massive transfusion
    11. Hemolytic disease of the newborn
    12. Transfusion-transmitted diseases and look-back
    13. Filtration
    14. Irradiation
  2. Practical:
    1. ABO/D typing
    2. Antibody screen
    3. Crossmatch
      1. Immediate-spin
      2. AHG-phase
  1. DAT
  2. Elution
  3. Antibody identification
  4. ZZAP

Clinical Responsibilities (after proven competence):

  1. Evaluation of DAT results
  2. Evaluation of antibody workups
  3. Transfusion reaction workups
  4. Component substitutions for inventory management (excluding Rh-incompatible)

Assessments:

  1. ABO typing and discrepancies
  2. Rh(D) typing and discrepancies
  3. Antibody identification
  4. DAT and drug-related hemolysis evaluations
  5. Transfusion reaction assessments
  6. Post-training

Working Hours:

  1. 0900-1700, Saturday through Wednesday
  2. Must carry pager for clinical responsibilities

Original Date:  26/6/06 for NGHA Riyadh, Reviewed 27/8/20

Processing and Software Building 39: Atreus and Reveos

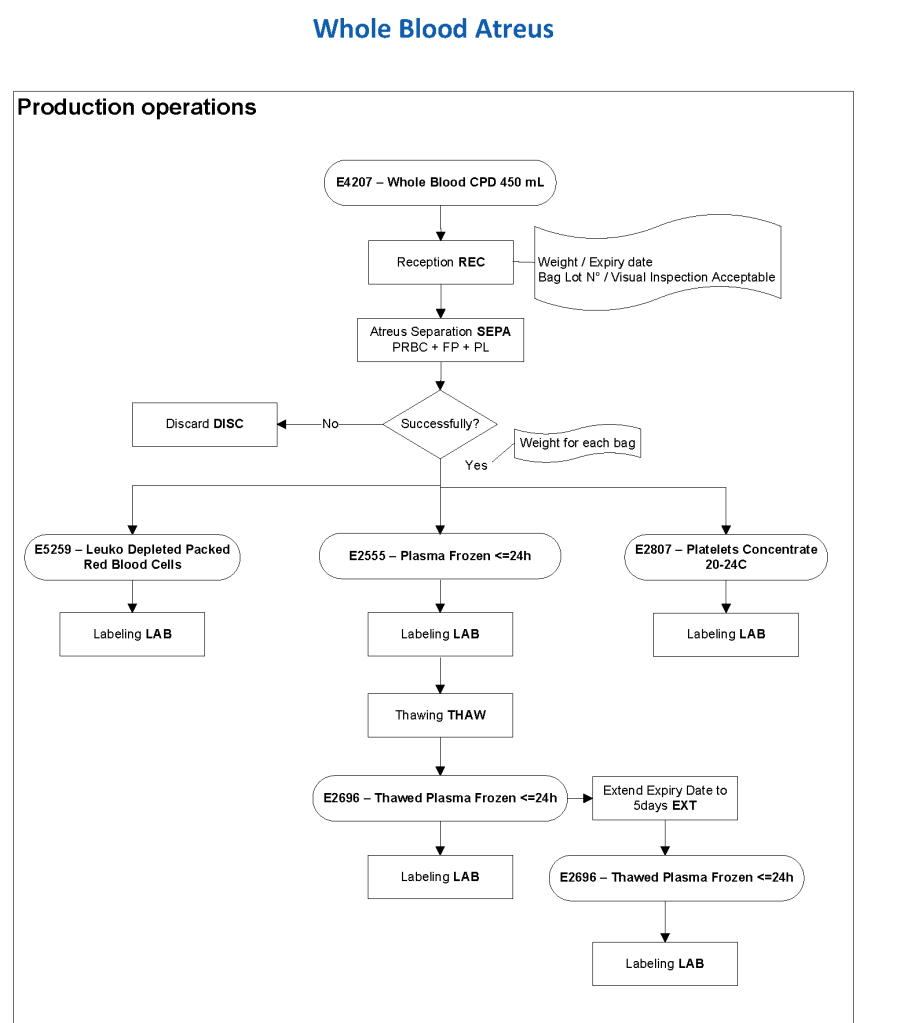
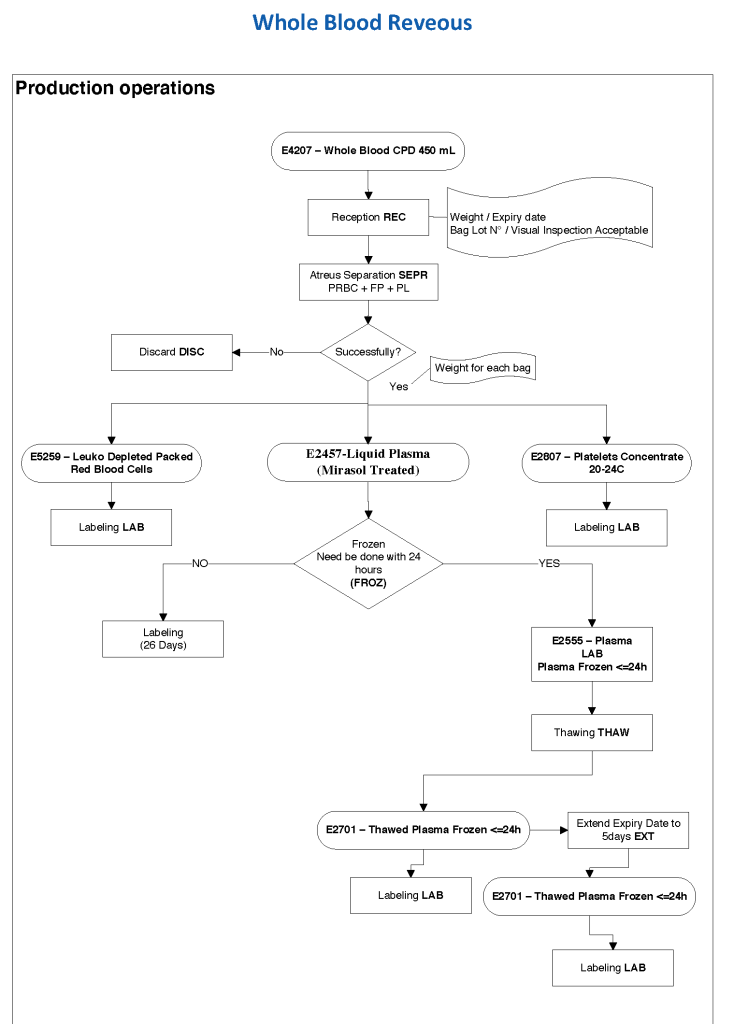
Automated component processing is an almost hands-free separation of into packed RBCs (ready for leukodepletion), buffy coat platelets (ready for pooling), leukodepleted plasma, and a residual buffy coat.  The older Atreus device takes about 10 minutes for one whole blood unit whereas the newer Reveos device needs slightly more than 20 minutes to process four whole blood units.  At the end of processing:

  1. RBCs are ready for leukodepletion using the integral filter provided with the kit.
  2. Plasma is ready for pathogen-inactivation and freezing.
  3. Buffy coat platelets are ready for pooling using the Platelet Yield Index PYI.
    1. Further processing (filtration and Mirasol treatment) occurs if the donor marker testing results pass
  4. Residual buffy coat is not a clinical product but may be used for quality control for stem cell processing and/or cell line expansion

The process in Medinfo is as follows:

  1. Receive the whole blood units for processing by reading the ISBT specimen barcode.
  2. Collection data (volume, time to complete collection, time of collection, etc.) is transferred to the component processor.
  3. Select the processing machine:  Atreus vs. Reveos
  4. Select the protocol:  2C (RBCs and plasma) versus 3C (RBCs, platelets, and plasma)
  5. Further processing as per the flow diagrams.

At HMC Doha, Medinfo developed the first bidirectional interfaces to both Reveos and Atreus.

To Be Continued

2/9/20

Advanced Hematology Resident Training in Donor Center and Apheresis

Objectives:

  1. Donor criteria based on AABB standards
    1. Is it safe for the donor to donate?
    2. Medical history
      1. Current medical conditions
      2. Past medical conditions
  2. Medications
  3. Vaccinations
  4. Travel history
  5. High-risk behaviors
  6. SARS/MERS
  7. COVID-19 convalescent plasma CCP
  8. Prion diseases
  9. Donor medical examination
  10. Is it safe for the recipient to receive the donor’s blood?
  11. Donor registration issues
    1. Positive identification
    2. Donor deferral database
  12. Donor phlebotomy
    1. Safe volume to donate
    2. Anticoagulant-preservative solutions
    3. Time limit for phlebotomy
    4. Post-donation care
  13. Donor reactions—Dx and Rx of the following:
    1. Vasovagal
    2. Seizures
    3. Air embolism
    4. Arterial stick
    5. Hematoma
  14. Donor Apheresis
    1. Plateletpheresis
    2. Plasmapheresis
    3. Plateletpheresis with concurrent plasma collection
    4. RBC collection
    5. Combined platelet, plasma, and RBC collection
  15. Autologous donation
    1. Predeposit
    2. Perioperative
    3. Intraoperative
    4. Postoperative
  16. Donor self-deferral
  17. Therapeutic Phlebotomy
  18. Therapeutic Apheresis
    1. Therapeutic plasma exchange/plasmapheresis
    2. Leukapheresis
    3. Thrombapheresis
    4. Red cell exchange
    5. Stem cell collection
    6. Column absorption technologies
    7. Clinical indications
    8. Writing orders for above procedures
  19. Component Processing:
    1. Manual
    2. Automated—Reveos
    3. Pathogen Inactivation Mirasol
    4. Buffy coat vs classic platelet-rich plasma platelets and pools
    5. Platelet Additive Solution PAS
    6. FFP, FP24, thawed plasma
    7. Cryoprecipitate
    8. Cryo-poor plasma (plasma, cryoprecipitate-removed)
    9. COVID-19 convalescent plasma CCP

Clinical Responsibilities (after proven competence):

  1. Triage of donor requests
  2. Handling of donor reactions
  3. Approval of therapeutic phlebotomies
  4. Assistance with therapeutic apheresis

Assessments:

  1. Pre-training/baseline
  2. Competency documentation for clinical responsibilities (#11 above)
  3. Post-training

Working Hours:

  1. 0900-1700, Saturday through Wednesday
  2. Must carry pager for clinical responsibilities

Reviewed 17/8/20

Processes and Software Building 38: Component Processing Overview

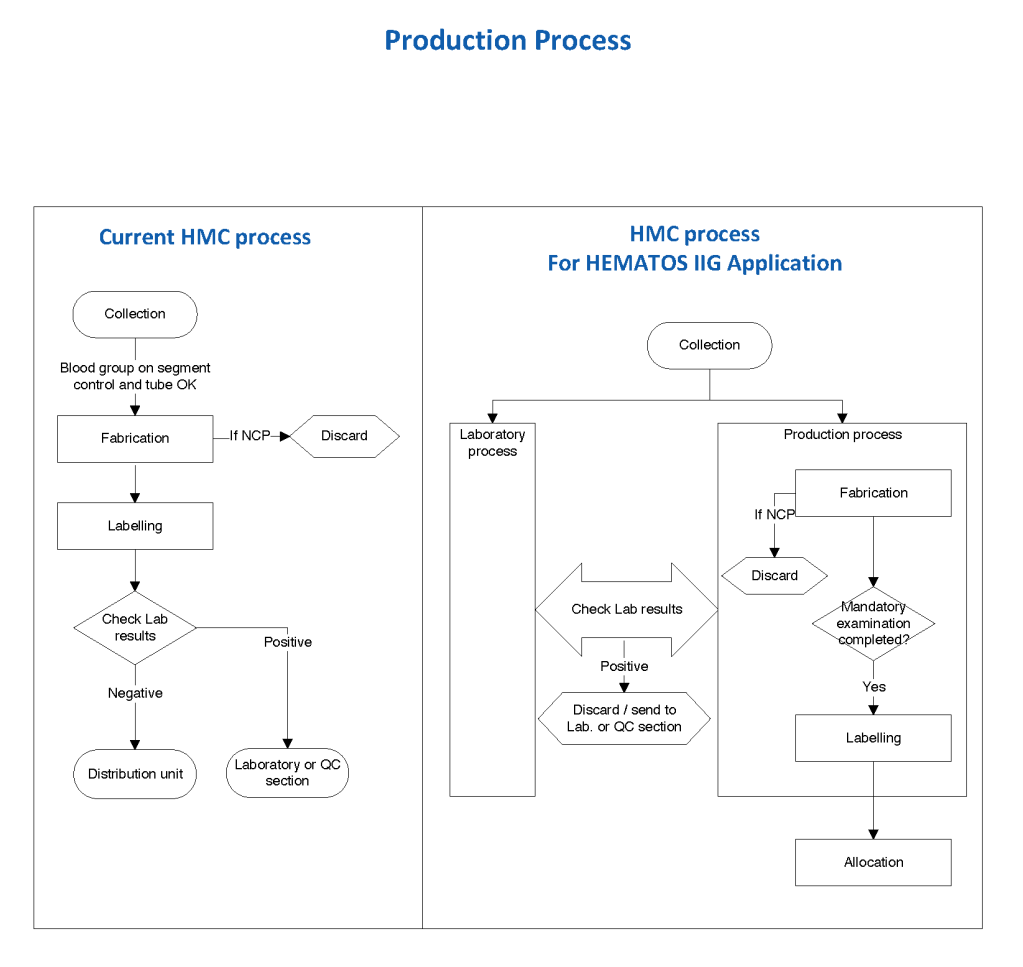
As with each major area of Transfusion Medicine, a current state is captured.  From this, a future state overview is then developed.

At this time, the client should study his current state and the future state and see how he can bolster the critical control points and build them into the processes.

In this series of posts, we will consider:

  1. Component production by Reveos automated component processing
  2. Component production by Atreus automated component processing—replaced by Reveos
  3. Manual component processing
  4. RBC leukodepletion
  5. Platelet pooling
  6. Mirasol pathogen inactivation for platelets and plasma
  7. Platelet production with platelet additive solution PAS
  8. Cryoprecipitate and cryo-poor plasma production
  9. Labelling

The example of current and future state shown is what Medinfo and I built for HMC Doha:

To Be Continued

1/9/20

Basic Hematology Fellowship Rotation in Transfusion Medicine

Objectives:

  1. Donor Center
    1. Donor eligibility criteria
    2. Whole blood collection
    3. Donor apheresis (platelets, plasma, dual-RBC)
    4. Donor reactions
  2. Therapeutic Apheresis
    1. Plasma exchange
    2. Leukocyte reduction—stem cell collection
    3. Reductive thrombapheresis
    4. RBC exchange
    5. Column-absorption procedures including phototherapy
  3. Component Preparation
    1. Preparation and release issues
  4. Transfusion Service:
    1. Blood component therapy
    2. RBC blood groups
    3. Compatibility Testing
    4. Antibody Identification and clinical significance
    5. Transfusion reactions
    6. Direct antiglobulin test clinical significance
    7. Drug-related hemolysis

Venue:

TMS Donor and Transfusion Services

Conducted by:  Head, TMS, and senior TMS technical staff

Evaluation:

Discussion of topics with TMS Head and written final examination

Source Materials:

  1. Technical Manual, AABB
  2. Standards for Blood Banks and Transfusion Services, AABB
  3. Apheresis, Principles and Practice, AABB

This is a full-time, one-month rotation—attendance in mandatory.  Vacations should NOT be taken during this rotation.

Originally Prepared for NGHA Riyadh 31/3/09

Reviewed 26/8/20

Projective Assessment 4

As a transfusion medicine physician, I must know if I can trust my staff’s interpretation of immunohematology testing.  I may be called at night and they will provide me with results and I must use these to make a medical judgment.  If their interpretation is flawed, I might make a decision that harms the patient.

I really don’t like multiple-choice questions, but nowadays this is often the norm.  For my staff, especially senior staff and those who want to be promoted to senior staff, I have developed a series of projective exercises to help me understand their thought processes.

Here is another exercise, usually given to base medical technologists.  I have the staff review this panel and tell me to interpret it:

You just can’t solve this without the enzyme panel.  Will the staff member ask for this?  Will he note that the one cell reacting is homozygous for E?  Will he ask for extended antigen typing (the patient is R1R1)?

Processes and Software Building 37: Donor Marker Testing–Final Comments

This series of the processes for donor marker testing has demonstrated the complexity and flexibility of designing processes.  In Medinfo, you can custom-design the criteria based on your local, national, and international requirements.  The end-user client must specify what he wants, and I reiterate:  Be careful what you ask for, you may get it.  Seek assistance if you are uncertain of what to use.

My criteria were based on several international standards, e.g. AABB, US FDA, CE, and Australian.  I strongly recommend you start with a set of standards and localize it for your needs.

For example, US FDA/AABB do not have a screening criteria for brucellosis since it is rare in their jurisdiction.  However, it is relatively common in the Middle East so I added a donor screening question for it.  International AABB does allow for variance with US FDA criteria so if you are outside the USA, embrace this.  The advantage of customizable software allows you do localize it to your needs.  A turnkey system, e.g. from the USA, may not allow such changes.

Finally, there are emerging pathogens that are constantly changing the donor criteria (e.g. SARS-CoV-2, MERS, SARS, Zika).  The software must be robust and allow rapid alteration to meet new donor screening criteria.  This is a constant uphill battle and requires a lot of time to keep up and validate any changes.

Complete Interim Policy on Marker Testing

For your reference, the following is the complete set of marker testing algorithms I used just before I left HMC Doha:

Definitions:

Positive result for EIA means S/CO ratio >= 1.0

Positive result for LIA means particular pattern of bands as defined by the manufacturer

Indeterminate result for LIA means presence of bands not meeting positive criteria

  1. Hepatitis B:
    1. HBsAg non-negative, then:
      1. HBsAg positive with HBsAg confirmatory positive, regardless of other results:  permanent deferral, refer to Infectious Disease clinic
      2. HBsAg positive with HBsAg confirmatory borderline or negative, repeat all HBV testing after 8 weeks
      3. HBsAg borderline:  repeat all HBV testing after 8 weeks
      4. HBV-DNA positive confirmed, regardless of other results:  permanent deferral, refer to Infectious Disease clinic
    2. If HBcAb positive, repeat after 8 weeks
    3. Repeat Hepatitis B Testing After 8 weeks:
      1. HBsAg positive with HBsAg confirmatory positive:  permanent deferral, refer to Infectious Disease clinic
      2. HBsAg positive with HBsAg confirmatory borderline or negative:  permanent deferral, refer to Infectious Disease clinic
      3. HBsAg borderline, permanent deferral, refer to Infectious Disease clinic
      4. HBV-DNA positive confirmed:  permanent deferral, refer to Infectious Disease clinic
      5. HBcAb positive or borderline with negative HBsAg and negative HBV-DNA:  review HBsAb level:
        1. If HBsAb level >= 100 mIU/mL (100 IU/L), donor may be reentered
        2. If HBsAb level < 100, then recommend to donor to receive booster HBV vaccine
          1. After HBV vaccine administration, retest after 30 days:
            1. If HBsAb level >= 100, donor may be reentered
            2. If HBsAb level < 100, donor is indefinitely deferred
      6. HBsAg, HBcAb, HBsAb all negative:  reenter into donor pool
  • Hepatitis C:
    • HCV-RNA positive confirmed, regardless of other HCV results:  permanent deferral, refer to Infectious Disease clinic
    • HCV-RNA borderline:  repeat all HCV testing after 6 months
    • HCV-InnoLIA positive, regardless of other HCV results:  permanent deferral, refer to Infectious Disease clinic
    • HCV-InnoLIA indeterminate:  repeat all HCV testing after 6 months
    • HCV-Ab positive, HCV-RNA negative, do HCV-InnoLIA:
      • If HCV-InnoLIA positive, permanent deferral, refer to Infectious Disease clinic
      • If HCV-InnoLIA indeterminate or negative, repeat all HCV testing after 6 months
    • Repeat Hepatitis C Testing After 6 months:
      • HCV-RNA or HCV-InnoLIA positive:  permanent deferral, refer to Infectious Disease clinic
      • HCV-RNA or HCV-InnoLIA borderline:  permanent deferral, HCV infection not confirmed
      • HCV-Ab positive or borderline without positive HCV-RNA or positive HCV-InnoLIA:  permanent deferral, HCV infection not confirmed
      • HCV-Ab negative, HCV-RNA negative, HCV-InnoLIA negative:  reenter donor into donor pool
  • HIV Testing:
    • HIV-RNA positive confirmed, regardless of other HIV results:  permanent deferral and do HIV-InnoLIA, refer to Infectious Disease clinic
    • HIV-RNA borderline:  do HIV-InnoLIA
    • HIV-InnoLIA positive, regardless of other HIV results:  refer to Infectious Disease clinic
    • HIV-InnoLIA indeterminate:  repeat all HIV testing after 8 weeks
    • HIV Ab positive with negative HIV-RNA and/or borderline/negative HIV-InnoLIA:  repeat testing after 8 weeks
    • Repeat HIV Testing After 8 Weeks:
      • HIV RNA positive and/or HIV-InnoLIA positive, regardless of other HIV results:  refer to Infectious Disease clinic
      • HIV-InnoLIA and/or HIV antibodies indeterminate:  permanent deferral, HIV infection not confirmed
      • HIV Ab negative and HIV-RNA negative and HIV-InnoLIA negative:  reenter into donor pool
  • HTLV 1/2 Testing:
    • HTLV Antibodies positive, then do HTLV-InnoLIA:
      • HTLV InnoLIA positive for HTLV-1 and/or HTLV-2:  refer to Infectious Disease clinic
      • HTLV InnoLIA indeterminate or negative, repeat HTLV Ab and HTLV InnoLIA testing after 6 months
    • Repeat HTLV Testing After 6 Months:
      • HTLV 1/2 antibodies positive, permanent deferral and do HTLV InnoLIA
      • HTLV 1/2 antibodies indeterminate,  permanent deferral and do HTLV InnoLIA
      • HTLV InnoLIA positive for HTLV-1 or HTLV-2: refer to Infectious Disease clinic
      • HTLV InnoLIA indeterminate, donor permanently deferred.
        • Issue letter HTLV-Not Confirmed
      • HTLV 1/2 Ab negative and HTLV InnoLIA negative, reenter donor.
  • Malaria Testing:
    • Defer donor if he has been in malarial endemic zone within the past 3 months
    • If travel to malarial zone > 3 months, do malarial antibody testing:
      • Malaria antibody negative:  no deferral
      • Malaria antibody positive, perform malarial antigen test:
        • Malaria antigen test positive, refer to Infectious Disease clinic—defer until 3 years after cessation of treatment
        • Malaria antigen test negative:
          • Plasma may be collected
          • RBCs and platelets must be destroyed.
        • Repeat malarial antibodies after 3 years:
          • If malarial antibody test positive, donor must not be used for RBC components but may be used for plasma production
          • If malarial antibody test negative, reenter donor for all components
    • Defer donor if he has received malarial treatment (not prophylaxis) for 3 years
      • Perform both malarial antibody and antigen testing:
        • Defer based on section 5.2
  • Syphilis Testing:
    • Syphilis Ab test positive or indeterminate:  do InnoLIA-Syphilis test
      • InnoLIA-Syphilis test positive:  permanent deferral, refer to Infectious Disease clinic
      • InnoLIA-Syphilis test borderline or negative:  defer for 1 year, then repeat all syphilis testing.
    • Repeat Syphilis Testing after 1 Year:
      • Syphilis antibody testing negative, reenter into donor pool
      • Syphilis antibody positive or borderline:  do InnoLIA-Syphilis test
        • InnoLIA-Syphilis test positive:  permanent deferral, refer to Infectious Disease clinic
        • If InnoLIA-Syphilis borderline or negative:  permanent deferral, syphilis not confirmed

References:

  1. Revised Recommendations to Reduce the Risk of Transfusion-Transmitted Malaria, Guidance for the Industry, US Department of Health and Human Services, FDA, Center for Biologics Evaluation and Research CBER, April, 2020
  2. Use of Serologic Tests to Reduce the Risk of Transfusion-Transmitted Human T-Cell Lymphotropic Viruses Types I and II, Final Guidance for Industry, February 2020
  3. Draft Guidance for Industry:  Recommendations for Requalification of Blood Donors Deferred Because of Reactive Test Results for Antibodies to Human T-Lymphotropic Virus Types I and II (anti-HTLV-I/II), CBER, September 2018
  4. Guidance for Industry:  Nucleic Acid Testing (NAT) for Human Immunodeficiency Virus Type 1 (HIV-1) and Hepatitis C Virus (HCV): Testing, Product Disposition, and Donor Deferral and Reentry, US Department of Health and Human Services, Center for Biologics Evaluation and Research CBER, May 2010
  5. Guidance for Industry:  Requalification Method for Reentry of Blood Donors Deferred Because of Reactive Test Results for Antibody to Hepatitis B Core Antigen (Anti-HBc), US Department of Health and Human Services, Center for Biologics Evaluation and Research CBER, May 2010
  6. Product inserts, InnoLIA-Syphilis/HCV/HIV/HTLV, Immunogenetics, Singapore
  7. Malaria Section, Australian Red Cross brochure, 2007

25/8/20