Data Entry Verification

Principle:

This policy outlines steps taken to minimize the risk of data entry errors and is based on a dualistic approach:  review of results by a senior technologist and/or supervisor and various computer safeguards built into the Medinfo Hematos IIG blood bank computer HIIG system.  This policy also discusses the verification (here called authorization) and purge processes of HIIG.

Policy:

  1. Review by senior technical, supervisory, or transfusion medical staff:
    1. Designated test procedures require review by a second technologist before authorization.
    2. Complex immunohematology testing and specimens showing aberrant results (e.g. ABO/D discrepancies) are reviewed by the supervisors or designates and ultimately a transfusion medicine physician before authorization.
  2. Computer system HIIG rules:
    1. Privileges:
      1. System restricts which staff can perform specific tests
    2. Patient/donor identity:
      1. System asks end-users to verify patient/donor identity before starting any access to the patient/donor record.
      2. System performs historical database checking and flags any inconsistencies (e.g. historical ABO/D typing differences, etc.)
    3. Testing:
      1. Only selected staff have privileges to authorize or purge.
      2. ABO/D testing algorithms require entry of reactions, not interpretation of results and are compared to a truth table.
        1. Aberrant results require special review before ABO/D typing results can be authorized/purged.
        2. D-controls must be negative to allow D typing results to be authorized for liquid D-typing reagents.
      3. DAT results require appropriate controls to meet truth-table criteria.
      4. Eluates require last wash to be negative before authorization
    4. Blood components:
      1. Selection of RBC or plasma units requires two independent sample determinations within 72 hours of each other.
      2. ABO-incompatible RBC or FFP/FP24 transfusions are not allowed.
      3. Donors with any detectable antibodies are permanently deferred.
      4. Depending on the patient’s antibody history, release of RBC units may require antigen-matched units.  Examples:
        1. Mandatory matching (only antigen negative matched units allowed—no antigen positive or antigen-untyped units):  Antibodies against H, D, c, K, k, Kpa, Kpb, Jsa, Jsb, Jka, Jkb antigens, anti-PP1Pk
        2. Priority matching (incompatible or untested can be approved by a transfusion medicine physician):  C,E, e, Fya, Fyb, M, S, s
        3. Antigen matching not required:  Lea, Leb, N
      5. Least-incompatible crossmatch require special authorization to release
      6. Protocols to force irradiation or other modified components can be setup in HIIG.
    5. Donors:
      1. Donor tests have same criteria as the same test used in patient testing for controls, etc.
      2. Donor demographics are read directly from the Ministry of Interior database—no manual entry (bar code only used).

References:

  1. Workflows for Hematos IIG (1001 through 1005), 2013-2020
  2. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  3. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

Supervisory Candidate Examination

This is the sample examination I made for the senior-most staff and candidates. This is really a projective exercise. How far can you go with this? The candidate must specify what additional information he/she needs to complete the assessment.

Name:                                                                        Badge #:

Date of Exam:

Answer the following questions:

  1. What is the ABO blood type in each of the following results:
Anti-AAnti-BAnti-A,BA1 cellsB cellsO CellsABSType?
04+3+0000 
3+03+1+4+0Neg 
3+1+3+03+0Neg 
Weak02+04+0Neg 
0004+4+4+Pos, all cells 
Weak004+4+4+Pos, all cells 
04+3+4+2+0Pos, SCIII 
Mf0004+0Neg 

ABS = antibody screen; mf = mixed field reaction

Assume that all reactions are the same by both the tube and gel methods.

In the above table, list any discrepancies in each of the testing panels.  Describe what additional tests or information, if any, are required to resolve the type.

  1. What is ABO and D typing in each of the following results?
Anti-AAnti-BAnti-DD-controlA1 cellsB cellsO cellsABS
4+4+4+3+4+4+4+Pos All cells
Anti-AAnti-BAnti-DD-controlA1 cellsB cellsO cellsABS
004+2+4+4+00
Anti-AAnti-BAnti-DD-controlA1 cellsB cellsO cellsABS
004+2+4+4+2+2+
  1. Using anti-D antisera, explain the difference in reactivity you expect between R1R1 and R2R2 cells.
  1. Describe at least two antibody specificities associated with a mixed field reaction.
  1. Describe the discrepancy noted in the following gel reaction and provide a differential diagnosis for the possible cause(s).
  1. Describe when to use Diluent 1 versus Diluent 2 with the Diamed gel cards.
  1. There is a critical staffing shortage so you are working the bench when emergency, class I blood is released (O-positive to a 25 year old male victim of a car accident).  You receive the specimen and obtain the following set of results:

Anti-A—0, Anti-B—0, A1 cells—4+, B cells—4+, ABS—3+ in SCI/II/III

What actions will you take now?  What blood type will you release for subsequent RBC requests?  Be explicit!

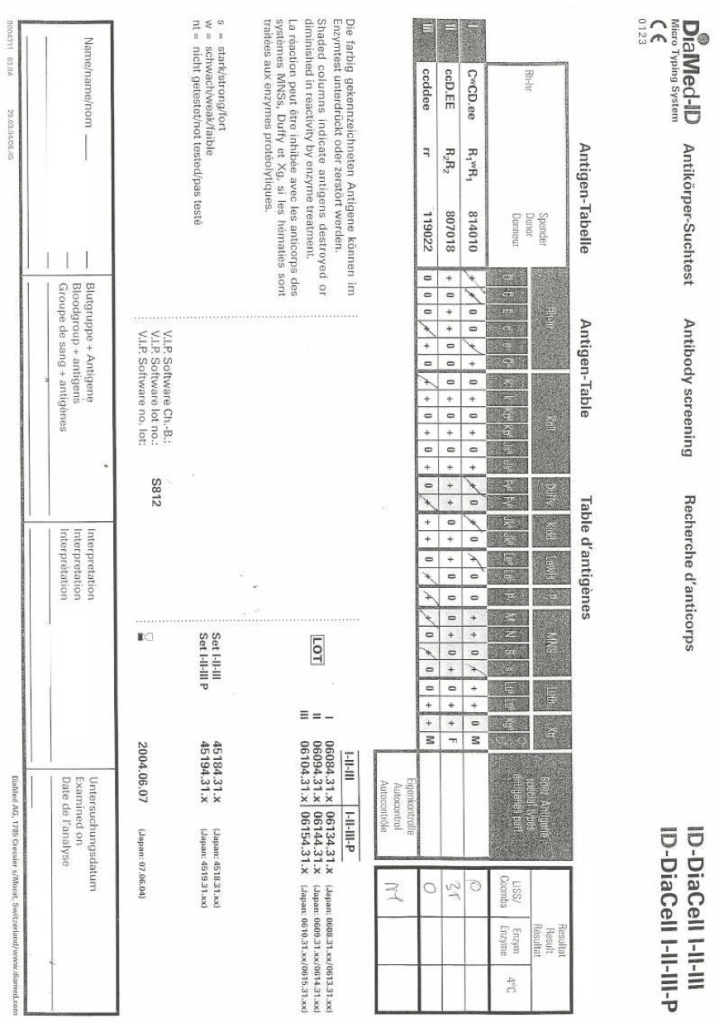
  1. An extended phenotype is ordered and Diamed Profile I-II-III cards are used.  The following results are obtained on Profile Card III:
MNSSFyaFyb
000000

Interpret these results.

  1. Describe the rationale for the prophylactic use of E-c- cells in a patient only showing anti-E.
  1. A patient develops pain at the infusion site with back pain while a unit of packed RBCs is being transfused.  The following results were obtained in the subsequent workup:

Pretransfusion DAT:  negative

Post-transfusion DAT:  negative

Hemolysis Check—post-transfusion sample—strongly positive

Hemolysis check—pre-transfusion sample—negative

Clerical Check—OK

Pretransfusion ABO/D:  B-positive—reverse typing normal

Post-transfusion ABO/D:  B-positive—reverse typing normal

Returned unit ABO/D:  B-positive

Repeat crossmatch—compatible

Give possible reasons for these findings.  What further investigations would you do?

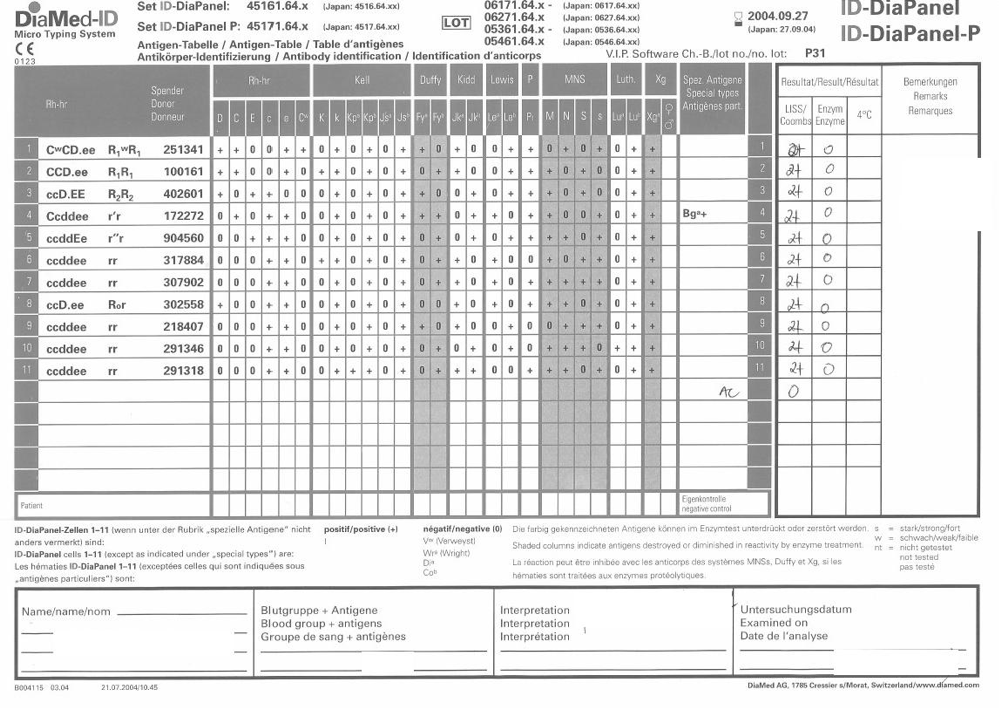
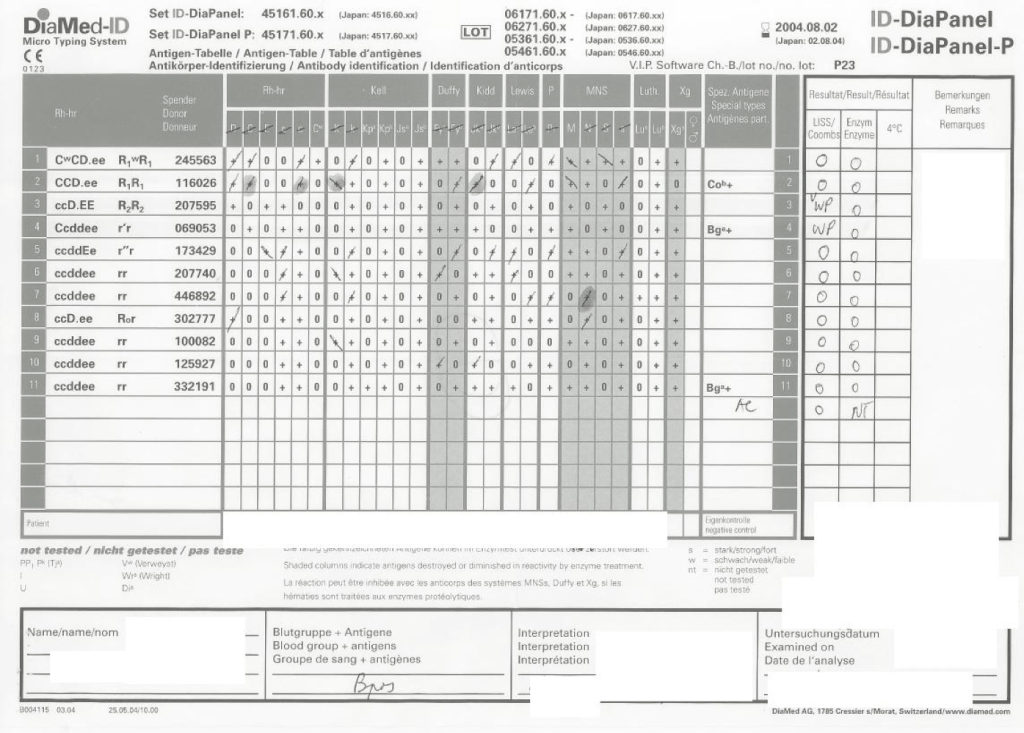
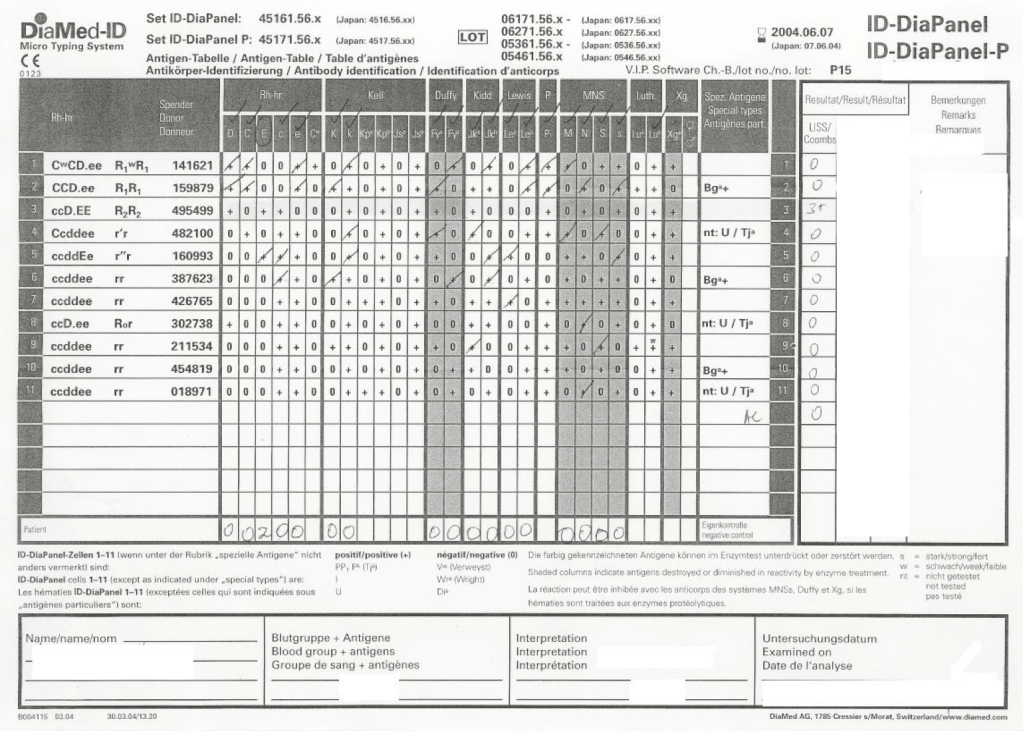
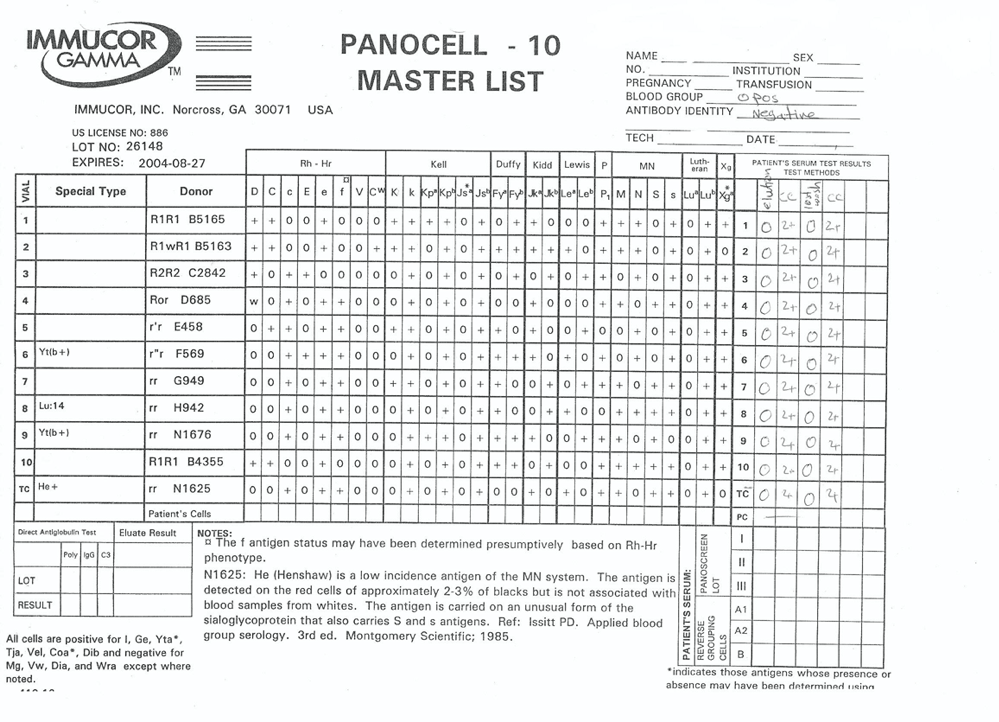
  1. Interpret the following panels:

48 year old female with septic arthritis and severe anemia (Hgb 6.9 g/dl) and positive autocontrol 2+ (Polyspecific 2+, IgG 2+, C3d nil) and negative antibody screen:

The eluate panel results follow:

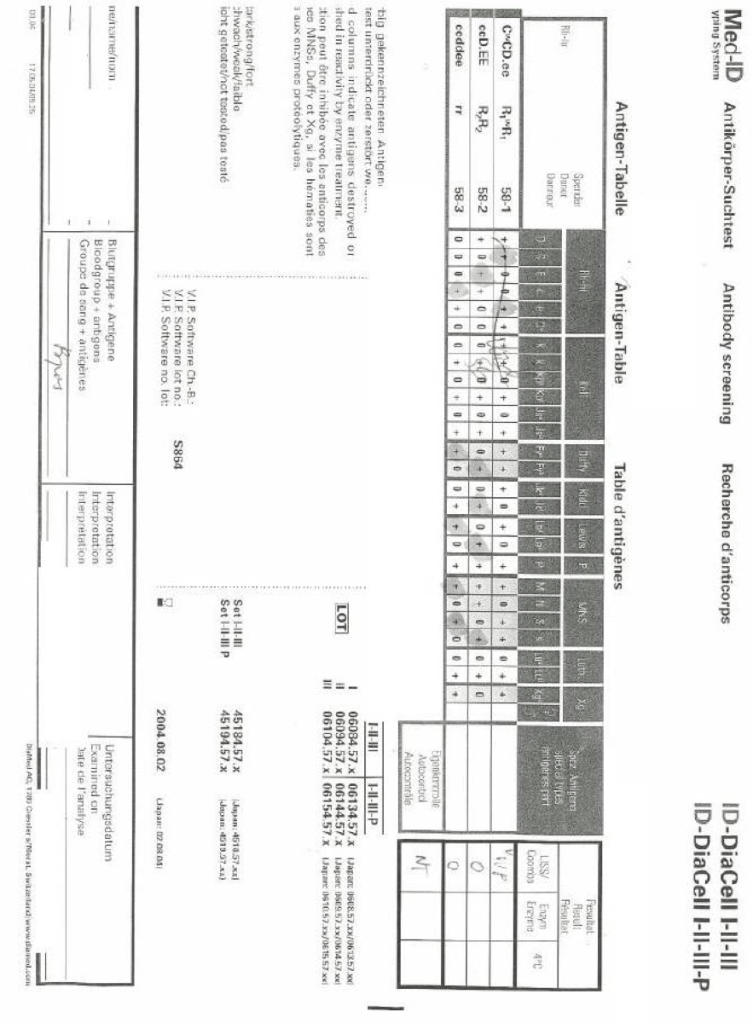
Please give your interpretation of the findings.  Be sure to specify other information you may require if any.

71 year old female with aortic stenosis admitted for surgical correction, blood type AB positive, antibody screen 2+ positive in all 3 cells, autocontrol negative, no history of recent transfusions.

Extended phenotype is:

C+E+c-e+K-k+Kpa-Kpb+Fya+Fyb-Jka-Jkb+Lea+Leb-P1+M+N-S+s-Lua-Lub+

Note:  Cell #1 reacts 2+ at LISS/Coombs using monospecific IgG IgG/Coombs Card.

60 year old male with paraplegia for surgery, B-positive, auto-control negative, no recent transfusion history:

39 year old, pregnant female—no previous history:

36 year old pregnant female, O-positive:

Interpret the panel.  What RBC phenotype would you transfuse?

60 year old male with paraplegia for surgery, B-positive, auto-control negative, no recent transfusion history:

Advice to Transfusion Medical Directors on the Selection of Blood Bank Software

Most Transfusion Medical Directors are not information technology IT people.  Still, regardless if you direct a hospital blood bank/transfusion service, a blood donor center, or both, you will still have to evaluate software for your operations.  You will probably have to sign off on the selection of a system and on the final build before going live.

This can be a formidable task, especially since none of us were trained in IT.  In my opinion, you can still do this based on your knowledge and experience and make a successful choice.

The most important thing is to KNOW YOUR OPERATIONS!!  Someone in your organization should map out all your processes, preferably as flow charts.  Optimize your manual processes.  Look at your critical control points:  How does the software enhance operations and safety?  How does the candidate system enhance security and consistency?  Does it bolster the critical control points?

My experience has been that the best software build is the one based on a good manual system.  Study the new candidates:  how do they enhance your operations?  Now reconstruct your processes with the enhanced features of the new system.

Don’t be afraid to ask for help.  Check your local resources and/or consider outside consultants if necessary.  The latter should have experience in working with blood bank systems and ideally have worked with your candidate vendors.

Human beings are not consistent creatures.  We often do not like following a series of steps in a processes, we like to skip around.  All of this is very dangerous to patient care.  The ideal system enforces consistency and integrity.  I actually like it when my staff complain that the software is merciless—they cannot take shortcuts.  They must follow each step in order!

Choosing a module from within a laboratory or hospital information system LIS/HIS will facilitate integration with the rest of system.  However, such modules (mainly limited to hospital blood banks) do not have all the features that a dedicated blood bank software has  For example, will they prevent release of unphenotyped or Kell-positive units in a patient with anti-Kell?

If you choose the dedicated system option, you must determine if a functioning interface to the LIS/HIS exists.  If not, what is the time frame to make the connection?  Very importantly, check that your specifications are actually built into the interface.  Almost every LIS/HIS vendor says that they can make an interface, but are they communicating what you need?  If you talk English and they answer you in Sanskrit, are you effectively communicating?

I prefer a dedicated blood bank system for both patients and donors, especially one that allows you to create rules to handling different situations like electronic/computer crossmatch, irradiation, etc.  Integrating both patient and donor operations will facilitate operations, especially in times of disaster and product recalls/quarantines.

Make certain that there are interfaces available for your analyzers and blood production equipment (e.g. Ortho Vision Max, Reveos, Mirasol, etc.).  Check these out on a site visit.  Many vendors promise that they can communicate with your equipment, but you must verify this yourself.

You are the pilot.  Is the transfusion or donor information organized to facilitate your decision making? Is it available all on one screen?  Do you have to flip across many screens to get the information (e.g. transfusion history, transfusion reactions, DAT, antibodies, donor history, marker testing) you need?

If you are directing a donor center, you will most likely need a separate dedicated software.  Usually, donor center software does not directly integrate into the LIS/HIS.  However, at least your patient hospital blood bank module must be able to read your ISBT labels properly.

I recommend a visit to a site comparable to your current operations.  Look for ease of use, response time, and talk privately with the end-users at the site.  Ask your IT staff to help you select a site that uses the same operating and database software (e.g. Oracle) as you will be using.

How readily can the system be modified for new practices?  With COVID-19, SARS, ZIKA, etc. there have been many changes in regulations in a short time.  How long will it take your vendor to update your system?  Is the system compliant with your local regulations and international accreditation standards?

Structurally, the optimal system is one that is a framework where almost all changes can be handled by changing settings or parameters.  The underlying structure does not change so this facilitates making the modification.  There is no need to “hard code” the changes.  You are not writing a new software structure.  Warning:  many blood bank softwares do not have this framework or flexibility—it takes a long time often even to make minor changes or updates.

Using blood bank software is like playing with fire.  Defects in design can adversely affect patient care.  The vendor will install the software with settings, but it is still YOUR responsibility to verify it works according to the specifications.

I recommend engaging computer-literate end-users (nurses, doctors, medical technologists, recruitment staff) .from the very beginning of the actual software build.  These staff can become Super Users to handle minor issues and train other staff and can help perform your software validations.

In summary, you will have to accept the choice of vendor and the final software build.  Find resources to help you with these tasks.  Never forget that what you are doing could adversely affect patient care if you are not vigilant!

4/11/20

Blood Bank Software is Dynamic, NOT Static

I was recently talking with one of the hospital software system administrators from my previous site.  He had originally worked on building the Medinfo system, but was then reassigned to the laboratory modules of the hospital information system.

His alarming comment to me was that the Medinfo build was completed so there was no need to worry about it now—it was finished.  I guess he was looking from the perspective of the general laboratory software.  There is no need to make major changes to the build, just update interfaces and troubleshoot.

I was surprised.  He had no idea of how many times we have to update the structure for new rules and regulations, and changes in blood bank practice—let alone emerging pathogens such as ZIKA, dengue, Chikungunya, and most recently, COVID-19.

My daily morning routine was to survey several blood bank websites with changes to blood donor criteria including US FDA CBER, read the transfusion journals (Transfusion, Vox Sanguis, etc.), AABB, and ASFA.  If there were any changes pertinent to our organization, I had to make interim policies and procedures, and finally prepare specifications for changes in the Medinfo software.

The Medinfo engineers would prepare flow charts of the proposed changes and implement them in a test environment for the Super-Users to test.  I had to prepare validation protocols for the testing, and then review the validation results and finally approve the adoption of the changes.

I cannot remember even a month going by without some revision in the donor protocols.  When COVID-19 came, I had to prepare a parallel, but separate, processing and allocation/release system.

This was a never-ending story that kept the Super Users and the local Medinfo engineers busy.  I always reminded the hospital information system staff that playing with blood bank software was like playing with fire:  there is a good chance you will get burned if you do not set it up properly.

31/10/20

Opinion: International Perspective

In all my years practicing medicine outside the United States, I have come to appreciate working with a diverse group of health care professionals from many countries and cultures and with many different primary languages.

I learned that there are many different international standards and not all agree with each other.  Yet, despite the apparent contradictions, they all work to improve patient care and were generally successful.  It made me reconsider my roots and think less dogmatically and be willing to learn from other perspectives.

This applies in many ways.  First, which English should we use?  Most people are at least somewhat aware of American English, but there are differences with British, Australian, and international English—even the term “blood bank” may have different meanings:  is it a hospital transfusion service, is it a donor center, or some combination of the two?

I have worked at many sites where I was the only person native in English.  I always tried to conceive how difficult it could be for someone non-native to understand and communicate in a highly technical and highly Germanic structured language.  I considered the scenario where I had to work in another language exclusively and perform all my tasks—I highly respect my staff having to cope with this.

English technical writing includes a lot of passive voice, subjunctive mode, perfect tenses, and participles.  How formidable a barrier are these to staff whose native languages may not use these structures?

I am not saying that English is the best language to perform the work in, but it is most prevalent one so everyone must cope with it.  I told many of my staff to learn German to better understand English grammar.

What bothers me is that certain software vendors and visiting lectures send speakers and staff who ONLY think in American English and American culture.  I can think of several anecdotes:

One speaker was talking about hyperlipidemia and used non-SI units.  He kept stating cholesterol > 200 and LDL-cholesterol > 120 to an audience who only used SI units.  Could the audience quickly convert to cholesterol > 5 and LDL > 3?  Did they know what a temperature of 104 F was 40 C?

Another speaker for a software company used an analogy of collecting maple sap and making maple syrup—in a presentation in the Middle East.  How many in the audience even knew what maple syrup is?

In building a series of software modules, some company staff used 24-hour clock and others used 12-hour clock.  It was chaos trying to define a 24-hour interval between the different modules.

Finally, I think of the Aesop’s fable about the mother who gave birth to a very ugly child, but to her, he was the most beautiful child in the world—so much so that she entered him into a beauty contest.  Well, each of us is the “mother” to our documents and memos.  The writing looks good to us and is perfect, but do our staff interpret it the same way we do?

I had my staff read my documents and then explain back to me what I was trying to say.  I was shocked at the differences in many cases.  After this, I always included a validation step to have other people read and interpret what I was saying—and correct any misconceptions in the writing before I finally released the document.

In summary, it is a whole new world outside the United States.  Don’t assume everyone thinks the same way or uses the same criteria to accomplish goals.  Be open to this and you will have a rewarding international career.

30/10/20

Document Specification

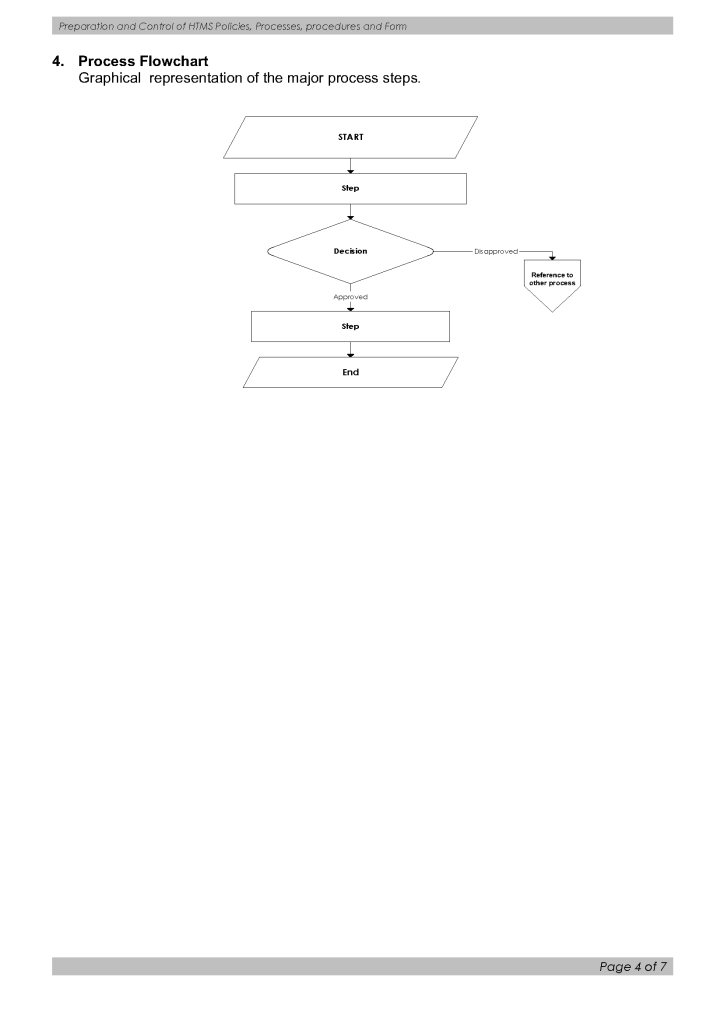
There should be a clear specification of how to prepare documents (policies, processes, procedures, and forms for Transfusion Medicine. The following is a draft document prepared by Transfusion Quality Management and myself for HMC in Doha. I want to thank Ms. Editha Durante, then Quality Manager and Quality Reviewer at HMC for all her work on this.

29/10/20

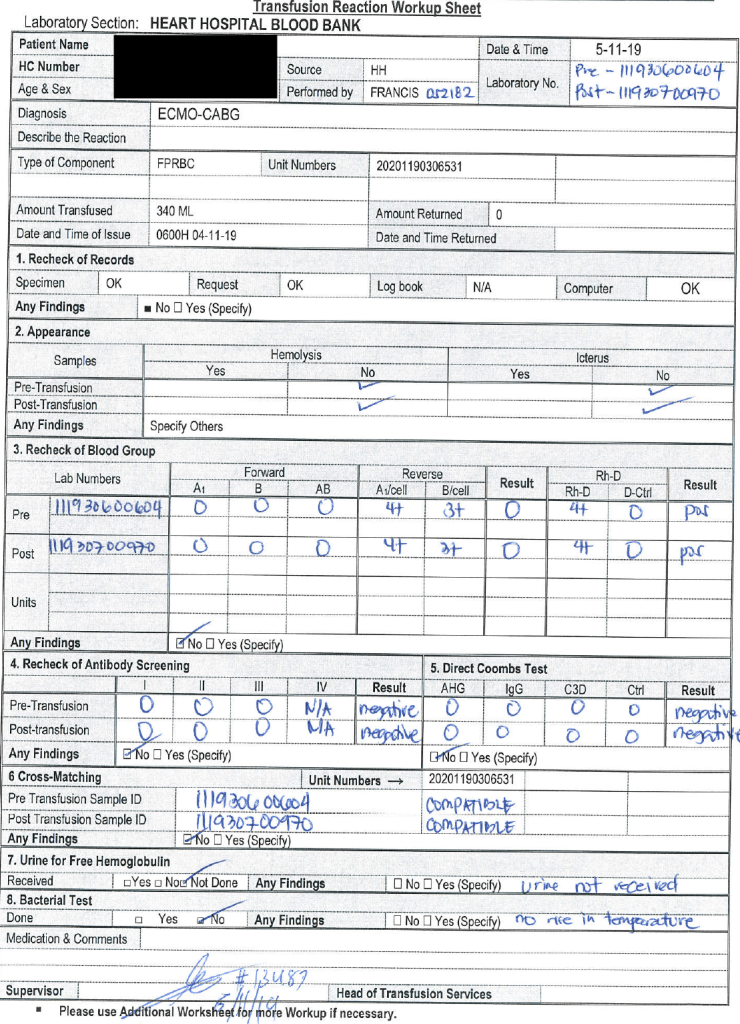
Transfusion Reaction Manual Data Collection Form

In my opinion, the key to using data effectively is to organize it efficiently.  A modern blood bank software like Medinfo is a great help;  however, a good manual system—if nothing else but a manual form during a computer downtime—is essential.  Also, a good manual system allows you to build an even better software!

Over the years of my practice at sites in the United States and the Middle East, the following form has emerged.  It started as a manual reporting form and was repeatedly updated to all the changes in the AABB Standards.  At my last site, it was used as a data collection form to present to the Transfusion Medicine Physician reviewing the final transfusion reaction workup.  Antibody results, elution, microbiology cultures, etc. would be attached as needed.  .   The actual transfusion vital signs and patient symptoms on a separate transfusion data sheet were also provided.

Like the computer system, this form enforces a consist set of testing be performed before submitting it for the final disposition for the case.  However, like all transfusion reaction workups, the transfusion physician is called with the data of the clinical symptoms, clerical check, DAT, repeat ABO/D typing, antibody screen, visual pre- and post-hemolysis findings so that within one hour the physician can rule out life-threatening hemolysis.

In a future post, I will explore the data entry and interpretative reporting performed in Medinfo.

26/10/20

Processes and Software Building 55: Manual Stock Entry

At times of disaster, it is crucial to know the blood component stock at each location.  In Medinfo, it is very simple and fast (measured in seconds) to display information by location, outdate, type, etc.  It can also enumerate stock in preparation at the component preparation sites.

To manually accomplish this, it took plenty of phone calls and a lot of staff to count units—staff that could be better deployed with handling the emergency.

SOP:  Cumulative Stock Inventory Using Medinfo

Principle:

The Medinfo HIIG computer system can calculate the inventory of various blood components at any site or within transit dynamically upon request.  THIS IS HIGHLY SENSITIVE INFORMATION THAT HAS NATIONAL SECURITY IMPLICATIONS!!

Policy:

  1. Access to Cumulative Stock Inventory functionality is restricted to designated staff.
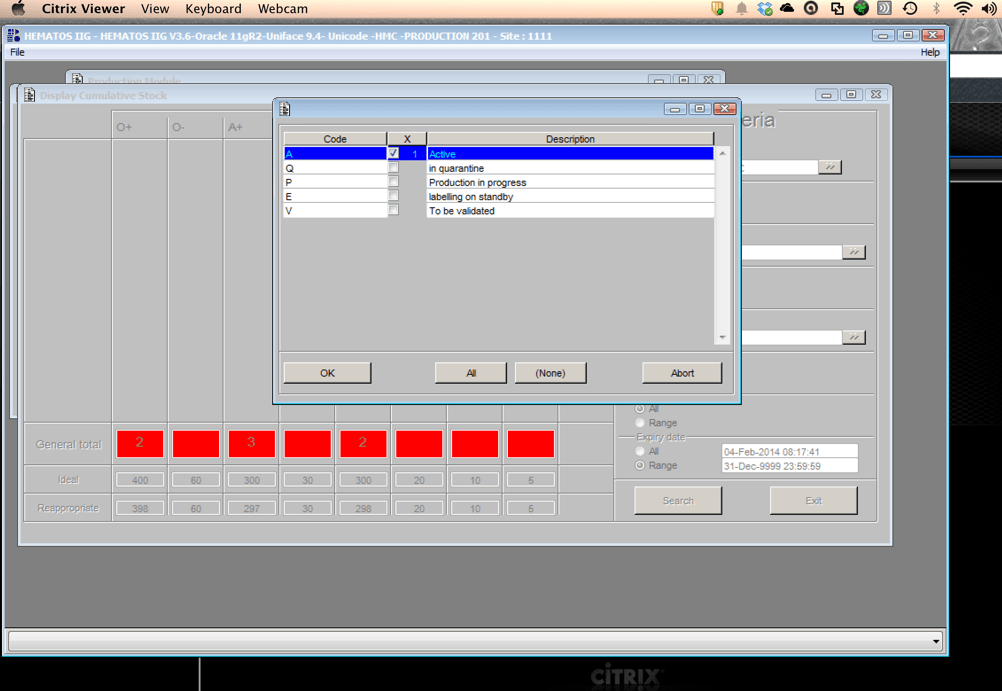
  2. The total number for any search will include stock of a given status (active, quarantine, etc.)
  3. Inventory levels are privileged information for Transfusion Medicine staff for planning and recruiting purposes.
  4. Release of stock levels to non-Transfusion Medicine staff must be approved by the Division Head, Transfusion Medicine, a transfusion medicine consultant, or blood bank supervisory personnel only.
  5. Active stock includes both reserved/allocated and unallocated units.
  6. For queries about specific phenotypes or modified components, stock entry (not cumulative stock entry) function should be used.

Procedure:

  • Sign into HIIG with your user name and password.
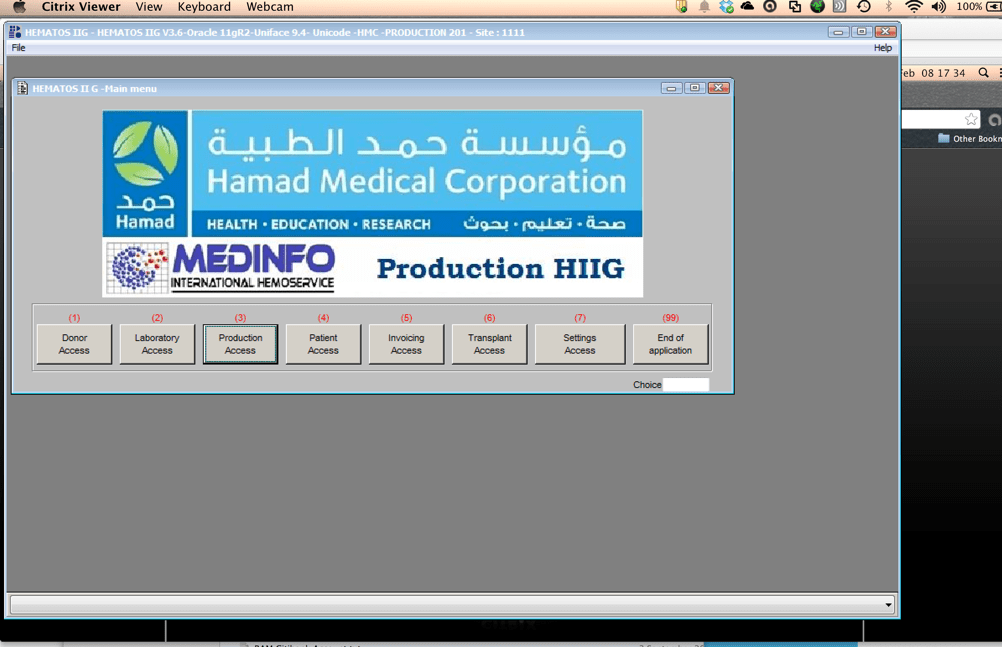
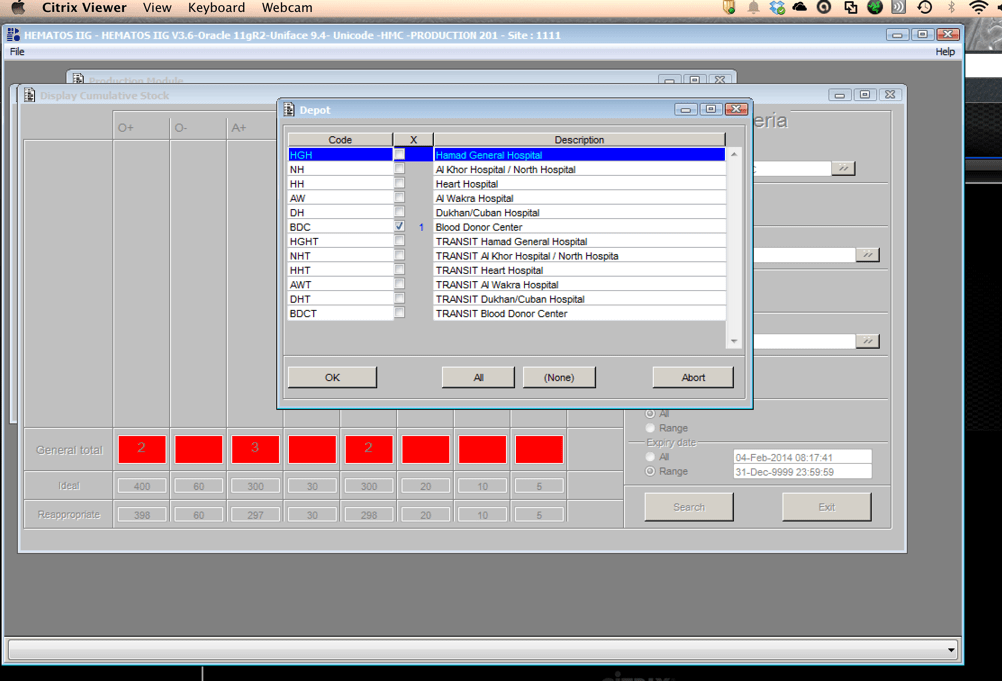
  • Select Production Access:

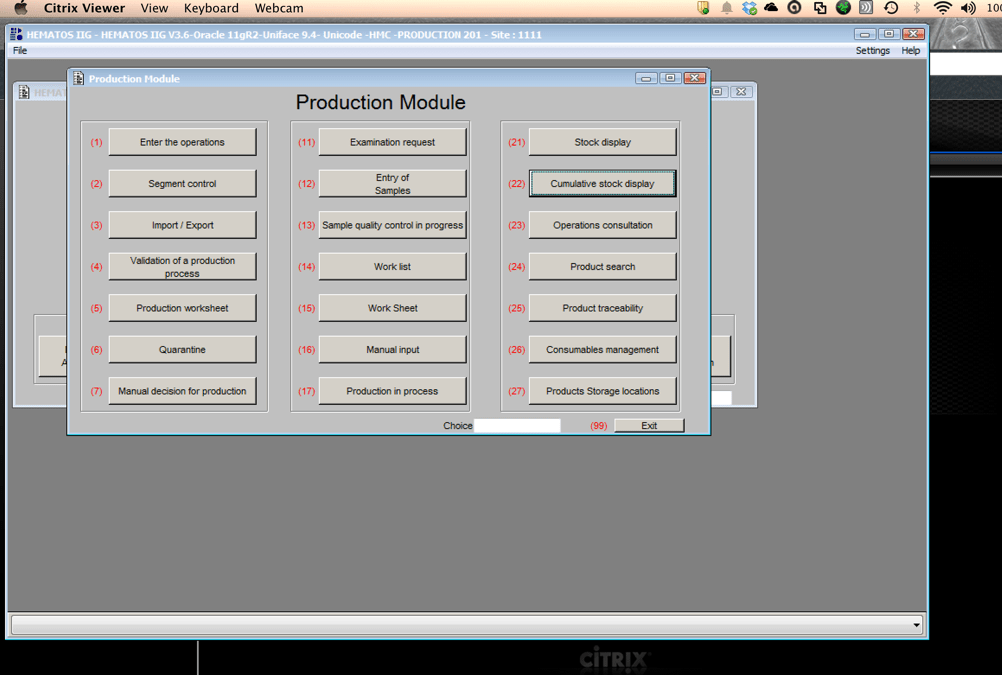
Then select Cumulative Stock Display:

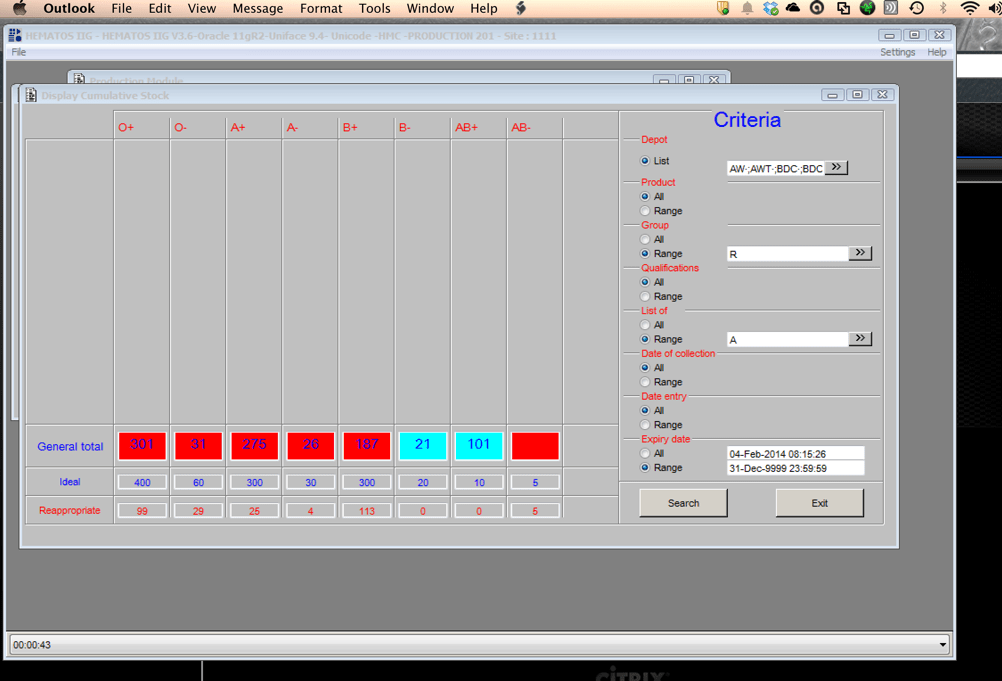
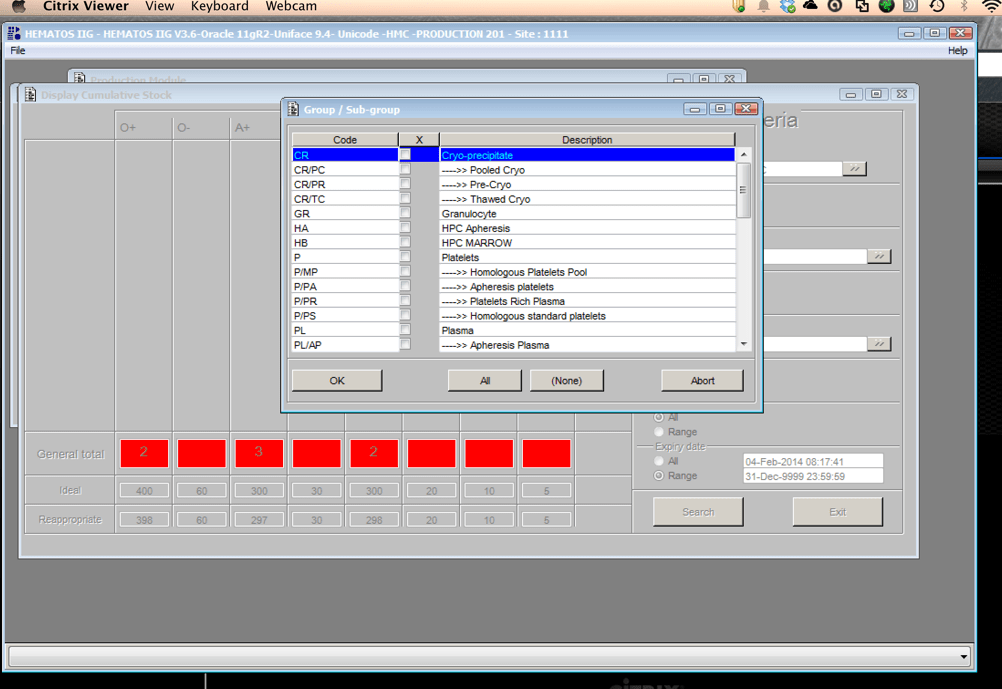
The Display Cumulative Stock Screen will appear:

  • Select your criteria (depot, product, group, qualifications, list, date of entry/production, date range, expiration date).
  • Then press the Search button.
  • Exit the program using the Exit button.

Sample options follow:

25/10/20

Minimizing Plasma Wastage

Principle:

Plasma products (FFP, FP24, thawed plasma) are only available in limited quantities so wastage must be minimized.  Thawed plasma has full factor activity for 24 hours; after 24 hours, all factors are still present at near normal levels except factors VIII and V.  AABB Standards permit continued usage of thawed plasma stored between 1-6 Celsius as the component, “thawed plasma” for 5 days.

Thawed plasma may also be prepared directly at the time of production (i.e. without freezing) for certain cases (MTP, liver transplant protocol, plasma exchange) to shorten the release time.  It is called liquid plasma since it was never frozen but should be considered equivalent to thawed FP24 if used within 24 hours or thawed plasma if used between 24 and 120 hours.

Liquid plasma, as we use here, is prepared directly from plasma treated with Mirasol and generally used within 5 days;  however, in Medinfo HIIG, this plasma may have an outdate of 26 days in accordance with 21CFR610.53, but it is not used beyond five days except if approved by the Senior Consultant/Division Head of Transfusion Medicine.  Since it is used within 5 days, it is equivalent to thawed plasma.

Definitions:

Responsible blood bank physician: specialist or consultant physician on-call at the time the discrepancy is detected

Policy Details:

  1. Plasma is dispensed without regard to the Rh(D) of the donor.
  2. Check if thawed plasma or liquid plasma (<5 days) is available first.
  3. Do not thaw plasma until the clinical service is ready to transfuse it.
    1. Tell clinical service to contact transfusion service 2-3 hours before intended transfusion time.
    2. Exceptions: liver transplant surgery, massive transfusion protocol, therapeutic apheresis, class 1 emergency requests
  4. If thawed plasma or liquid plasma is kept in the blood bank but not  used:
    1. Reassign to another patient of compatible ABO type as thawed FFP/FFP24 if < 24 hours post-thaw or <24 hours of production if liquid plasma (see attached table).
    2. If thawed > 24 hours or liquid plasma between 24 and 120 hours post processing, reassign component as thawed plasma and use for up to 5 days.  It is preferable to use thawed plasma < 24 hours old for neonates.
  5. Thawed >120 hours post-thawing and/or liquid plasma > 120 hours post-production should be discarded.
  6. Plasma usage and wastage will be monitored and reported to the Transfusion Committee.

Note:

Thawed plasma released from transfusion service should be discarded if returned.

References:

  1. Technical Manual, Current Edition, Bethesda, MD, USA
  2. Standards for Blood Banks and Transfusion Services Current Edition, AABB, Bethesda, MD, USA
  3. 21CFR610.531(c):  Whole Blood and Blood Components Storage Temperatures and Dating Periods, Current Version

PERMISSIBLE FFP/FP24/THAWED PLASMA SUBSTITUTIONS

PATIENT BLOOD TYPEUSE THE FOLLOWING:
  
OALL BLOOD TYPES
AA or AB
BB or AB
ABAB

24/10/20

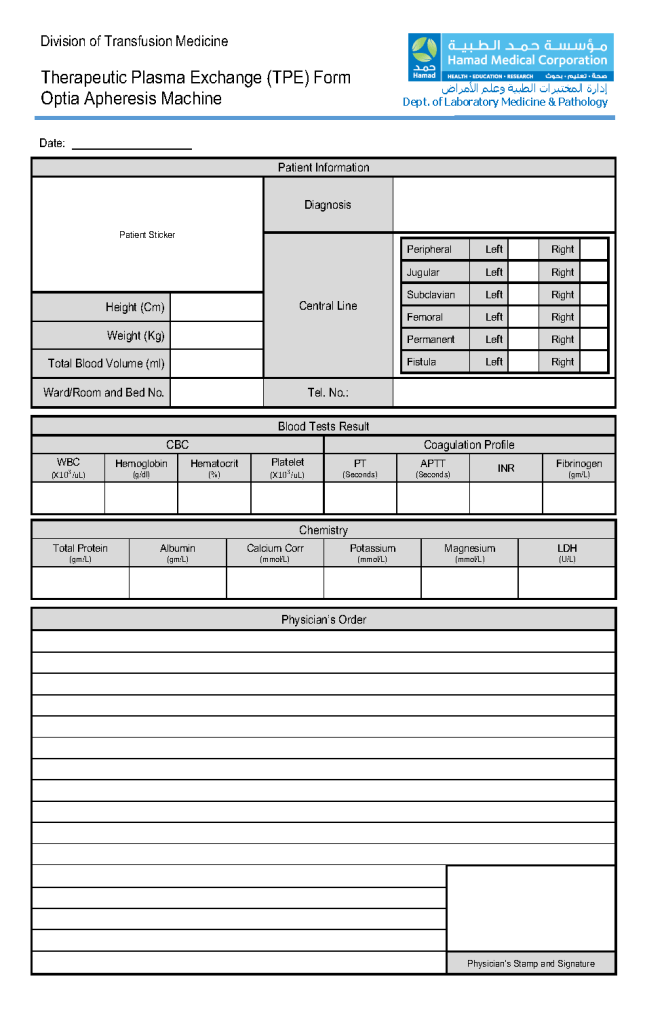
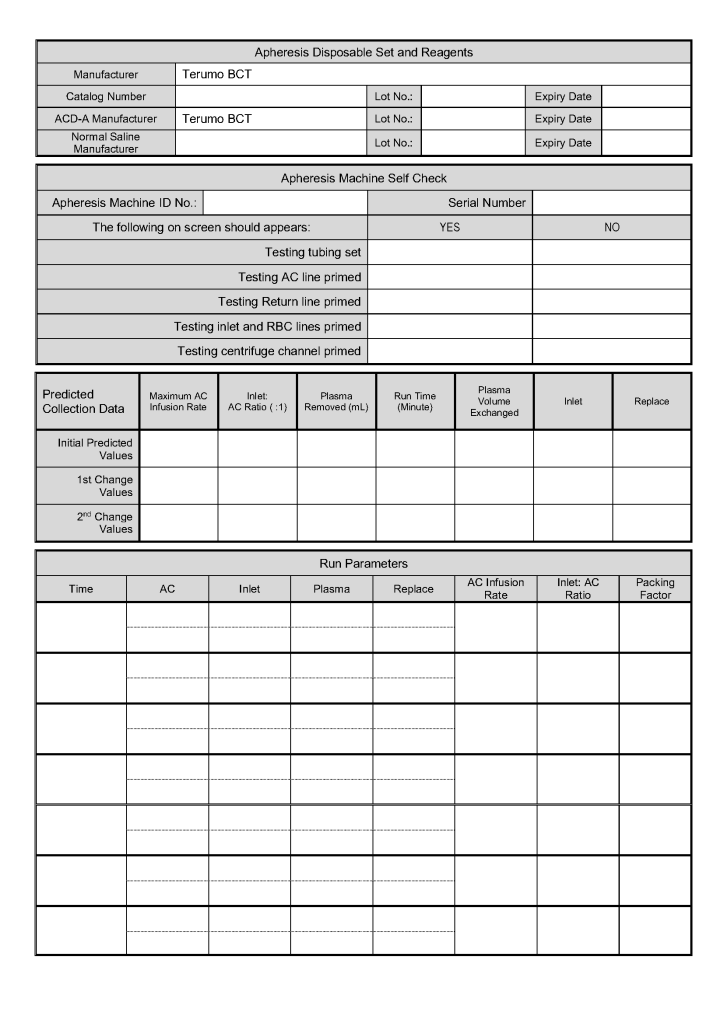
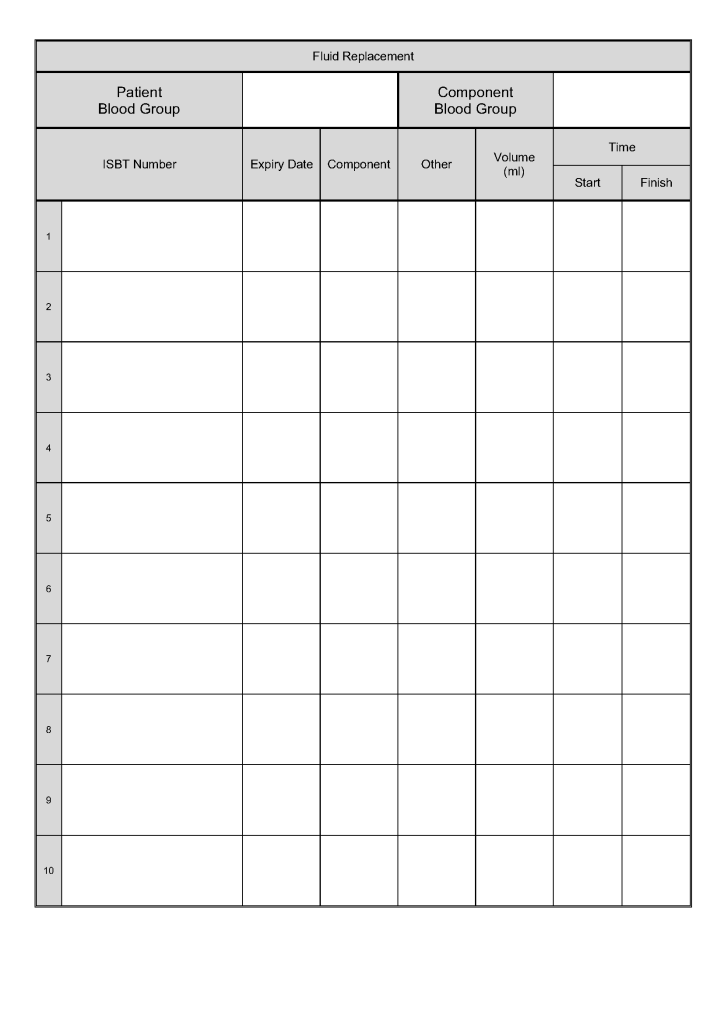
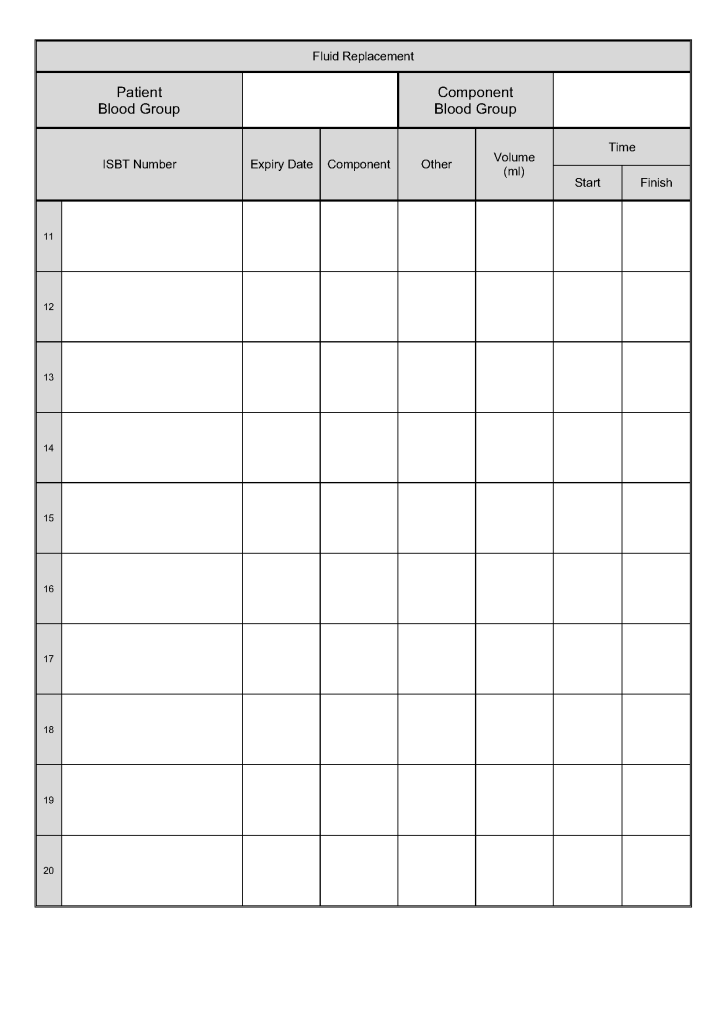
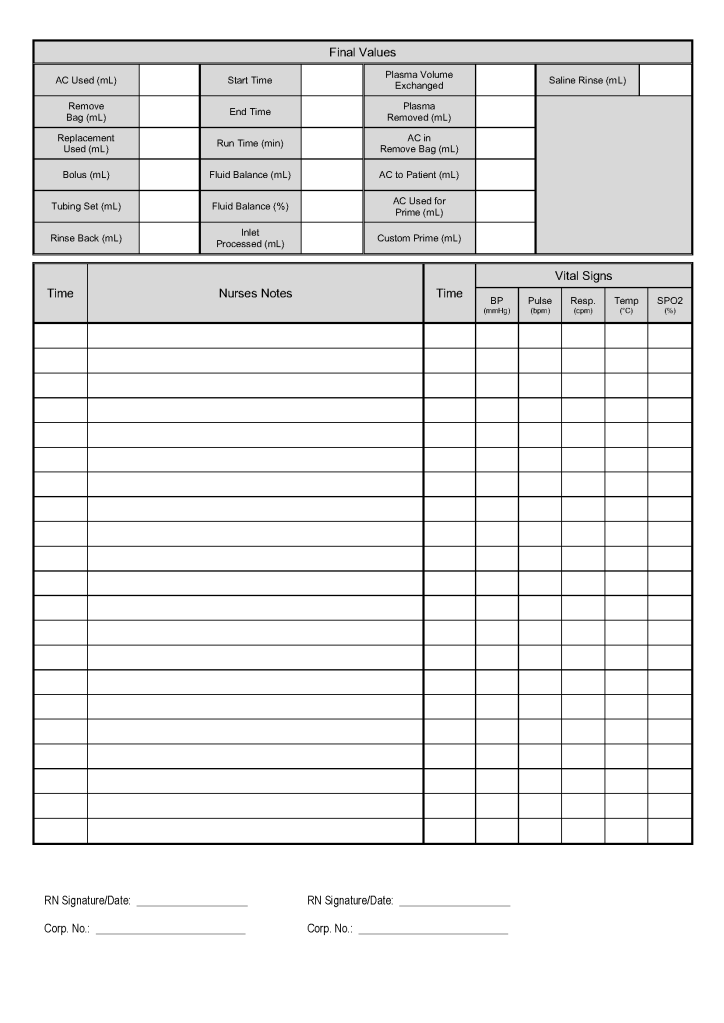
Therapeutic Plasma Exchange Apheresis Form

The apheresis nurses provide critical support to critically ill patients by performing various therapeutic procedures, especially plasma exchange. Not only does the nurse have to administer therapy, but he/she must constantly monitor the patient and the parameters of the procedure, including the blood components and IV solutions, medications, and any intra-procedure tests.

It is important that this data is collected in a visually appealing way to maximize pattern recognition and is easy for the nurse to enter the data. He/She does not have the time to flip through several pages to record everything.

The following is example of the TPE form we used at my previous position. I want to thank Dr. Saloua Al Hmissi, Consultant Transfusion Medicine, Ms. Mini Paul, Head Apheresis Nurse, and other apheresis staff for designing this beautiful form.

In my opinion, having a good manual form is the first step to computerizing the process since the design effort ensures the staff know the process thoroughly.