












Teaching medical and technical staff transfusion medicine
Everyone is excited at the potential of using stem cells for research and therapy. Below is my presentation of the logistics necessary to get those stem collected in an orderly manner, especially in this time of the COVID-19 pandemic. It will also consider blood bank software logistics.














In my opinion, the direct antiglobulin test is the most important concept that a transfusion medicine physician or technologist must understand in interpreting complex serology patterns.
Like all other testing, the DAT must not be interpreted alone but rather in the context of other laboratory and clinical results. Still, it is very important to understand the significance of the DAT in hemolysis.
The mere presence of immunoglobulin on the RBC surface does not necessarily mean severe hemolysis. The DAT strength increases with increased immunoglobulin coating of the RBCs but does not necessarily indicate how quickly the RBCs will be cleared. That depends on the class and subclass of the antibody, whether and if so, how avidly it fixes complement, etc.
One trick question I give in my lessons to staff is, “What is the clinical significance of a negative DAT?”
In my career, I have seen severe hemolysis with either negative or weak DAT, the latter especially if there is weak C3 staining. The DAT can be negative because there is no significant antibody OR there is a highly destructive antibody causing massive hemolysis, leaving only the antigen-negative cells (and in that case, there is still the possibility of innocent bystander hemolysis).
I show them the following case of an ABO-incompatible acute hemolytic transfusion reaction:
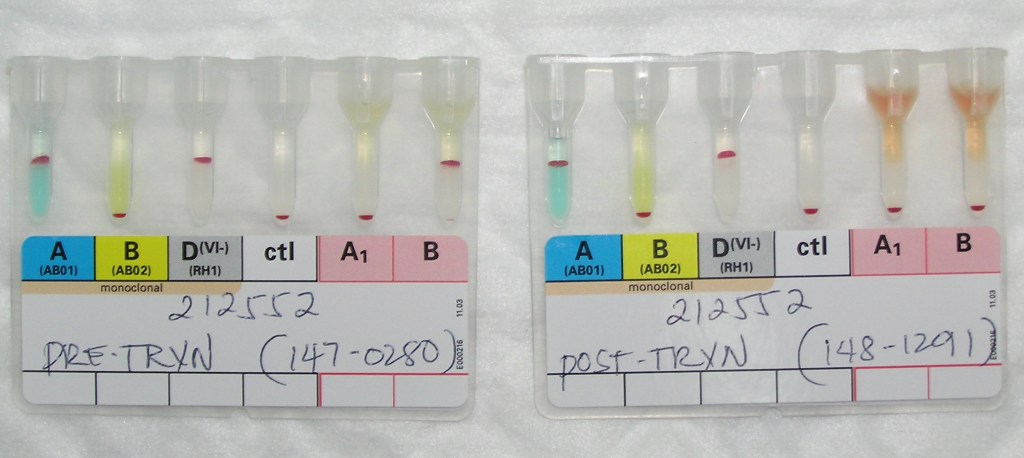
In this case, a group A patient received a group B RBC unit intended for a patient with a similar name who was group B and was in a bed next to him.
Notice the patient’s complete loss of the reaction to group B cells in the reverse type and the supernatant hemolysis. The DAT was negative. The transfused B cells were not even present in the post-transfusion gel.
Here is the urine specimen from that case showing gross hematuria:

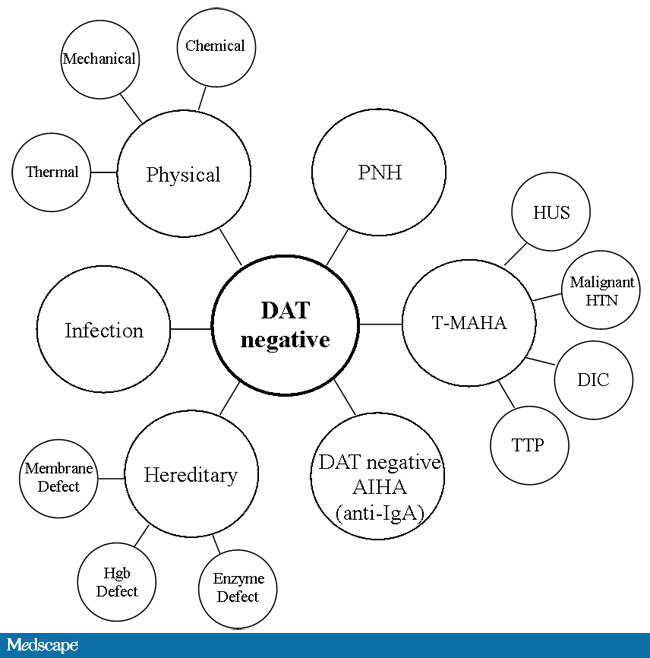
So, in severe, life-threatening hemolysis, even antibody-mediated, you may have a negative DAT. DAT negativity may also be seen in non-immune hemolysis. I will discuss causes of DAT-negative hemolytic anemia is a future post.
In summary when doing a hemolysis investigation, a negative DAT does not mean everything is all right. Everything must be interpreted in the context of the clinical and other laboratory findings.
This is a summary diagram for the causes of DAT-negative hemolytic anemia, both immune and non-immune. For immune cases, a negative DAT may indicate “not-detected” with the amount of immunoglobulin on the RBC being below the threshold of the test methodology being used. Also rare IgA associated cases will not be detected unless a specific alpha-heavy chain monospecific reagent is used.
In my career, I have dealt with many different laboratory software vendors. Regretfully, not all encounters have been straight-forward. Since ultimately these products are used for patient care, I had hoped that there would be a sacred trust to do what is best.
Things that bother me:
When I first moved overseas from the United States, I brought the perspective of my American training and experience. I saw everything in my new blood bank through those eyes.
Yet, most of my staff were not American or even North American. Few were even native in English, and most of those were not American. They had different qualifications, many of which would not have been accepted by the American schemes. Still, they functioned well.
I also worked with the US military technologist staff during Gulf War One. Some did not even have a Bachelor’s degree; yet, they performed the work well.
I used many technologies that were not yet (or never) US FDA approved such as gel or glass bead typings and pooled buffy coat platelet production. There were rare reagents I could buy off the shelf (e.g. anti-Tja/PP1Pk).
Later, I adopted pathogen-reduction technology (Mirasol), automated component production (Atreus then Reveos), and platelet additive solution. I achieve a level of good manufacturing practice that would have been difficult to achieve by the FDA-approved methods.
My perspective had changed. In the Middle East, I studied many frameworks and came to the conclusion that the best approach was to customize them to our local needs. My particular experience was to start with one framework, i.e. Council of Europe CE, and then localize it.
To do this, I could not use an American turnkey blood bank software for either the donor or patient operations. I needed a flexible system that could be customized to my needs. Again, I chose a CE-marked system, Medinfo Hematos IIG that had already been adapted to many frameworks.
It is much easier to work solely within one system such as FDA. However, if I had done that, I would have lost so much flexibility and not had a system optimized for local conditions. I would not have used Mirasol, Reveos, Diamed, and many other reagents.
One big disappointment at such international meetings is the perspective by one country’s regulatory agency that they feel its regulations and framework will work well overseas. I would wager that those people were not well acquainted with international conditions.
Another frustration was attending another international meeting in which the presenters apologized for the source of information since it came from a foreign country (France) and not their own (United States).
No country has a monopoly on what is best for everyone. To share our experiences and compare is so valuable. No one assume his way is the best. In my career, I have had the richest experiences studying other perspectives and my organizations have benefited greatly from the exchange. We can all learn from each other. We are citizens of the world.
I am attaching the US Center for Biologics Evaluation and Research CBER Guidance for Industry revision dated December 2020 to replace the one issued in September 2019.
This is a very detailed document that will require US blood centers to comply with newer more stringent safeguards to minimize the risk of bacterial contamination of platelet components.
The easiest way to comply is to universally pathogen-inactivate all platelet components: then the rest of the algorithm does not apply. I am happy that for over 10 years I have used pathogen-inactivation (riboflavin-based Mirasol, Terumo BCT) and not experienced any bacterial sepsis from platelet or plasma components.
For those of us practicing outside the USA, please note:
The US still does not permit pooled, buffy coat platelets to have either a 5 or 7 day outdate. For pooled components stored at 20-24 C, the FDA only allows a four-hour outdate, regardless what the rest of the world permits. Thus, the USA mainly uses apheresis platelets.
If you have pathogen-inactivated platelets, you are so fortunate that you don’t have to follow these other recommendations to have a low risk of bacterial contamination.
Reference:
Bacterial Risk Control Strategies for Blood Collection Establishments and Transfusion Services to Enhance the Safety and Availability of Platelets for Transfusion, Guidance for Industry, U.S. Department of Health and Human Services, Food and Drug Administration, Center for Biologics Evaluation and Research, September 2019 updated December 2020
CBER Guidance for Bacterial Contamination Guidance, Revised December 2020 (PDF)
I will be posting a detailed series about the manual and software-enhanced COVID-19 processes that I set up in Qatar at HMC Doha in March-April 2020.
In this series I will provide you with screen shots of my Medinfo Hematos IIG software design for each step in the process: collection, processing, testing, inter-depot transfer, and hospital transfusion service/blood bank release.
This GMP-compliant software-enhanced system is based on the manual system I set up in early March 2020 at HMC.
I want to thank Medinfo Hematos IIG for their rapid response to building this parallel system based on my standard processes in so short a time (two weeks) and my special thanks to the software engineering team at Vital Health Technologies, the agent for Medinfo in Qatar.
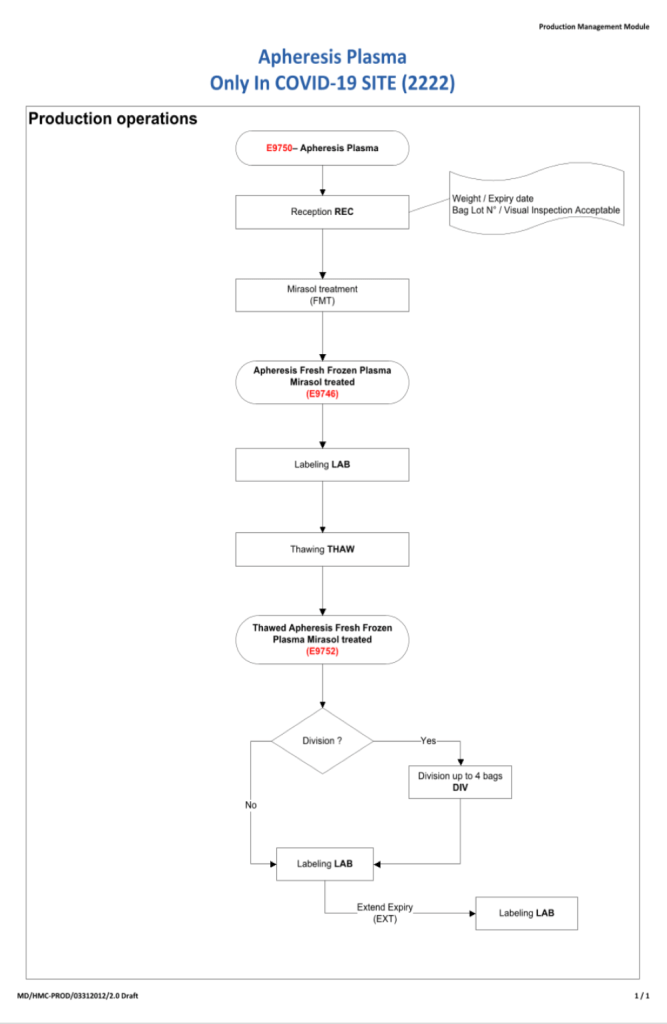
To start the series, I am providing the basic workflow for the system. As is normal in Medinfo software design, a full mapping of the processes are made. This workflow shows the new CCP ISBT codes and the quarantine collection and processing steps. The donor testing (marker and immunohematology) processes are similar to those for regular donor units.
This is basically the same process both manually and in the software. I always say:
A good software process is based on a good manual process!!
Please note the following workflow for our initial discussion.
During an AABB inspection many years ago, I observed the Lead Assessor interacting with a medical technologist at the bench. As expected, the Assessor asked in detail about the test and where the documentation and any teaching aids were located. Most importantly, the tech was asked to explain the procedure step-by-step and if they knew WHY each step was done and how the various outcomes affected the test.
In my opinion, the WHY is the most important issue. In our testing and processing, we are not baking a cake. We do not need a mindless automaton to perform the steps without knowing what they are doing. To get it right, the technologist must understand why he/she does each and everything—and what are the consequences for not following the procedure precisely. If the staff member knows this, he/she has respect for the process and is more likely to adhere to the proper method.
In my interactions with my staff, I want to engage them in the importance of their testing to the patient’s care. If they know that the result may affect the care, they may become more respectful of their work since they are part of the patient care team.
I want them to understand what each of the various results will mean to the patient, i.e. how he will be handled. I give them updates about the patient’s condition. A caring technologist is more likely to follow the steps properly. They understand that a deviation from the process may adversely affect the patient.
To this day, I often go to the technologists and quiz them about what they are doing, e.g. why do they add a particular reagent, why the incubation time is 15 minutes versus 60 minutes. I encourage them to check and recheck what they are doing if they have any doubts. Working the bench is not a quiz or examination. If they are uncertain, I want them to seek out the information, ask questions. In fact, I tell them there is no shame in saying, “I don’t know”—but be certain to add, “I will find out what to do.”
Blood bank can be fatal to those who guess. Each of us must know our individual limitations and seek the necessary knowledge. In fact, many of my assessments are open-book. They can use any resource in the blood bank or references on-line. This is real life: I discourage them from relying on memory if they are understand. Our end point is the correct action.
13/12/20
Principle:
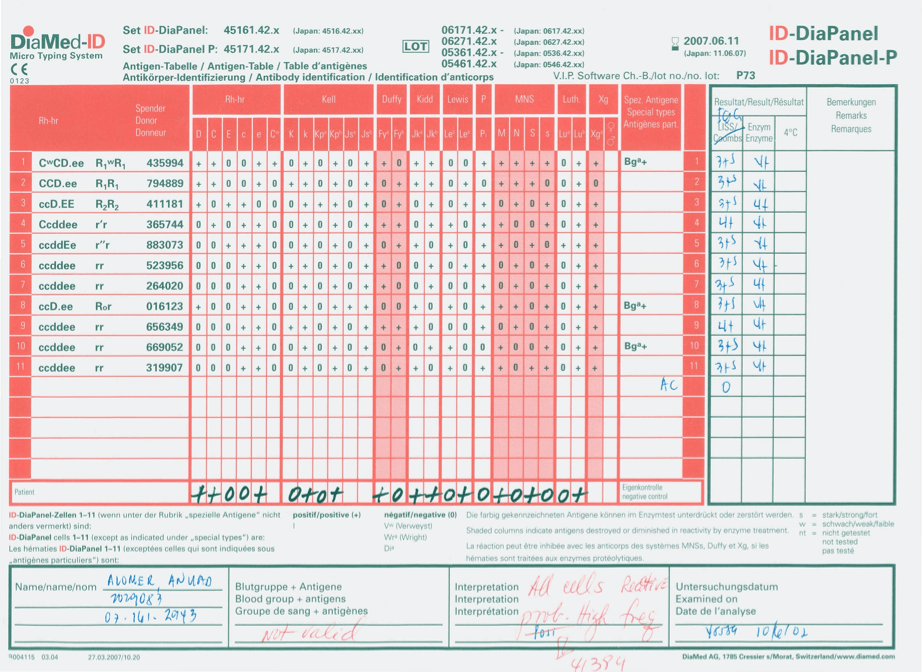
Performing antibody panels using both enzyme (ficin, bromelin, and/or papain)-treated and routine panel cells may be necessary to detect most clinically significant antibodies
Policy:
Example 1:
Antibody to High-Incidence/Prevalence or Public Antigen:
Reactions destroyed by enzyme (typical of anti-Ge2):
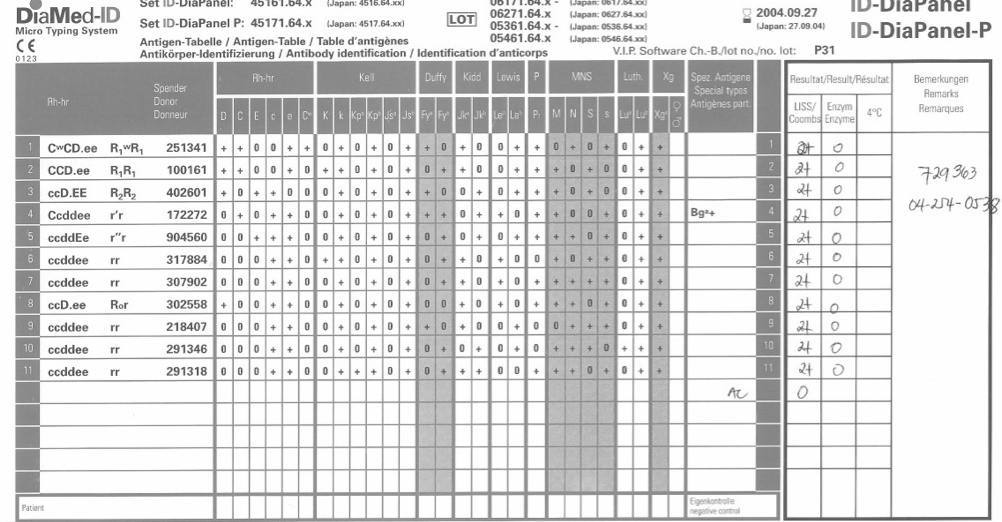
Example 2:
Antibody to high-incidence antigen, reactions unchanged or enhanced by enzyme—VERY DANGEROUS PATTERN: Examples: Anti-H, Anti-Tja (PP1Pk), anti-k (cellano), anti-U
 Dr. Zeyd Merenkov
