How I Select Technologist Candidates for Work or Promotion

As a transfusion medicine physician, I must know if I can trust my staff’s interpretation of immunohematology testing.  I may be called at night and they will provide me with results and I must use these to make a medical judgment.  If their interpretation is flawed, I might make a decision that harms the patient.

I really don’t like multiple-choice questions, but nowadays this is often the norm.  For my staff, especially senior staff and those who want to be promoted to senior staff, I have developed a series of projective exercises to help me understand their thought processes. I also used this approach on prospective candidates for hire.

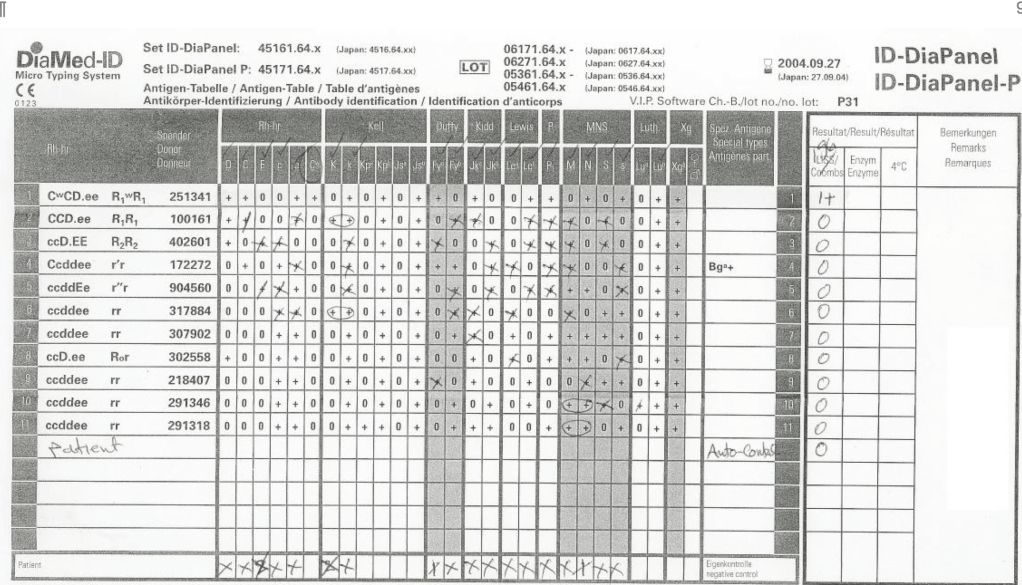
Here is a sample exercise.  I have the candidate or staff review this panel and tell me to interpret it:

Most of them answer that this is an anti-Cw without hesitation.  However, they are basing that on only one Cw-positive cell.

More astute ones indicate it might be anti-Cw but ask to test additional Cw-positive cells and perform an enzyme panel.  These are the ones that I will consider for hire or promotion now.

Product Delivery in Medinfo 1

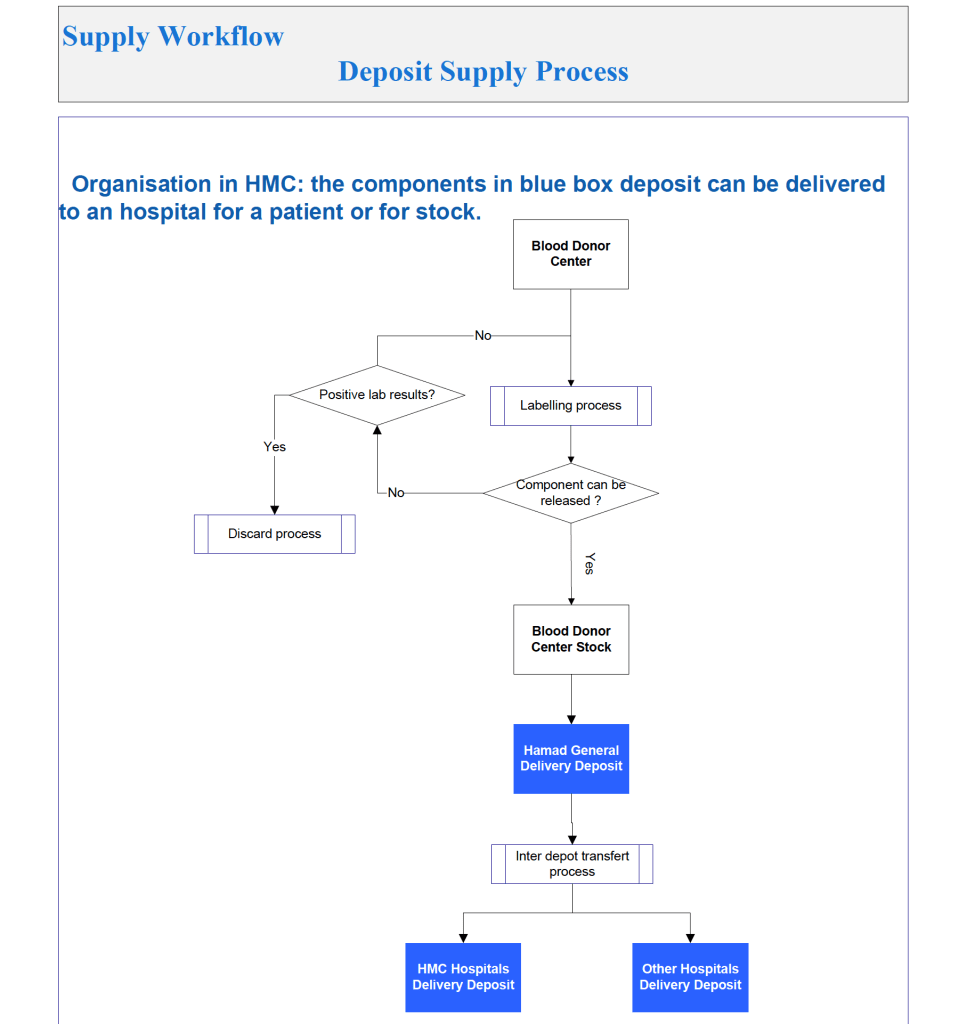
This is the start of a series of posts on how Medinfo blood bank software was designed for product delivery in the HMC system in Doha.

The overall process was:

  1. Transfer blood components (all types) from the Blood Donor using the Interdepot Transfer process (see that post for details) to the Hamad General Hospital HGH General Delivery Deposit.
  2. Release components to individual HMC system hospitals and client blood banks from the HGH General Delivery Deposit,.

It was also possible to release blood components directly from the Blood Donor Center to HMC hospital blood banks as a contingency.  Client hospitals outside the HMC system still had to obtain their components from HGH General Delivery Deposit.

Interfaces with Quantitative and Qualitative Results

Processes and Software Building Part 7

This is an update of a previous post.

Blood Bank instruments may perform tests and release test results in a numerical or alphanumeric format or both.  For example, nucleic acid and enzyme immunoassay may release a qualitative result (e.g. positive, reactive, borderline/gray-zone, negative, nonreactive).  Alternatively, the machine may release the signal to cutoff ratio (S/CO) as a numeric result.

Blood bank software may use either kind of result on which to base interpretative rules for acceptability of the donor.  The qualitative result criteria are based on the quantitative SC/O but the equipment automatically interprets this.  The S/CO ratio of 1 is the cut-off point.  Thus a value of 0.99 is negative and the value 1.01 is positive.  But is it really so clear-cut since the difference between the two is so small?  Thus, some people have added the term gray-zone for values close to but below the cutoff.  Could a value of 0.95 be an early infection?

I personally prefer to see the actual cutoff but use the manufacturer’s criteria for interpretation.  As a physician, it is good to review the S/CO on serial exams.  If a borderline or gray-zone result becomes positive, then perhaps the original result indicated early infection.  The question still remains, what is the gray-zone?  0.95 to 0.99, 0.90 to 0.99, etc.  Some accrediting schema have not used gray-zone for interpretation.

With Medinfo’s blood bank software, I could choose either option or both—or at least store the S/CO as a nonreported result for subsequent review.  I could even chose, test by test, in a series between reporting either S/CO or the qualitative result.

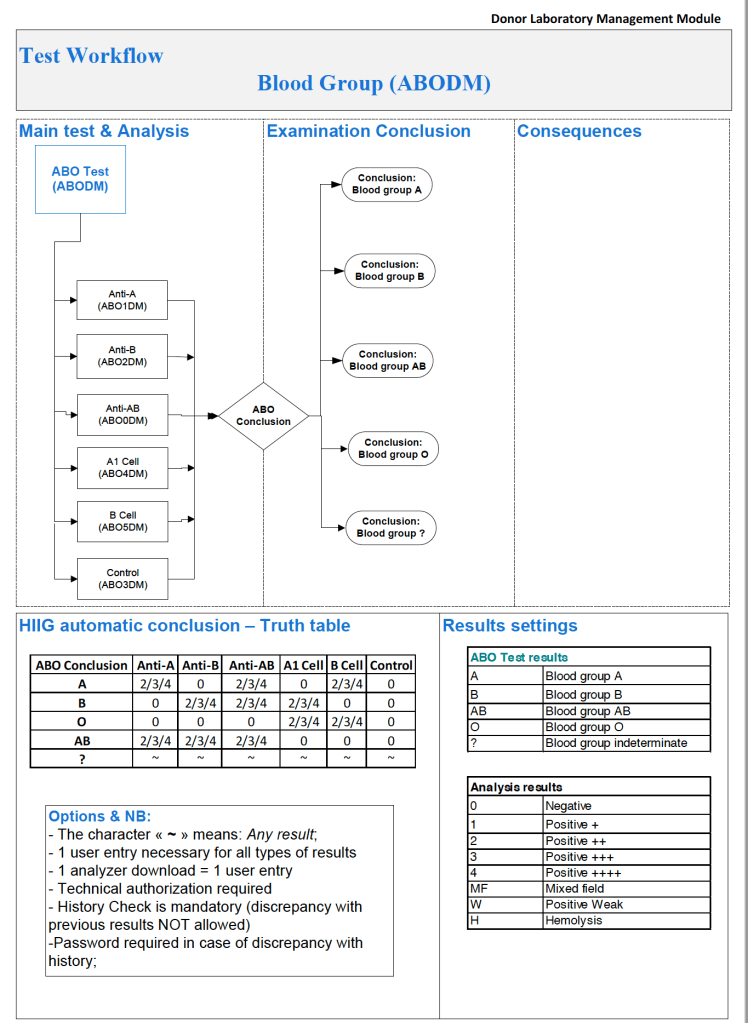
Semiquantitative results, e.g. in {0, 1+, 2+, 3+, 4+} are qualitative and could also include mixed field (mf) and hemolyzed (h).  I showed examples of this with ABO/D antigen typing in a previous post—see attachment.

On the contrary, the results from blood production equipment may include parameters such as time of preparation, original volume, final volumes for each component, platelet yield index as an indirect measure of platelet count.  When there is pooling, the final total volume is critical to determine if pathogen-inactivation procedures and platelet additive solution can be used.  This is a much more complicated interface.

Process: Donor Physical Examination

This is a sample process document for donor physical examination. Compare it to the previous post Policy: Donor Physical Examination.

5.3.1 PROCESS DONOR PHYSICAL EXAMINATION:

Process:

  1. The donor is positively identified by a designated picture ID and Hematos donor consent form with specimen/encounter number and barcode.
  2. Donor staff measures vital signs of donor and enters results into Hematos IIG.
  3. Donor staff inspects donor arms for suitable veins and checks for concurrent skin diseases and/or scarring.
  4. Medinfo Hematos IIG determines donor eligibility to collect components.

References:

  1. HMC 1001 Setting Specification, Version 1.5, Hematos IIG, Medinfo
  2. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, Maryland, USA

Policy: Donor Physical Examination

This is another example of a short concise policy statement. The process example will follow:

5.3 POLICY: DONOR PHYSICAL EXAM

Policy:

  1. All donors will be positively identified with a picture ID and by their Hematos identifiers (donor ID and session registration/specimen number).
  2. The donor’s vital signs (BP, pulse, temperature, respiratory rate) will be measured by designated Donor Center staff.
  3. The donor’s arm veins will be inspected for a suitable donation site and evidence of scarring.
  4. Donor eligibility for actual collection will be determined by the Hematos IIG algorithms based on this data.
  5. All policies, processes, and procedures must comply with Qatari, HMC, and applicable accreditation standards (i.e. AABB, CAP, and JCI).

References:

  1. HMC 1001 Setting Specification, Version 1.5, Hematos IIG, Medinfo
  2. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, Maryland, USA

Antiglobulin Reagents

Antiglobulin reagents are used to detect molecules bound to the RBC surface.  What they detect depends on their specificity.  Such detection can be performed in the routine immunohematology laboratory or elsewhere such as flow cytometry.  This discussion is for the blood bank laboratories, both routine and reference immunohematology.

This is how I classify and use the various reagents in my daily practice:

  • Routine use—DAT testing and compatibility testing
  • Antibody identification
  • Drug-related hemolysis and transfusion reaction workups
  • Special assays:  DAT-negative AIHA, prediction of clinical significance of reaction by IgG subclass determination

There are many types of antiglobulin reagents:

  • Polyspecific:  IgG and complement usually C3d but sometimes C3b specificity included
  • Whole Molecule IgG including mu heavy chains and kappa and lambda light chains
  • Monospecific gamma heavy chain, mu heavy chain, alpha heavy chain, C3c, C3d, C3b
  • IgG subclass:  IgG1 IgG3

Whole molecule IgG detects class-specific mu heavy chains AND light chains kappa and lambda.  Since kappa and lambda are found on all immunoglobulin classes, whole molecule reagents can detect IgM so there may be weak staining with cold antibodies that are not clinically significant.

C3d is the final breakdown product of C3b and does not cause hemolysis.  Its presence merely means that at some time—unspecified—complement was fixed.  C3c is an intermediate product in the breakdown pathway.  If detected, C3c positivity means ACTIVE complement fixation was occurring at the time of specimen collection.

General Use:

Routine DAT testing:

  • Polyspecific:  if positive, then use
  • Monospecific IgG and monospecific C3 reagents

Antibody workups:

Routine:  antibody screens and AHG crossmatch (if indicated)

  • Polyspecific
  • Gamma heavy-chain monospecific

Monospecific gamma heavy chain is preferred to minimize non-clinically significant, cold antibody interference.

Complicated—where detection of complement reactivity is especially important:

Polyspecific for drug-related hemolysis and transfusion reactions

Difficult antibody workups, e.g. to rule out anti-Jka and/or anti-Jkb

Specialty Reference Procedures:

  • DAT-negative AIHA:  mu heavy chain, alpha heavy chain for IgM and IgA mediated hemolysis (rare), C3c to detect active complement fixation
  • Predicting clinical significance:  IgG1 IgG3

Complement fixation may be important in various drug-related hemolysis and some transfusion reactions so I always use a polyspecific reagent in these situations.  Most antibodies can be detected by gamma heavy-chain specific reagents;  however, there are rare examples of anti-Jka and anti-Jkb which are only detected by complement.  Whenever I have a nonspecific reaction in an Jka-negative or Jkb-negative patient, I repeat the AHG panel using polyspecific reagents.  I do not use polyspecific routinely because of the nonspecific and non-clinically significant cold antibodies.

One way to assess for the clinical significance of an antibody is to determine its IgG subclass.  In general, IgG3 antibodies may fix complement and cause severe hemolysis.  Both IgG1 and IgG3 antibodies cross the placenta and may cause hemolytic disease of the fetus/newborn.

In summary, when reviewing immunohematologic reactions using AHG, I always remember to check which type of AHG reagent was used.  I always keep multiple types of AHG reagents in the laboratory for the reasons explained above.

TRALI TACO

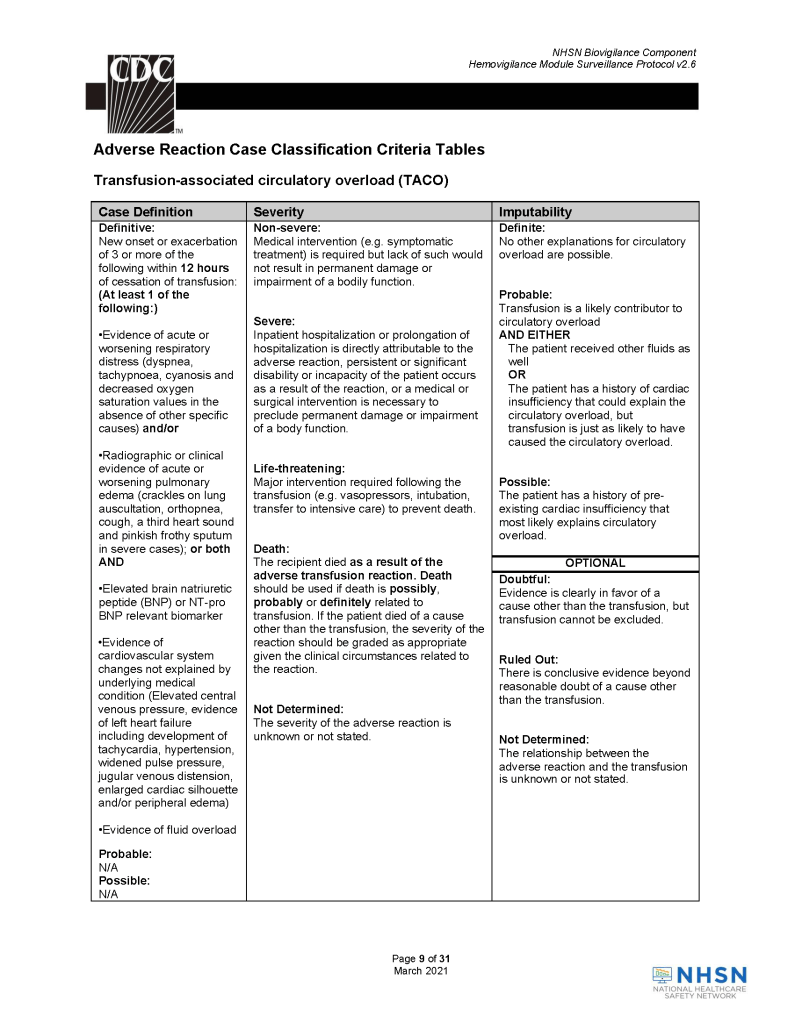
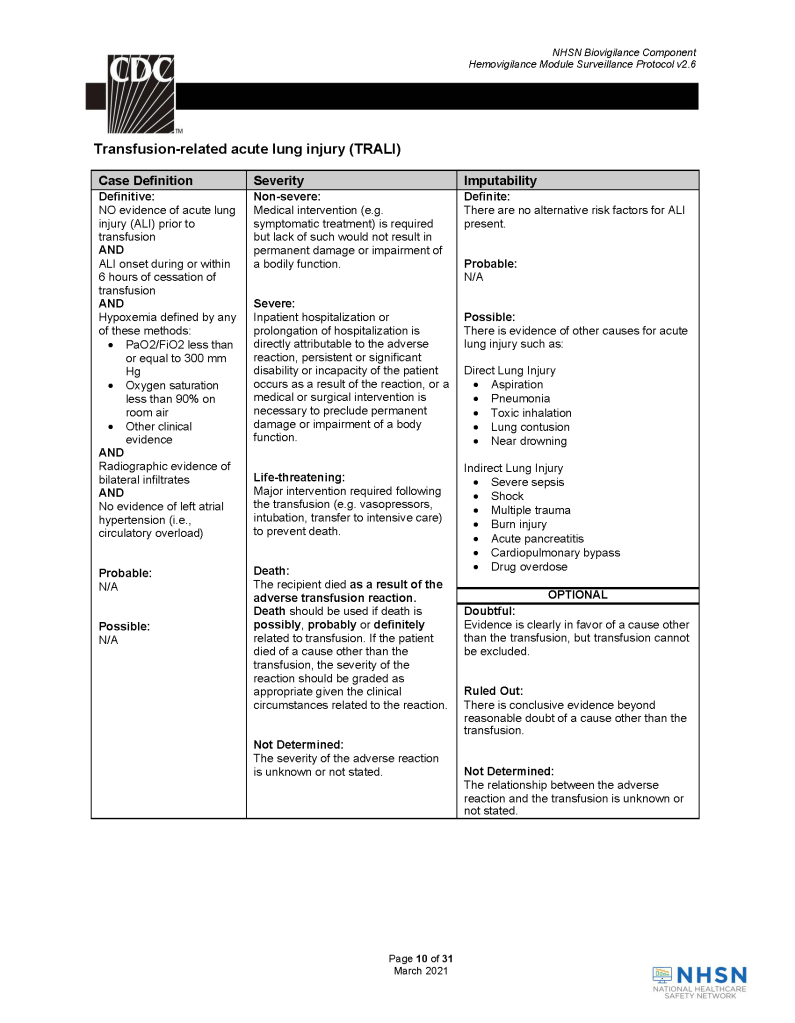
This is a revision of a previous post, incorporating an updated definition of Transfusion-Associated Cardiac Overload TACO from the National Healthcare Safety Network, Biovigilance Component Hemovigilance Module Surveillance Protocol,  Version 2.6.

Processes and Software Building 6: Interfaces

This is an updated version of a previous post.

Interfaces—General Considerations:

When buying equipment while planning/implementing new laboratory software, I originally had a rule not to purchase anything that the vendor did not have a ready interface.  Even that was not so clear since some vendors had interfaces listed as alpha, beta, and completed.

Could you use an alpha or beta interface?  Was it safe for patient care?  What was the development cycle for new interfaces with your vendor—months, years?

Even if the vendor had a completed interface?  How “complete” was it?  Did it accept all data from the machine?  Did the data stream require reformatting?  Who would write the transformational script?

Even if the vendor could support it, could your local IT organization and the local agent’s IT staff do it?  I had plenty of headaches over this.  The best equipment with the best interface that the local agent could not support was worthless to me.

Some finished interfaces took months to install because of connectivity issues.  What version of the operating system OS was used?  Was it secure?  Did our IT department accept that OS version (e.g. Windows 7) and the provided malware protection?  I have seen malware spread across a network from the interface software installed by the vendor, threatening the entire corporate system. 

Did the solution require middleware?  What were the implications of having middleware and its affect on the main software program, especially at the time of its upgrade or the main software?

I have seen vendors using Windows 2000 for their interface software as late as 2017.  It was difficult for some of them to update to current, more secure versions.  Anyway, our corporate IT department gave them all a deadline to update to the current operating system—they all complied or risked losing all connectivity to the network.

Almost every instrument vendor has told me that they can communicate with my laboratory system.  I guess that is true:  one talks in Russian and the other Sanskrit—they do communicate but is it effective?  Talking is not necessarily useful communication!

I remember one open EIA machine that had a TCP/IP port but it was not functional by the standard protocols.  One had to emulate a serial port to get some rudimentary communication.  The port’s light blinked, however.  I never imagined that someone would put a nonfunctional port as a mere decoration.

On the other hand, I have had excellent experience with another software vendor Medinfo.  Even if the vendor did not have the interface developed, they could build it from scratch in a few weeks.  Paradoxically, it was faster to build these new interfaces than some so-called already interfaces.

I must emphasize:  This is a collaborative team effort between the blood bank information system, software vendor, instrument vendor, and your institution’s IT staff.  There must be excellent cooperation between them for a successful result.

When installing the Medinfo Hematos IIG software, many of our most important interfaces (the Terumo mixed shaker, Trima, Reveos and its predecessor Atreus, Mirasol illuminator) had no developed interfaces when we started.  This was a risk, but actually those interfaces were developed in a few weeks and fully functional.  In fact, we were the first site in the world to have those interfaces working—and without any Middleware.

In general, the blood bank software vendor installed the completed interface and did some low-level testing.  Then, my blood bank computer team did the testing.  The final responsibility for testing and acceptance was with the end-user blood bank team and me as Head of the Laboratory Information Systems.

In general,  I wrote the validation protocol and assigned the tasks to the Medinfo Super Users.  To perform this testing, we still had to register donors and collect and then export the specimens to the donor marker testing laboratory before the actual interface testing could begin.  This was all done in a special test domain separate from the production domain.  The interface did not go live until the validation was completed and accepted and then was moved to the production environment.

I made the validation criteria and reviewed all data as Division Head of Laboratory Information Systems.  Representative screen shots were made.  All data was sent to me.  My final acceptance was required before the interface could be activated.

Automated component processing (Reveos) and component modification are more complicated and will be covered in a future post.

Time: Appreciating Testing and Component Release Times

This is a revised version of a previous post.

I have had many medical students, residents, and fellows rotate through my Transfusion Medicine section.  Hardly anyone has any interest in making my discipline his/her career.  It is a required rotation or an “easy” rotation during which the trainee may take his vacation.  The trainee will cram for the examination and then promptly forget it.

I left practice in the USA in 1990, in what I consider the golden age of laboratory medicine.  We had supervisors for each laboratory section.  In the blood bank, we had many staff with SBBs or who were SBB students.  We were very self-sufficient in handling immunohematology problems except for rare blood types or antibodies to high incidence/prevalence antigens.

When I returned to visit my old laboratory, I sensed a deprofessionalization of the laboratory and blood bank in particular.  Blood Bank now is a cost center, not an area of revenue.  Why hire experienced blood bankers for most hospitals?  Send the antibody workups to the Blood Center.  There are limited jobs for transfusion medicine consultants.  Minimize testing, don’t do extended antigen typings, etc.

Nowadays, I feel like one of the dinosaurs marching into oblivion like in Walt Disney’s Fantasia film, the section called The Rite of Spring.  Who will replace those retiring?  Have you ever noted the average age of attendees at the AABB annual convention?  I feel young when I go there (and don’t worry about the gray hair!)

I want to attract new doctors and scientists to Transfusion Medicine.  I really try, but most have no interest and look on their rotations as a necessary evil.

I have lowered my expectations for most medical trainees in Transfusion Medicine.  They don’t like it, they just want to pass it, and move on.  What must I impress them with for their future careers?  What is essential for them to remember?

I have had both pathology and non-pathology trainees.  Surgical and ob/gyn doctors used to spend one month whereas the hematology and pathology residents/fellows spent on average three months.  The few interested in the field might do multiple rotations.

I still gave them lectures on a variety of topics, especially how to transfuse blood components, basic ABO/Rh antigens, compatibility testing, and direct antiglobulin testing.  They would forget most of this, but I wanted them to remember TURN-AROUND-TIMES:

Examples:

HOW LONG DOES IT TAKE TO PERFORM THE TEST?  TO FIND COMPATIBLE BLOOD?  TO THAW THE PLASMA?  RELEASE AN MTP SHIPMENT?  TO PERFORM A TRANSFUSION REACTION WORKUP BEFORE RELEASING MORE BLOOD?

I am not discouraging people from entering the field, but I am a realist to know that few will share my passion for serology or want to take call on difficult immunohematology cases.  At least if they understand the pressure the technical staff are in and these turn-around-times this will make both their work as clinicians and mine as transfusion medicine more congenial.