This is the third part of this Saudi Ministry of Health presentation that I gave several years ago and looks at TRALI/TACO pathophysiology.











To Be Continued
13/8/20

Teaching medical and technical staff transfusion medicine
This is the third part of this Saudi Ministry of Health presentation that I gave several years ago and looks at TRALI/TACO pathophysiology.
To Be Continued
13/8/20
Second part of fatal adverse effects due to transfusion: this was originally presented at the Saudi MOH several years ago:




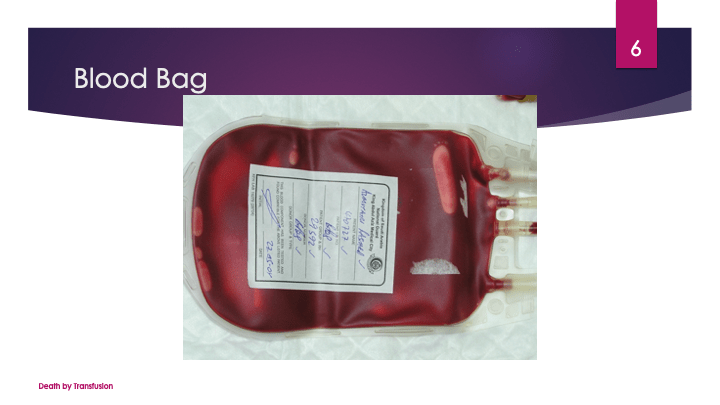

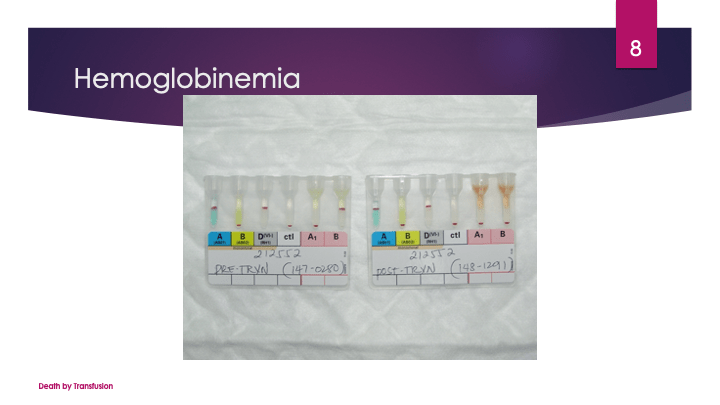

To Be Continued:
12/8/20
This is a presentation I made at the Saudi MOH many years ago, but it is still good for teaching purposes. I am dividing it into multiple parts because of its size.








To Be Continued:
11/8/20
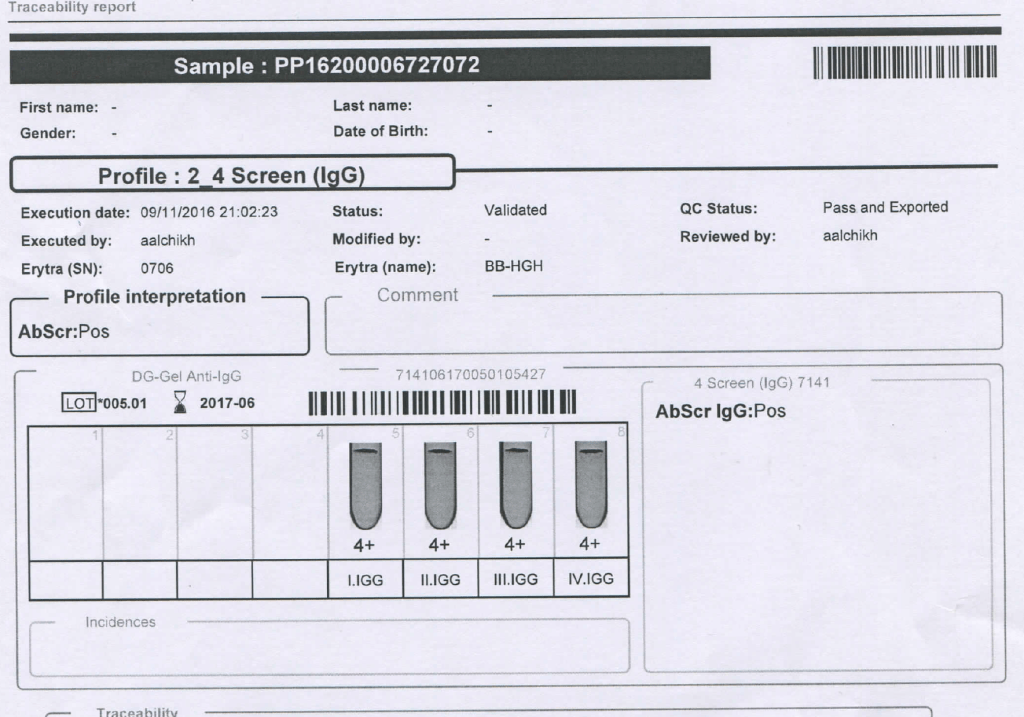
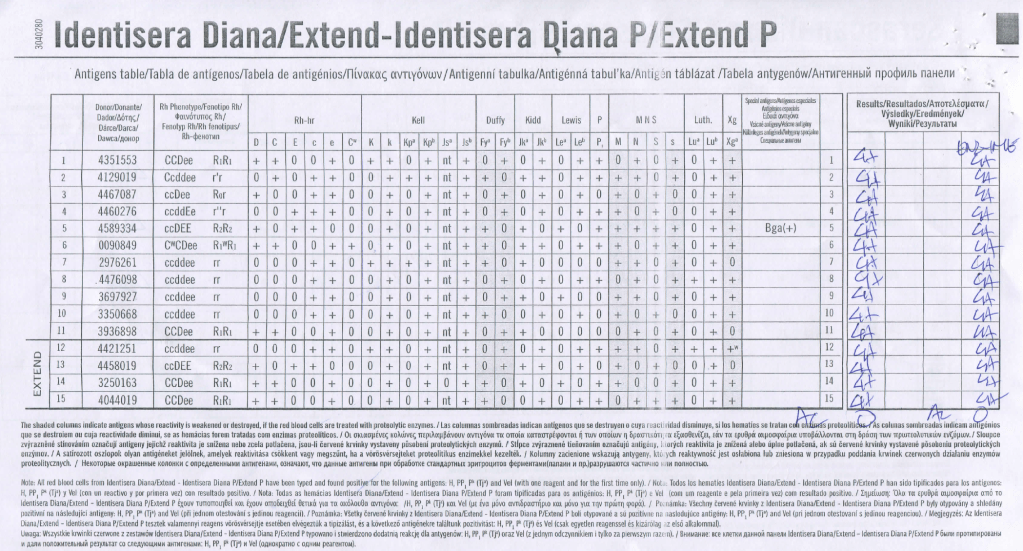
We had a mother (R1R1 K-neg) from Tamil Nadu who had several visits to our hospital. Anti-H lectin was negative. Here is a summary of her workup:
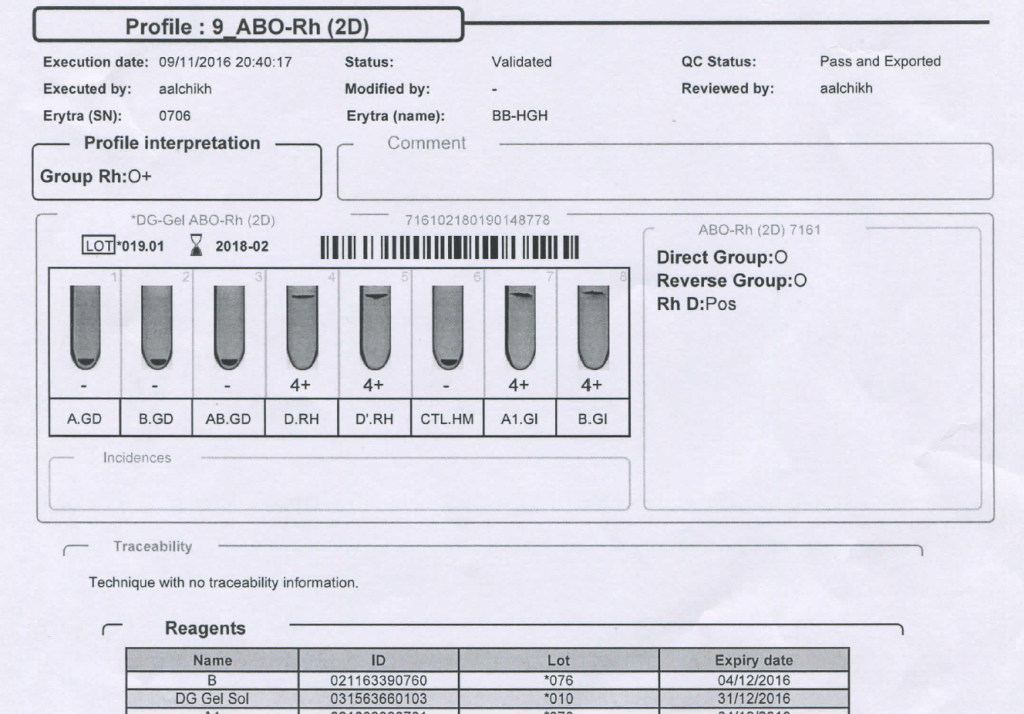
Mother’s ABO/D Typing:
Mother’s Antibody Screen:
Mother’s Antibody Identification:
She gave birth to a baby girl, group B, R1R1 K-neg. This is the neonate’s workup:
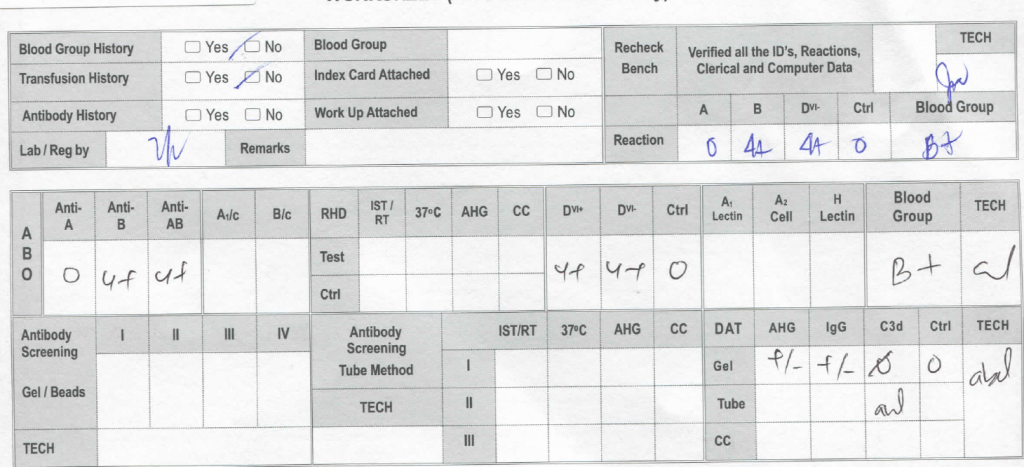
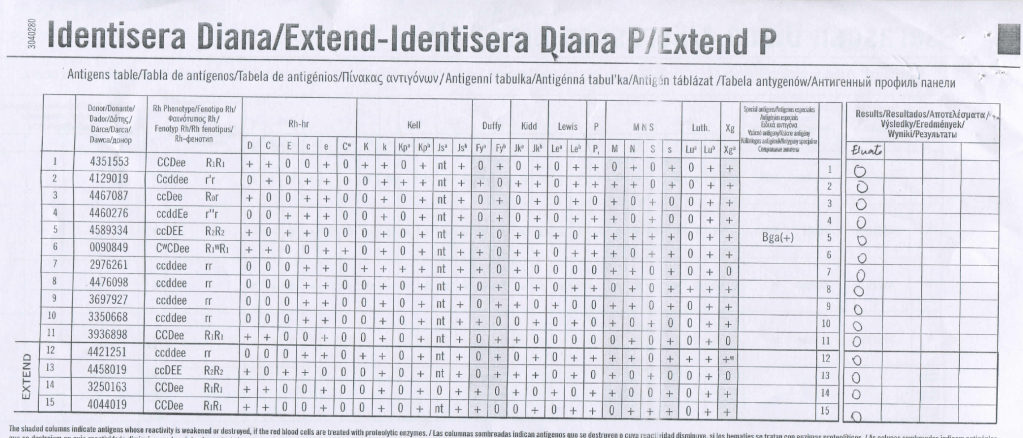
Despite the weakly positive IgG DAT, the eluate was negative. The neonate was asymptomatic.
Anti-H is mainly an IgM antibody and does not cross the placenta, thus no HDFN was noted.
6/8/20
I have had many medical students, residents, and fellows rotate through my Transfusion Medicine department. Hardly anyone has had any interest in making my discipline his/her career. It is a required rotation or an “easy” rotation during which the trainee may take his vacation. The trainee will cram for the examination and then promptly forget it.
I left practice in the USA in 1990, in what I consider the golden age of laboratory medicine. We had supervisors for each laboratory section. In the blood bank, we had many staff with SBBs or who were SBB students. We were very self-sufficient in handling immunohematology problems except for rare blood types or antibodies to high incidence/prevalence antigens.
When I returned to visit my old laboratory. I sensed a deprofessionalization of the laboratory and blood bank in particular. Blood Bank now is a cost center, not an area of revenue. Why hire experienced blood bankers for most hospitals? Send the antibody workups to the Blood Center. There are limited jobs for transfusion medicine consultants. Minimize testing, don’t do extended antigen typings, etc.
Nowadays, I feel like one of the dinosaurs marching into oblivion as in Walt Disney’s Fantasia film, the section called The Rite of Spring. Who will replace those of us retiring? Have you ever noted the average age of attendees at the AABB annual convention? I feel young when I go there (and don’t worry about the gray hair!)
I want to attract new doctors and scientists to Transfusion Medicine. I really try, but most have no interest and look on their rotations as a necessary evil.
I have lowered my expectations for most medical trainees in Transfusion Medicine. They don’t like it, they just want to pass it, and move on. What must I impress them with for their future careers? What is essential for them to remember?
I have had both pathology and non-pathology trainees. Surgical and ob/gyn doctors used to spend one month whereas the hematology and pathology residents/fellows spent on average three months. The few interested in the field might do multiple rotations.
I still gave them lectures on a variety of topics, especially how to transfuse blood components, basic ABO/Rh antigens, compatibility testing, and direct antiglobulin testing. They would forget most of this, but I wanted them to remember TURN-AROUND-TIMES:
How long does it take to perform the test?
Find compatible blood?
Thaw the plasma?
Release a massive transfusion protocol shipment?
Complete a transfusion reaction workup before releasing more blood?
I am not discouraging people from entering the field, but I am a realist to know that few will share my passion for serology or want to take call on difficult immunohematology cases. At least if they understand the pressure the technical staff are in and these turn-around-times this will make both their work as clinicians and mine as transfusion medicine more congenial.
Principle:
Daratumumab is a monoclonal antibody that binds to CD38 antigen, which is expressed weakly on the surface of all RBCs. It may thus cause a positive direct antiglobulin test DAT and so interfere with compatibility testing if an antiglobulin phase is required.
This effect may persist up to 6 months after discontinuing the drug. The monoclonal antibody does not interfere with routine ABO/D typing.
Special techniques (neutralization of CD38 antibodies by CD38 anti-idiotypic antibodies, or soluble CD38 antigen) may remove the panreactivity but are not generally available. DTT, a sulfhydryl reagent may denature the native CD38 antigen on RBCs but it should be used under a biologic hood.
Kell antigens will be denatured so Kell antibodies cannot be detected after treatment so Kell-negative RBCs should be used. In the Gulf Area, this is about 72% of RBCs. In the Medinfo software a rule to require K-negative RBCs has been built.
Policy:
References:
Trick or Treatment, Anti-CD38 Reactivity and How to Treat It, AABB Satellite Symposium transcript, U. Cincinnati and RedMedEd, October, 2015 (attachment)
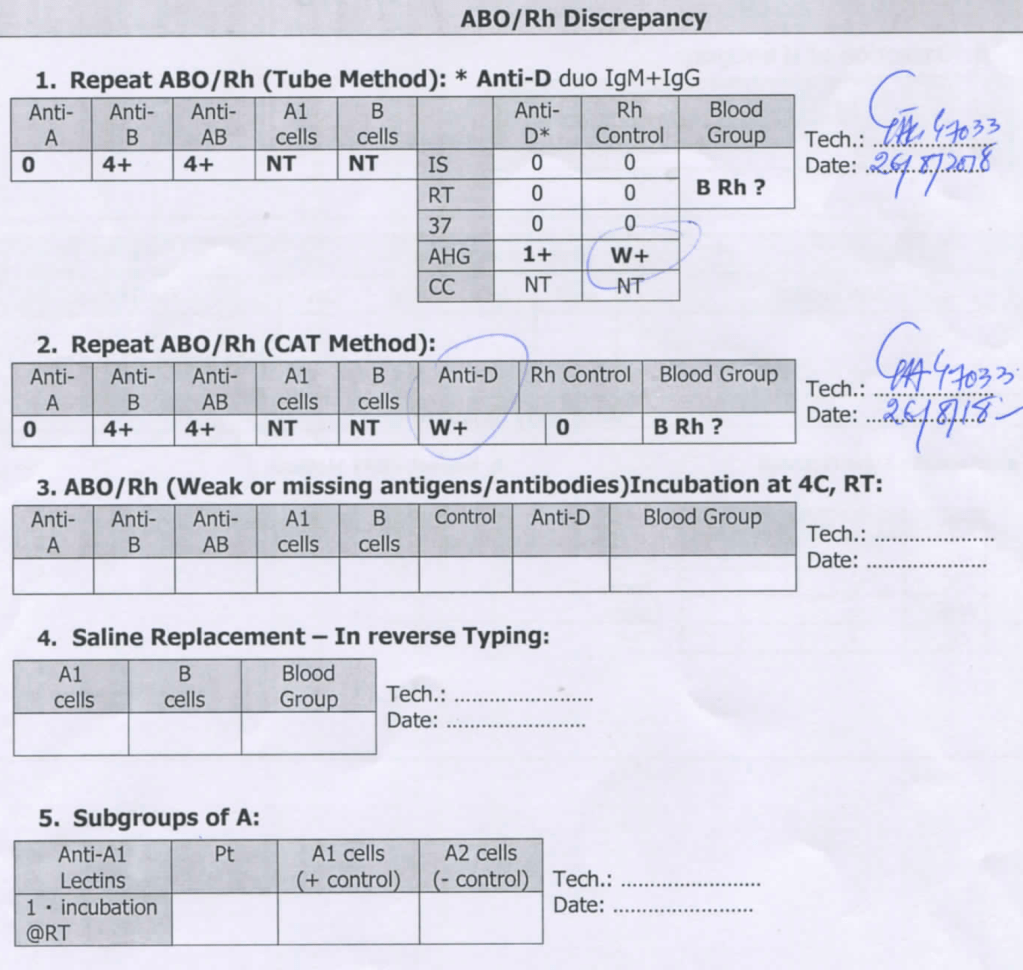
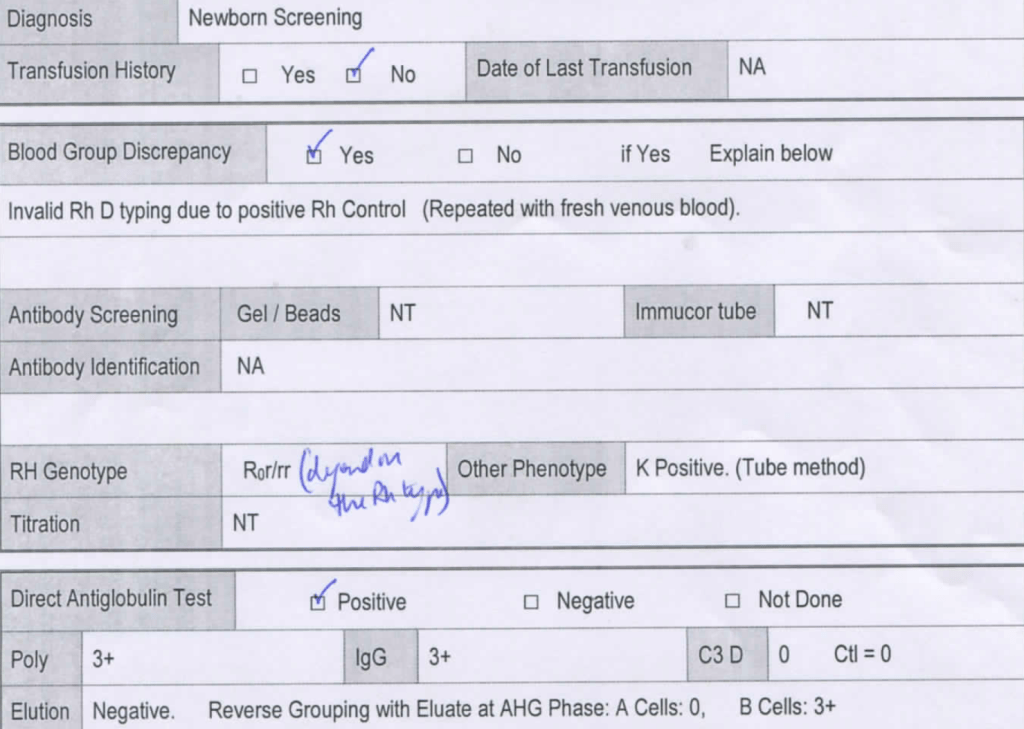
Recently, I had a case where the blocking antibody was not an anti-D, but rather an anti-B in a case of ABO hemolytic disease of the fetus/newborn HDFN. The D typing result was weak but the D control in the gel was positive so the result was indeterminate. DAT was 3+ IgG and anti-B was identified in the eluate (mother was antibody screen negative, regular elution panels (group O cells) were negative. Some of the actual workup follows:
29/7/20
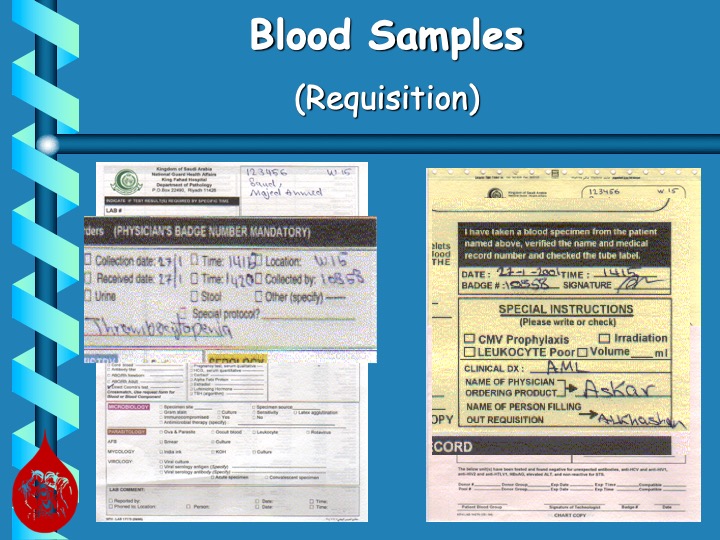
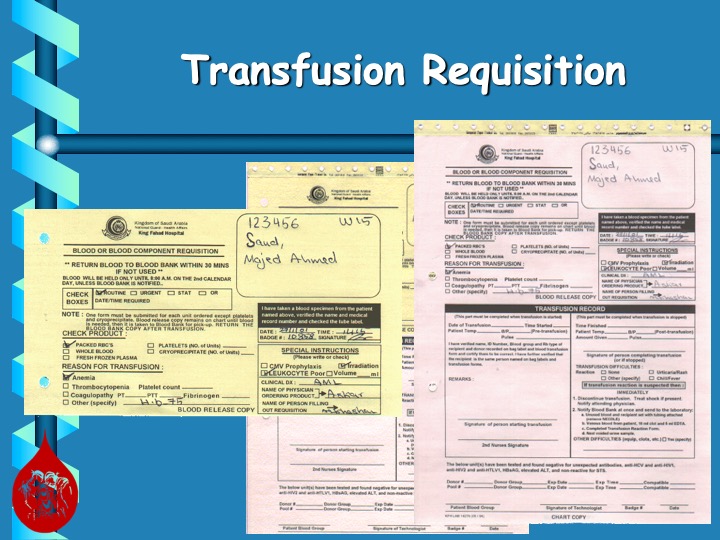
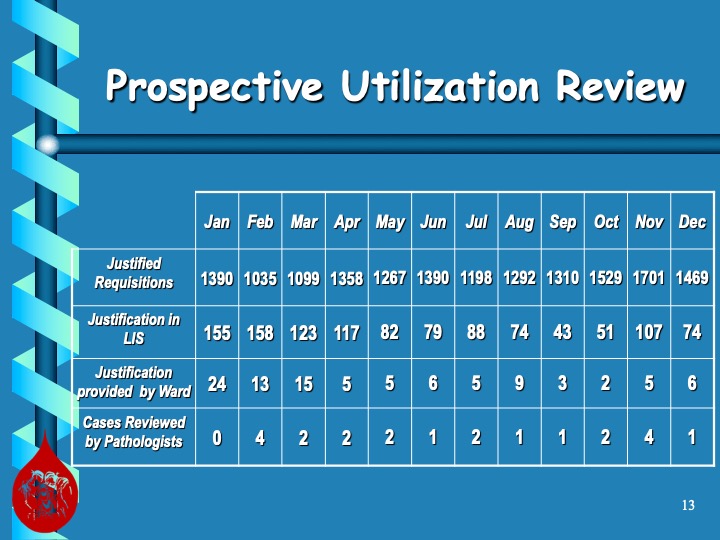
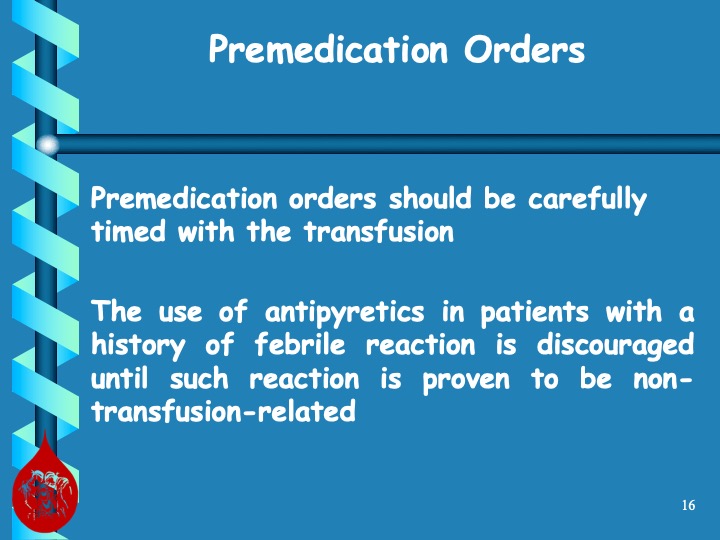
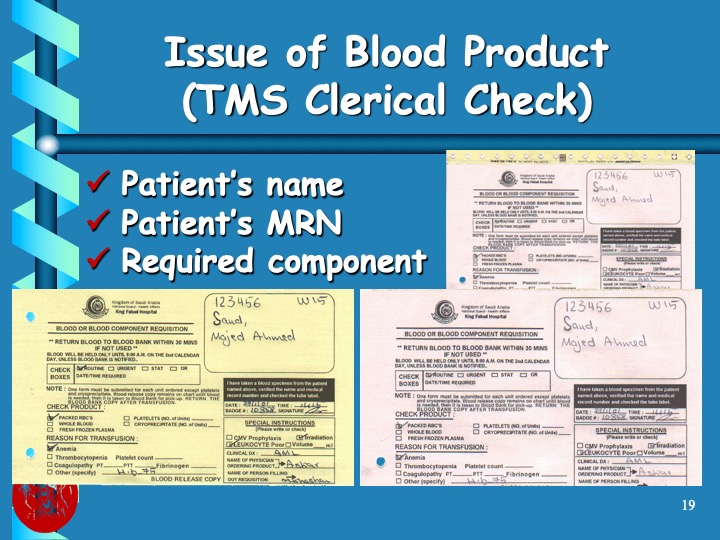
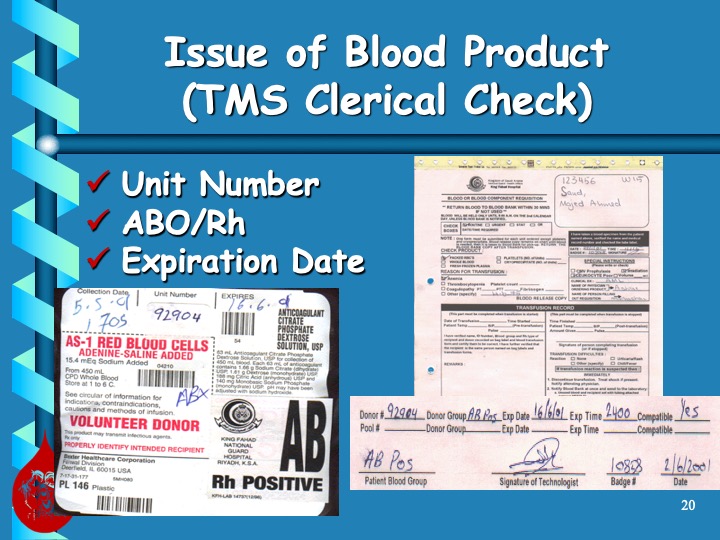
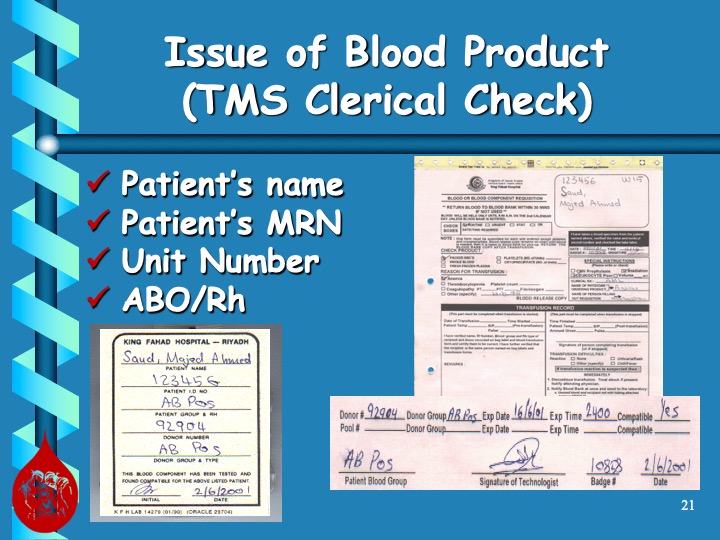
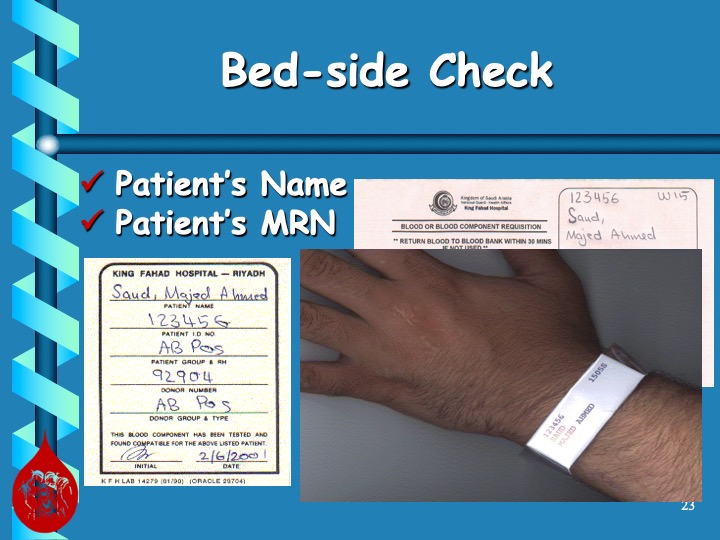
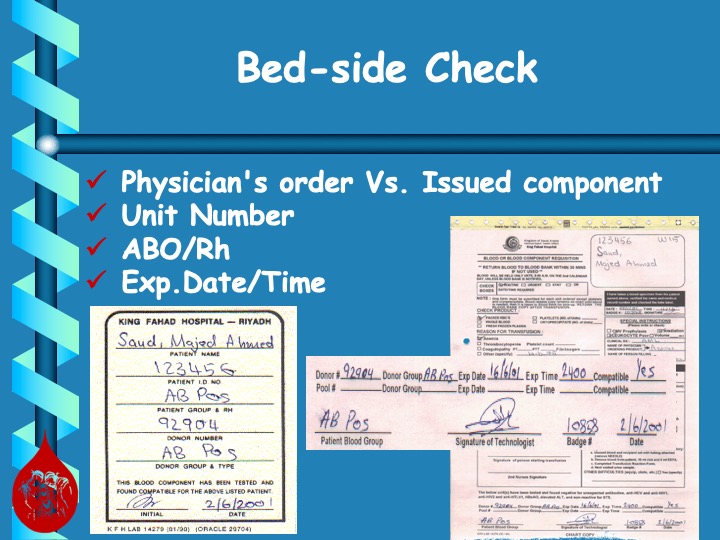
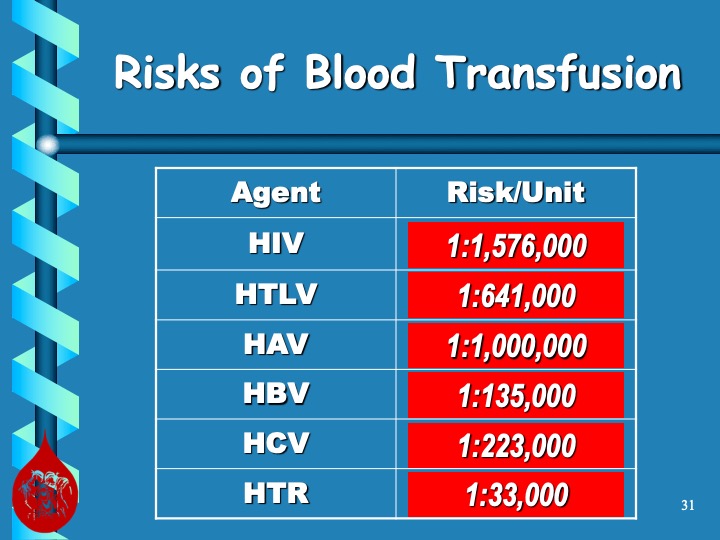
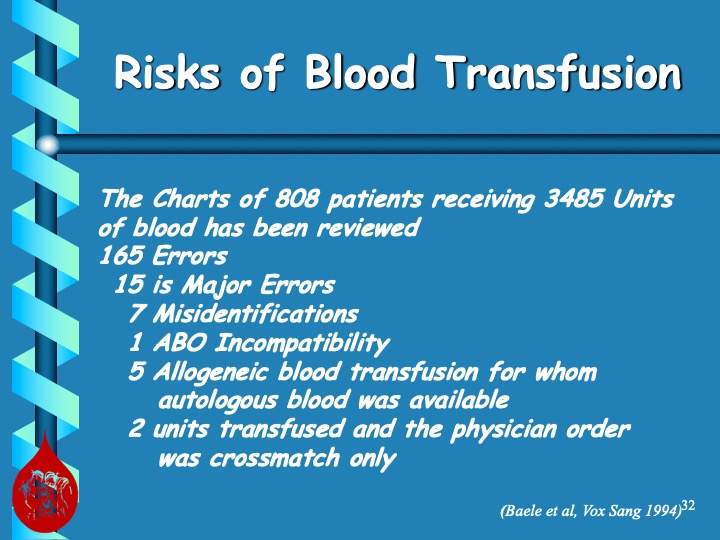
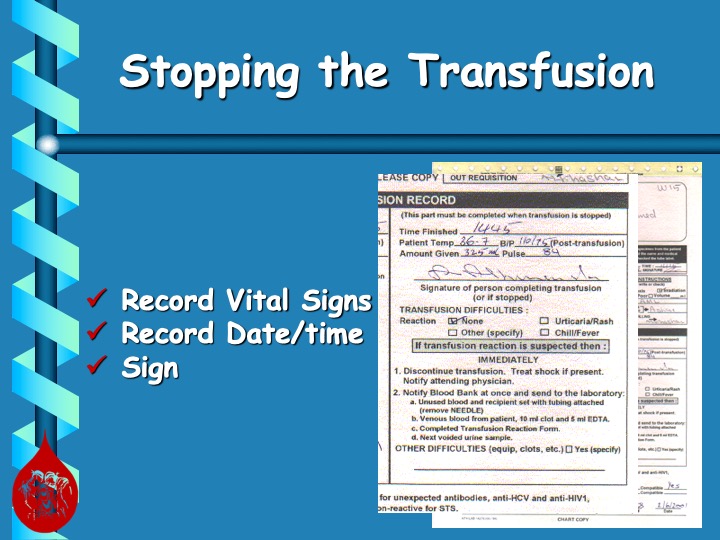
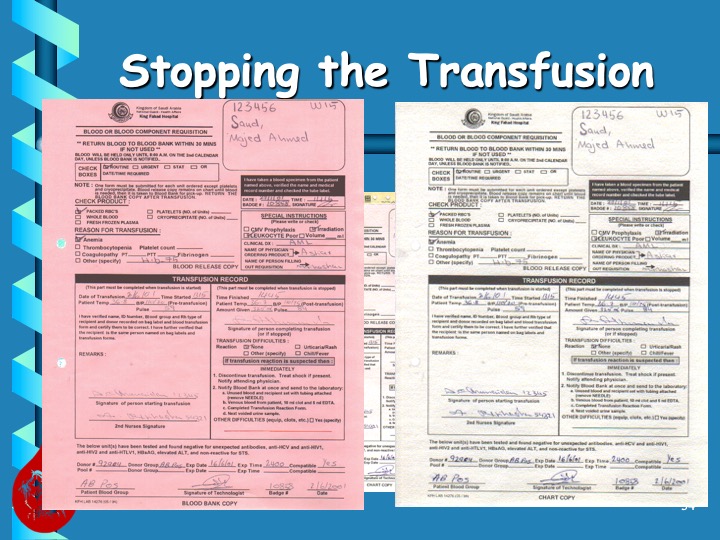
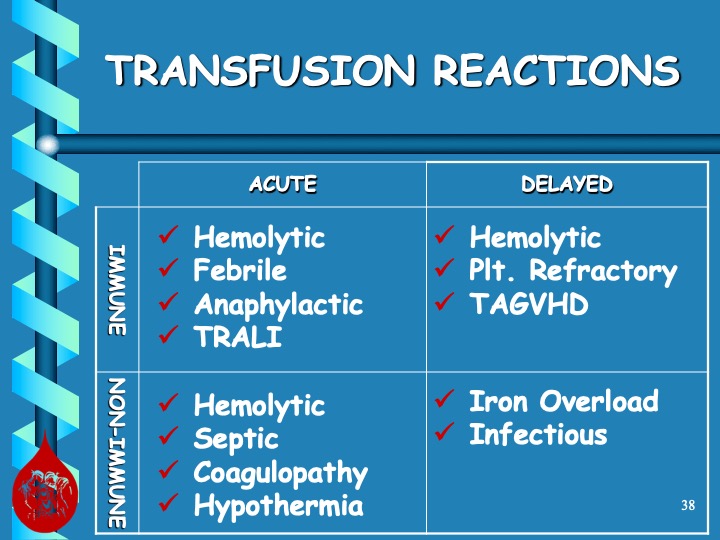
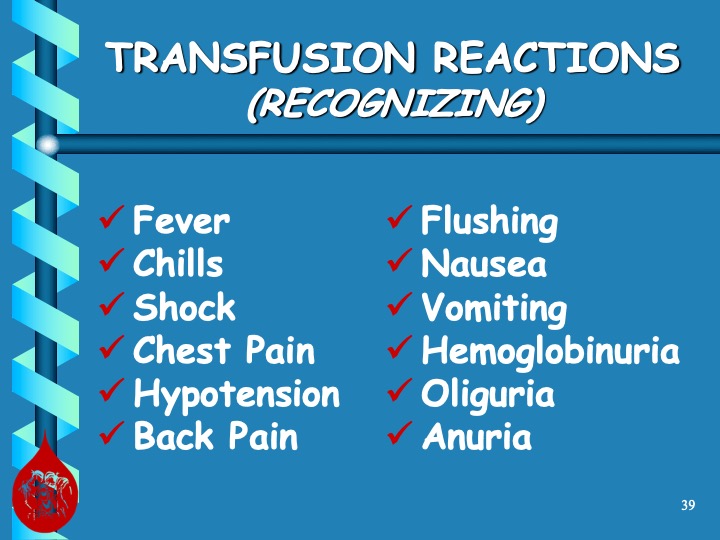
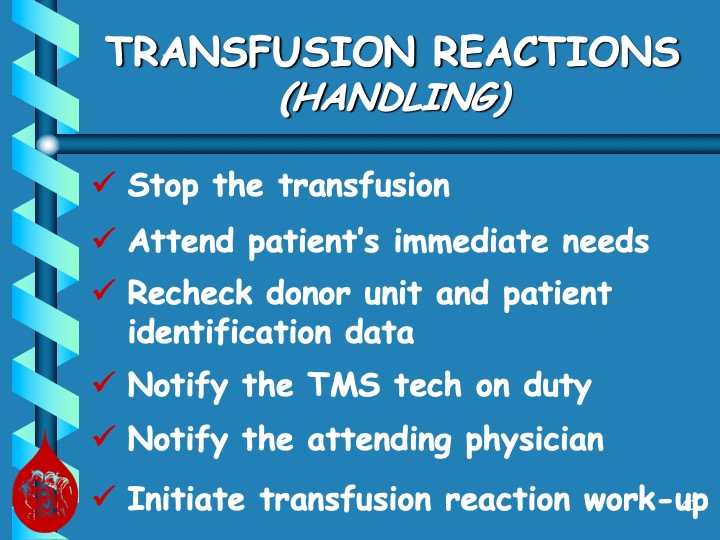
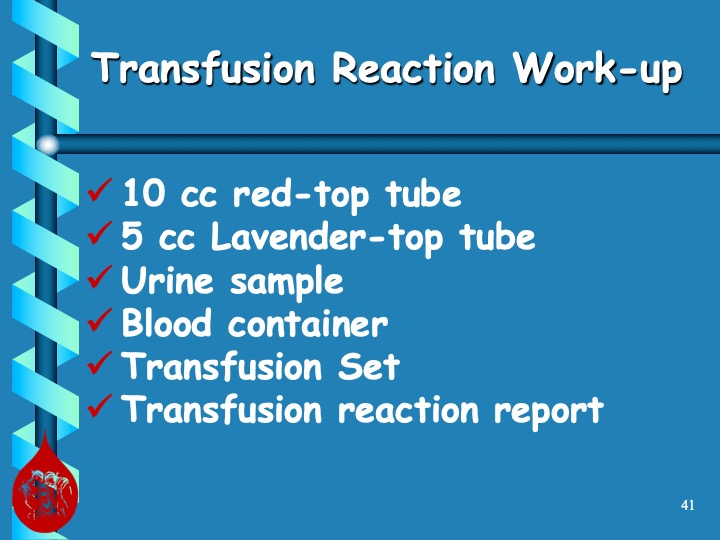
When I was affiliated with National Guard Health Affairs in Riyadh, my staff and I gave weekly new-arrival nursing orientations. The attached PowerPoint file from 2004 shows the manual system in effect at the time, but it is still illustrative to acquaint new staff on the hospital blood bank as it relates to their nursing duties, including specimen collection, pick up and transfusion of blood components, and adverse effects of transfusion.
I wish to give full credit to Mr. Abdullah Al Khashan, who prepared this file in conjunction with Ms. Editha Durante, the Transfusion Clinical Resource Nurse. The three of us used to rotate giving this lecture. This is my version of their presentation (with some minor formatting changes).










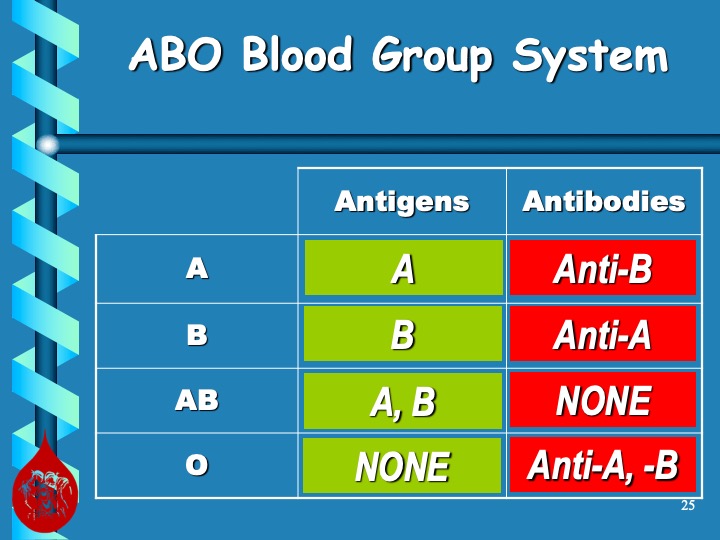

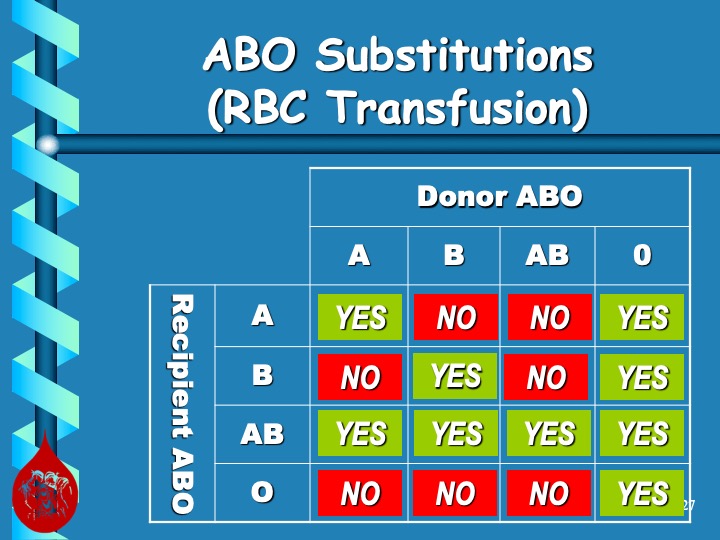
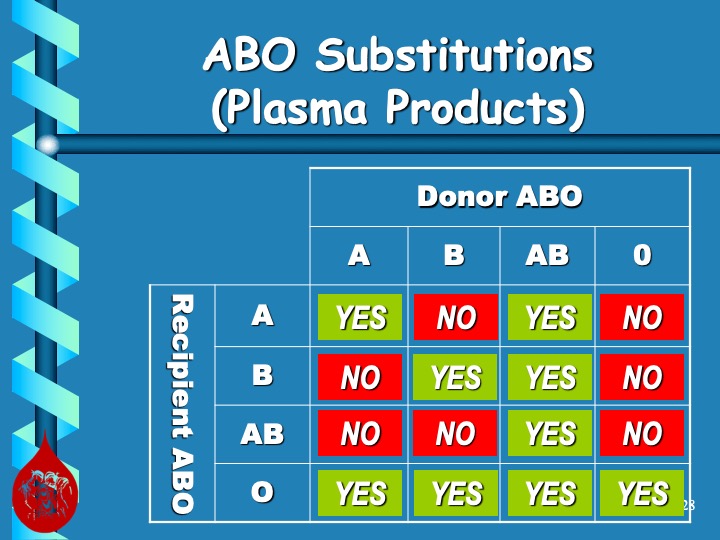
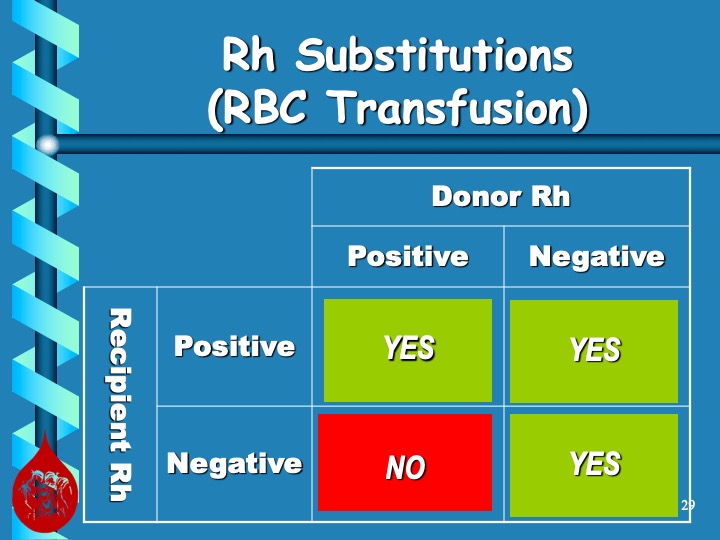






I cannot emphasize enough proper technique in doing the washing during the elution process. We are usually concerned about too little washing and thus possibly residual reactions in the last wash. However, aggressive overwashing may remove the bound antibody resulting in a negative result.
Here is an example of anti-PP1Pk (alias anti-Tja). The mother’s panel shows an antibody to a high prevalence/incidence antigen with negative autocontrol and no lability at enzyme phase:
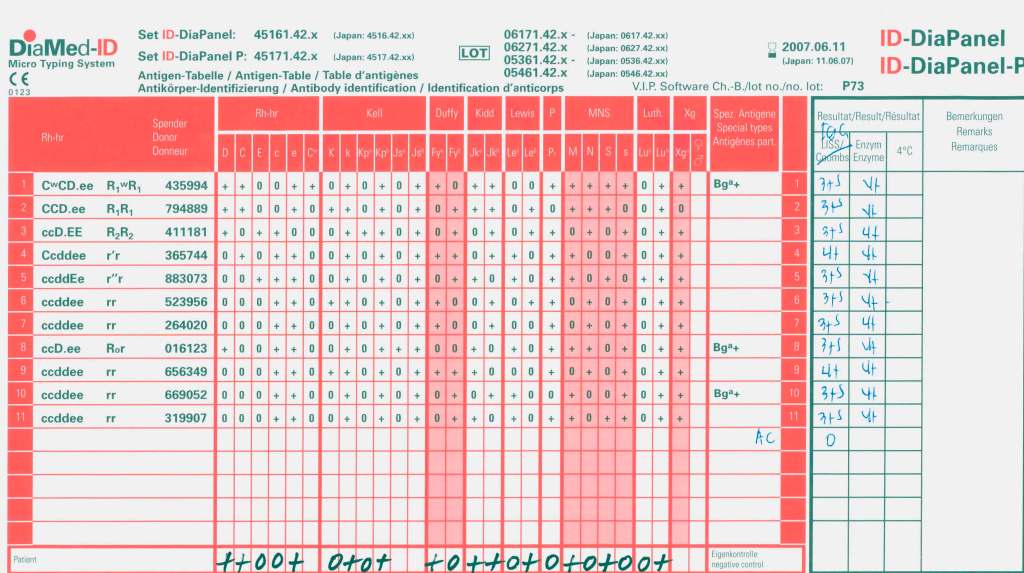
The neonate’s DAT was weak positive at polyspecific and IgG monospecific phases. An eluate was performed. Here is the result after washing four (4) times:
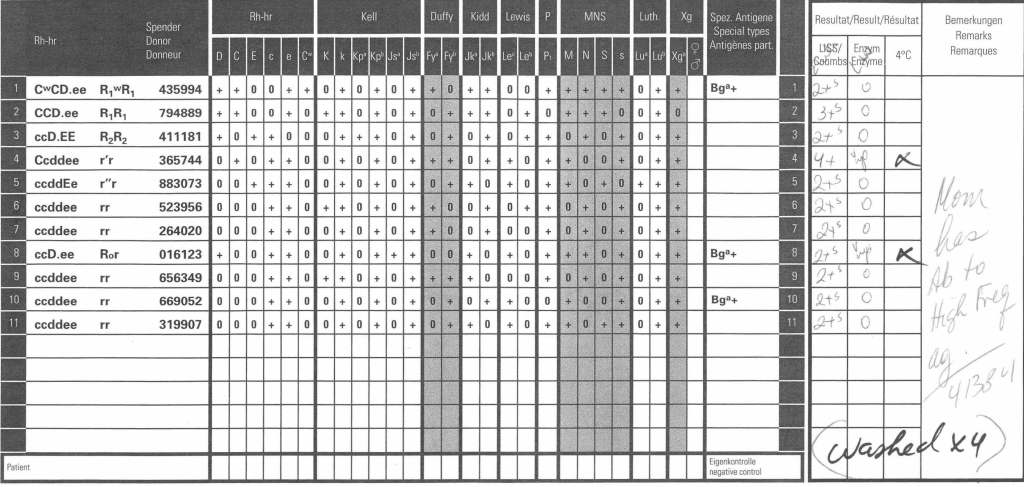
Since 2 cells in the last wash were very weakly positive, the washing was continued for a total of 9 times with the following results:
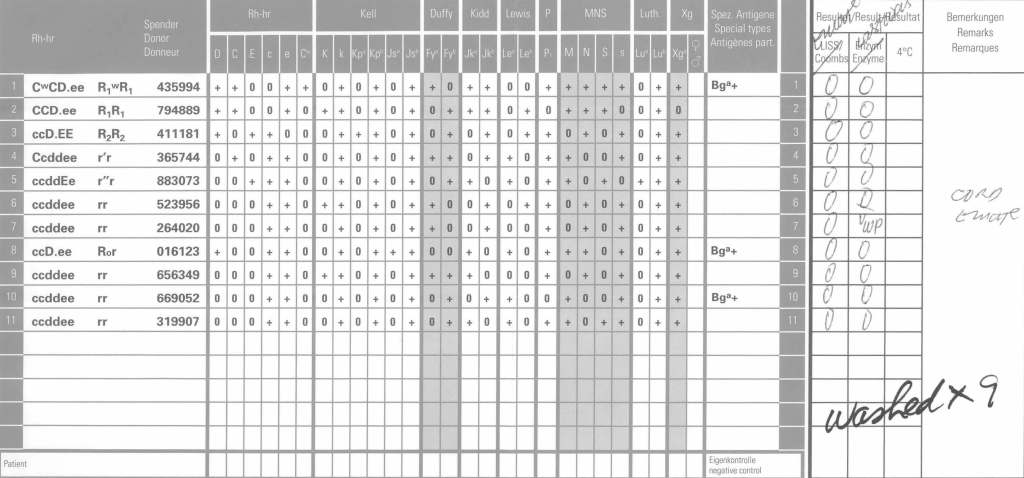
Even then there was very weak positivity in one cell, but the eluate was negative. We had washed away the attached antibodies.
A 31 year old Indian female’s prenatal testing results follow:
ABO Group B—unremarkable pattern
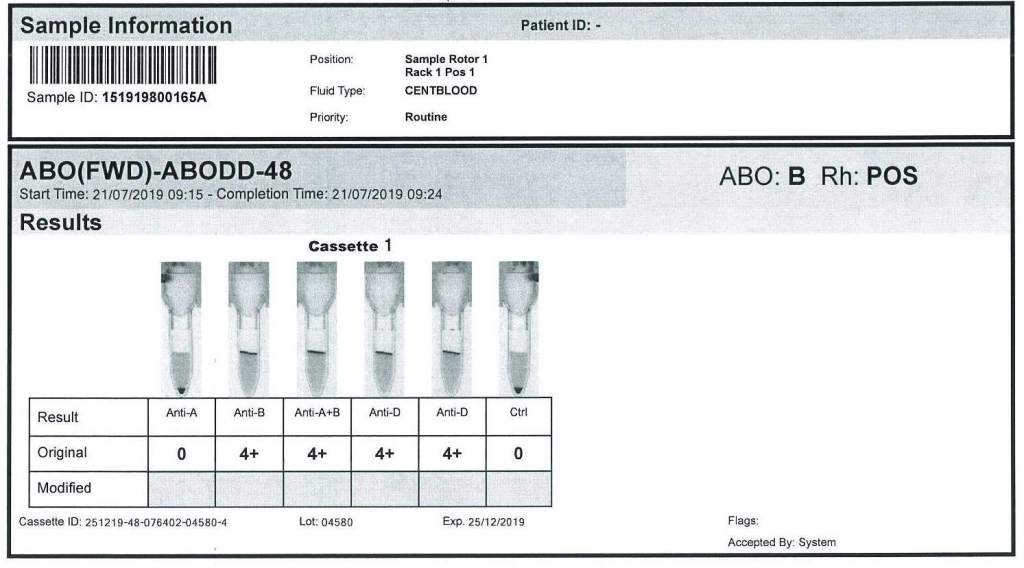
Rh(D) positive by both DVI+ and DVI- reagents by multiple manufacturers, both with gel and tube methods
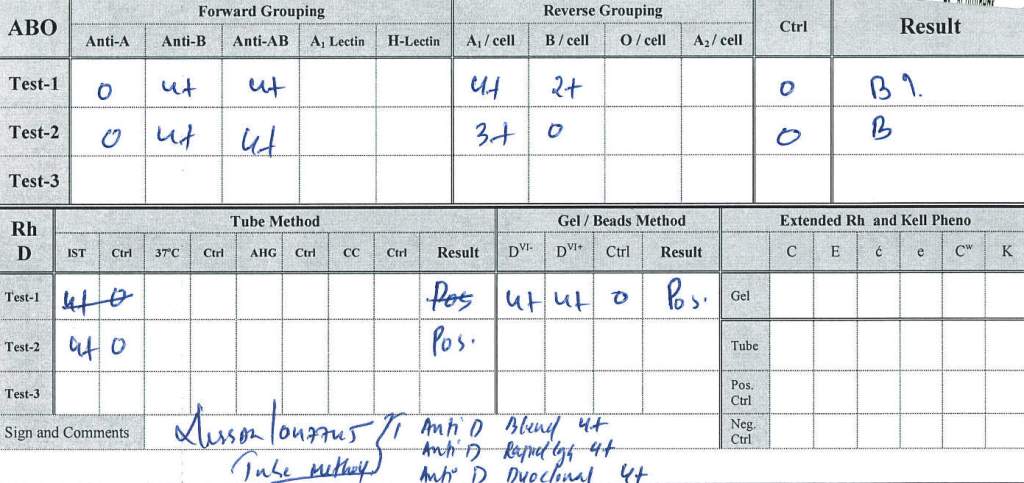
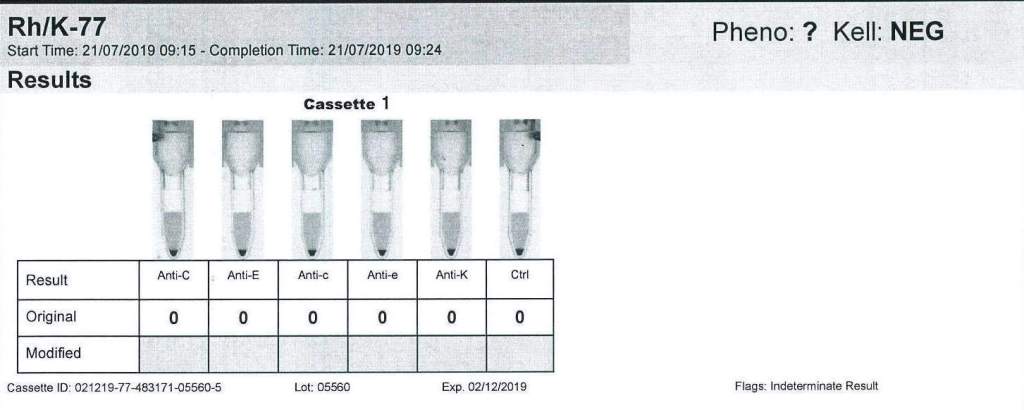
Extended Rh and Kell:
No reactions for C, c, E, e; Kell negative
(These results were confirmed by multiple manufacturer’s tube and gel reagents)
Extended Antigen Typings:
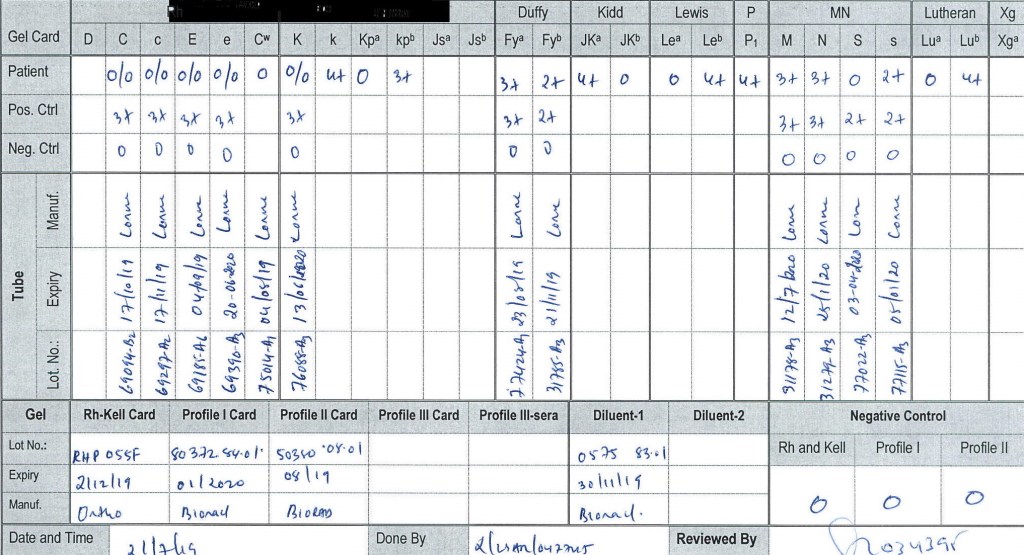
From the phenotypic data, we could already rule out anti-H, k, PP1Pk, U, and some unusual MN system variants found in the region.
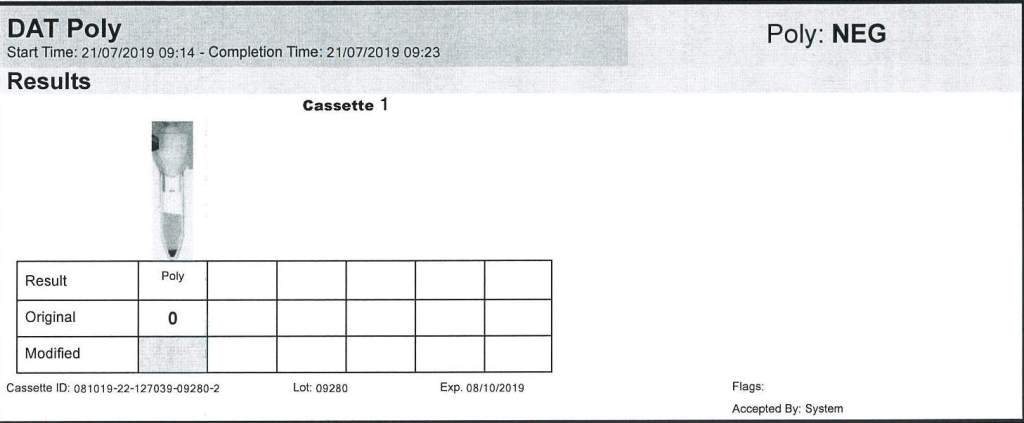
DAT: Polyspecific and monospecific IgG, C3b/C3d were all negative.

Antibody Screen: 4+ panreactive
Antibody Panel: 4+ panreactive, autocontrol negative, also 4+ by enzyme
Clinical Course:
At the time of the prenatal specimen, we informed the clinicians that we did not know the significance of the panreactive antibody. We recommended screening any blood relatives and autologous blood collection. We also recommended genotyping of the mother.
Several months later the patient presented in labor with severe fetal hydrops. The previous workup was repeated and confirmed. Neither genotyping or autologous collection had been done. No relatives had the same phenotype, and none were compatible with the mother.
We now knew that the antibody was highly clinically significant and very dangerous. With the permission of the treating obstetrician, the mother’s blood was used for transfusion of the newborn (washed, irradiated). Both mother and baby were group B positive.
To date of my departure from HMC Doha, the antibody had not been characterized, but we continued to recommend genotyping and autologous collection from the mother.
 Dr. Zeyd Merenkov
