Transfusion Medicine, Blood Bank IT, Pathogen Inactivation, Plasma Fractionation, COVID-19 Convalescent Plasma Production
Category: Patient
Includes compatibility testing (AHG, electronic, immediate-spin), antigen typing, antibody screening and identification, direct antiglobulin testing, elution, transfusion reaction and drug reaction workups, component typing tests upon receipt in hospital blood bank, release and return of components
Medinfo software is rules-based so the institution may set its own custom rules for all processes. One chooses a framework and then adds any additional rules it needs for optimization. Turnkey systems do not offer this flexibility.
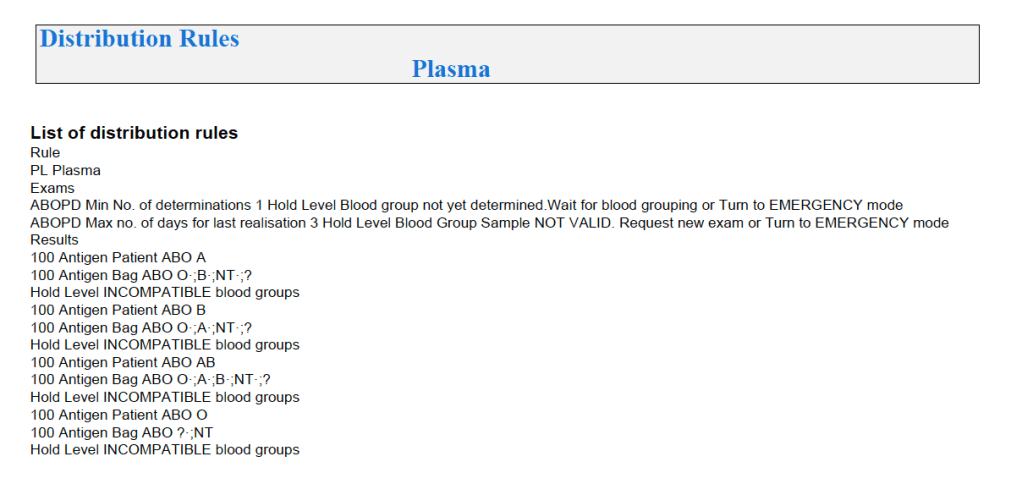
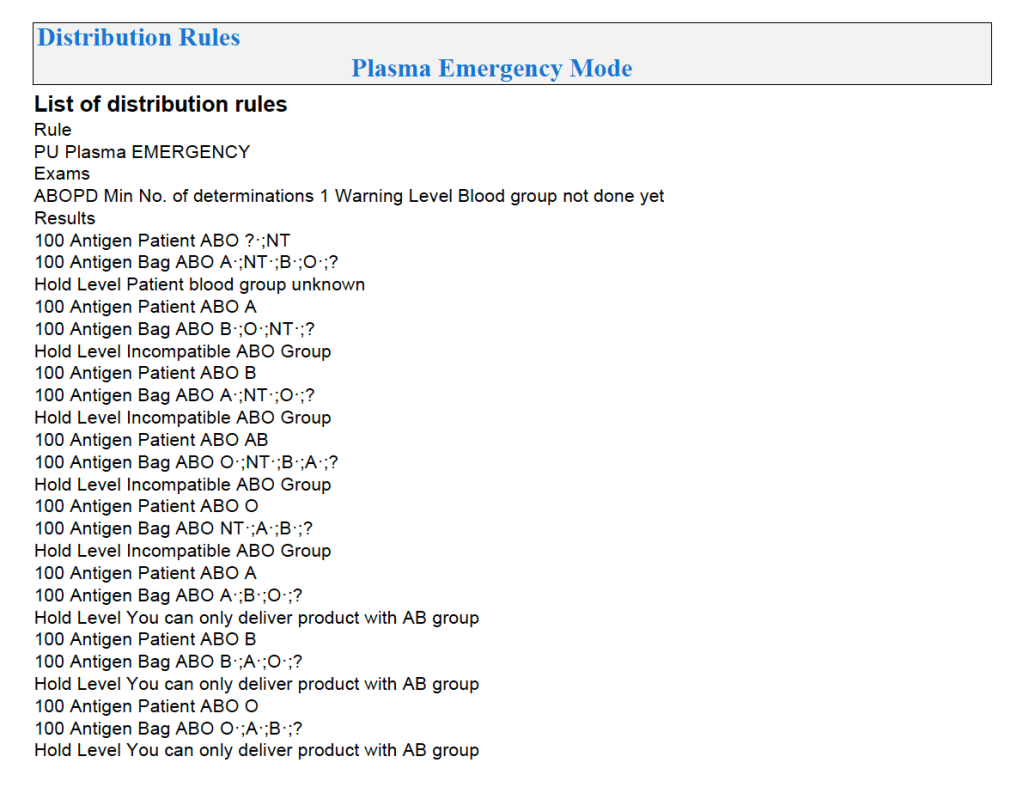
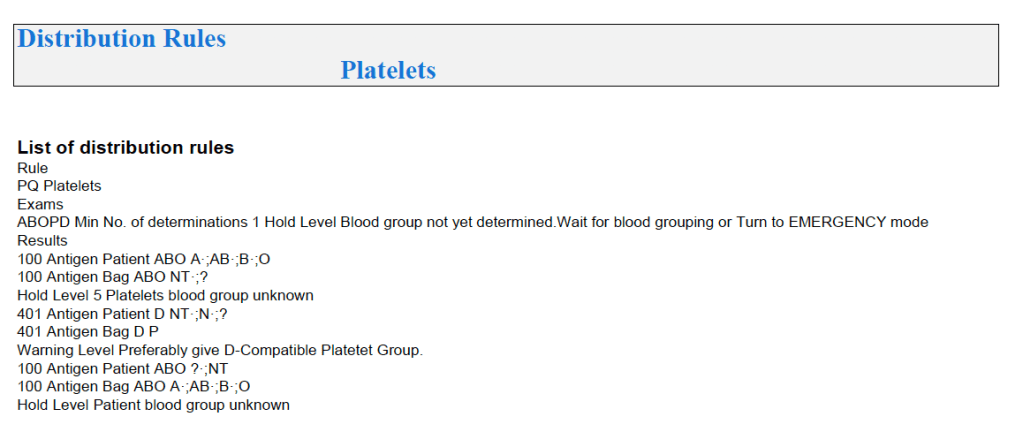
The rules for platelet and plasma components are much simpler than those for RBCs since usually we only consider ABO type. There are two modes: regular and emergency, the latter applying if not all the patient testing (including historical checking) is available. The components, on the other hand, must meet all criteria before being considered for patient use.
Example rules for plasma follow:
For platelets, note that for adults and anyone else >= 20 kg, I gave any type of platelet pool or plateletpheresis component without regard to ABO matching. With our production method, I did not give Rh immunoprophylaxis to females of child-bearing age receiving platelets from D-positive donors based on our clean (essentially RBC-free) Reveos automated production process.
Similarly, allocation rules for granulocytes, etc. could be made and enforced by the software. Low-B-titer group A universal plasma would also be easy to implement.
In the previous post I outlined how Medinfo handled antibody screening and identification. This post reviews how antigen matching is used based on these results.
There are two modes, regular and emergency. If the patient has not had at least two ABO/D determinations and/or does not have a recent antibody screen, then emergency mode must be selected with its own rules. Otherwise, the regular mode applies.
Regular Mode:
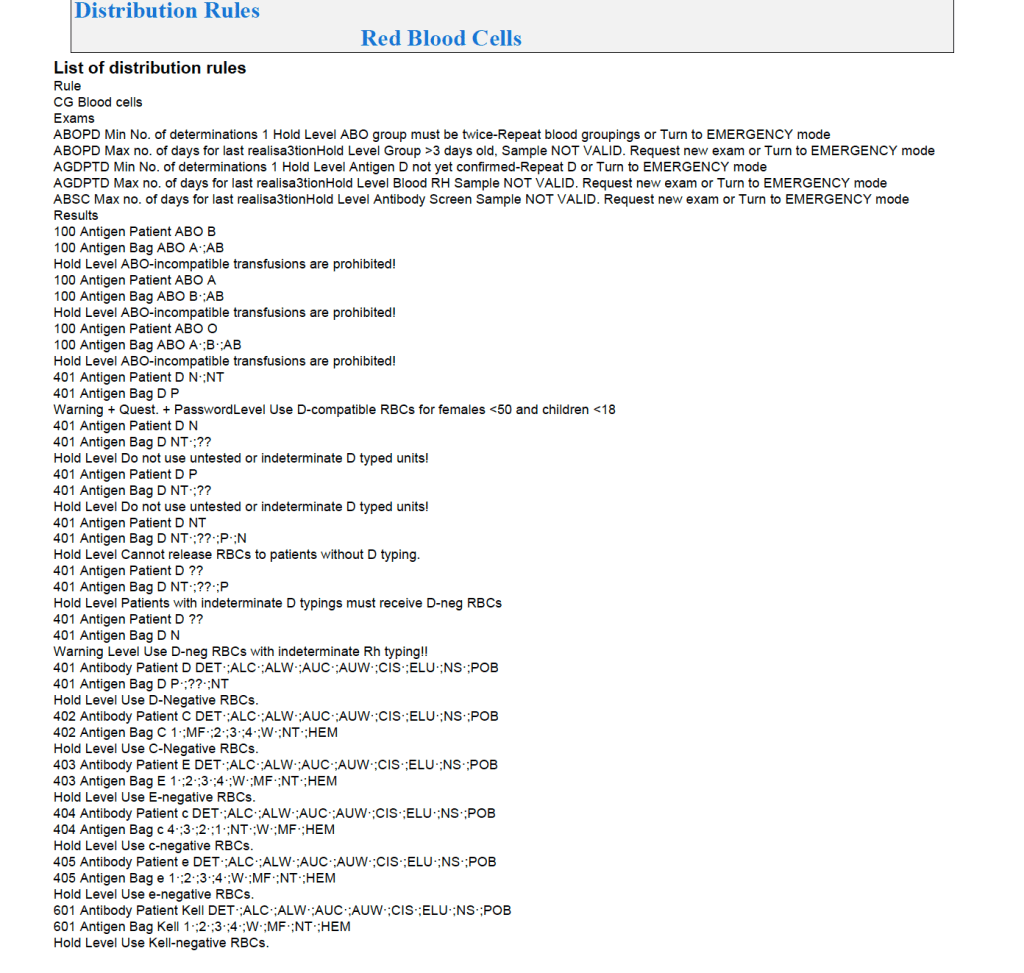
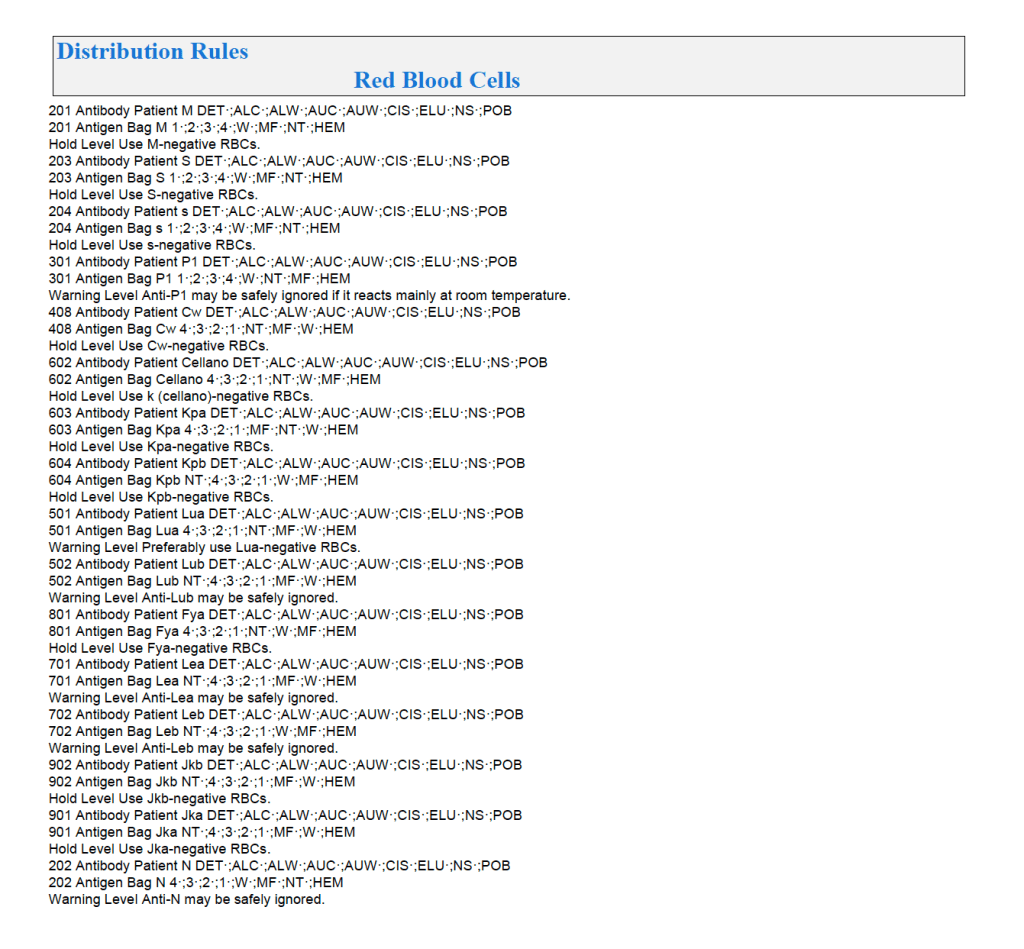
In general, if there is a clinically significant antibody, an RBC unit which has not been matched for the corresponding antigen or has the corresponding antigen cannot be routinely selected. However there is a hierarchy here also:
Absolutely prohibited release—no one can override the logic (e.g. giving group O to a patient with anti-H)—not even the transfusion medicine physician can override this
Restricted release—only certain staff can release the incompatible or untested unit (e.g. giving C-positive unit to someone with anti-C)
Least-incompatible for WAIHA: requires transfusion medicine physician approval
Informational release: authorized staff may release antigen-incompatible or untested unit but a pop-up menu appears and asks them to accept (e.g. Lewis untested unit in a patient with anti-Lea).
Antigen-specificity matched—the usual mode for patients with antibodies
Examples of Regular Mode rules follow (these are not the complete lists but just provided to show the complexity of the process).
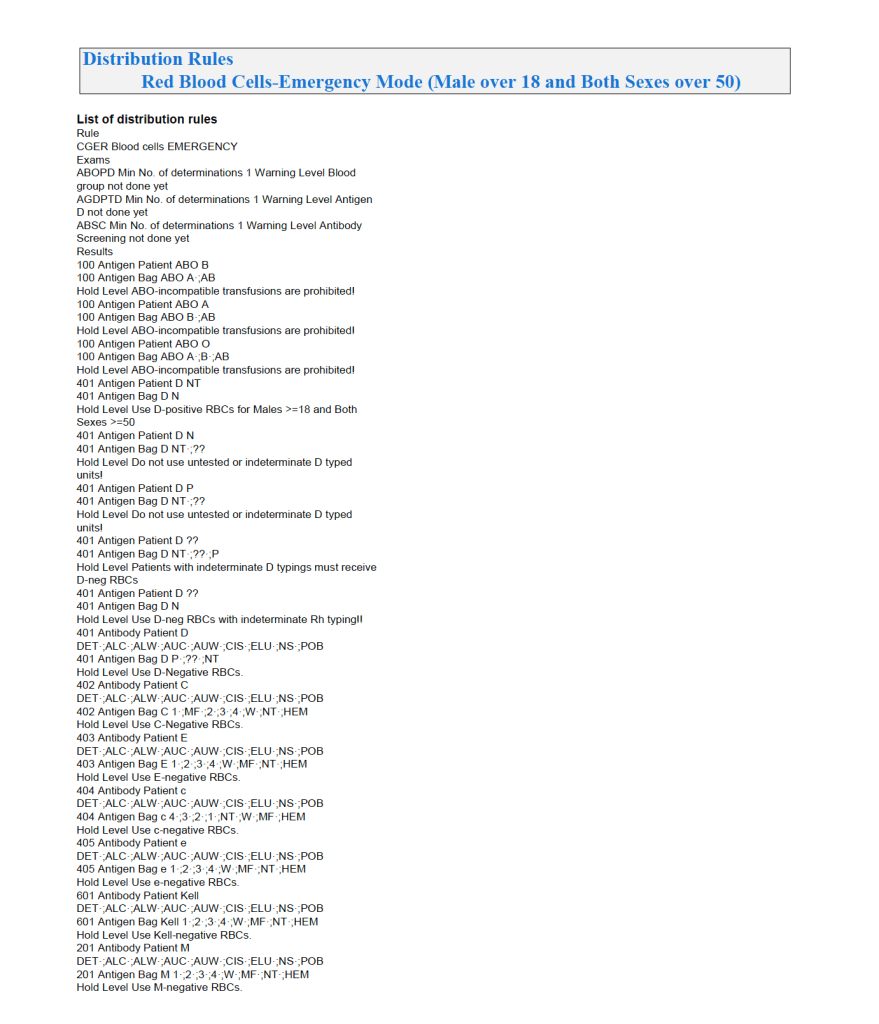
Emergency Mode:
This is much more restricted for selection of ABO/D and other antigen typings. An example follows:
A similar hierarchy exits for platelet and plasma allocation and will be considered in a future post.
The blood bank is one of the last bastions of manual testing, especially for complex procedures. Basic antigen typing, direct antiglobulin tests, and antibody screening adapt well for routine automation, but the actual antibody identification requires multiple methods and requires considerable experience to complete. At least today, a machine cannot replace the blood banker!!
One could take the approach to perform antibody panels in an automated system and record the results. However, these are worthless unless you have the actual panel in hand. Artificial intelligence to analyze the panel results is limited. You still have to manually review everything. In Medinfo, we could also scan the manually performed panels and add them to the record.
While I was at HMC, some of the hospital transfusion services elected to run panels automatically and then review the results manually. We prepared a contingency to record the panel results but these by themselves could only be used with the actual red cell panels in use.
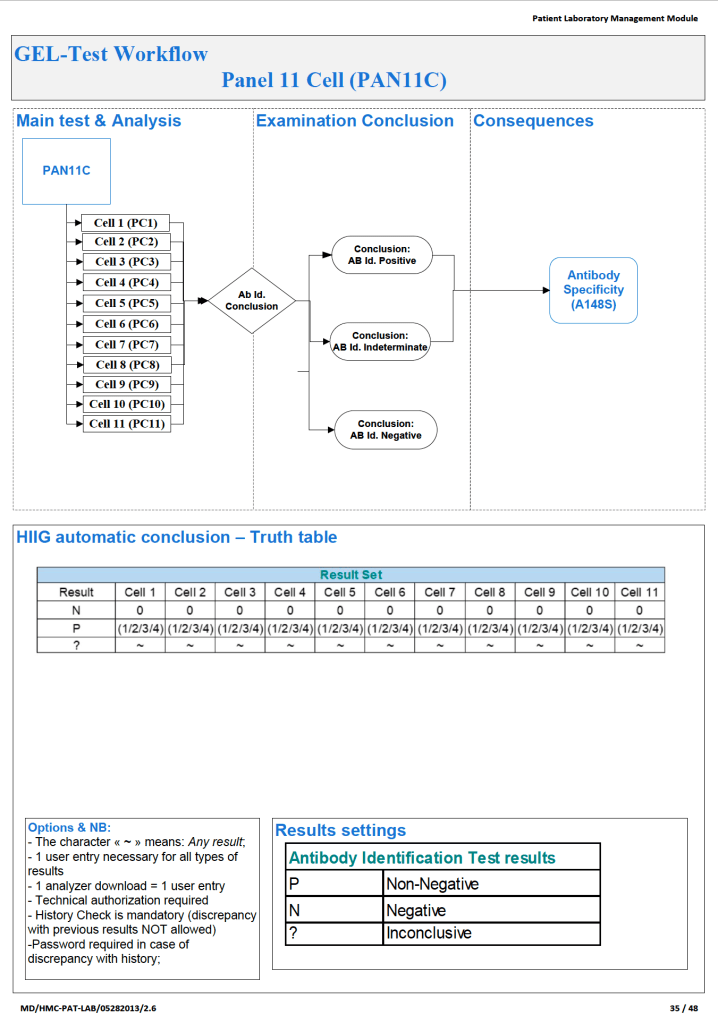
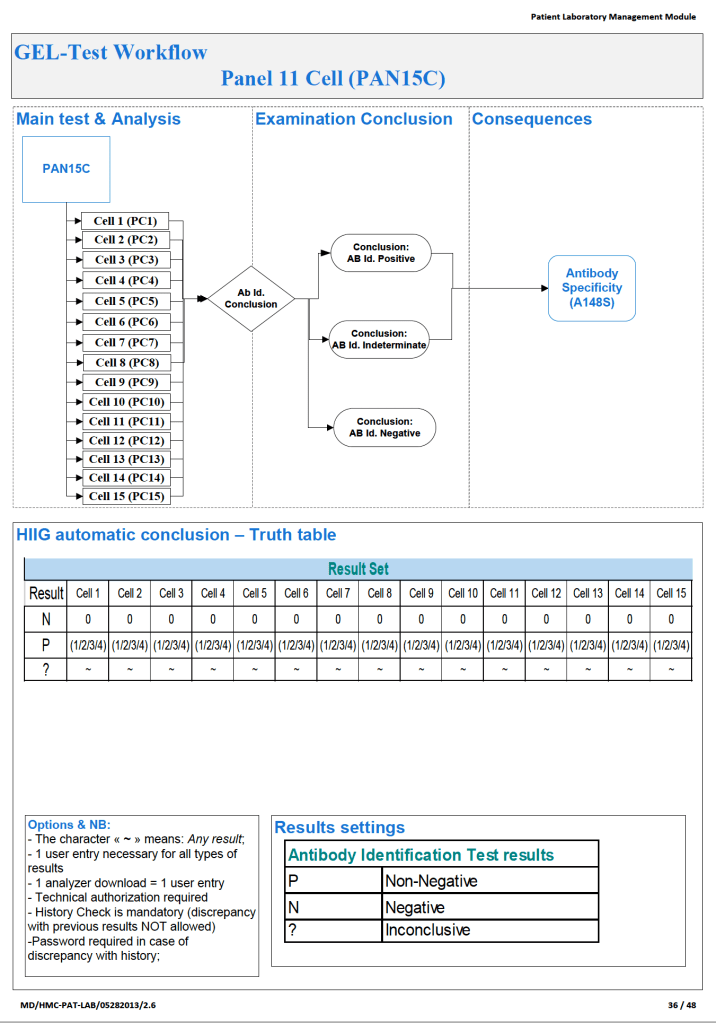
Examples of 11-R and 15-cell panel result importation follow:
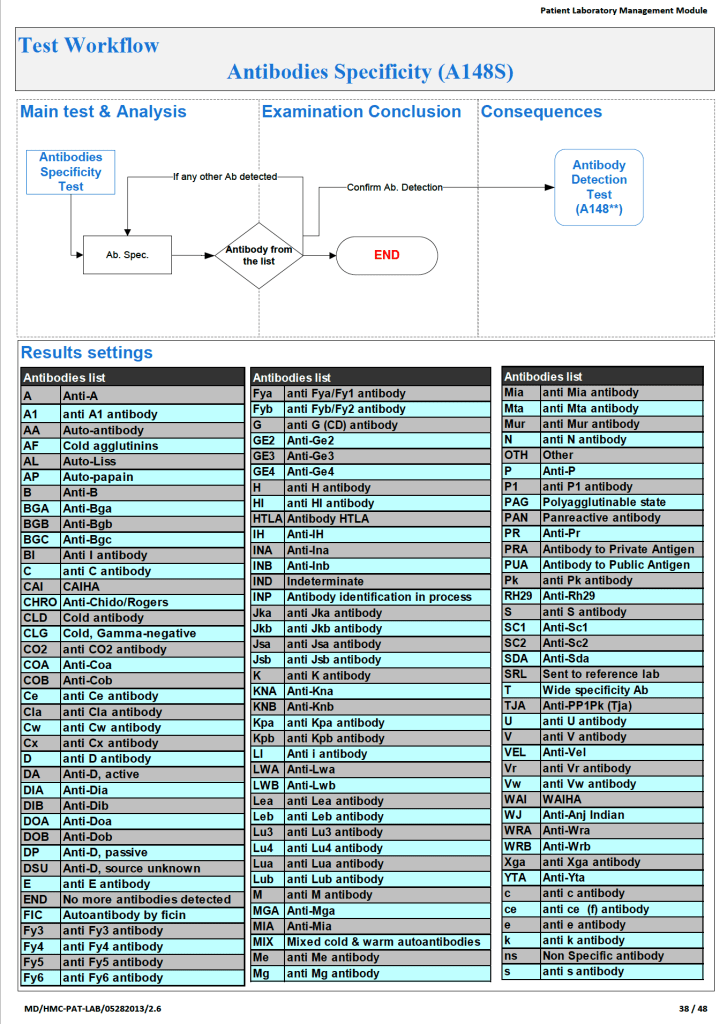
What we absolutely had to do was enter the antibody specificity in a way that it could trigger our algorithms, i.e. our rules-based system of RBC allocation according the permissible blood types. Each antibody specificity and each antigen typing had its own unique code. It could not be entered free text! Workflows follow:
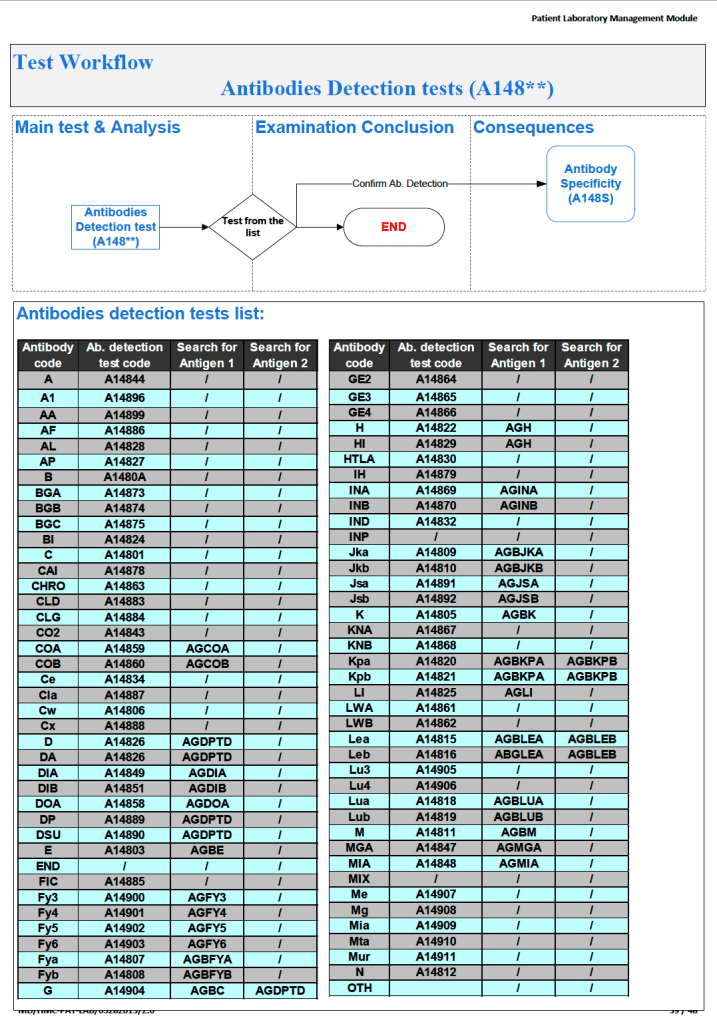
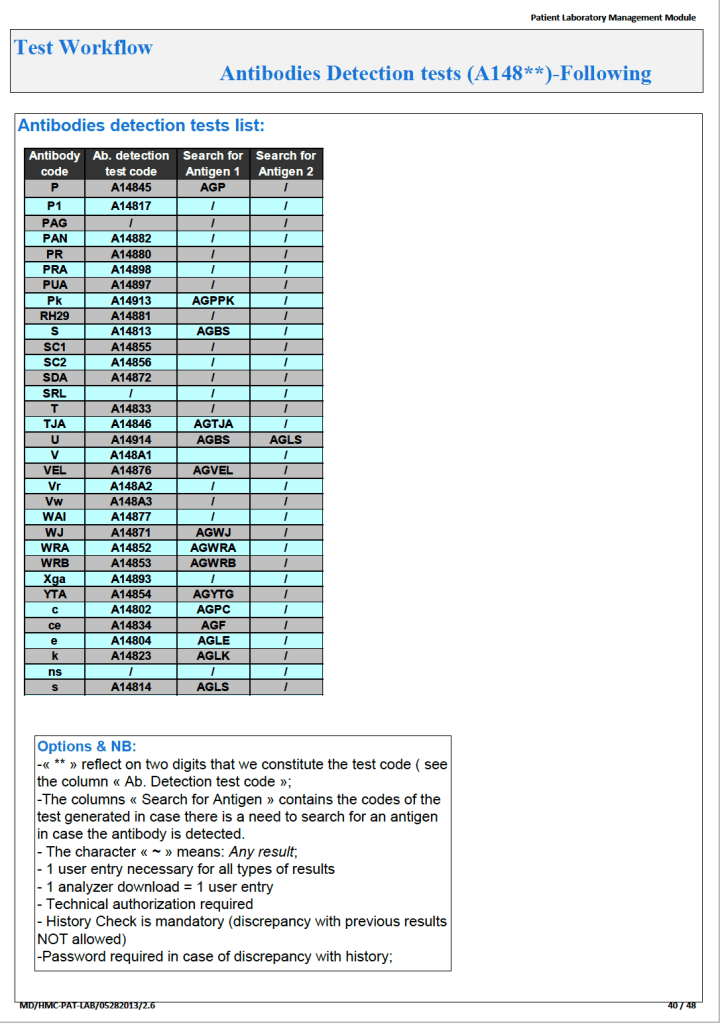
Next, the antibody specificity test would trigger antigen typings for the correspond antigen and/or closely related antigens:
Based on the antibody specificity and antigen typings, a whole series of rules for routine and emergency-mode release were triggered. This will be discussed in a subsequent post.
Revision Date: 15/7/20 (replaces 9/6/20 post on Linked In and now recommends full extended Rh phenotype matching for sickle cell patients).
Principle:
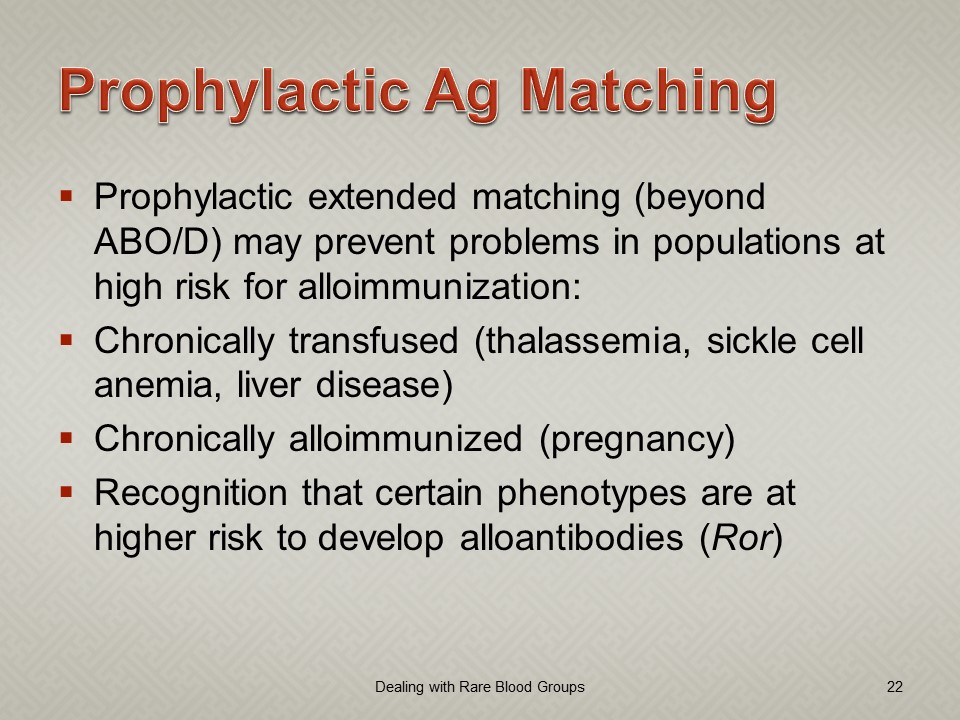
Extended/extra antigen typing may mitigate alloimmunization in selected populations (chronically transfused such as sickle cell anemia, thalassemia, leukemias, lymphomas, etc.) and those patients already making RBC antibodies. It can also help in discerning antibody specificities in patient workups where the antibody identification is unclear. This policy is in addition to the current selection of antigen-negative RBCs when clinically significant antibodies are present (e.g. Kell-negative RBCs for patients with anti-Kell).
Policy:
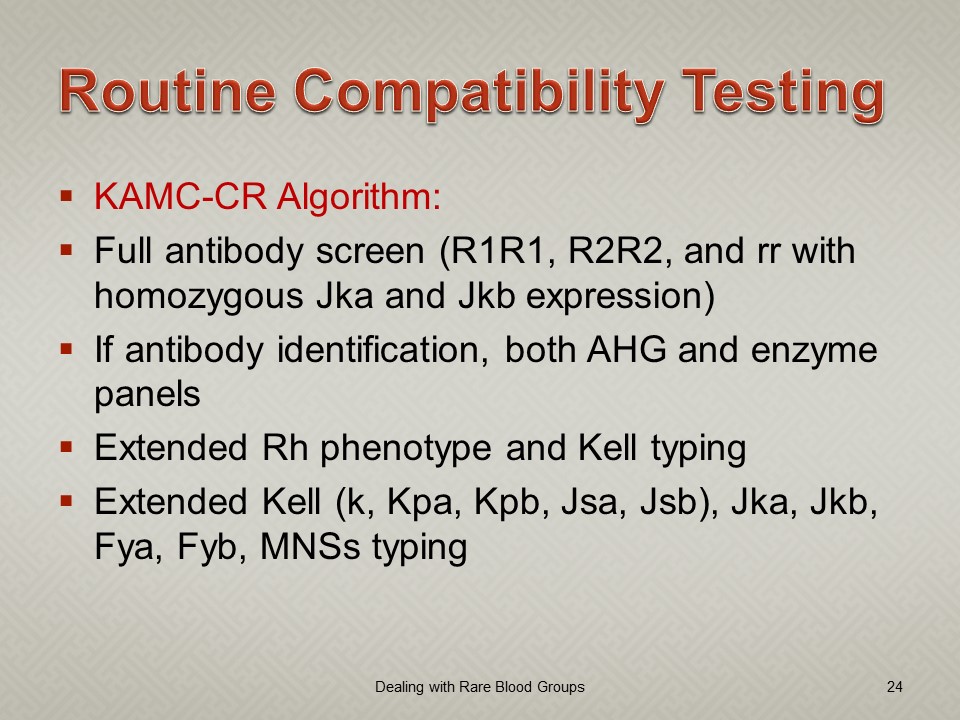
Perform extended Rh/Kell typing (CcEeK) in the following cases:
Patient has a positive antibody screen during routine testing (unless typing has been previously performed and is showing in Medinfo Hematos IIG)
All patients with hematopoietic neoplasia or related conditions: leukemias, lymphomas, myelodysplastic states, myeloproliferative states (polycythemia rubra vera, primary thrombocythemia, agnogenic myeloid metaplasia/myelofibrosis), aplastic anemia
All patients with sickle cell anemia, thalassemia, sickle-thalassemia
Selection of Donor Units in these situations:
Match R1R1 when possible
Match K-negative for K-negative patients
Match rr for females <50 and children < 18 years
There is no need to routinely match R1r, R2r, Ror, R1R2, or R2R2 genotypes with theses corresponding donor typesexcept for sickle cell patients (item #5)
Match exactly extended Rh phenotype and Kell for sickle cell patients (CcEeK): e.g. evenR2R2 for R2R2
Hemolytic Disease of the Fetus/Newborn:
If the neonatal eluate or mother at term shows a clinically significant antibody, phenotype the baby for the corresponding antigen (e.g anti-Fya present, type baby for Fya)
Extended antigen typing beyond Rh/Kell (e.g. k (cellano), Kpa, Kpb, Fya, Fyb, Jka, Jkb, MNSs, etc.) should be performed in the following cases:
Sickle anemia, thalassemias, sickle-thalassemia
Any antibody workup where the pattern is nonspecific
Verify any antibody specificities by phenotyping the patient (e.g., if anti-M identified, do M typing)
Cw phenotyping is not required unless anti-Cw is suspected.
Genotyping may be considered if:
Recently transfused patient and the extended typing is needed for antibody identification
Ambiguous or unusual typing results (e.g. M-neg N-neg, lacking CcEe antigens by serologic typing)
When NOT to phenotype:
RBC transfusions within 3 months
Previous phenotype in Medinfo Hematos IIG (unless the patient subsequently has had a stem cell transplant)
Any other cases in which the Head, Transfusion Medicine or the other transfusion medicine physician requests additional typing.
Prepared By:
Zeyd Merenkov, MD, FCAP, FASCP
Senior Consultant/Division Head, Transfusion Medicine
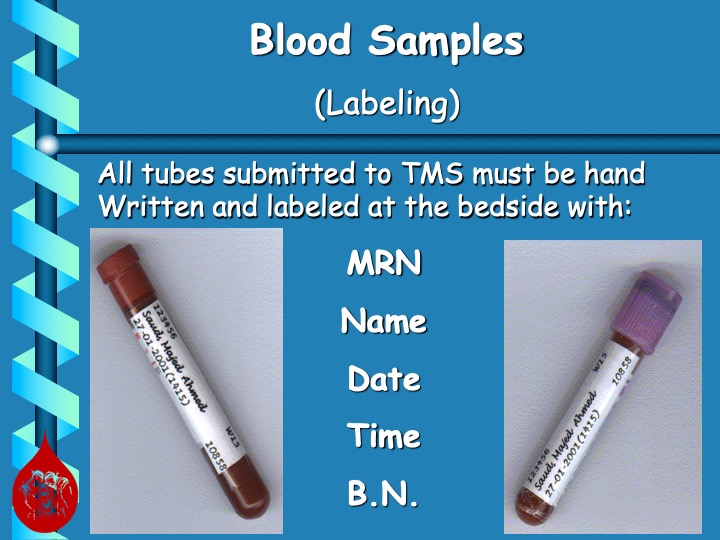
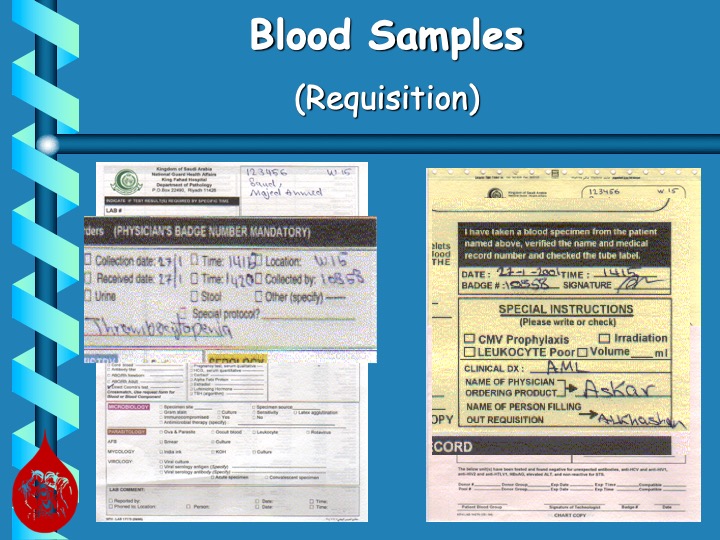
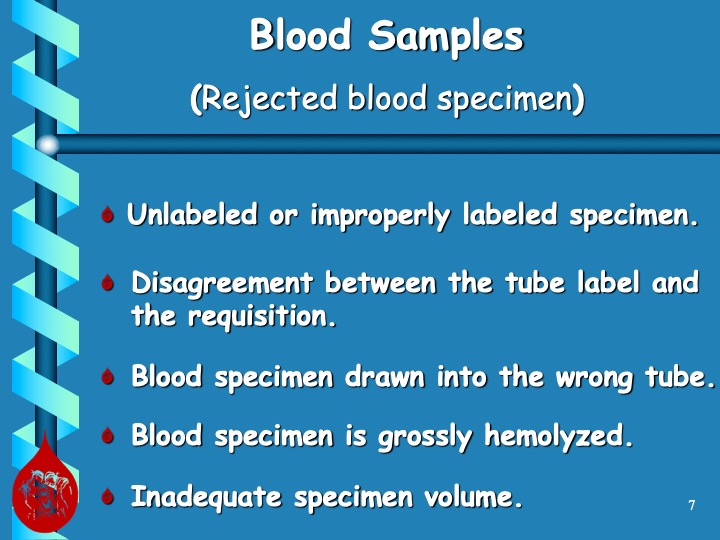
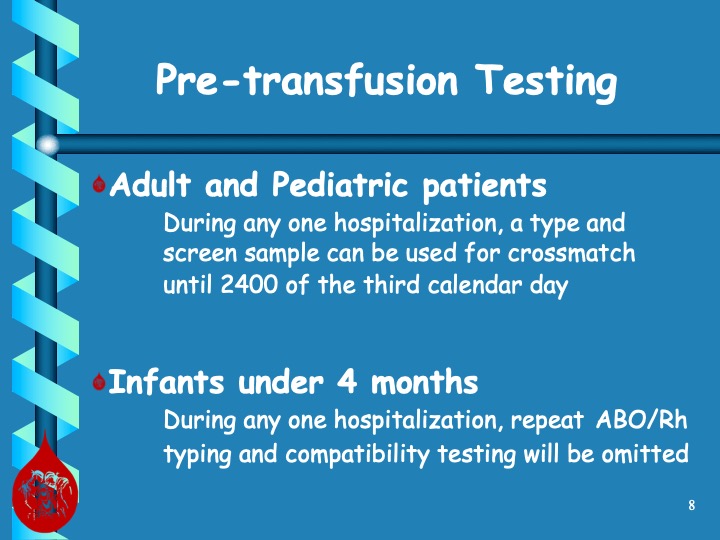
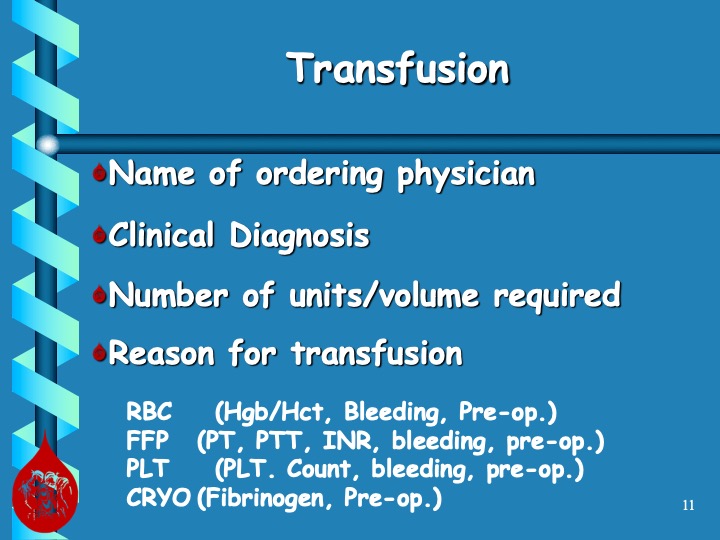
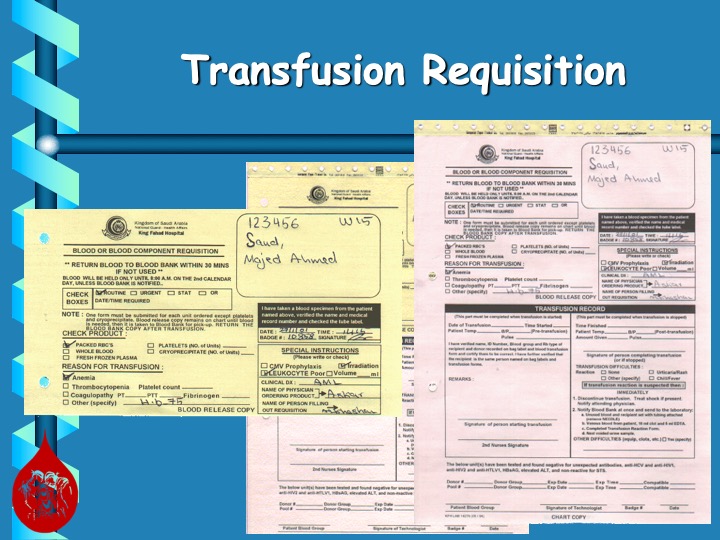
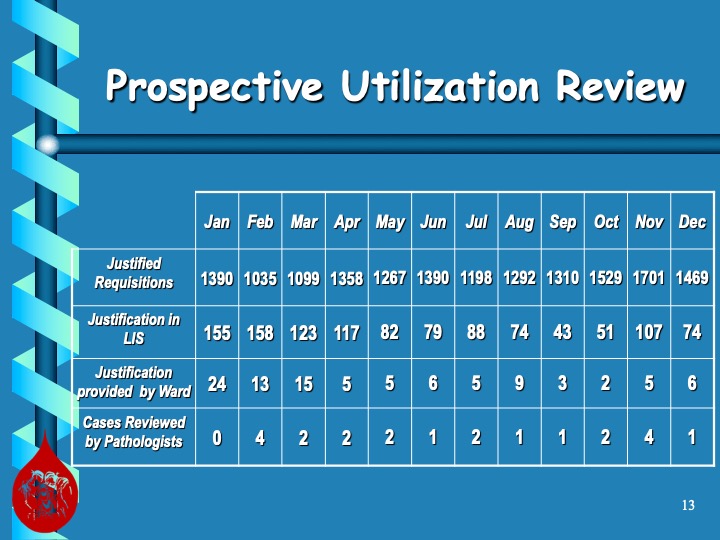
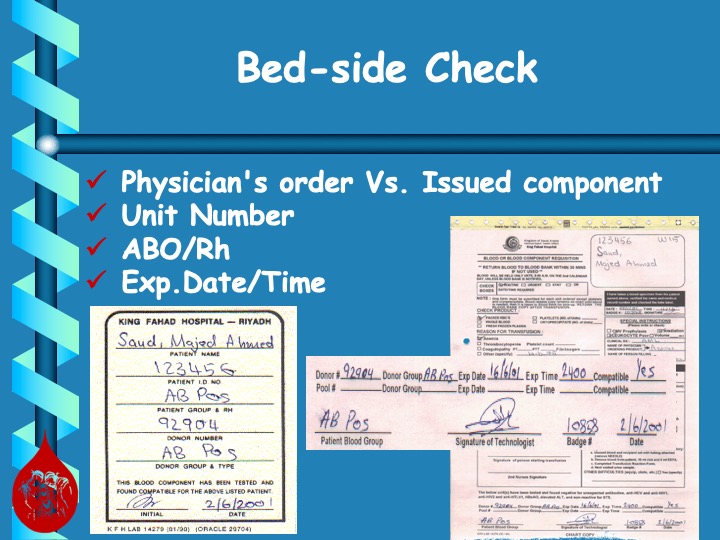
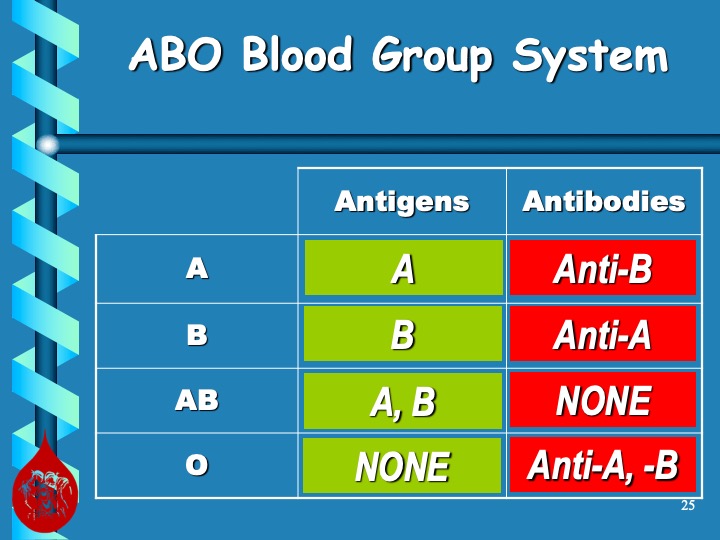
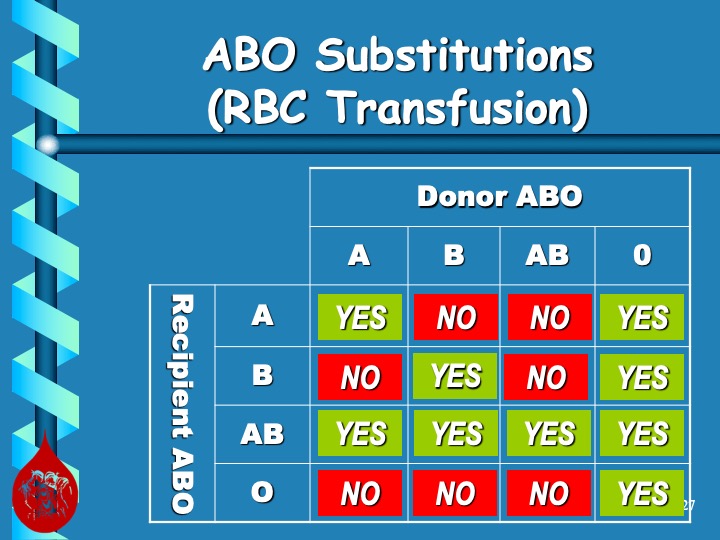
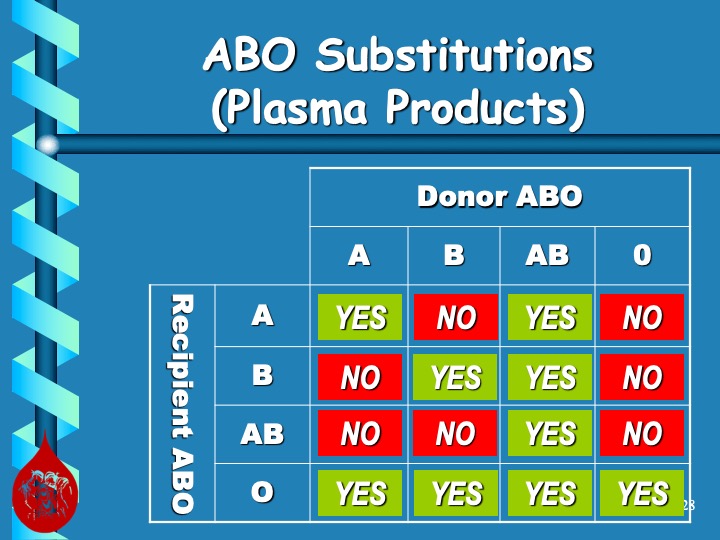
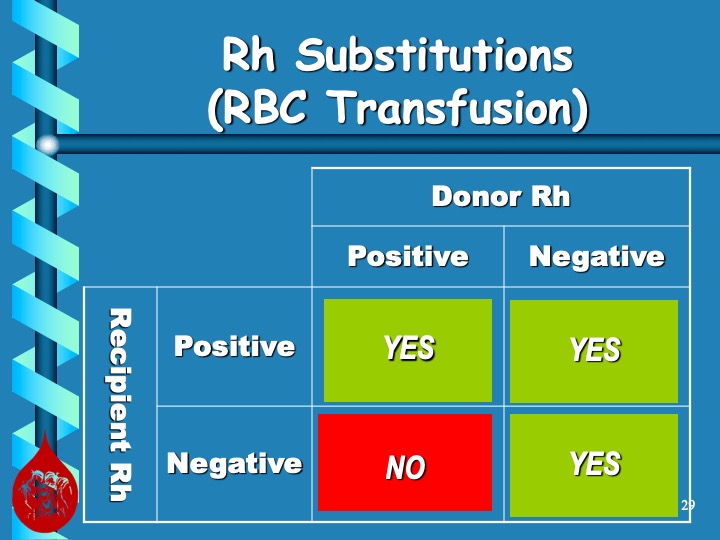
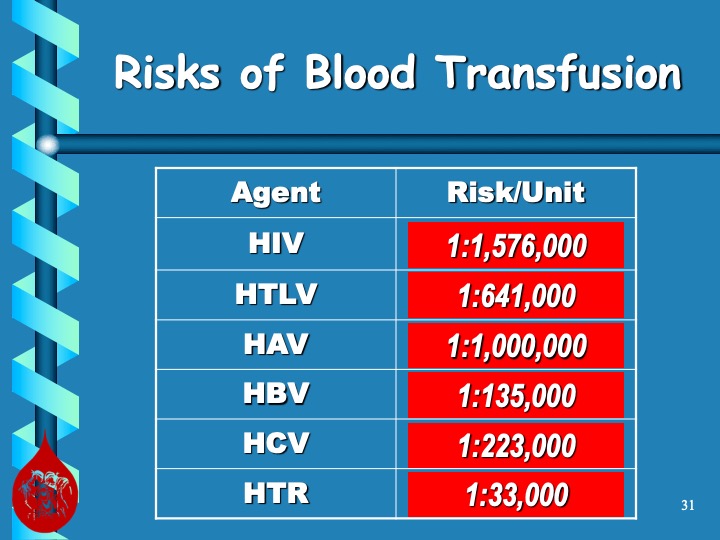
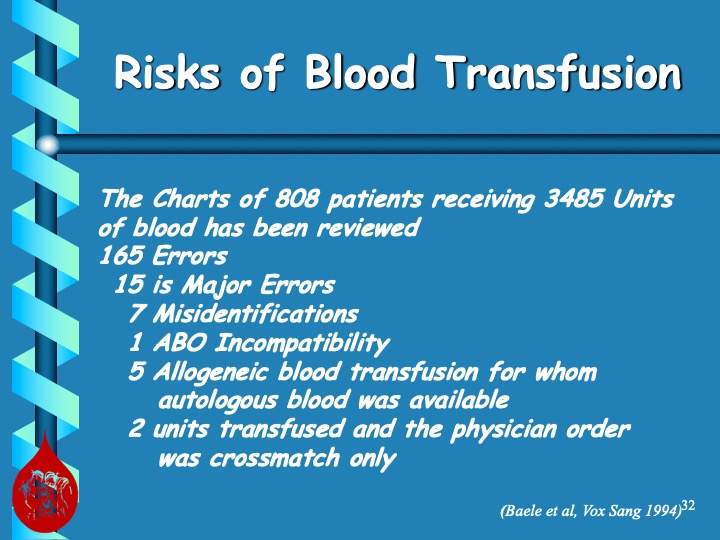
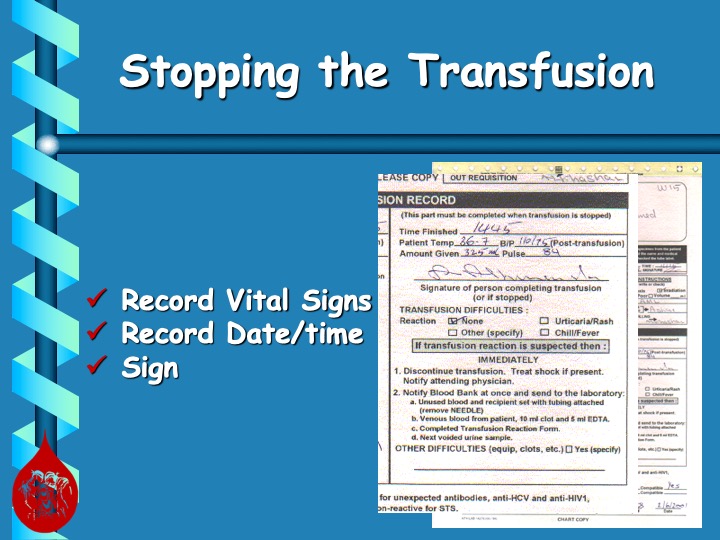
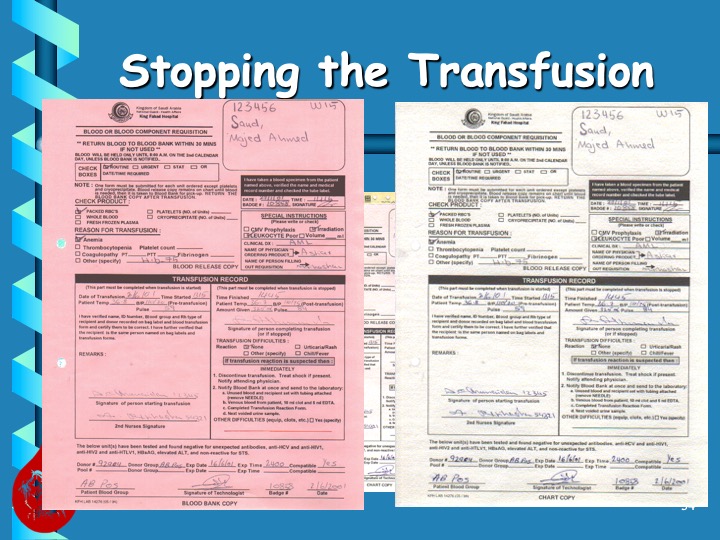
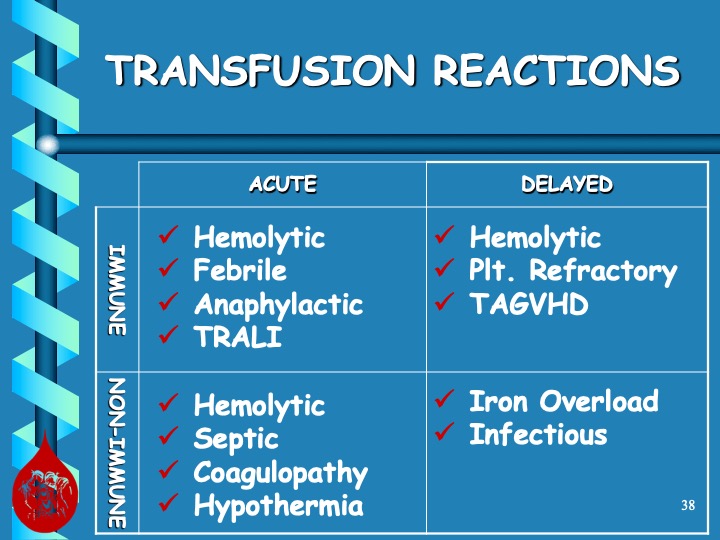
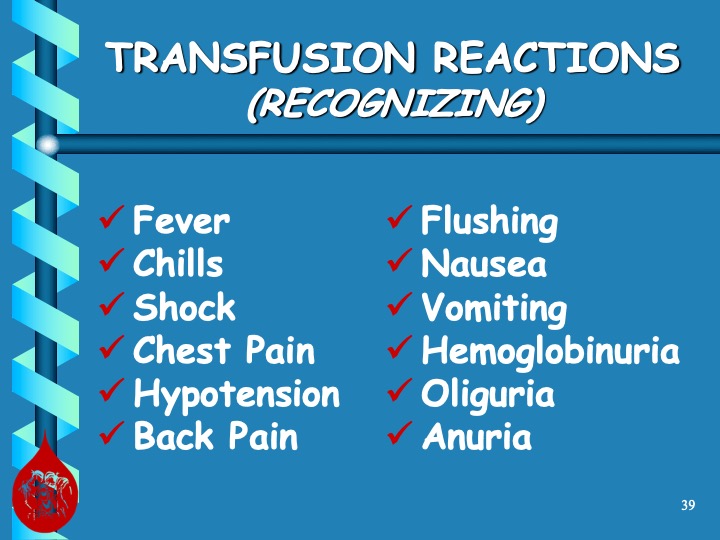
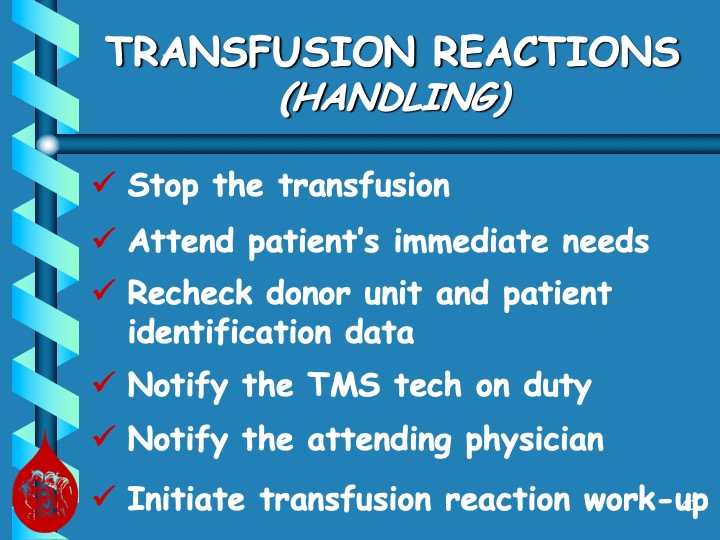
When I was affiliated with National Guard Health Affairs in Riyadh, my staff and I gave weekly new-arrival nursing orientations. The attached PowerPoint file from 2004 shows the manual system in effect at the time, but it is still illustrative to acquaint new staff on the hospital blood bank as it relates to their nursing duties, including specimen collection, pick up and transfusion of blood components, and adverse effects of transfusion.
I wish to give full credit to Mr. Abdullah Al Khashan, who prepared this file in conjunction with Ms. Editha Durante, the Transfusion Clinical Resource Nurse. The three of us used to rotate giving this lecture. This is my version of their presentation (with some minor formatting changes).
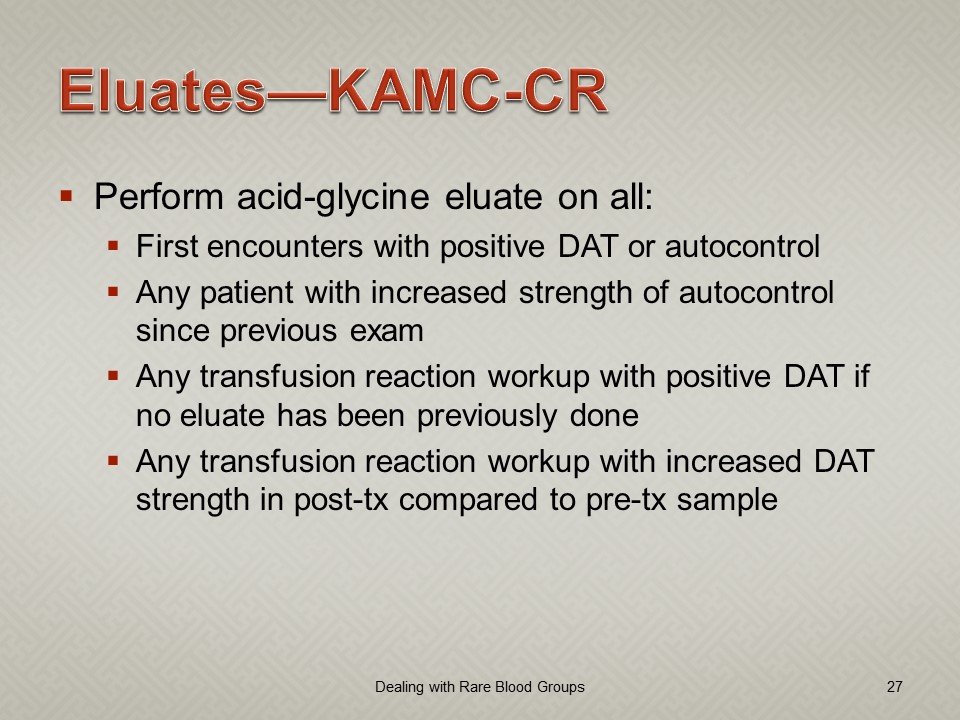
I cannot emphasize enough proper technique in doing the washing during the elution process. We are usually concerned about too little washing and thus possibly residual reactions in the last wash. However, aggressive overwashing may remove the bound antibody resulting in a negative result.
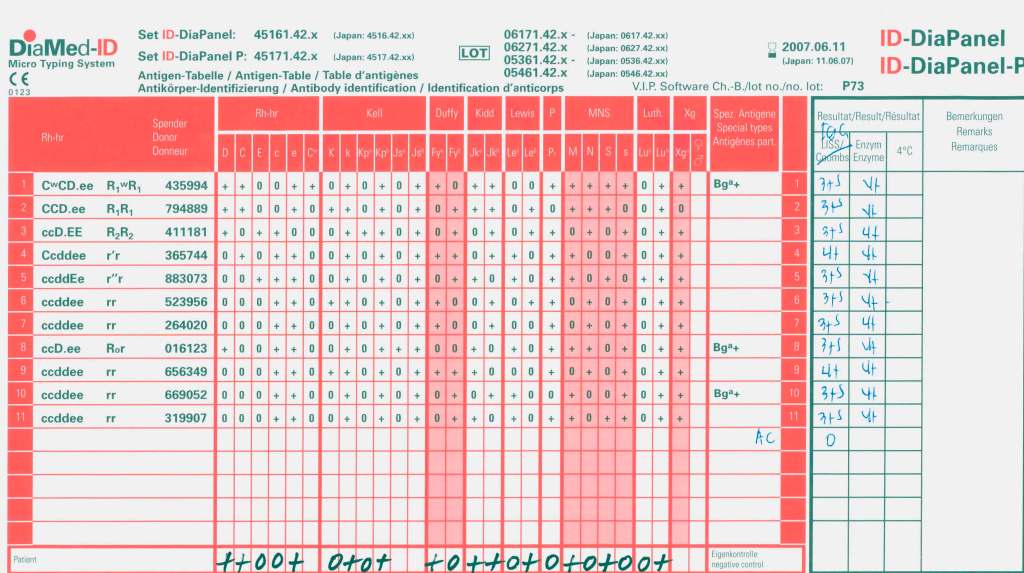
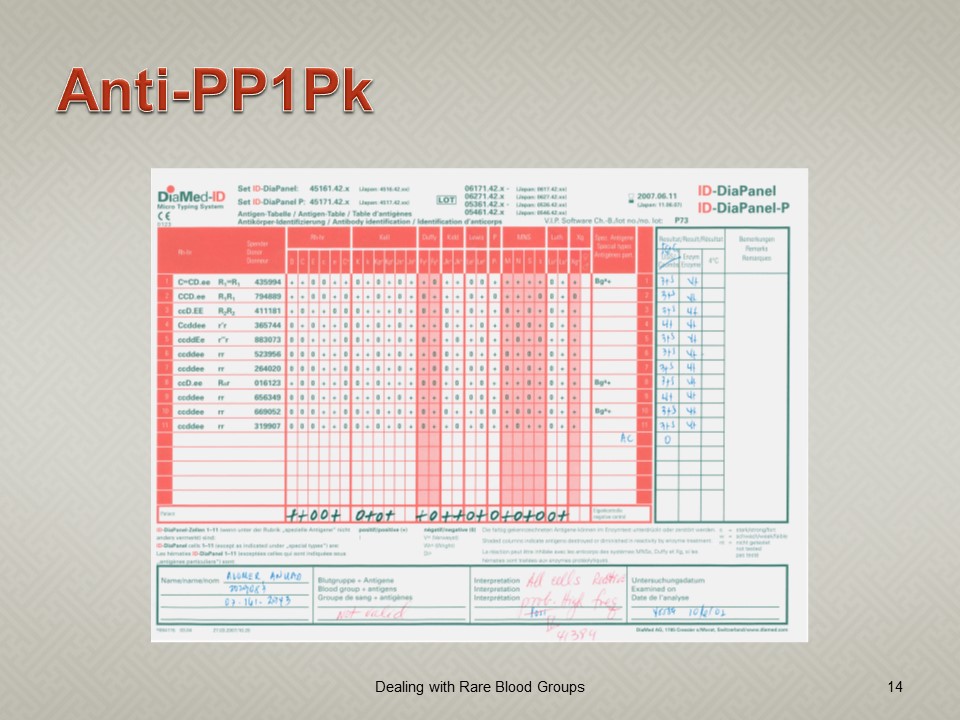
Here is an example of anti-PP1Pk (alias anti-Tja). The mother’s panel shows an antibody to a high prevalence/incidence antigen with negative autocontrol and no lability at enzyme phase:
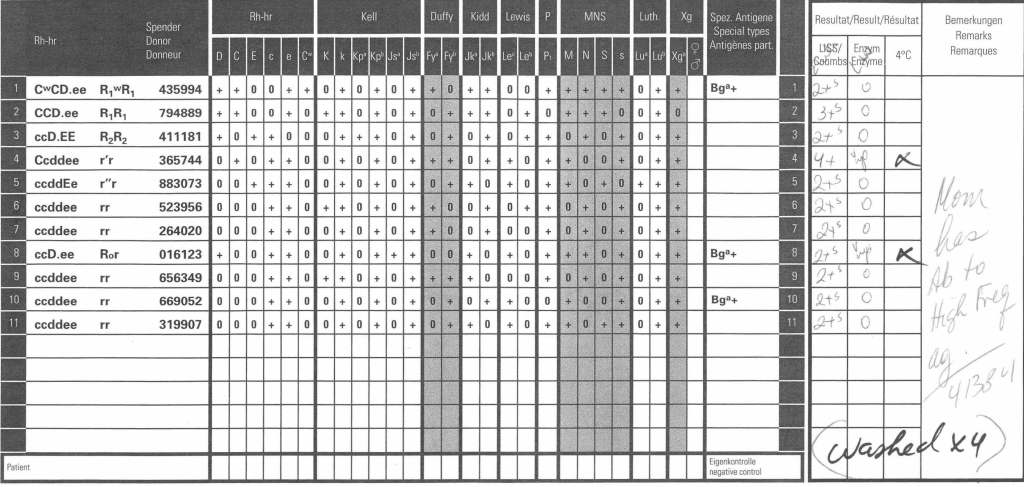
The neonate’s DAT was weak positive at polyspecific and IgG monospecific phases. An eluate was performed. Here is the result after washing four (4) times:
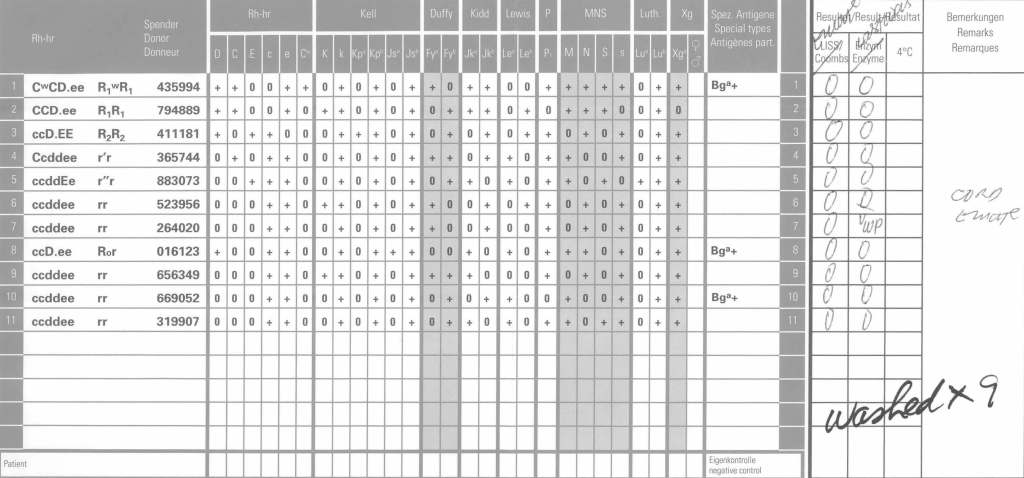
Since 2 cells in the last wash were very weakly positive, the washing was continued for a total of 9 times with the following results:
Even then there was very weak positivity in one cell, but the eluate was negative. We had washed away the attached antibodies.
The direct antiglobulin test DAT may be the first or last place that a delayed hemolytic transfusion reaction can be detected. In my practice, I always performed it the first time I encountered a patient with a positive DAT. If the subsequent DAT testing is of the same strength and there is no change in the clinical status of the patient, then I might empirically repeat the elution after 14 days, i.e. just when new antibody emergence may be detected.
In summary, my criteria for elution after a positive DAT are:
First patient encounter with a positive DAT
At least 14 days since the previous elution
DAT strength has increased since the previous exam (at least 1+ increase in strength in either IgG or C3)
Patient shows evidence of hemolysis
Suspected cases of drug-related hemolysis
Transfusion Medicine physician specifically orders it otherwise
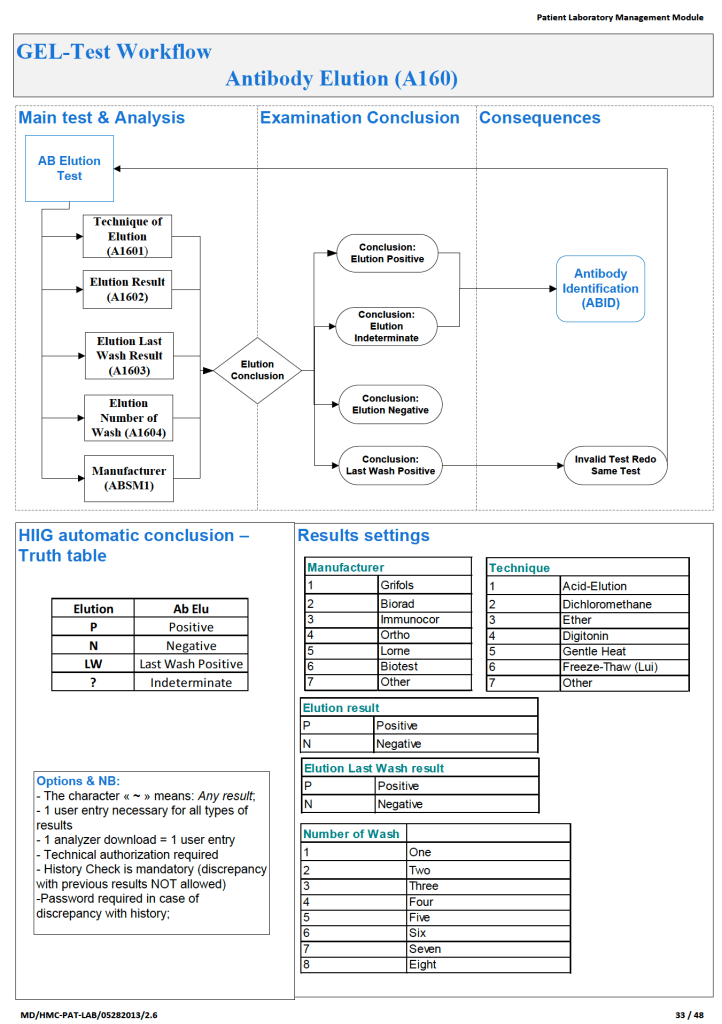
In the software processes, the following parameters were recorded:
Technique of elution (acid glycine, dichloromethane, digitonin, ether, etc.)
Number of washes (too many may remove the antibody from the RBCs)
Last wash result (must be negative to accept conclusion)
Manufacturer of the elution kit (if any)
Elution result based on panel testing
Note:
All indeterminate or positive eluates would trigger an antibody identification.
All results would be reviewed by me or the covering Transfusion Medicine physician. A comment would be entered into the results that could be viewed by the clinician either directly from Medinfo or through the hospital information system.
If the DAT was only positive for complement, it was up to the Transfusion Medicine Consultant to decide whether to proceed with elution. Personally, I would usually proceed because the eluate is more concentrated and may occasionally detect an antibody that was not noted in the patient’s plasma.
The attached Medinfo workflow shows the process designed by me for use at HMC Doha.
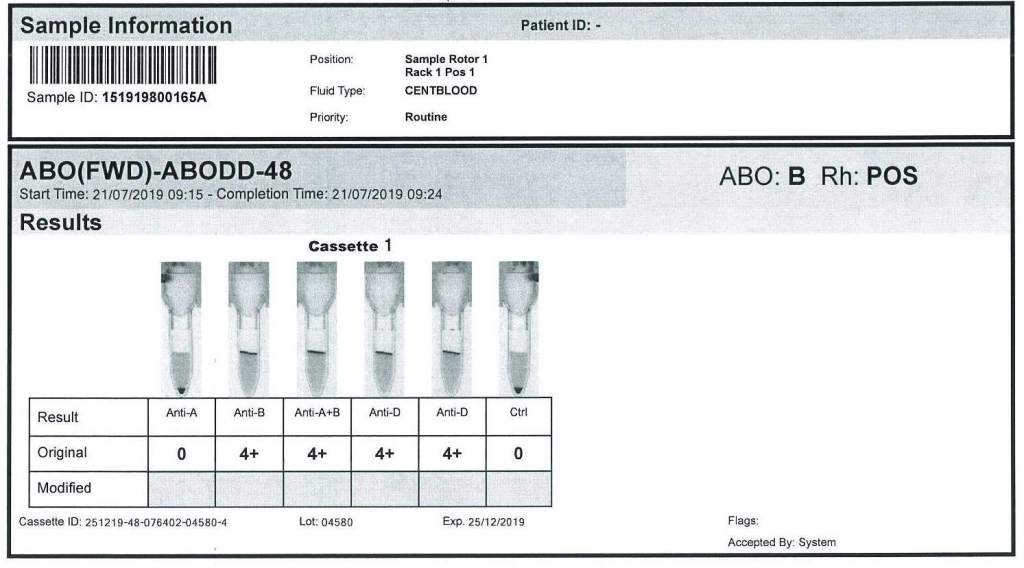
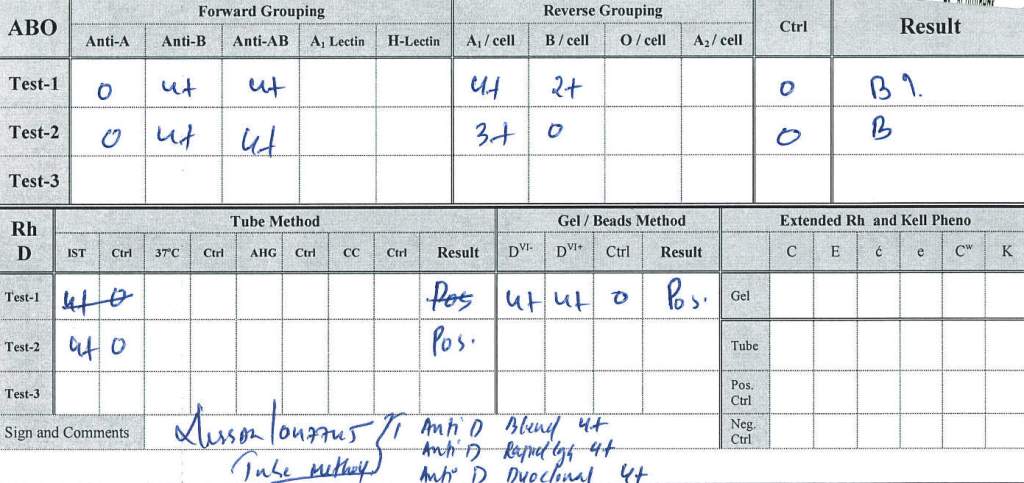
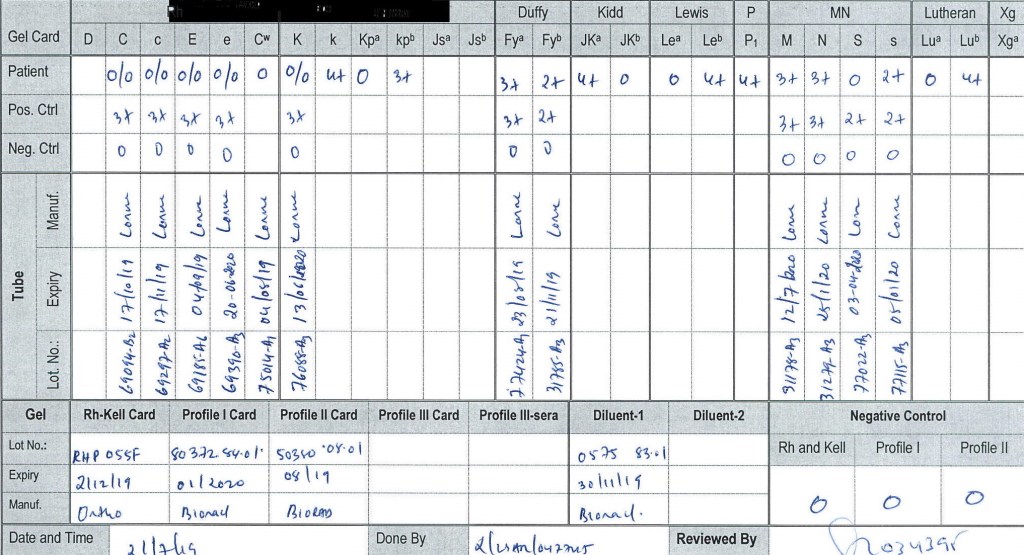
A 31 year old Indian female’s prenatal testing results follow:
ABO Group B—unremarkable pattern
Rh(D) positive by both DVI+ and DVI- reagents by multiple manufacturers, both with gel and tube methods
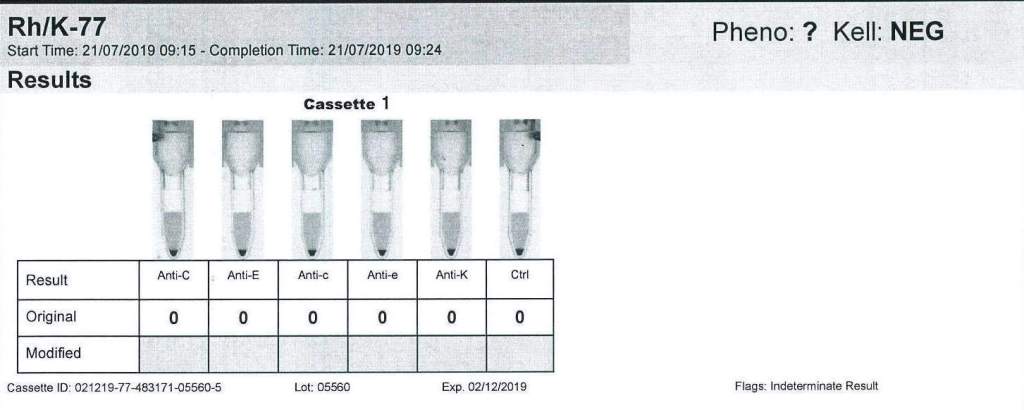
Extended Rh and Kell:
No reactions for C, c, E, e; Kell negative
(These results were confirmed by multiple manufacturer’s tube and gel reagents)
Extended Antigen Typings:
From the phenotypic data, we could already rule out anti-H, k, PP1Pk, U, and some unusual MN system variants found in the region.
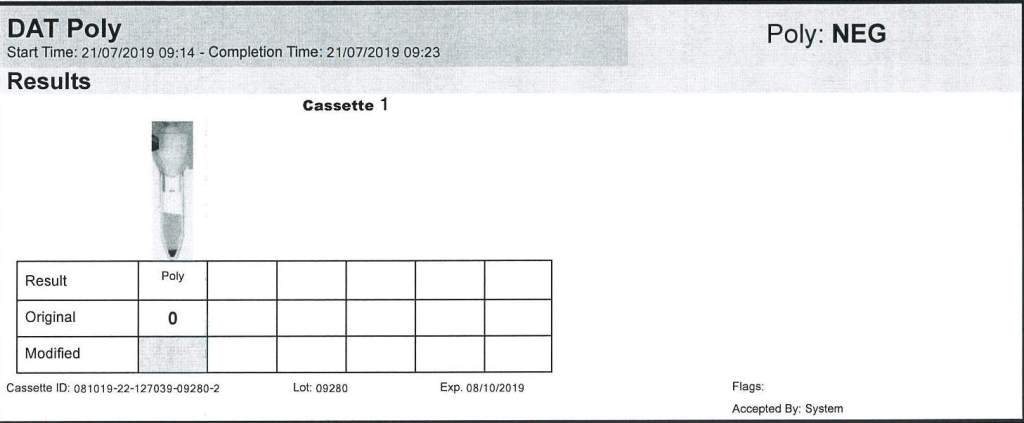
DAT: Polyspecific and monospecific IgG, C3b/C3d were all negative.
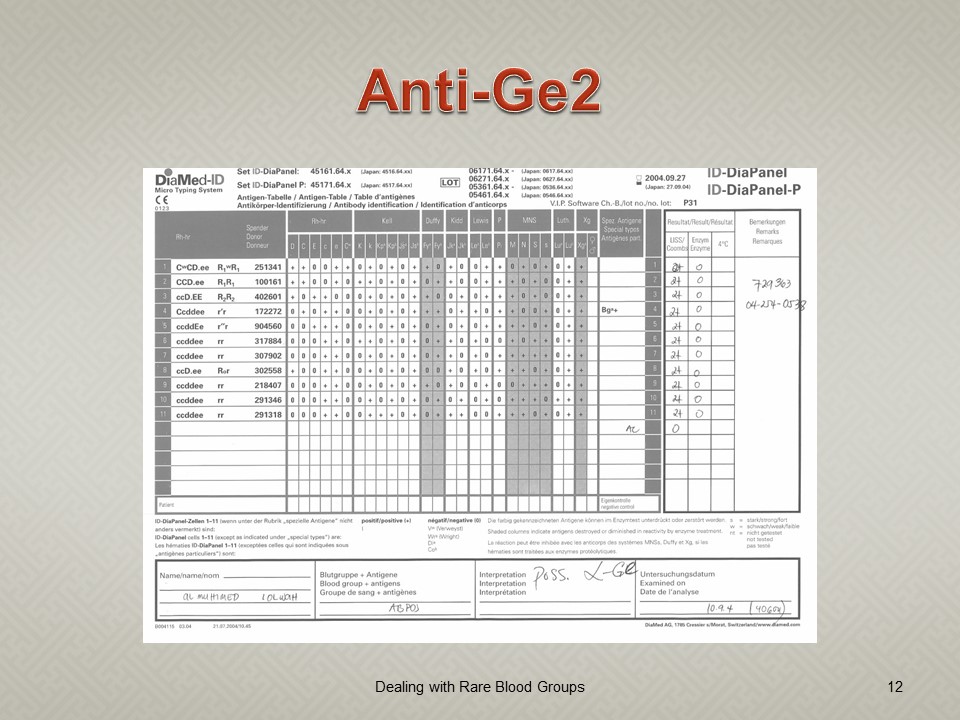
Antibody Screen: 4+ panreactive
Antibody Panel: 4+ panreactive, autocontrol negative, also 4+ by enzyme
Clinical Course:
At the time of the prenatal specimen, we informed the clinicians that we did not know the significance of the panreactive antibody. We recommended screening any blood relatives and autologous blood collection. We also recommended genotyping of the mother.
Several months later the patient presented in labor with severe fetal hydrops. The previous workup was repeated and confirmed. Neither genotyping or autologous collection had been done. No relatives had the same phenotype, and none were compatible with the mother.
We now knew that the antibody was highly clinically significant and very dangerous. With the permission of the treating obstetrician, the mother’s blood was used for transfusion of the newborn (washed, irradiated). Both mother and baby were group B positive.
To date of my departure from HMC Doha, the antibody had not been characterized, but we continued to recommend genotyping and autologous collection from the mother.
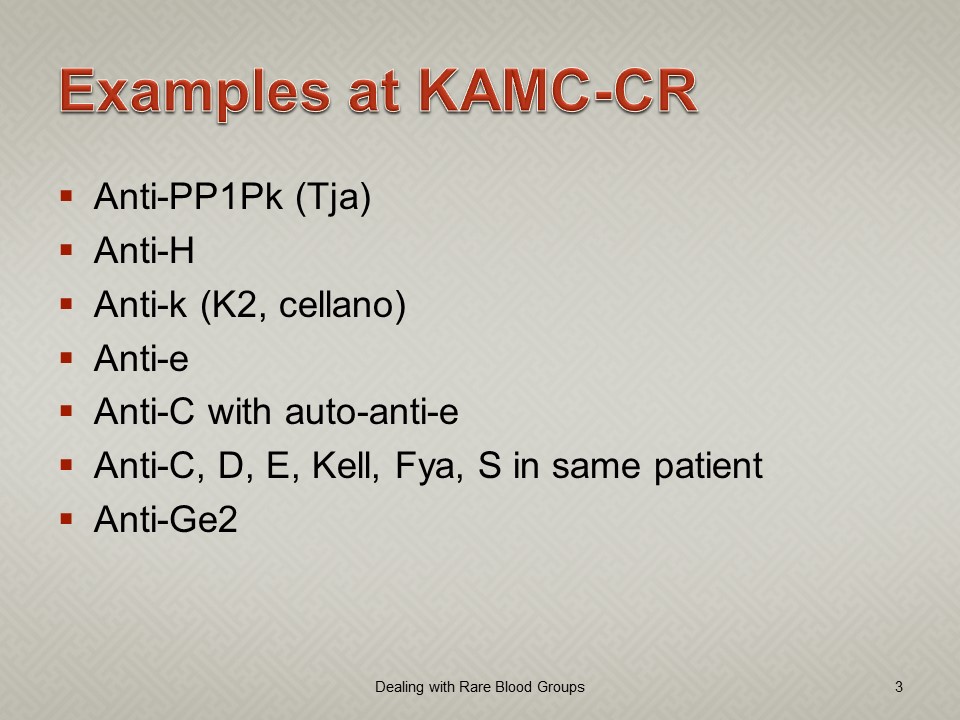
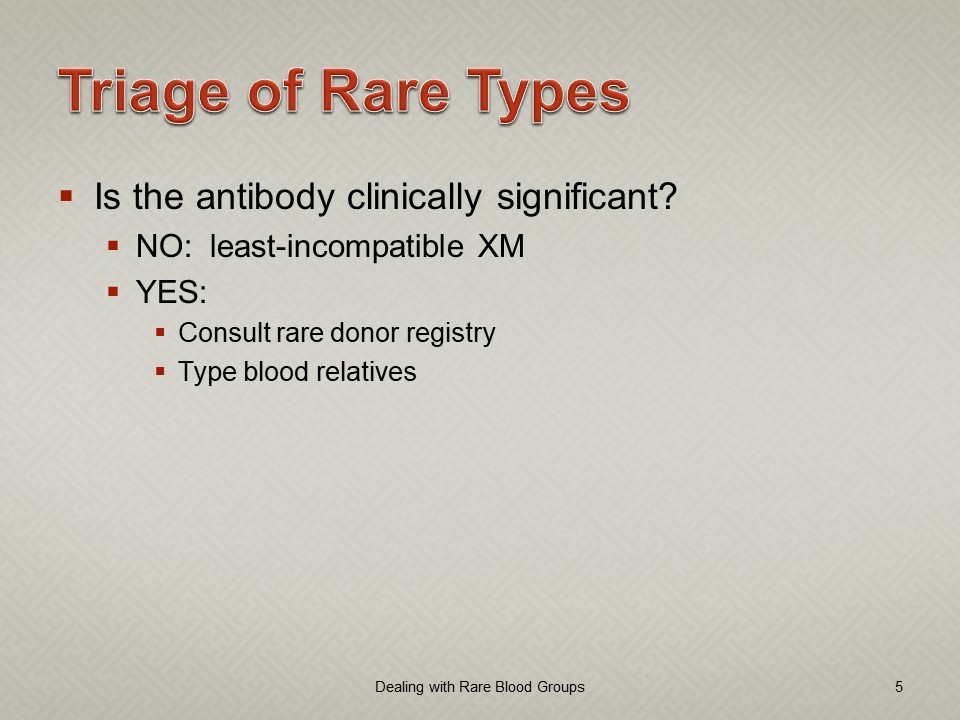
This is a presentation from my time at NGHA Riyadh on a strategy for rare RBC types in the Gulf/Middle East region. This is my practical method for dealing with these antibodies.
As regards prophylactic antigen matching, my remarks are based on the antibodies observed in my region. I know that some would match at least Duffy antigens, but emergence of anti-Fya and anti-Fyb have not been common in my practice.
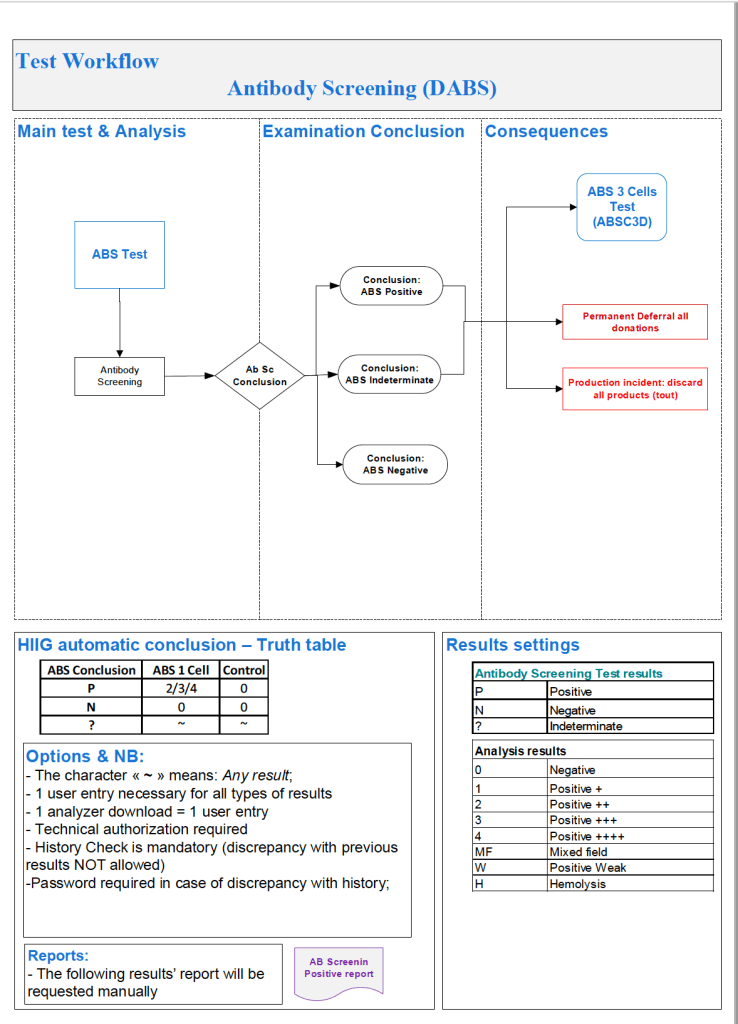
Based on the previous software post, I use the antiglobulin test algorithms to construct the antibody screen ABS, namely an INDIRECT antiglobulin test, i.e. incubate reagent red cells with the donor or patient’s plasma and then perform the DAT. At HMC Doha and at NGHA in Riyadh, we mainly used three cell screens (no pooled cells for donors). The reactions could be machine-read (we had the interface) but the interpretation of the specificities found was done manually.
Donor ABS:
We screened all donors for irregular antibodies. I disqualified most donor with non-negative screens from donation (my personal preference). However, for nonspecific antibodies, I might elect to discard the current collection and then reassess the donor’s status at the next encounter. Not everyone would agree with this most restrictive approach but I would not use the platelets or plasma in such situations. I also did not use the donor RBCs, even though they were in SAGM—but I could elect to override this decision in Medinfo if there were a rare blood group (e.g. r’r’).
Example #1 (following) shows a sample donor ABS process:
Patient ABS:
Excluding emergency release, if the patient did not qualify for the electronic (computer) crossmatch, then the AHG crossmatch was required. A three-cell antibody screen including R1R1, R2R2, and rr RBCs was used that usually included cells homozygous for the Kell, Duffy, Kidd, MNS antigens. For any case with a non-negative antibody screen, either donor or patient, an antibody identification was performed.
Note that I did not use any other software to make antibody identifications. I required my technologists to be proficient in identifying basic and intermediate-level testing. The actual antigen makeup of each lot number of antibody screen or identification panel was NOT stored in Medinfo. We scanned the antibody screen and panel workups and could store those in Medinfo.
Example #2 (following) shows a sample patient ABS process:
Patient ABS Fix for Interface Regression Caused by HIS:
Regretfully, with a software update from the hospital information system HIS vendor, a major regression occurred. It would not discard results from Medinfo if more than one antibody result (e.g. anti-E and anti-c) was sent back. We could see the results in Medinfo, but those outside Transfusion Medicine could not see antibody results. The entire interface for antibody identification had to be rewritten so that the HIS would see each result uniquely and thus all results could be sent back to it.
Regression Example:
Anti-Kell sent from Medinfo: one antibody result, HIS would store and show this result.
Anti-E and anti-c sent from Medinfo: No antibody results shown, both results kicked out.
Regression Fix:
Anti-E sent as Method Type1-Antibody 1 and anti-c sent as Method Type 1-Antibody 2: both results displayed in HIS.