Base Medical Technologist Assessment Examination

Background:

I prepared this exam for base transfusion service technologists and candidates. For prospective new staff, I would be more lenient and use it as a projective exercise in the potential abilities. However, for staff working one year in my blood bank, I expected a higher score. Each and every problem is based on issues they would actually encounter at work–nothing esoteric.

Answer the following questions:

  1. What is the blood type in each of the following results:
Anti-AAnti-BA1 cellsB cellsType?  
  4+  0  0  3+ 
  0  4+  3+  0 
ABO Typing Problems
  1. You are signing out a unit of FFP, Group A Pos, Unit #23556 for Mohd Ahmad Ali Al Harbi, MRN# 729887 in Ward 21.  The nurse comes with the requisition to pick up the thawed unit.  The requisition says to pick up the thawed FFP for Mohd Ali Ahmad Al Harbi, MRN# 728987 in Ward 21.  Can you release the unit?  Explain.
  1. The antibody screen and crossmatch results are shown on the following IgG Coombs card (Biorad):
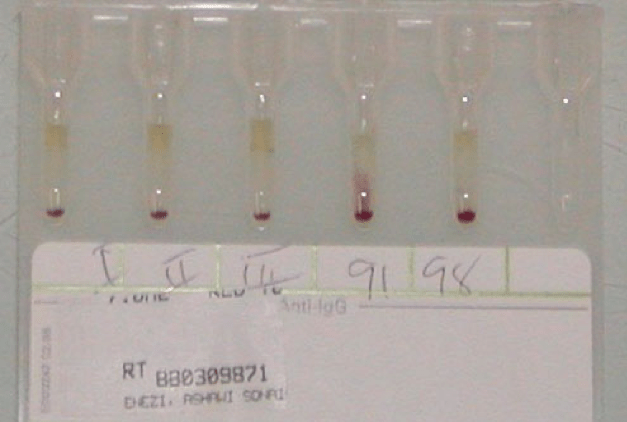
The reactions I-II-III are the antibody screen results.  Note the crossmatches # 91 and 98.  Which one(s) is/are compatible?

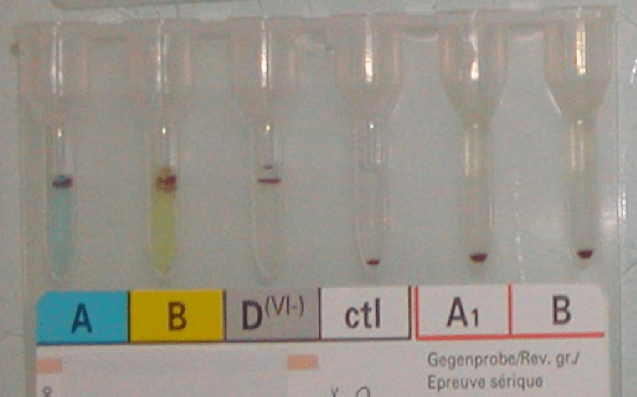
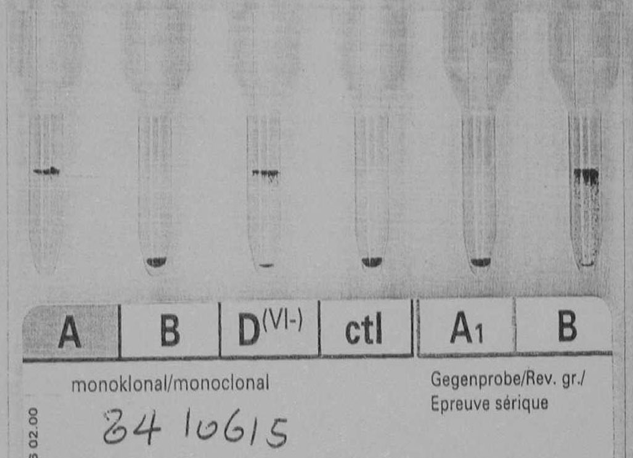
  1. The following are actual ABO/D typing results with the Diamed (Biorad) reagents.  What are the ABO/D types?
  1. The Blood Bank is severely short of AB packed cells and AB plasma.  What other blood types can you safely issue?

Request for AB packed RBCs:  Permissible substitutions are:

Request for AB plasma:  Permissible substitutions are:

  1. A specimen for crossmatching is drawn at 7:30 a.m. on 26/10/20.  When does it expire?
  1. Emergency blood, group O positive is issued for a 30 year-old male victim of a traffic accident.  You receive the specimen and complete the crossmatching.  You find the unit is incompatible.  What do you do?
  2. A patient has anti-C antibody.  How do select the appropriate type of blood to give?  Select any or all that apply:
    1. First crossmatch the requested number of units, then if compatible, release them.
    2. First crossmatch the requested number of units, then antigen type them for “C”, release only the ones that are C-negative.
    3. First screen for C-negative units, then crossmatch and release compatible units.
    4. None of the above
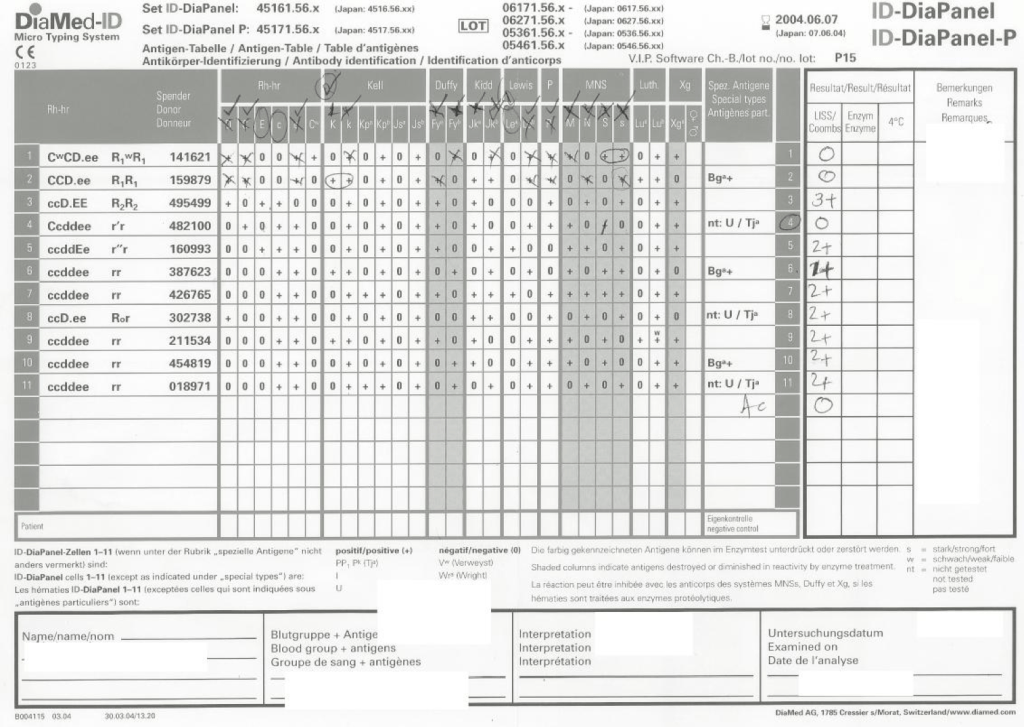
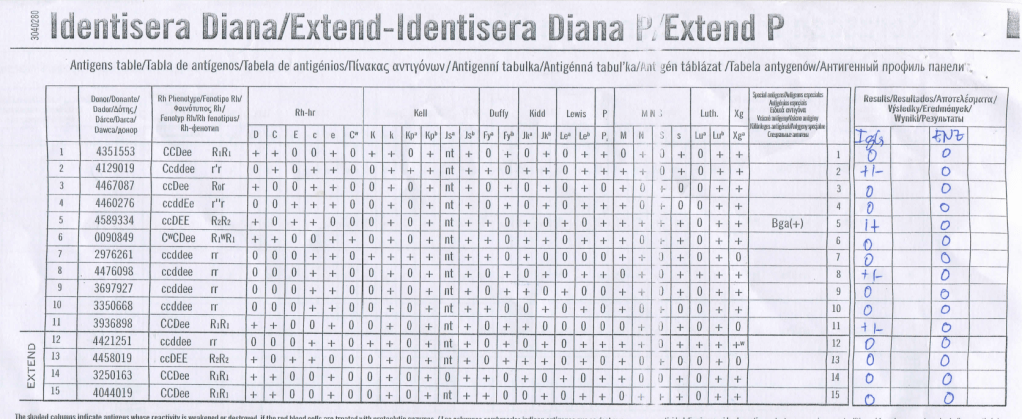
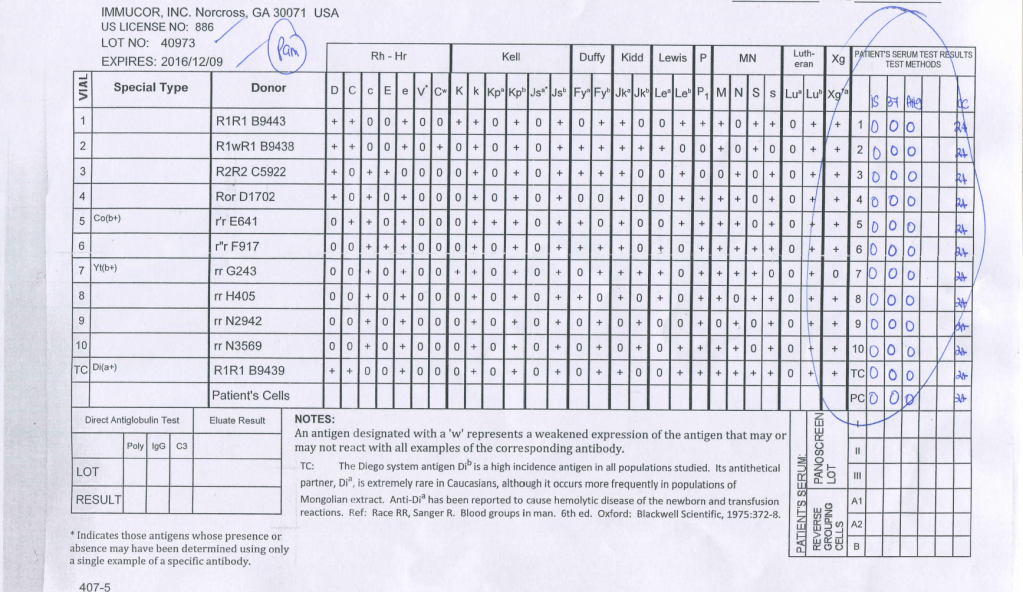
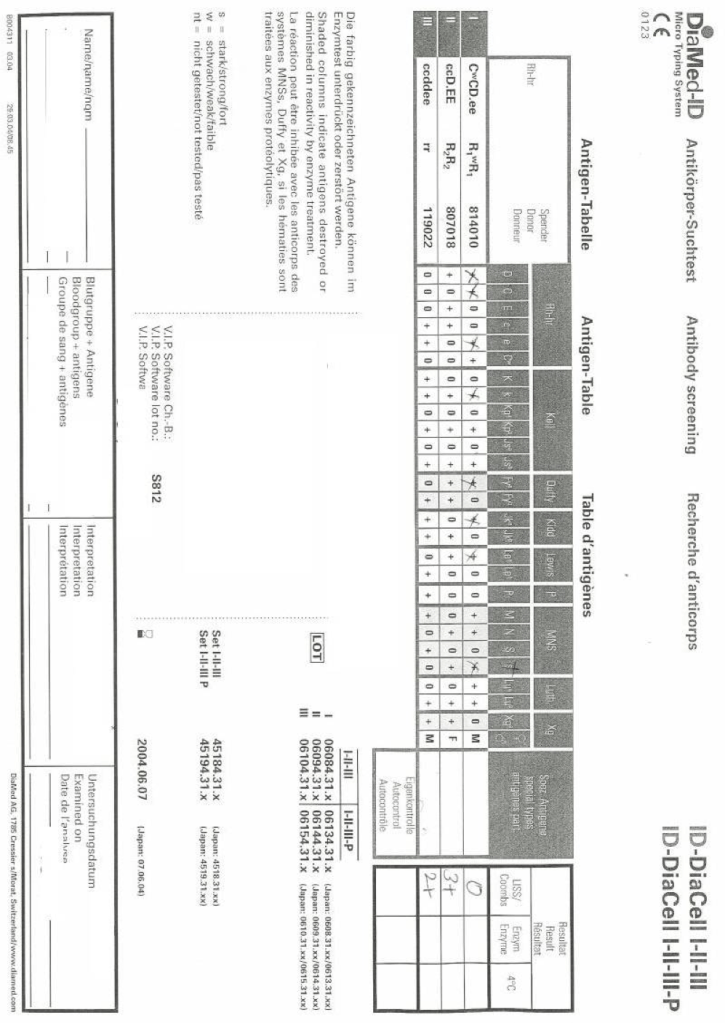
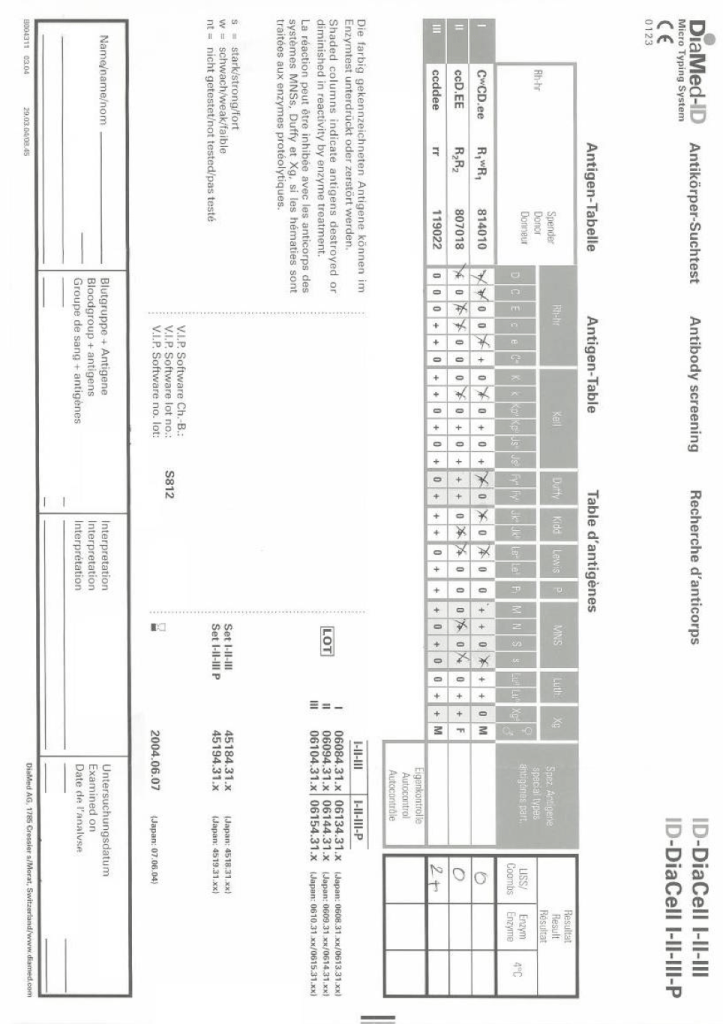
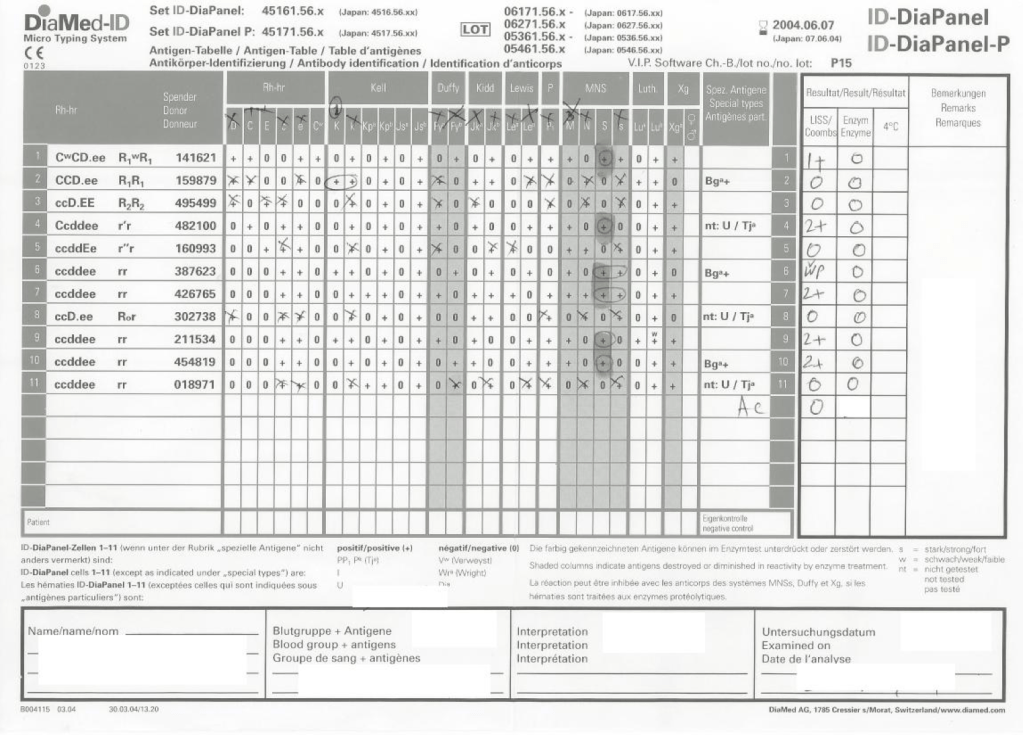
  3. Evaluate the attached antibody screening and panel results:

37 year old pregnant female, no previous history:
26 year old G3P3 pregnant female in labor, O-positive, no previous transfusion or antibody history:
19/10/20
Opinion: Vendor Compatibility with ISBT Codes

While I was  Division Head, Laboratory Information Systems LIS elsewhere, we serviced a client hospital not using Medinfo for its patient hospital blood/transfusion services.  It used the blood bank module of a hospital information system’s laboratory system.

In their service level agreement, they wanted a complete list of all the ISBT product E codes that we used.  I found this strange and told them their system must have access to the ISBT database so they should have no problem in reading our codes directly.

The same hospital system was in use for our hospital system (excluding our blood banks, which used Medinfo and had no such problems.)  I discovered that this hospital system could NOT read any ISBT codes natively for the end-users, e.g. departments outside the blood bank.  Without informing us, the nursing staff were manually entering “something” into their system.   That something could be anything:  the system would accept any series of alphanumeric characters.  They could select any type for each component (e.g. RBC for a platelet, plasma for an RBC, etc.).  They had no reliable record of transfusion!

In fact, in that hospital information system, ISBT codes could only be read in their blood bank module, which we did not use at all.  That vendor subsequently purchased another software to read the labels, but I discovered that the new “solution” software still could not directly access the ISBT database!!  They still had no functionality to read ISBT labels on the wards!!  You still had to hard-code it into their system.

Thus, we were forced to give the new client a list of our current E codes.  I warned them that we did change these codes (e.g. when we adopted platelet additive solution).  It was their responsibility to change the “hard code” into their blood bank module of that vendor.

As regards our hospital information system, we had to “hard code” the ISBT codes into the order requests so they could use that to document the transfusion.  We also had to provide the descriptor for each and every code.

To this day, I am astounded that a modern hospital system still cannot read ISBT codes natively.  Surely, they could license a copy of the ISBT database—or at least let the end-user client license it and upload it into their system.

I am skeptical of a “one-size-fits-all” comprehensive, Swiss Army Knife like software that has some limited functionalities but lacks the details needed for actually using blood components.  I wonder if the compromises made to build this system make it similarly mediocre for other functionalities outside the blood bank sphere.

I consider myself very fortunate to have elected NOT to use this patient transfusion service module and go with a full-feature blood bank system.

Conclusion:

Be careful about trusting the vendor’s promises.  Check to see how they handle the ISBT labels.

17/10/20

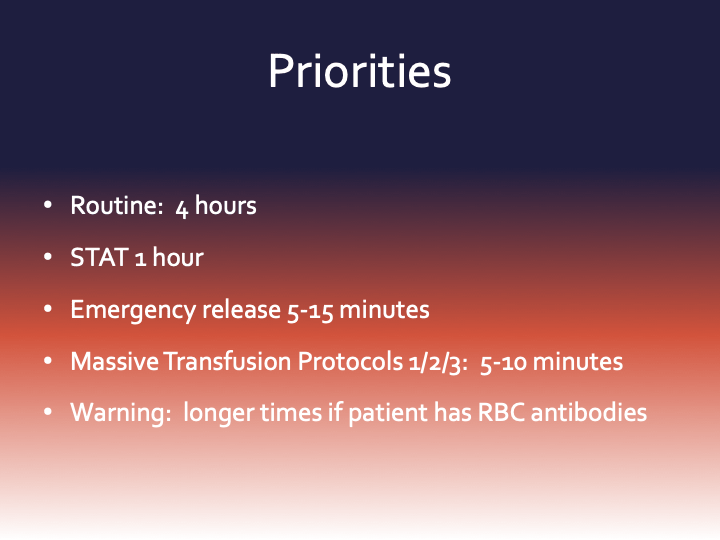
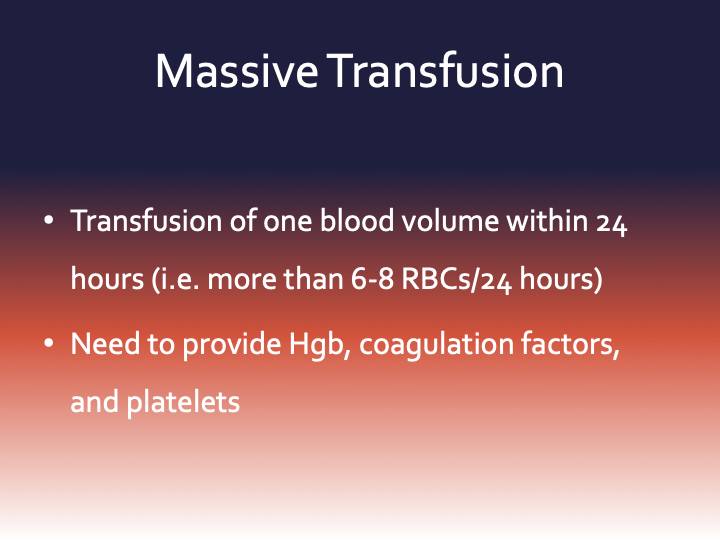
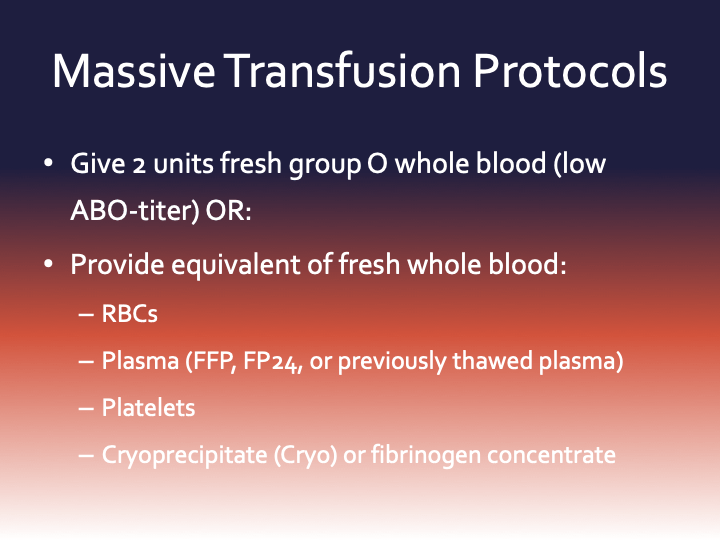
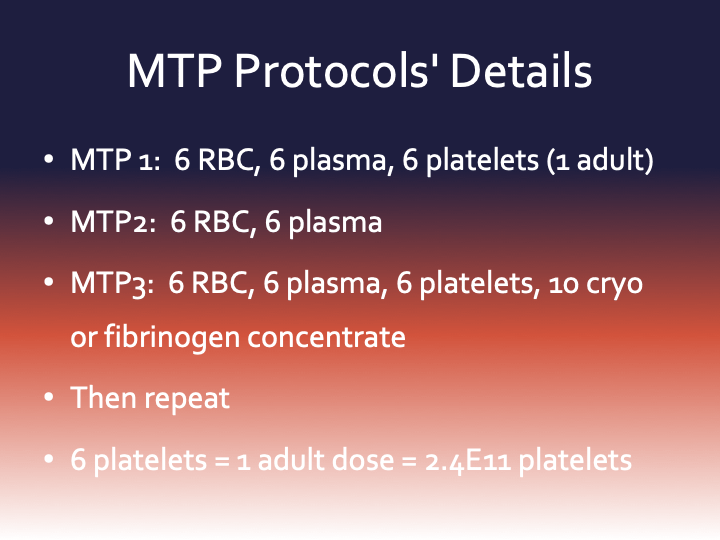
Massive Transfusion Protocols

This is a sample massive transfusion protocol originally prepared at HMC Doha with my input and Division Head, Transfusion Medicine. I have updated it to include use of fibrinogen concentrate and the option to use fresh whole blood (group O, < 14 day old in SAGM, low ABO titer IgM < 1:256).

The volumes for blood components is based on our automated production system Reveos with the RBCs in SAGM, platelets in Mirasol and additive solution, and plasma in Mirasol.

Opinion: Advantages of Using Both the Medinfo Donor and Patient Modules

The donor module of Medinfo includes recruitment, logistics, registration, donor screening, collection, marker testing, donor immunohematology, and component production.  There is also a module for inter-depot transfer of blood units from the donor center to the hospital end-users.

The patient module includes patient testing (ABO/D typing, antibody screen, antibody identification), direct antiglobulin test, elution, component modification (washing, aliquoting, pooling), allocation/reservation of blood components for a patient, release of blood components, and their return.

Some sites elect to use their laboratory system’s blood bank module in conjunction with Medinfo donor module.  In this case, they receive each and every unit into their laboratory blood bank module and do all patient activities in it.  There is no link between patient and donor module.  They will have to monitor and transfer inventories in their laboratory system.

At a site using integrating both the donor and patient modules of Medinfo, they will be able to track units across the system to any hospital blood bank.  They will have access to the rules-based system to generate algorithms for use of blood components based on user-defined criteria.  They can instantly perform look back of donor units associated with adverse effects, and be able to rapidly quarantine components subject to recall from the manufacturer or product incidents.  Here are some examples of this functionality:

Example 1:  The hematologists want all their patients to receive leukodepleted irradiated RBCs and platelets at a site not using pathogen-inactivation.  Medinfo can prepare an algorithm by site, clinical diagnosis, or other criteria which will block release of those components that are not irradiated and leukodepleted.  Blood Bank staff will not be able to release anything else.  The donor module can prepare customized component or modification can take place in the hospital blood bank.

Example 2:  During production, it is discovered that units prepared in one of the centrifuges (or automated component equipment Reveos) became contaminated with a foreign substance.  In Medinfo.  In Medinfo, all units prepared during the affected time interval can be immediately quarantined across the system including all hospital blood banks and thus prevent their being transfused.

Example 3:  A patient has developed hepatitis C after transfusion.  Using the transfusion history, one can retrieve data on all transfused units.  The entire production process can be reviewed for each unit, including donor marker testing.  If a unit is implicated, then all patients receiving other components from that donor can be immediately identified for follow-up.

If a disaster occurs, one can quickly check Medinfo’s cumulative stock display of all components at all sites—donor unit and all hospital blood banks.  One can initiate transfer of units from unaffected sites to the disaster location.  This can be updated as frequently as needed—within seconds!

There are probably ways to accomplish this by using the laboratory information system, but it will be slower and require separate communication to the Medinfo donor site.  There will be no seamless integration and delay.

In summary, there are many advantages to using both donor and patient Medinfo modules.  Even at sites where there was separate transfusion service functionality, I elected to use both modules together for seamless integration.  It would be very time-consuming to manually check between the laboratory and Medinfo donor module.  Medinfo’s patient module offers has strong safeguards to prevent release of untested or partially tested units (example:  release of Kell-untested RBCs to a patient with anti-Kell) and a very robust electronic (computer) crossmatch.

11/10/20

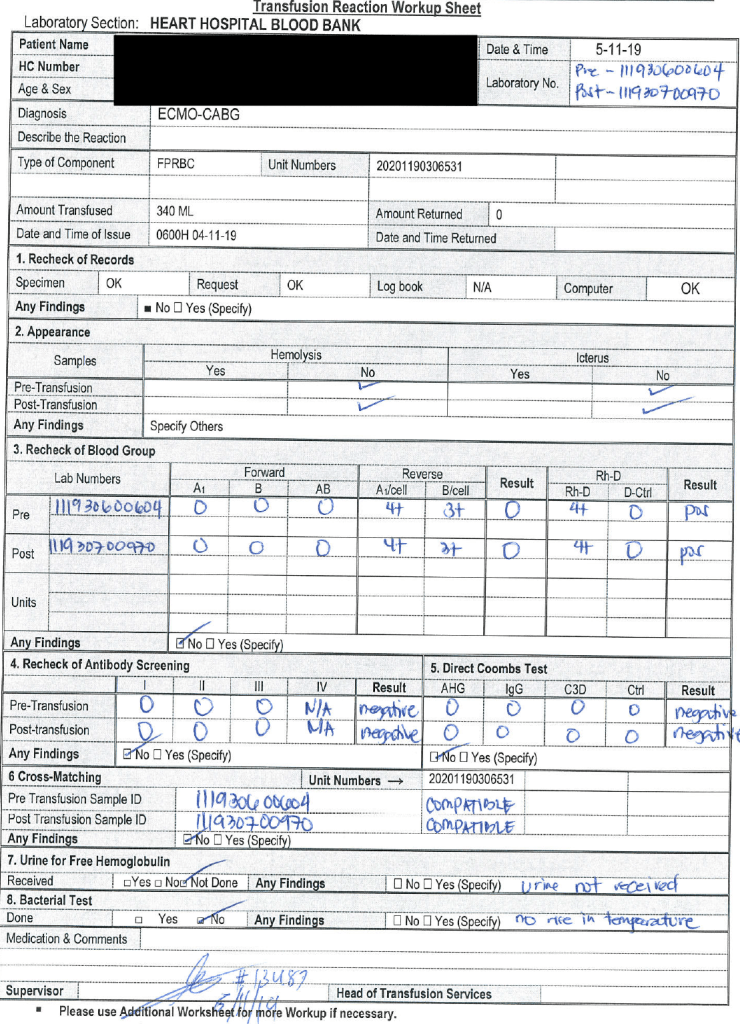
Transfusion Reaction Workup Form

It is easy to regurgitate data, but the key to using it successfully is to organize to maximize pattern recognition.  Once a transfusion reaction has been called, the transfusion blood bank staff must expeditiously (STAT) perform testing to rule out acute hemolysis—one of the four fatal transfusion reactions (others being anaphylaxis, septic shock, TRALI/TACO).

The attached form was designed by my staff and me based on my experiences at several institutions.  It organizes the workup and helps ensure that all the testing and checks are performed.  The clinical area calling the reaction will provide a transfusion form that includes the vital signs (pre-, post-, and during the transfusion) as well as the symptoms.

With these forms, life-threatening hemolysis can be ruled out and further studies made to rule out other serious adverse reactions.

The data on this worksheet are entered into the Medinfo Hematos IIG Patient Module. The transfusion physician reviewing the workup will enter the type of reaction and recommendations. This will document the transfusion reaction for accreditation purposes.

10/10/20

Opinion: Continue Manual Data Collection During Therapeutic Apheresis Procedures

While I was  Division Head, Laboratory Information Systems LIS at my previous position, I was asked to use the hospital information system HIS to collect information during the procedure analogous to what was done for dialysis.

I thought of the logistics:  one apheresis nurse, one Spectra Optia machine, and one metal cage containing a theft-proof computer on a stand.  There was no room for the patient’s bed with all this equipment—the nurse could not move around comfortably.

Second, what I was presented was a hodge-podge of screens on the HIS that the apheresis had to maneuver back and forth between for each measurement—none of the data entry was on one screen!  Honestly, there wasn’t enough time to enter all the data between the screens AND look at the patient.

I remind everyone that therapeutic apheresis is not a benign procedure.  The patient may be critically ill.  The apheresis nurse must concentrate on the patient.  The HIS team was more interested in the data collection, even at the expense of the patient.

LIS had not been engaged in building the pathway and the HIS wanted us to follow the dialysis template.  They did not know that there are many types of therapeutic procedures, often with different data collection.  There is no one-size-fits-all screen!

I refused.  The nurse must concentrate on the patient, not the LCD screen.  To use the HIS would have been harmful to patient care in this situation.  We retained the manual, cellulose interface.  We scanned the manual data form and uploaded it into HIS.

Lessons to be learned:

  1. HIS must engage LIS, and in particular Transfusion Medicine, when building anything for the blood bank.  This is in accordance with international  accreditation standards.
  2. We must never lose sight that we are treating the patient, not the computer screen.  Especially in therapeutic apheresis, we must use the apheresis specialist nurse to monitor the clinical status of the patient, first and foremost!
  3. If the proposed computer process is worse than the manual process, keep the latter.

8/10/20

Contacting the Transfusion Physician with Transfusion Reaction Workup Results

Principle:

The physician on-call for the blood bank requires a certain minimum amount of data to determine the significance of a suspected transfusion reaction and to decide if further testing is required.

Policy:

  1. DO NOT call the transfusion physician about a transfusion reaction until the following data is ready:
    1. Patient name and hospital number
    2. Patient age and diagnosis and location
    3. Previous transfusion history including antibodies and previous transfusion reactions
    4. Vital signs (BP, temperature, pulse, and respiratory rate) before AND after the transfusion
    5. Clinical symptoms (e.g. fever, chills, rash, urticaria, dyspnea, hematuria, etc.)
    6. Repeat ABO and D type on the post-transfusion specimen
    7. Direct antiglobulin/Coombs test (DAT) on the post-transfusion specimen
    8. DAT on the pretransfusion specimen if the post-transfusion specimen is DAT-positive
    9. Results of hemolysis check on pre- and post-transfusion plasma/serum
  2. The transfusion physician may order additional testing based on the above results.

My Opinion: Use Gamma-Heavy-Chain-Specific AHG Reagent

There are many types of antiglobulin reagent available which have differing specificities to immunoglobulins (e.g. whole molecule IgG, IgG-heavy-chain specific, IgM-heavy-chain-specific, IgA-heavy-chain-specific) and complement fragments (e.g. C3b, C3c, C3d).

For the purpose of antibody identification using the indirect antiglobulin test IAT, normally polyspecific, whole molecule IgG, and/or gamma-heavy-chain-specific reagents are used.

The purpose of antibody identification is normally to detect clinically significant antibodies—NOT ALL ANTIBODIES.  In a busy hospital blood bank, I am not routinely interested in detecting cold antibodies that do not react at 37C.

Polyspecific reagents will detect both complement and/or immunoglobulin and are commonly chosen.  However, the complement may detect insignificant cold antibodies that may obscure clinically significant IgG antibodies.

A whole-molecule IgG reagent is not really monospecific since it detects both heavy and light chains.  The light chains (kappa and lambda) are shared by all classes of immunoglobulin.  Thus, an IgM antibody (usually cold) may show weak reactivity—nonspecific cold antibodies may be detected!

My usual choice is to routinely use a gamma-heavy-chain-specific reagent.  I have been using this for many years and it expedites the workflow.  The likelihood of missing a clinically significant antibody is rare.  In my long career, I have only detected a small number of Kidd antibodies that required a polyspecific reagent with complement. 

If there is a nonspecific antibody, I will check the Jka and Jkb typings.  If either is negative, I will check for an antibody showing dosage and consider using a polyspecific reagent.  I have previously reported such an antibody in an earlier post—it is extremely rare!

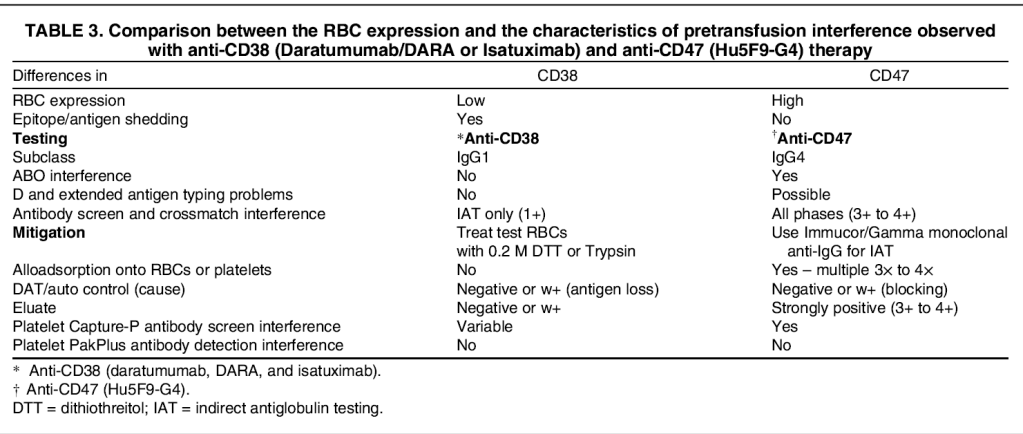
Another consideration is the detection of interference from a new chemotherapy reagent, anti-CD47.  This nonspecific reactivity will be eliminated by using a gamma-heavy-chain specific reagent:

This is an example of a nonspecific reagent using whole molecule IgG AHG:

Here is the same sample using gamma-heavy-chain-specific AHG:

4/10/20

Projective Exercise 8 Solution: D-positive with anti-D

Some Possible Explanations:

Always review the transfusion history of all component types, medication history, and the clinical history!! Start with this first.

  1. Receipt of plasma with anti-D (RhIG, IVIG, etc.)–passive antibodies
  2. Partial D with anti-D:
    1. Partial or mosaic D patient who received D positive RBCs and made anti-D directed against its missing epitopes
  3. Anti-G:
    1. Not all anti-G is anti-C and anti-D:  It is really a separate specificity.  It is possible that anti-G may be made even though the patient is C-positive.
  4. Anti-LW:
    1. However, it is unlikely to show such strong reactions

Can you think of other explanations?

3/10/20