Policy: Donor Physical Examination

This is another example of a short concise policy statement. The process example will follow:

5.3 POLICY: DONOR PHYSICAL EXAM

Policy:

  1. All donors will be positively identified with a picture ID and by their Hematos identifiers (donor ID and session registration/specimen number).
  2. The donor’s vital signs (BP, pulse, temperature, respiratory rate) will be measured by designated Donor Center staff.
  3. The donor’s arm veins will be inspected for a suitable donation site and evidence of scarring.
  4. Donor eligibility for actual collection will be determined by the Hematos IIG algorithms based on this data.
  5. All policies, processes, and procedures must comply with Qatari, HMC, and applicable accreditation standards (i.e. AABB, CAP, and JCI).

References:

  1. HMC 1001 Setting Specification, Version 1.5, Hematos IIG, Medinfo
  2. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, Maryland, USA

Antiglobulin Reagents

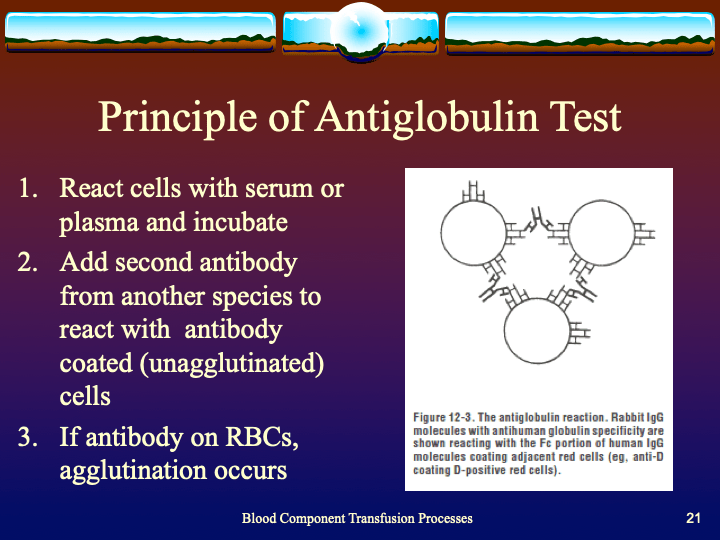
Antiglobulin reagents are used to detect molecules bound to the RBC surface.  What they detect depends on their specificity.  Such detection can be performed in the routine immunohematology laboratory or elsewhere such as flow cytometry.  This discussion is for the blood bank laboratories, both routine and reference immunohematology.

This is how I classify and use the various reagents in my daily practice:

  • Routine use—DAT testing and compatibility testing
  • Antibody identification
  • Drug-related hemolysis and transfusion reaction workups
  • Special assays:  DAT-negative AIHA, prediction of clinical significance of reaction by IgG subclass determination

There are many types of antiglobulin reagents:

  • Polyspecific:  IgG and complement usually C3d but sometimes C3b specificity included
  • Whole Molecule IgG including mu heavy chains and kappa and lambda light chains
  • Monospecific gamma heavy chain, mu heavy chain, alpha heavy chain, C3c, C3d, C3b
  • IgG subclass:  IgG1 IgG3

Whole molecule IgG detects class-specific mu heavy chains AND light chains kappa and lambda.  Since kappa and lambda are found on all immunoglobulin classes, whole molecule reagents can detect IgM so there may be weak staining with cold antibodies that are not clinically significant.

C3d is the final breakdown product of C3b and does not cause hemolysis.  Its presence merely means that at some time—unspecified—complement was fixed.  C3c is an intermediate product in the breakdown pathway.  If detected, C3c positivity means ACTIVE complement fixation was occurring at the time of specimen collection.

General Use:

Routine DAT testing:

  • Polyspecific:  if positive, then use
  • Monospecific IgG and monospecific C3 reagents

Antibody workups:

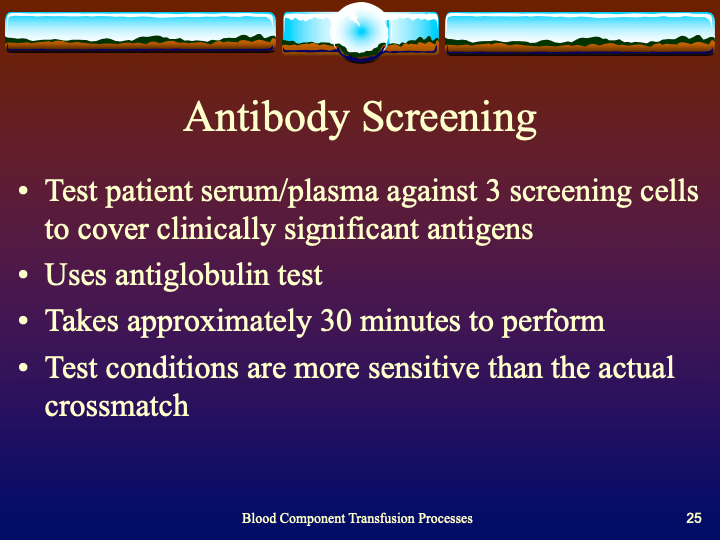
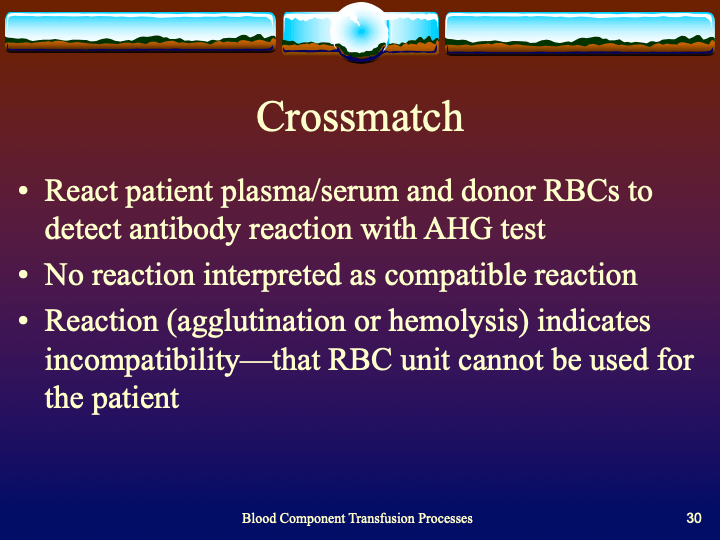
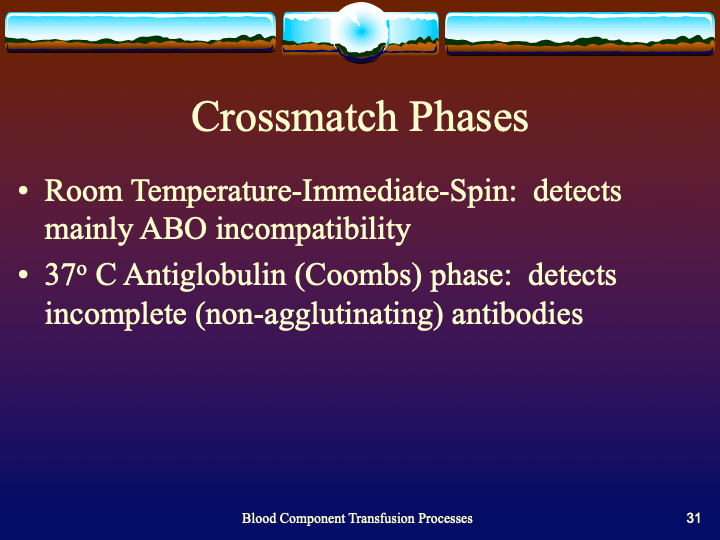
Routine:  antibody screens and AHG crossmatch (if indicated)

  • Polyspecific
  • Gamma heavy-chain monospecific

Monospecific gamma heavy chain is preferred to minimize non-clinically significant, cold antibody interference.

Complicated—where detection of complement reactivity is especially important:

Polyspecific for drug-related hemolysis and transfusion reactions

Difficult antibody workups, e.g. to rule out anti-Jka and/or anti-Jkb

Specialty Reference Procedures:

  • DAT-negative AIHA:  mu heavy chain, alpha heavy chain for IgM and IgA mediated hemolysis (rare), C3c to detect active complement fixation
  • Predicting clinical significance:  IgG1 IgG3

Complement fixation may be important in various drug-related hemolysis and some transfusion reactions so I always use a polyspecific reagent in these situations.  Most antibodies can be detected by gamma heavy-chain specific reagents;  however, there are rare examples of anti-Jka and anti-Jkb which are only detected by complement.  Whenever I have a nonspecific reaction in an Jka-negative or Jkb-negative patient, I repeat the AHG panel using polyspecific reagents.  I do not use polyspecific routinely because of the nonspecific and non-clinically significant cold antibodies.

One way to assess for the clinical significance of an antibody is to determine its IgG subclass.  In general, IgG3 antibodies may fix complement and cause severe hemolysis.  Both IgG1 and IgG3 antibodies cross the placenta and may cause hemolytic disease of the fetus/newborn.

In summary, when reviewing immunohematologic reactions using AHG, I always remember to check which type of AHG reagent was used.  I always keep multiple types of AHG reagents in the laboratory for the reasons explained above.

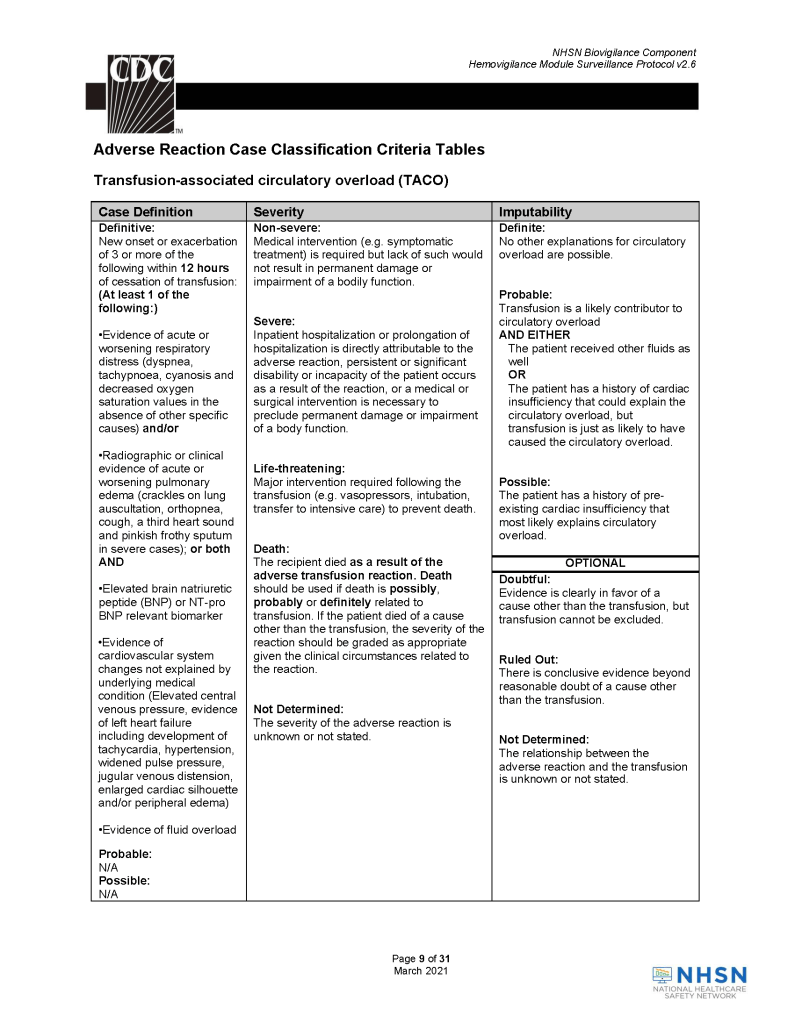
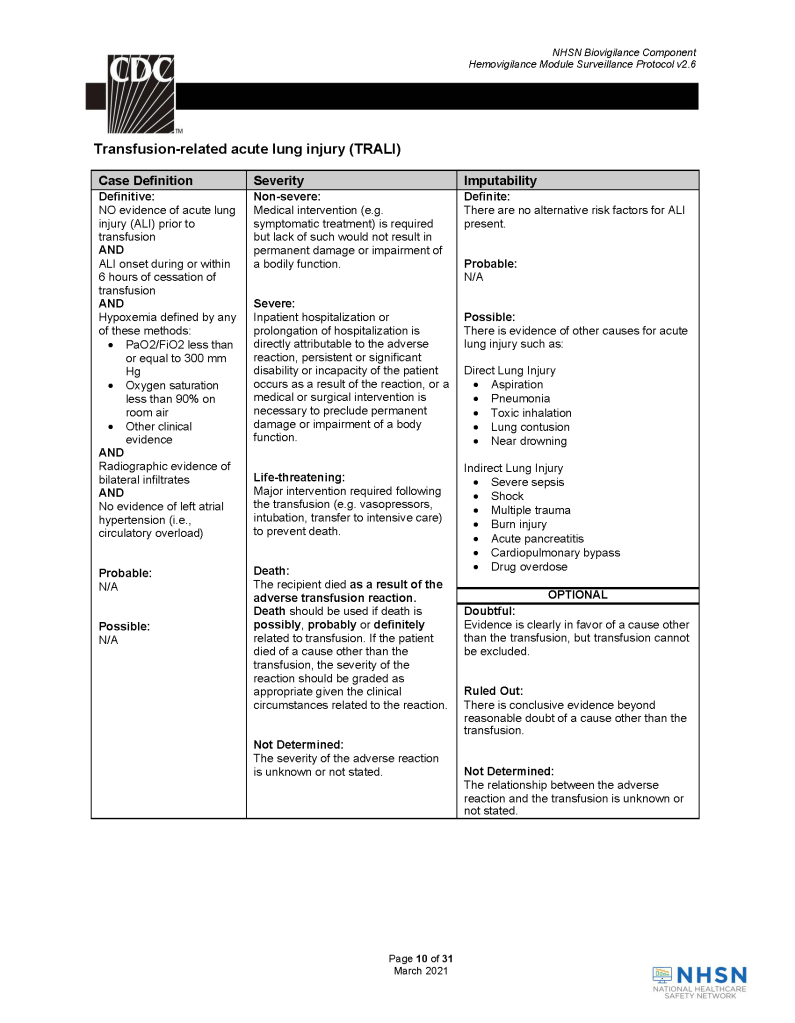
TRALI TACO

This is a revision of a previous post, incorporating an updated definition of Transfusion-Associated Cardiac Overload TACO from the National Healthcare Safety Network, Biovigilance Component Hemovigilance Module Surveillance Protocol,  Version 2.6.

Time: Appreciating Testing and Component Release Times

This is a revised version of a previous post.

I have had many medical students, residents, and fellows rotate through my Transfusion Medicine section.  Hardly anyone has any interest in making my discipline his/her career.  It is a required rotation or an “easy” rotation during which the trainee may take his vacation.  The trainee will cram for the examination and then promptly forget it.

I left practice in the USA in 1990, in what I consider the golden age of laboratory medicine.  We had supervisors for each laboratory section.  In the blood bank, we had many staff with SBBs or who were SBB students.  We were very self-sufficient in handling immunohematology problems except for rare blood types or antibodies to high incidence/prevalence antigens.

When I returned to visit my old laboratory, I sensed a deprofessionalization of the laboratory and blood bank in particular.  Blood Bank now is a cost center, not an area of revenue.  Why hire experienced blood bankers for most hospitals?  Send the antibody workups to the Blood Center.  There are limited jobs for transfusion medicine consultants.  Minimize testing, don’t do extended antigen typings, etc.

Nowadays, I feel like one of the dinosaurs marching into oblivion like in Walt Disney’s Fantasia film, the section called The Rite of Spring.  Who will replace those retiring?  Have you ever noted the average age of attendees at the AABB annual convention?  I feel young when I go there (and don’t worry about the gray hair!)

I want to attract new doctors and scientists to Transfusion Medicine.  I really try, but most have no interest and look on their rotations as a necessary evil.

I have lowered my expectations for most medical trainees in Transfusion Medicine.  They don’t like it, they just want to pass it, and move on.  What must I impress them with for their future careers?  What is essential for them to remember?

I have had both pathology and non-pathology trainees.  Surgical and ob/gyn doctors used to spend one month whereas the hematology and pathology residents/fellows spent on average three months.  The few interested in the field might do multiple rotations.

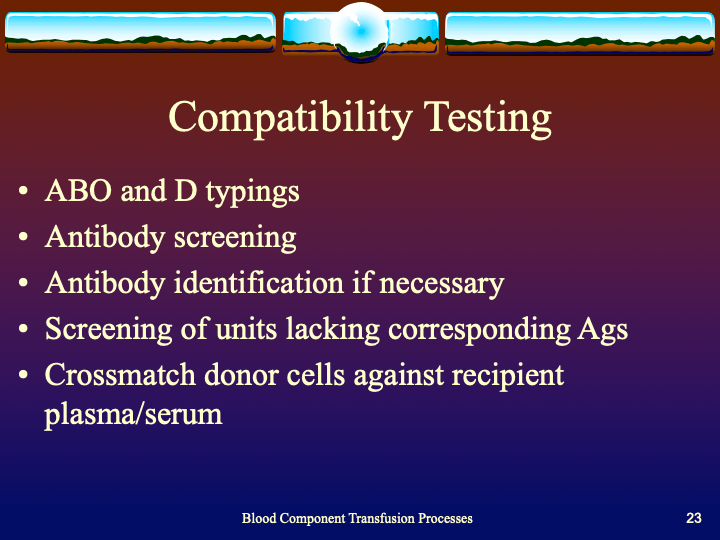
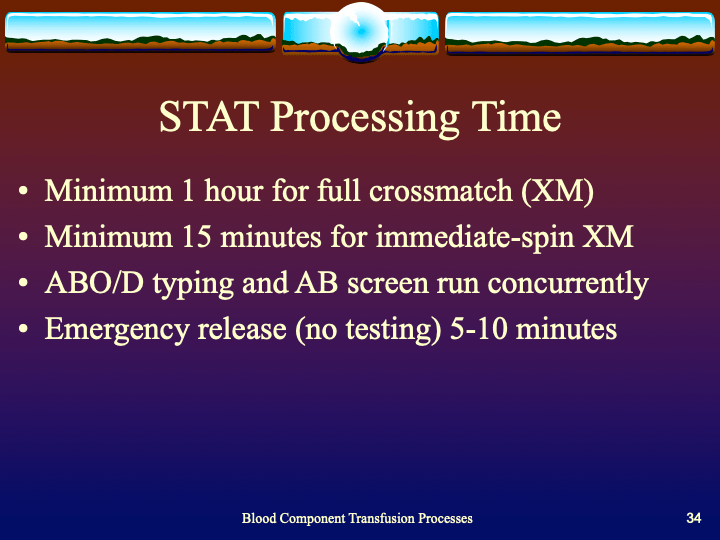
I still gave them lectures on a variety of topics, especially how to transfuse blood components, basic ABO/Rh antigens, compatibility testing, and direct antiglobulin testing.  They would forget most of this, but I wanted them to remember TURN-AROUND-TIMES:

Examples:

HOW LONG DOES IT TAKE TO PERFORM THE TEST?  TO FIND COMPATIBLE BLOOD?  TO THAW THE PLASMA?  RELEASE AN MTP SHIPMENT?  TO PERFORM A TRANSFUSION REACTION WORKUP BEFORE RELEASING MORE BLOOD?

I am not discouraging people from entering the field, but I am a realist to know that few will share my passion for serology or want to take call on difficult immunohematology cases.  At least if they understand the pressure the technical staff are in and these turn-around-times this will make both their work as clinicians and mine as transfusion medicine more congenial.


Anecdotes: Outside Software Consultants

Sometimes, you may not have adequate resources for a project so you will consider hiring an outside consultant.  During my career, I have used several outside consultants for projects ranging from installing a new general laboratory computer system to assisting in getting international accreditations.

Regrettably, my experience with software consultants has been mixed.  I have used them for general laboratory software installation and settings.  Very few have any experience with dedicated blood bank software or setting up hospital blood bank modules.  They are often former employees of the software vendor you are using.  There is always a potential for conflict of interest.

The software consultant must work for you, NOT for the vendor you are using.  He/she must maintain his independence from the vendor and only represent your interests.  I have had many problems with this.  Here are some of my unpleasant experiences:

Current and Future States:

One set of consultants gave essentially the following current state mapping for almost every test in our menu:

  • Order this.
  • Collect this.
  • Receive this.
  • Perform this.
  • Release this.

They did not know our current state so they were unable to help us build a proper future state.

Mapping Errors:

The consultants were in charge of exporting results from a previous system into the new one, this included mapping the results into the appropriate test fields.  They assumed it would map properly, I insisted on testing a two-week sample of laboratory results and discovered major errors that could adversely affect patient care—it was a major disaster and almost held up implementing a hospital go-live on-time.

Benefits of New Software:

The consultants were obsessed with calculating benefits of the conversion to the new software vendor and making fancy PowerPoint presentations to assure officials that they were gaining benefits.  There were many issues to resolve that were critical to the functionality that I felt the time would have been better spent in fixing the software issues than calculating alleged benefits.

The Need for Speed:

There were some consultants without any experience in blood bank who insisted that this had no bearing in making software settings.  One bragged to me that he could install a blood bank system in a few days.

Default Settings:

Some outside consultants kept pushing using the default settings.  There is no “one size fits all” solution for a large healthcare organization.  There is need for customization.  I wondered why we needed the consultants to set up default settings which is what the vendor wanted us to do anyway.

Opinion: Outside Accreditation and Quality Consultants

Sometimes, you may not have adequate resources for a project so you will consider hiring an outside consultant.  During my career, I have used several outside consultants for projects ranging from installing a new general laboratory computer system to assisting in getting international accreditations.

For a complex accreditation process such as AABB, I have used such consultants to audit operations in the donor center including processing and testing, hospital blood banks, and stem cell laboratory.  They are high-level technical specialists with highest blood bank qualifications (e.g. SBB(ASCP) or equivalent) and have considerable experience in practice of blood banking and quality systems.  They have been AABB Assessors so they can give you a dry-run accreditation assessment.

Depending on the project, you may need one or a group of consultants.  I have worked with both individual consultants and groups.  A group can complete the tasks quicker but this is not always necessary.  Organizations such as AABB have many different consultants with different types of expertise so you can select the most appropriate individuals to form a team for your needs.

These specialists can audit your operations and propose a model and if you want, actually help you to implement the processes.  They can help you with the accreditation formalities, especially if you do not have any staff with experience in the process.  It all depends how much you can spend.

In the Middle East, to bring in such consultants may mean expensive air fares, hotels, meals, plus the actual costs of doing the consulting.  This is a major investment for your organization but it is well worth it to expedite the process.  There are local consultants available as well and using them may greatly help with the expenses.

Although it is expensive upfront, it can be cheaper in the long run by establishing the appropriate framework in the first place.  You can engage the consultants to actually do much of the work themselves, but it is better for them to offer a train the trainer experience, i.e. engage your own technical staff to learn new skills and then have them cross-train the rest of the staff. 

Based on the findings, your local staff can implement the changes.  You can then consider rehiring the consultants to verify that the work has been done properly.

I have used both individual consultants and groups through AABB Consulting.  My staff and I have learned much from such interactions, and I highly recommend their use when local expertise is not available.

Process: Donor Medical Questionnaire

This is one of a series of posts comparing policies and processes in the blood bank.

PROCESS:  5.2.1 DONOR QUESTIONNAIRE

Process:

  1. The donor is positively identified by a designated picture ID and Medinfo Hematos donor consent form with specimen/encounter number and barcode.
  2. Donor is taken to a private area for the interview.
  3. Donor is asked ALL questions by Donor Center staff using the Hematos IIG questionnaire.
  4. Hematos IIG determines if any contraindications apply.
  5. Questionnaire will be referred to transfusion medicine physician for any questions requiring physician review.
  6. Donors without contraindication are sent for donor physical examination.

References:

  1. HMC 1001 Setting Specification, Version 1.5, Hematos IIG, Medinfo
  2. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, Maryland, USA

Policy: Donor Medical Questionnaire

This is one of a series of posts on blood bank operations, comparing the process and policy documents.

5.2 POLICY:  DONOR MEDICAL QUESTIONNAIRE

Policy:

  1. All policies, processes, and procedures must comply with Qatari, HMC, and applicable accreditation standards (i.e. AABB, CAP, and JCI).
  2. All donors will be positively identified with a picture ID and by their Medinfo Hematos identifiers (donor ID and session registration/specimen number).
  3. Donors will be assessed confidentially in a private area.
  4. Donors will be asked questions based on the latest Uniform Donor Questionnaire with additional localization questions for Qatar using Medinfo Hematos IIG software.
  5. Donor must understand either English or Arabic.
    1. Otherwise, they cannot be accepted for donation.
  6. Donors passing the donor questionnaire will be processed for the donor physical examination.

References:

  1. HMC 1001 Setting Specification, Version 1.5, Hematos IIG, Medinfo
  2. Standards for Blood Banks and Transfusion Services, Latest Edition, AABB, Bethesda, Maryland, USA