Donor Deferrals for Body Fluid Exposure

Principle:

New rules have been approved by US FDA CBER for body fluid exposure, tattooing, body fluid exposure, and body-piercing.  By similar logic we will extend this also to HIJAMA.  We will not make any changes to our sexual history/practices or history of sexually transmitted disease treatment.

Policy:

  1. Effective immediately, we will accept donors AFTER THREE MONTHS from the following activities:
    1. HIJAMA (ritual blood-letting)
    2. Tattooing
    3. Body piercing (e.g. piercing for ear-rings)
    4. Contact with blood of another individual through percutaneous inoculation such as a needle stick or through contact with a donor’s open wound or mucous membranes
  2. A TWELVE-MONTH DEFERRAL still applies after receiving a blood component or blood derivative except clotting factors.
  3. Transfusion of clotting factors remains a permanent/indefinite deferral.

Reference:

Revised Recommendations for Reducing the Risk of Human Immunodeficiency Virus Transmission by Blood and Blood Products, Guidance for Industry,  U.S. Department of Health and Human Services, Food and Drug Administration, Center for Biologics Evaluation and Research, April 2020
Processes and Software Building 45: Modifying RBC Components

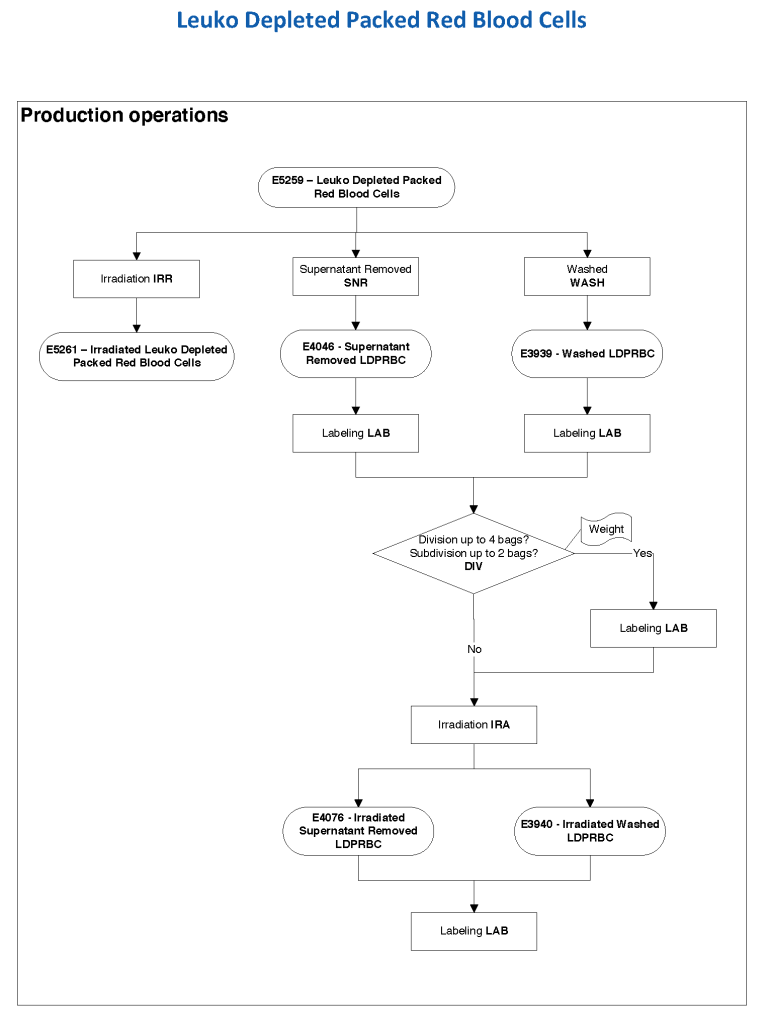
Components may be modified either in the Blood Donor Center or in the hospital blood bank.  In either case, they use the PRODUCTION section of Medinfo to perform these operations.

These operations may include:

  • Irradiation
  • Tight-packing (removal of the supernatant, especially for intrauterine or neonatal transfusions)
  • Washing
  • Aliquoting (division of the primary RBC bag and possibly further division of one of the secondary bags)
  • Final labelling of the modified component

The weight of the component is converted to the volume by the software.

The end-user can specify which modified components were available.  As with any ISBT-labelled products, any changes will trigger a new ISBT E code and label.

16/9/20

Processes and Software Building 44: Pooling Components

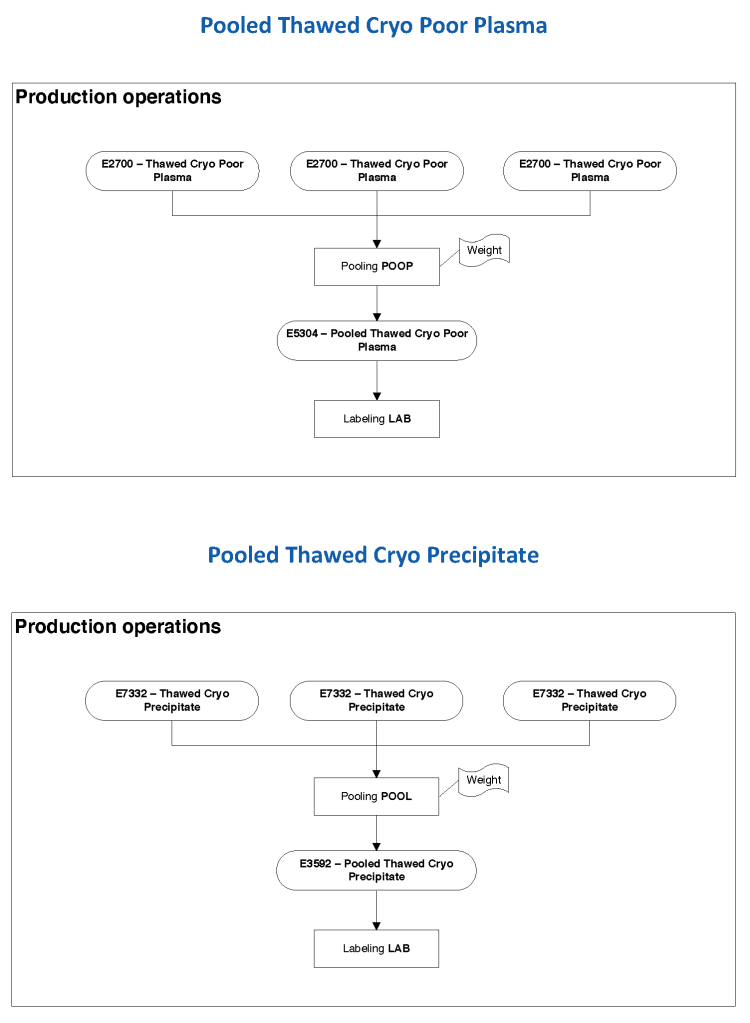
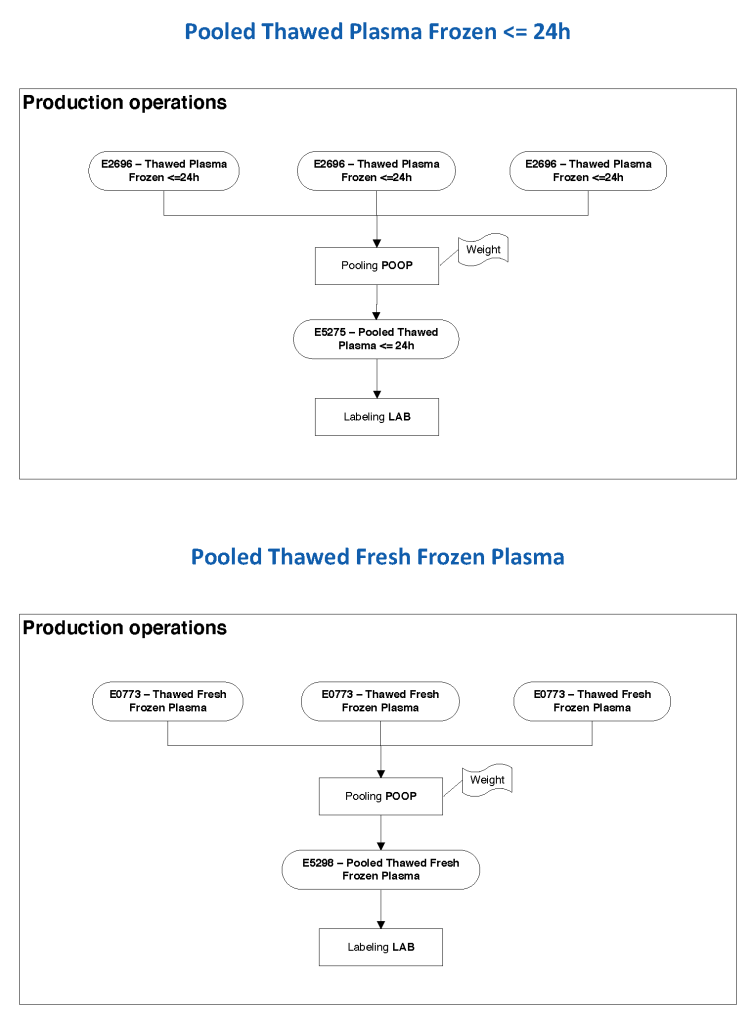
Medinfo Hematos IIG has a pooling operation that can be used for pooling platelets, plasma, cryoprecipitate, etc.  It is a one-step operation.  In the set-up, one specifies the maximum number of components to pool together for each component type.  In general, they are of the same ABO type;  however, at HMC Doha I did allow mixed ABO platelet pools to avoid wastage of platelets that would otherwise be discarded—this may not be allowed in all jurisdictions.

The following examples show pooling of FFP, FP24, cryoprecipitate, and cryo-poor plasma:

13/9/20

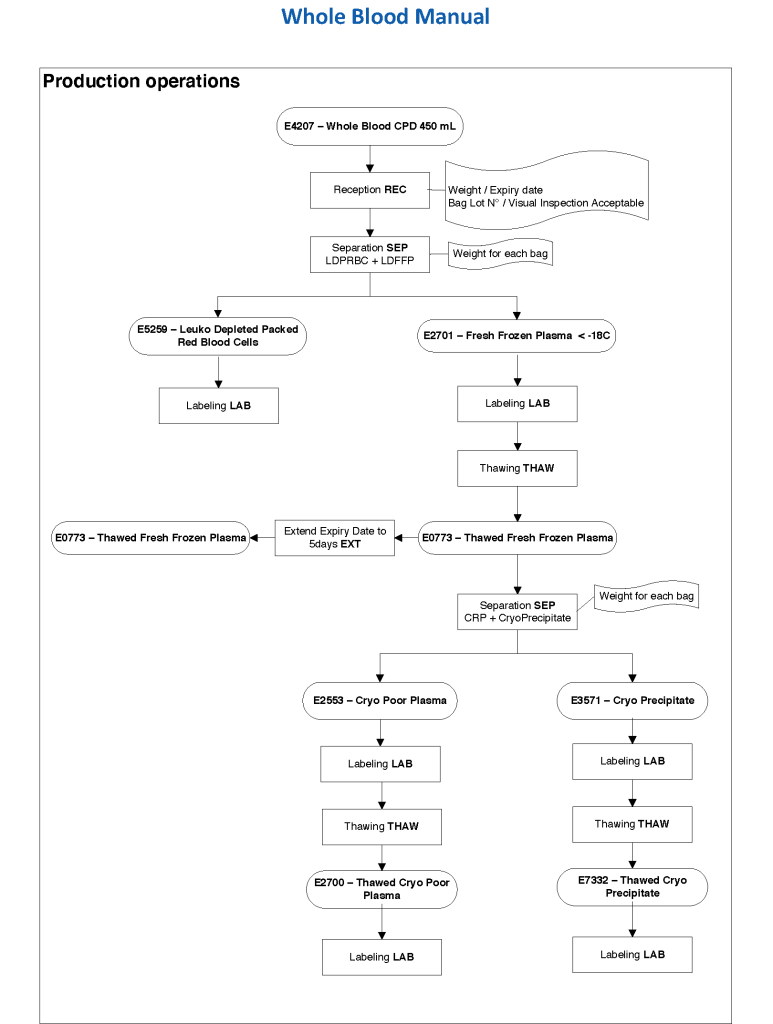
Processes and Software Building 43: Manual Whole Blood Processing

This was the HMC methodology for manual whole blood processing to prepare packed RBCs, plasma, cryoprecipitate, and cryo-poor plasma using blood bank centrifuges (not Reveos).  It did not include preparing platelets since we did not have manual buffy coat processing equipment.  In this algorithm we did not specifically release whole blood as a final product (although we did have the capability of activating this in emergency situations).

10/9/20

External Disaster Plan

Principle:

Maintaining an adequate blood supply and expedited compatibility testing are critical in disaster planning.  This plan is assuming that the Blood Donor Center is functional and can process donors and make components.

Medinfo Hematos IIG System is critical to monitoring inventory, preparing blood components expeditiously using Good Manufacturing Processes, and distributing blood components in a timely controlled manner.

Policy:

  1. Determinate total available blood supply across all locations by using the Cumulative Stock Display program in Medinfo Hematos IIG.
    1. Recheck stock at least every hour during the disaster.
  2. At each transfusion service site, in conjunction with the Transfusion Medicine Consultant:
    1. Cancel reservations for elective surgical and non-emergency medical cases of affected ABO/D types.
    2. Retain reservations for antigen-matched, oncology, NICU, and high-risk obstetrical cases.
  3. Inform Manager for Donor Recruitment/Logistics to send SMS, radio, and television messages for blood donors—all types.
  4. Contact ALL staff and have them report to duty.
    1. At Blood Donor Center, the Head Nurse, Recruitment Manager, Supervisor, Component Processing, and Supervisor, Marker Testing will contact their respective staff.
    2. At various hospital blood bank transfusion services, the site supervisor will contact all staff.
  5. Process blood components using automated component technology (Reveos).
  6. Perform all donor marker testing including single-well NAT.
    1. Abbreviation of donor testing is only at the discretion of the Head, Transfusion Medicine.
  7. Send blood components using Inter-Depot Transfer function of Medinfo.
  8. Transfusion Services:
    1. Release blood component according to the various protocols as needed:
      1. Massive transfusion protocol
      2. Emergency release
      3. STAT
      4. Priority
      5. Routine
  9. Compatibility testing will be electronic, immediate-spin, or full AHG as per our protocols.

References:

  1. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  2. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

Revised 10/9/20

Processes and Software Building 42: Platelet Pooling

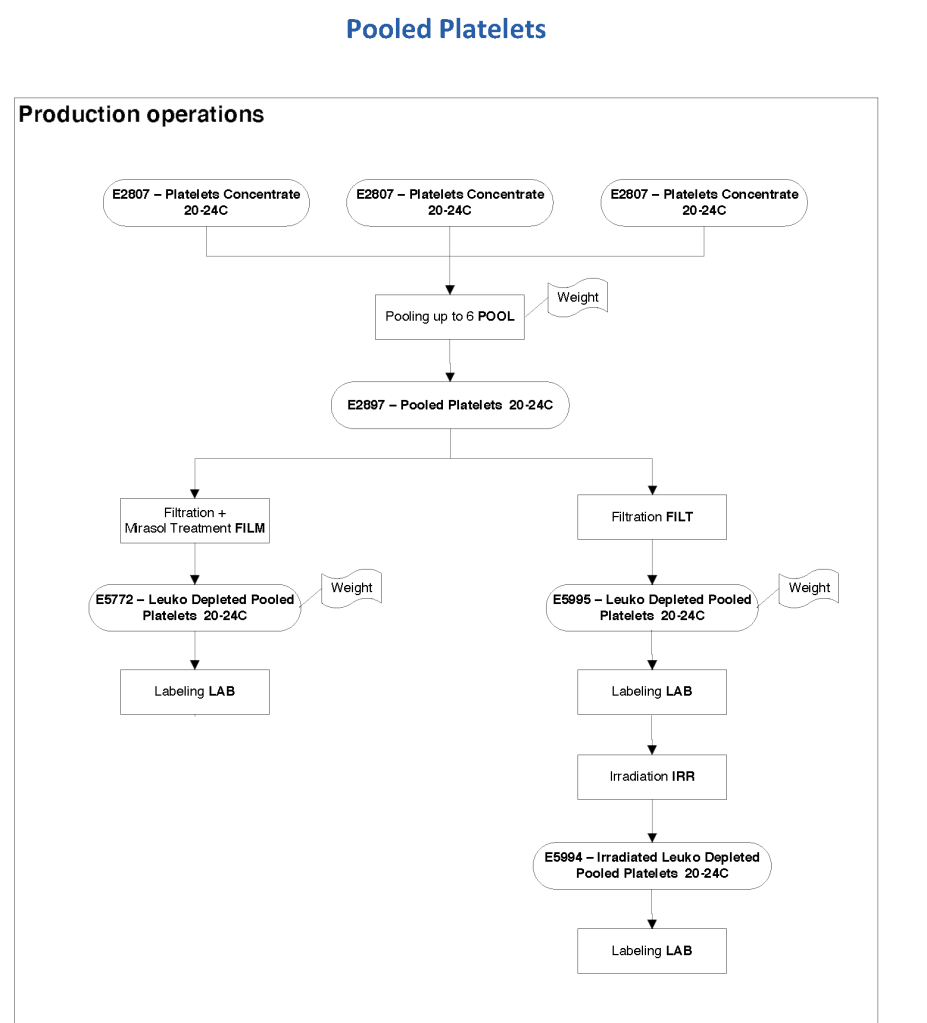
Outside the USA, platelet pools stored at room temperature may be valid for up to 7 days, especially if pathogen-inactivation is used.  The following workflow shows both Mirasol pathogen-inactivated and standard platelets.  The standard platelets are then irradiated.  Both types can be aliquoted.

A major advantage in using a specific blood bank computer software is to enforce the Good Manufacturing Process.  Medinfo is merciless:  there are no exceptions without authorization and that is restricted by the security policies.

In the recent Reveos post, the upper and lower platelet volume specifications were discussed.  The platelets are weighed and the volume is calculated.  If a manual or another method for preparing platelets is used, then the according values can be specified.

To Be Continued:  8/9/20

Minimizing Iron Deficiency in Blood Donors

Principle:

HMC Blood Donor Center is implementing a policy to limit or help limit iron deficiency in its blood donors (whole blood and/or apheresis).  The reasons for this are:

  1. Development of iron deficiency in some donors
  2. Progression of iron deficiency that occurs with frequent blood donation
  3. Potential adverse effects of iron deficiency

Definition:

Donors high-risk for iron loss include:

  1. Females—all, regardless of age
  2. Males donating three or more times within a 12-month period
  3. Apheresis donors giving 5 sessions in an 8-week period
  4. Donors after one RBC apheresis dual-unit donation
  5. Males and females with borderline low hemoglobin levels:
    1. Males with hemoglobin <= 13.5 g/dl
    2. Females with hemoglobin <= 13.0 g/dl
  6. Donors with low ferritin level (below current lower limit of reference range)

Policy:

  1. Donors will be provided with information regarding iron-deficiency from donation.
  2. High risk donors (as defined above) will be offered a prescription for iron supplementation equivalent to 18 mg of elemental iron daily for 30 days.
  3. During the iron supplementation period, the donor will be deferred for donation.
  4. If a donor does not take the iron supplement, then he/she is limited to 2 donations/year.
  5. We will offer donors to test ferritin in the following categories:
    1. Apheresis donors after their fifth donation of plasma or platelets within 8 weeks
    2. Whole blood donors after three donations within a 12-month period
    3. Donors after dual-unit (2-unit) RBC apheresis donation
    4. All female donors otherwise meeting donor criteria before donation
  6. Donors with low ferritin levels will be deferred until ferritin levels are normal (based on reference range currently in effect)

References:

AABB Association Bulletin #17-02, Updated Strategies to Limit or Prevent Iron Deficiency in Blood Donors, 26/3/17

Updated 6/9/20

Processes and Software Building 41: Off-Line Medinfo Donor Transactions

Principle:

Normally, outside donor campaigns still connect to the main server via wireless 4G/5G with a VPN.  However, if there is a “dead” spot, Medinfo can provide a local area network using one of the PCs/laptops to serve as a server.  The local server receives an uploaded image of the donor database.  Upon return to the donor center, the local server’s data is uploaded and synchronized.

When you cannot establish a direct link to the live Medinfo program, you must arrange for Medinfo/VHT to create a local server that will have the current Medinfo donor database for use at outside campaigns where the internet connection cannot be used.  This can also be used if for some reason the Blood Donor Center link is down in order to register donors and check the donor deferral database.

Policy:

  1. For each outside campaign, there should be a pre-campaign visit to verify the availability of internet to connect to Medinfo.
    1. If the internet connection is working, use Medinfo using the 4G/5G access points.  Otherwise:
    2. If none, inform Medinfo/VHT to prepare a local server—at least ONE DAY in advance of the campaign.
      1. Provide Medinfo/VHT one of the portable computers to download the database and software.  This will be the offline server for the campaign.
      2. Link the offline server to the other portable computers for the campaign (see the corresponding Medinfo job aid).
      3. Use the local network (offline server and other portable computers) for registering donors.
      4. Upon return to the Blood Donor Center, upload the data as indicated in the Medinfo job aid.
      5. Continue the regular processes after uploading.

7/9/20

Review of Product Inserts

This is a policy I made for NGHA Jeddah many years ago but is still useful today.

Principle:

All technical staff are required to read and understand the manufacturer package inserts that apply to the procedures that they perform.  This policy establishes a means of documenting compliance with this requirement.

Policy Details:

  1. Technical staff are defined as anyone who uses the reagent in the performance of a procedure or process or anyone reviews or supervises that process or procedure.  This includes the supervisor, medical technologists, medical technicians, nurses, phlebotomists, and assistants.
  2. All technical staff are required to read and understand ALL product inserts for each procedure applicable to the section(s) that they work in—apheresis, donor room, component preparation, and/or transfusion service.
  3. If they have any questions about a particular insert, they should refer it to the supervisor, senior technologist (Med Tech 1), or in the latter’s absence, the blood bank medical director/section head.
  4. Each staff member must sign the Manufacturer’s Package Insert Review Form for that particular policy/procedure, including his signature, employee identification number, and date.
  5. Each Manufacturer’s Package Insert Review Form will be retained with a copy of the package insert by the Blood Bank Supervisor in a special file while the material is being used and for at least five (5) years after a new or revised manufacturer package insert is applicable.
  6. A new Manufacturer’s Package Insert Review Form should be used for each revision of the insert.

Insert Review Form

Type of Insert:  New  Revised
Product Name:
Date of Insert:

I have read this insert and understand its contents and accept responsibility for following its instructions and directions.

Staff Name & Badge #–PRINT!SignatureDate


Sample Resident Examination for Donor Center

Reading Assignments:

  • Chapters 5-9:  Blood Donation and Collection in Technical Manual, 16th Edition
  • Standards for Blood Banks and Transfusion Services, AABB, 25th Edition

Study Questions:

  1. Which of the following candidates is acceptable for donation?
    1. Saudi, visited Sudan 11 months ago as part of National Guard exchange
    2. Saudi former student lived in UK for 2 years from 1993-95
    3. Normotensive taking amlodipine and valsartan
    4. Psoriatic using Tegison
    5. Male adult using ibuprofen for lower back pain
    6. Female 4 weeks post-partum
    7. Husband of patient with recent onset of hepatitis B infection
    8. Male stopped taking ampicillin one week ago for acute pharyngitis
    9. Donor with WBC count 12000/cmm but otherwise normal
  2. Which of the following donors is suitable for autologous donation?
    1. Cataract surgery patient
    2. Well, but had gastroenteritis 3 days ago
    3. Pregnant with Hgb 11 g/dl
    4. CGL patient with Hgb 13 g/dl
    5. Hodgkin’s disease patient Hgb 12 for exploratory laparotomy
    6. Patient with rare antibody anti-Tja, Hgb 13 for cholecystecomy
  3. How do you handle the following events?
    1. Donor draw fills bag with bright red blood in 30 seconds
    2. Donor faints when needle is shown
    3. Lipemic serum during donor plateletpheresis session
    4. Donor with numbness and tingling of extremities during donor apheresis session
  4. How would you handle the following therapeutic phlebotomy requests?
    1. Hgb 22 g/dl, suspected polycythemia rubra vera
    2. Hgb 13, suspected hemochromatosis patient
    3. Hgb 16, renal failure patient post-erythropoietin treatment
    4. Unstable angina, Hgb 9
  5. What is the final volume of each of the following blood components?
    1. Whole blood
    2. Packed RBCs—state hematocrit as well
    3. Washed RBCs
    4. Irradiated packed cells
    5. Platelet pool—state number of platelets
    6. FFP
    7. Cryo-poor plasma
    8. Cryoprecipitate
  6. What are the outdates of each of the following components?
    1. Packed RBCs
    2. Platelet pool
    3. FFP frozen at -35C
    4. Granulocyte concentrate
  7. Which donor units are acceptable for transfusion?
    1. HBsAg negative, HBcAb positive, HBsAb > 20 IU/liter
    2. HCV Ab positive, RIBA-3 negative, HCV-RNA negative
    3. Syphilis positive, FTA-ABS negative

Revised:

29/8/20