Investigation of Donor Unit Mislabelling

Principle:

All donor unit mislabeling is potentially life-threatening and must be stringently investigated as soon as possible after the discrepancy is detected.  Most importantly, if there is one error, there may be possibly ADDITIONAL donor unit errors (e.g. switch of donor tubes or units, etc.).  All donor units processed in the same batch must be also quarantined until the discrepancies are resolved.

Definitions:

Responsible blood bank physician:  specialist or consultant physician on-call at the time the discrepancy is detected

Policy Details:

The following steps MUST be performed as soon as possible:

  1. The Component Processing Supervisor or Senior Technologist must be IMMEDIATELY notified of any discrepancy.
  2. The Blood Bank Supervisor will inform the Division Head, Transfusion Medicine.  If the Head is not available, notify the Transfusion Medicine on-call.
  3. Quarantine ALL donor units collected and processed in the same batch.
  4. Obtain copies of all testing including photos of the gel/glass bead cards documenting the discrepancy.
  5. Obtain copies of all worksheets used in donor processing for the affected batch.
  6. Perform repeat ABO/D typing of ALL DONOR UNITS in the affected batch.  Any further discrepancies must be investigated and resolved.
  7. Identify all staff who were involved in handling the donor unit (phlebotomist, blood bank technicians processing and labelling the unit).  Identify those associated directly with the error.
  8. Submit all documents and photos to the Blood Bank Supervisor or designate.
  9. Prepare an occurrence/variation OVA report documenting all the data, findings, and interpretations.
  10. All investigations must be reviewed by the Supervisor, responsible blood bank physician, and one of the senior consultants.
  11. All such investigations must then be finally reviewed and approved by Head, Transfusion Medicine or his designate.  Only when the issue(s) are completely resolved and investigation is approved may the donor unit be properly relabeled and released into available stock.  Also, only at that time may the other units in the affected batch be released into available stock!!
  12. Photograph the correctly relabeled unit and attach it to the other documentation of the incident.
  13. If the discrepancy cannot be resolved, ALL units in the affected batch must be discarded.
  14.  The implicated staff’s personnel record should be reviewed for previous errors.   Appropriate disciplinary action should be taken and documented in the personnel record.  If a verbal warning is given, it should still be documented in the written record.
  15. If there is a systemic cause for the error, appropriate measures should be taken to minimize reoccurrence.
  16. All actions must be in accordance with the applicable regulations.

Teaching Document: Irradiating RBCs from Outside Transfusion Medicine

This is a teaching document of a process to irradiate RBC components when our irradiators are not functioning.  In our system, we used Mirasol pathogen-inactivation so our RBC units were affected.  The number of units for advance irradiation was based on our historical usage of irradiated units across our system.  The workweek is Sunday-Thursday so on Thursday special effort was made to have the minimum number of irradiated units available.

We used irradiated units for compatibility testing to avoid the possibility that the unit would be released without irradiation.

Emergency Interim Procedure:

  1. Verify the patient’s diagnosis/location:  All Hematology-Oncology patients should receive irradiated blood.  Refer to the list of diagnoses for which irradiation is indicated (attached).
  2. Only PRBCs need to be irradiated.  Mirasol-treated (pathogen-inactivated) platelets can be used directly without irradiation in accordance to Council of Europe CE regulations.
  3. Attach radiation indicator labels to the selected units as per the irradiation procedure.
  4. Send the units for irradiation to the Radiation Oncology department.
  5.  Verify that the proper dose of irradiation was received while in the Radiation-Oncology department.
  6. Keep a minimum stock of 20 group O-positive units irradiated at the start of each day AND before the start of the weekend on Thursday afternoon.  Irradiate that number of group O-positive units plus any other specific requests for blood.
  7. You should use the irradiated units for crossmatching.  DO NOT CROSSMATCH FIRST BEFORE IRRADIATING!!  If the antibody screen is positive, refer the specimen to the Transfusion Service for further processing and selection of units.
    1. Note:  If a special antigen typing is needed, we may have to irradiate after selecting the antigen-matched unit if it is not found in the group of irradiated units.
  8. If a unit is required for a child < 20 kg, it must be washed before release if the unit was irradiated more than 24 hours previously according to our irradiation policy.

Physician Comments in Medinfo

Principle:

There are several different types of comments in HIIG:

  • Donor Global
  • Patient Global
  • Analytical Comments
  • Result Comments

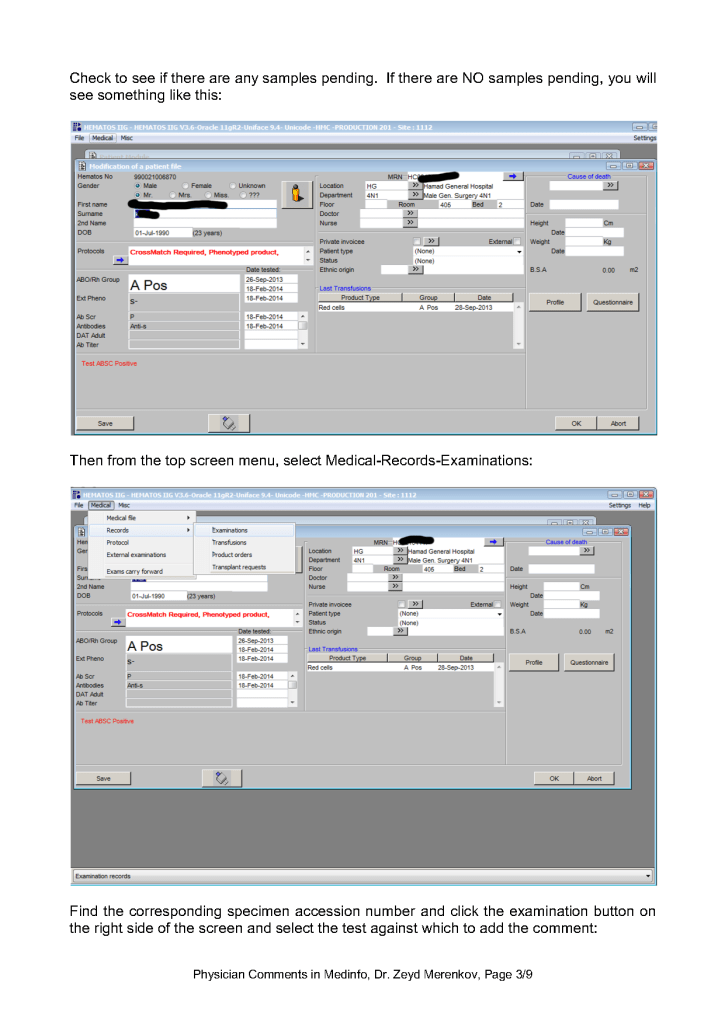
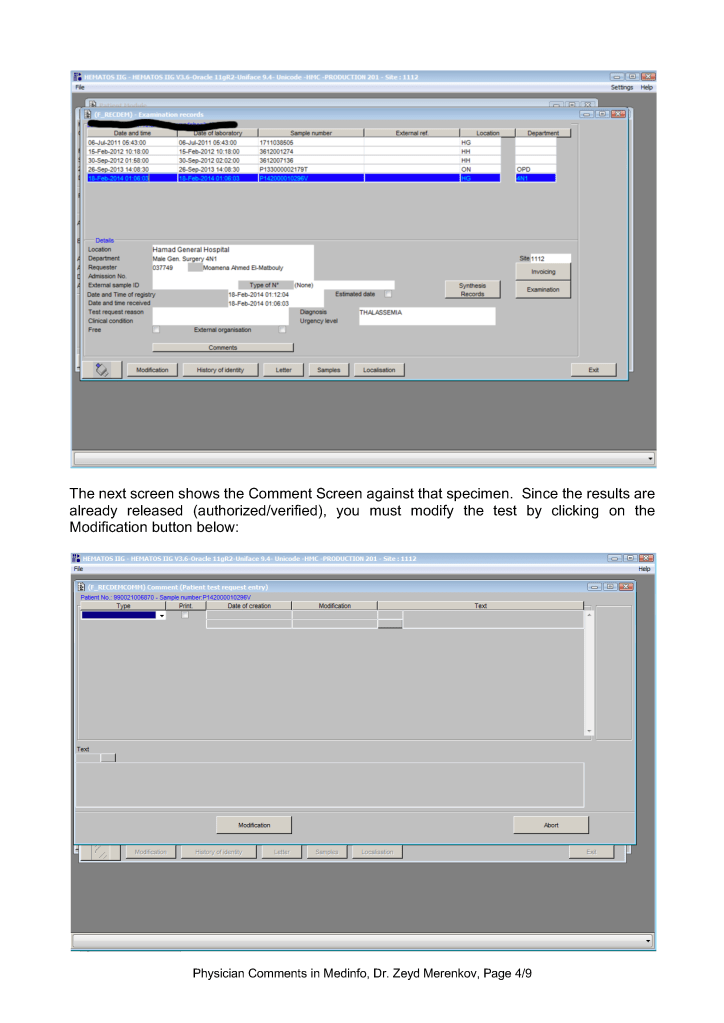
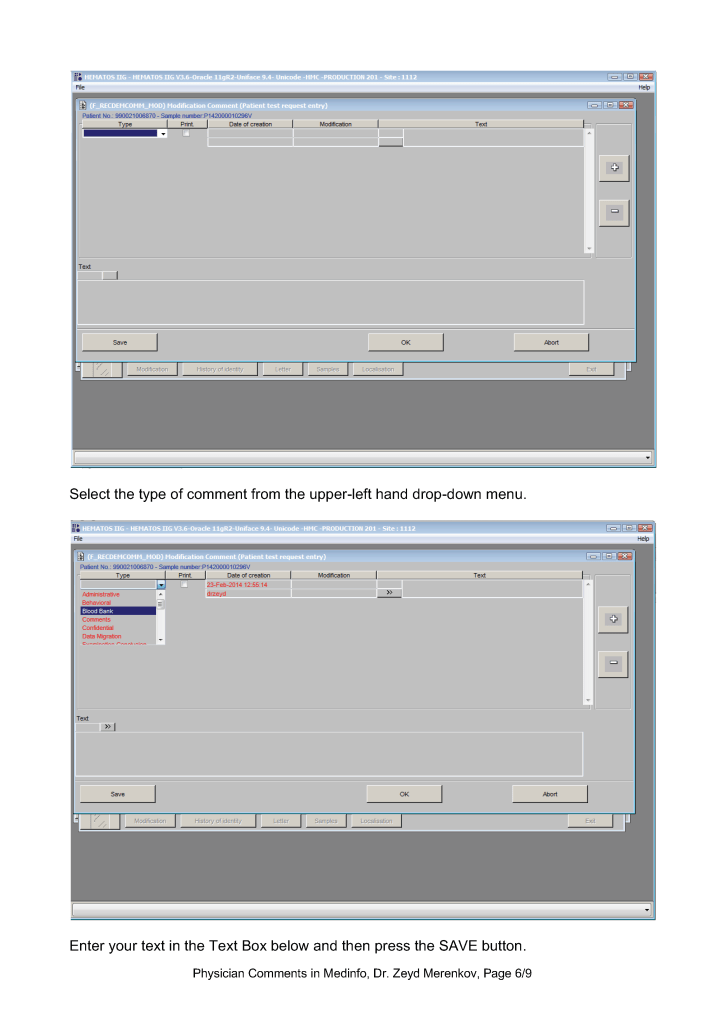
Physicians may enter any of these comment types.  Comments may be entered before or after a test is authorized/verified.  If entered after authorization, the test must be modified to accept the comment.  Only result comments are visible in the patient’s medical record.

Policy:

  1. Physicians should use comments in the following situations:
    1. Interpretations of DAT, antibody identification, ABO discrepancies
    2. Instructions for the selection of specific and/or modified blood components
    3. Donor eligibility issues (e.g. donor marker testing abnormalities and disposition)
    4. Donor reactions
    5. Telephone call documentation
    6. Donor counseling documentation
    7. Any special instructions to staff
    8. Any other situation where the transfusion physician determines it is desirable to enter a comment
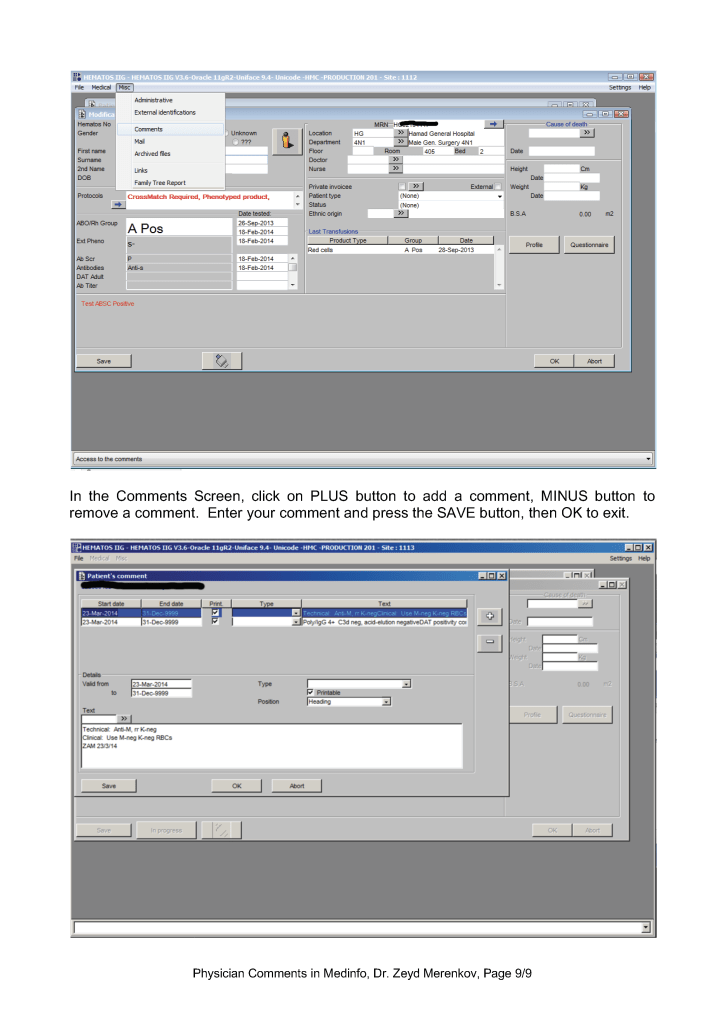
  2. Copy all result-comments and also enter then as global comments against the patient or donor record as applicable.

Procedure—Patient Result Comments After Results are Authorized/Verified:

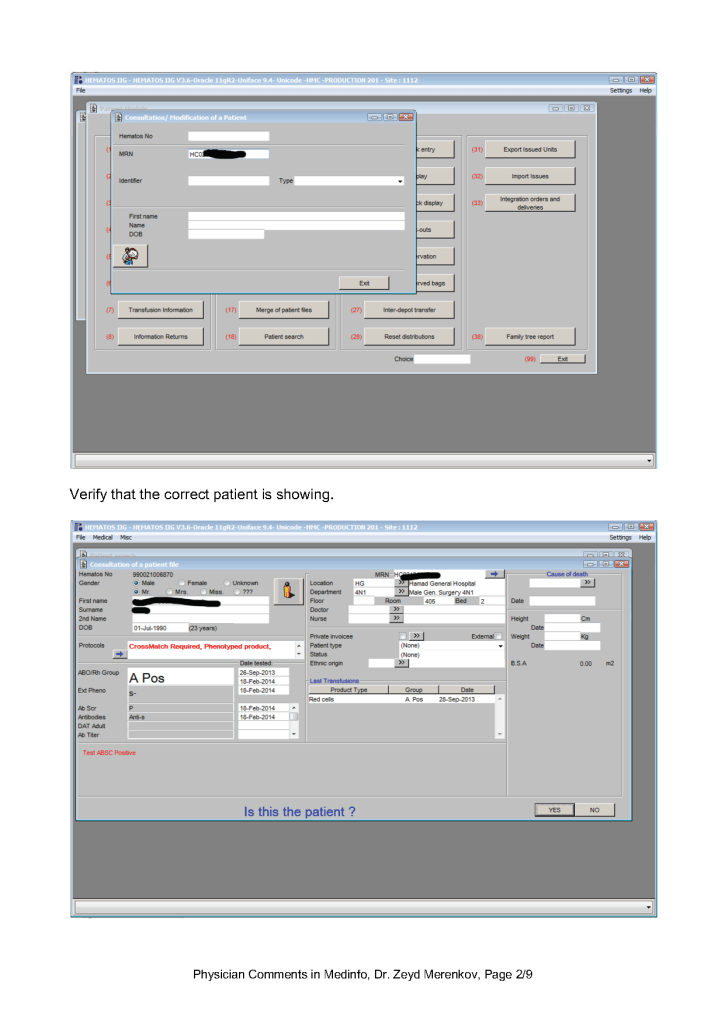
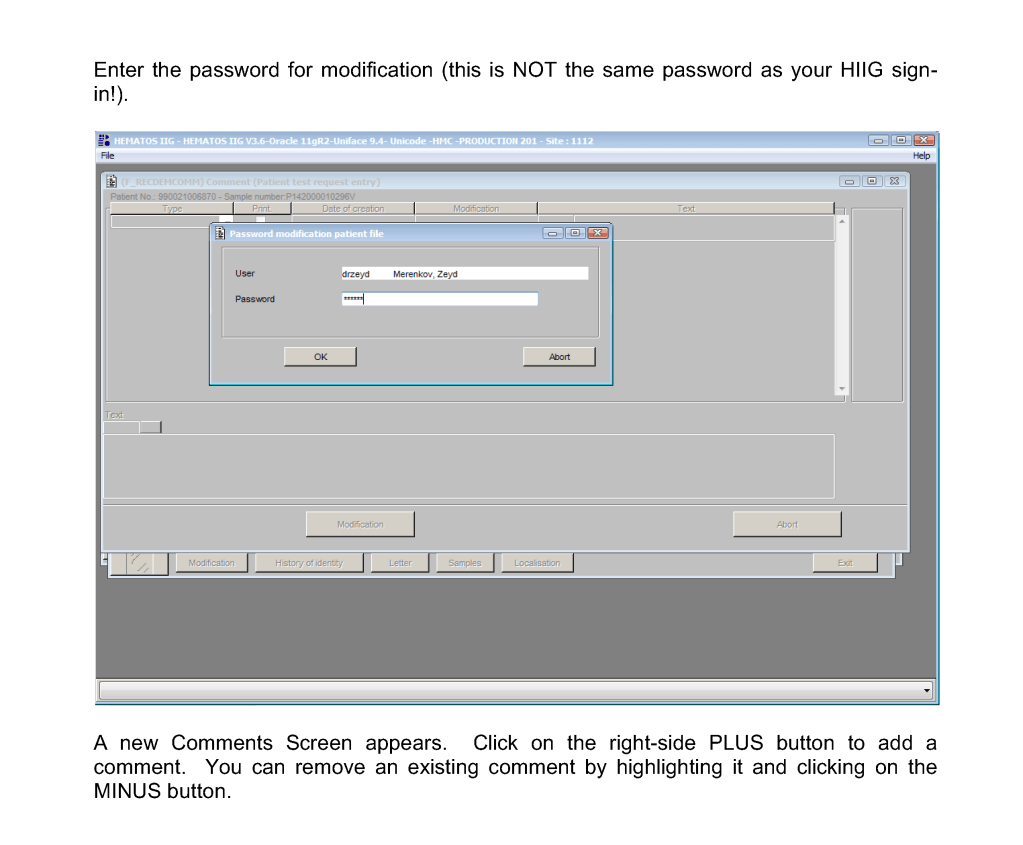
Sign into HIIG and select Patient module, Patient Consultation, and enter the patient hospital HC number.

Comments in Medinfo Hematos IIG

This post is the policy for using comments in Medinfo software.  A subsequent post will show the process of entering comments.

Principle:

There are several different types of comments in HIIG:

  • Donor Global
  • Patient Global
  • Analytical Comments
  • Result Comments
  • Contraindication Comments

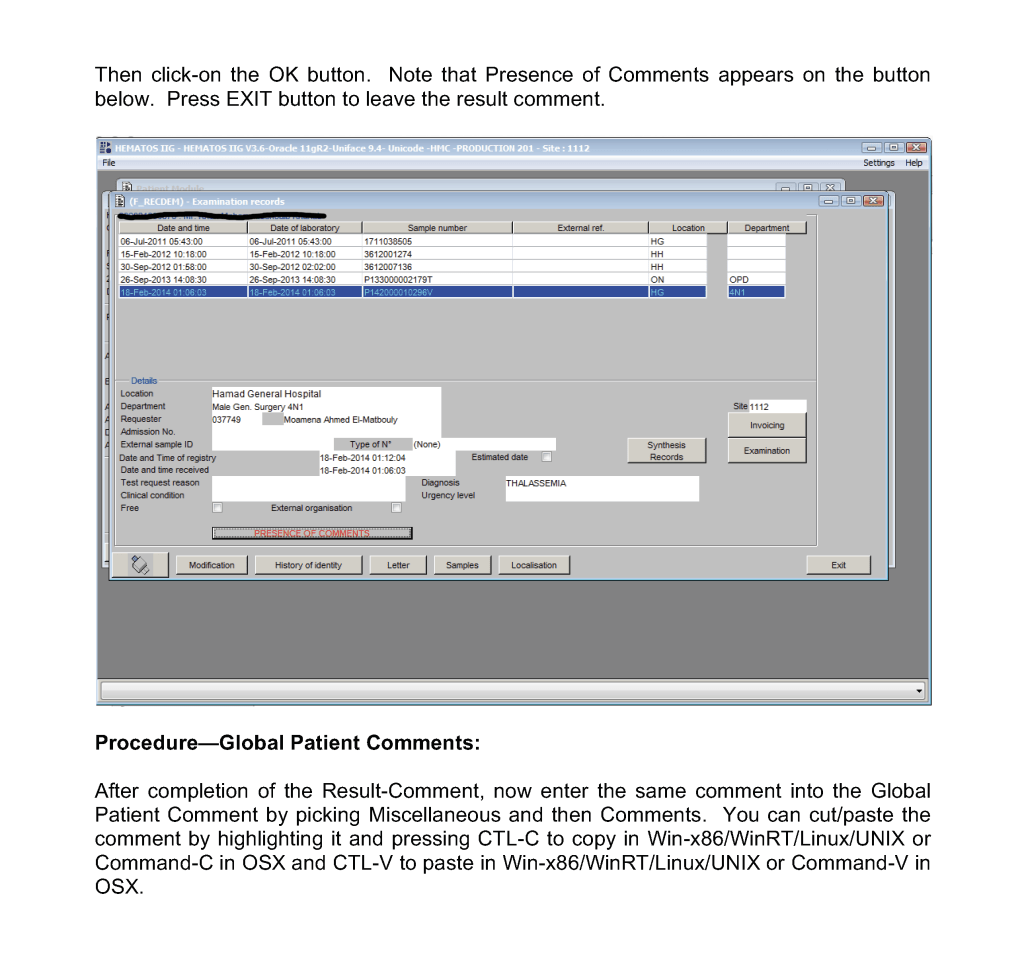
Global Comments appear on the first main screen of either the donor or patient record.  The presence of comments is indicated by a bar at the bottom of the screen (in yellow or blue saying Presence of Comments.  Double-clicking opens the list of entered comments.

Examination/Results Comments appear only when you open the result to which it is attached.  You must know in advance to which result they are linked to find them.

Contraindication Comments appear when entering a donor deferral code

At HMC, we will enter examination/results comments again as global comments (donor or patient) so it is easy for staff to retrieve them and see them with all other comments.  You can do this by cut and paste.

Physicians may enter any of these comment types.  Comments may be entered before or after a test is authorized/verified.  If entered after authorization, the test must be modified to accept the comment and require a special password (not the user sign-into HIIG).  Only results/examination comments are visible in the patient’s medical record.  Global, analysis, and contraindication comments are visible only in HIIG!  Donor comments are only visible in HIIG.

The presence of comments documents physician review of abnormal results as required by the various accreditation standards.

Policy:

  1. Only designated staff may enter comments.
  2. Comments entered after authorization/verification of results will modify the donor/patient record and require a special, high-level password distinctly different from the normal user password.
  3. Enter comments in the following situations:
    1. Telephone call documentation (e.g. critical values).
    2. Interpretations of donor or patient test results, transfusion reactions, etc.
    3. Instructions for the selection of specific and/or modified blood components
    4. Donor eligibility issues (e.g. donor marker testing abnormalities and disposition)
    5. Donor reactions
    6. Donor counseling documentation (e.g. donor counseled at 0930 on 24/3/14 about his abnormal result).
    7. Any special instructions to staff
    8. Any other situation where the transfusion physician/supervisor or designate determines it is desirable to enter a comment
  4. Copy all results/examination-comments and also enter then as global comments against the patient or donor record as applicable.

References:

  1. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  2. Workflows 1001-1005, Medinfo Hematos IIG, 2013-2014.

Documenting Physician Review of Abnormal Results

International accreditation standards require physician review of certain abnormal results such as transfusion reaction and antibody workups.  This post describes how such review is documented in Medinfo Hematos IIG dedicated blood bank software.

In general there are three main ways to do this:

  1. User ID associated with each transaction
  2. Comments against results, analysis, or globally
  3. Physician direct entry of results (e.g. transfusion reactions)

This applies to all modules of Medinfo, including donor and patient.

User ID:

The system records the User ID of the staff member who performed an action—this includes the authorized transfusion physicians  This covers everything in the system, donor or patient.  However, it may require a specific query by user ID to list all of that person’s transactions.  This is not easy to show an external assessor/inspector unless the query is performed in advance.

Comments:

For those cases requiring review, comments can be placed with the results, which will be visible to anyone viewing that record.  Additionally, internal comments can be added to the analysis and globally within the record.

Direct Physician Entry of Results and Interpretations:

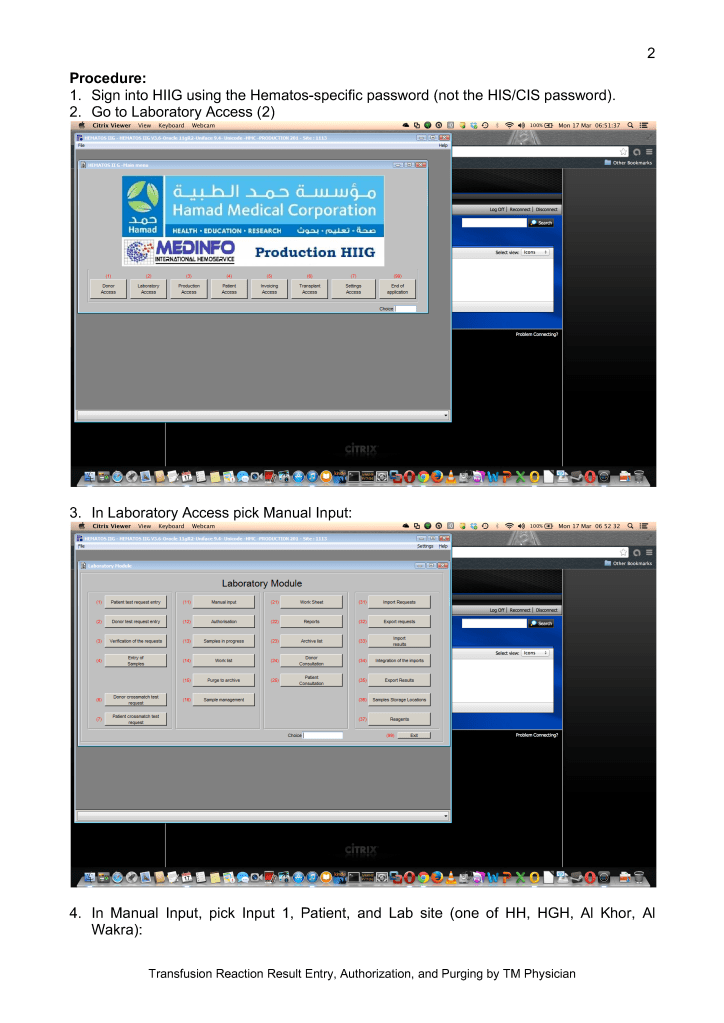
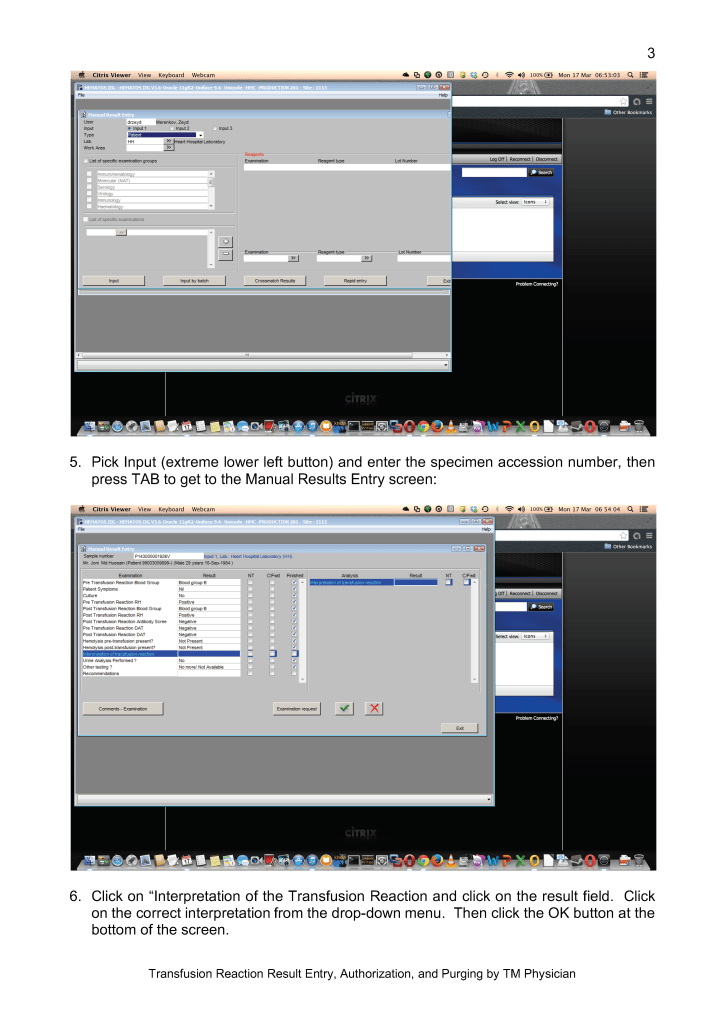
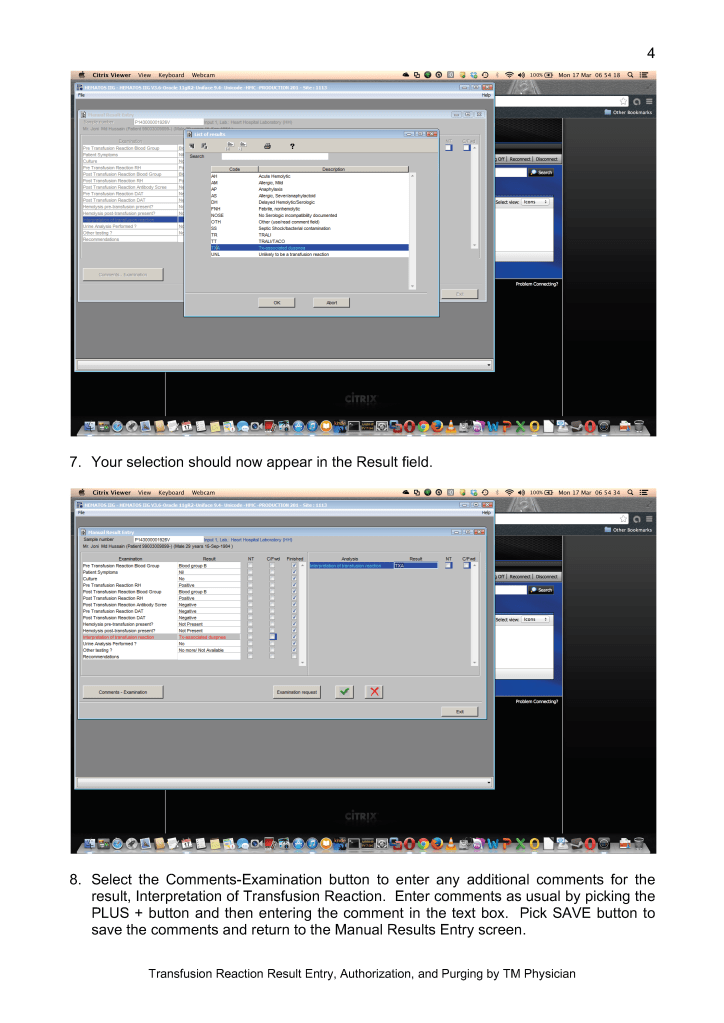
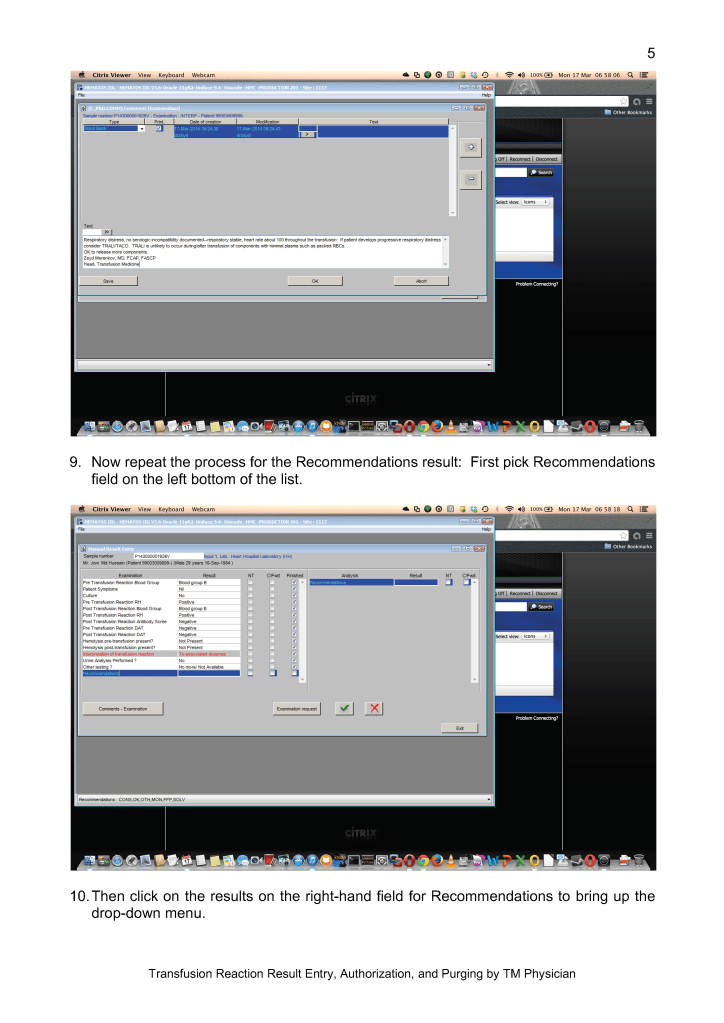
For transfusion reaction workups, physicians may directly enter their interpretations and results in the system.

Subsequent posts will show how comments and direct physician entry of results are performed in the system.