Massive Transfusion: When to Revert to the Original ABO Type

In a massive transfusion setting, the patient’s forward and reverse type will reflect the use of group O RBCs and the patient may even fully type as group O, depending on the number of units transfused.  Group O RBCs are very precious and in short supply so we need to switch the patient back to his/her own type as soon as feasible.  RBCs in additive solution (e.g. SAGM) have only minimal residual plasma so the load of anti-A,B from the O cells is minimal.  In my organization, we did not titer ABO hemolysins in blood donors.

Here is my approach:

  1. Use fresh specimen to perform forward and reverse type
  2. Check the reverse type:  does it show either anti-A and/or anti-B from the group O massive transfusion?
    1. If anti-A detected, do not give group A RBCs.
    2. If anti-B detected, do not give group B RBCs.
    3. If both anti-A and anti-B detected, continue using only group O RBCs.

Some people would recommend performing a full AHG crossmatch using the patient’s current plasma and RBCs of the original ABO type:

  1. If compatible, return to the original ABO type.
  2. Otherwise, continue using group O RBCs.

I did NOT do the full AHG crossmatch and had no hemolytic transfusion reactions if the RBCs were compatible with the current reverse type plasma.

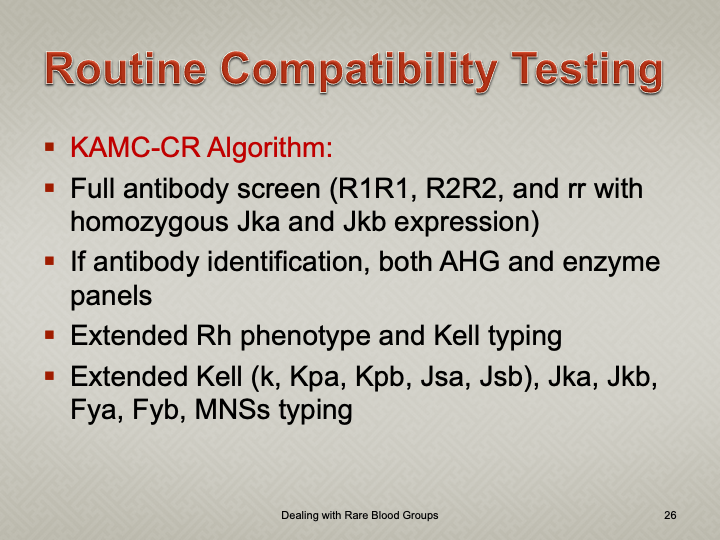
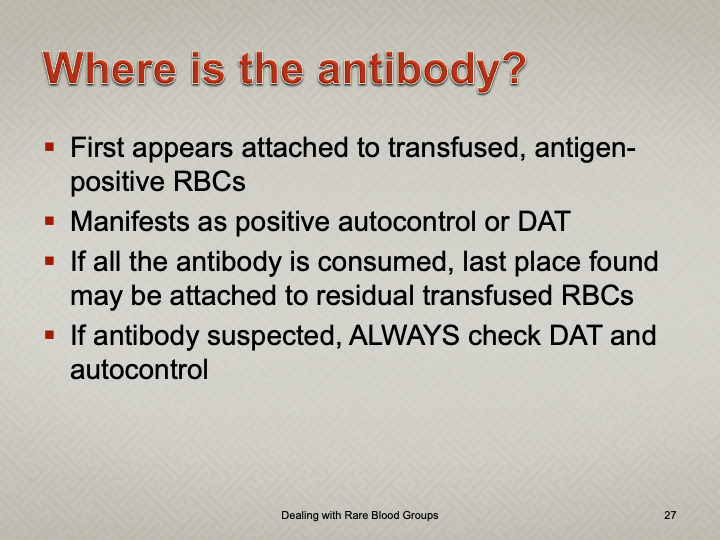
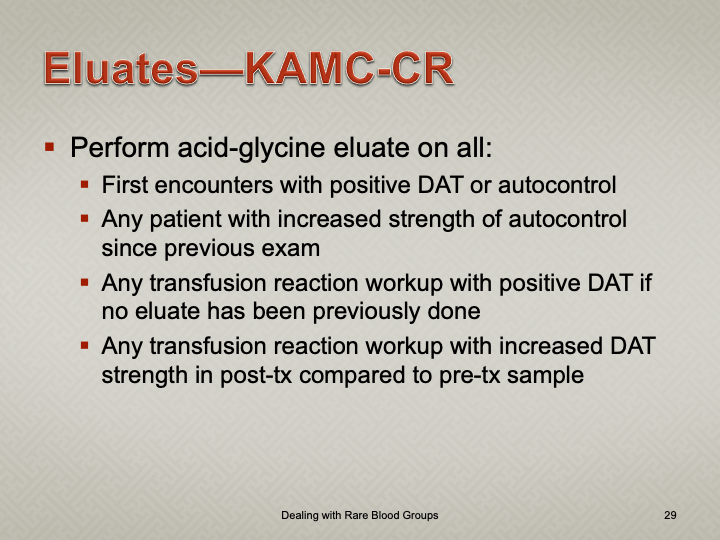
Antibodies to Public Antigens: NGHA Experience

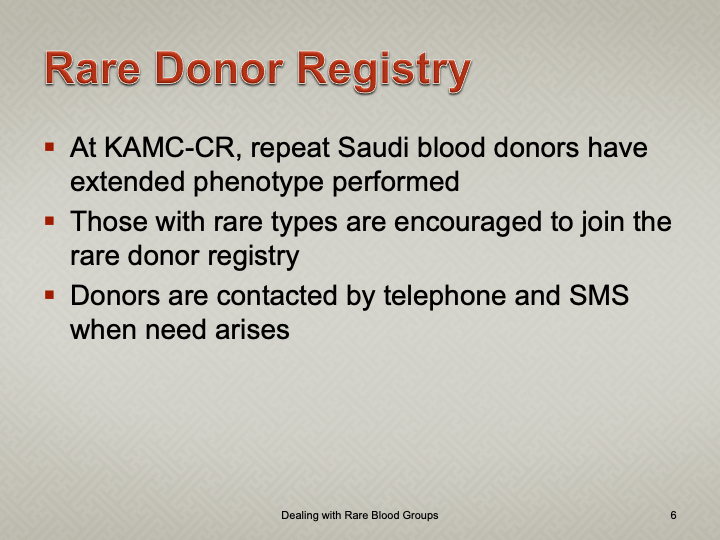
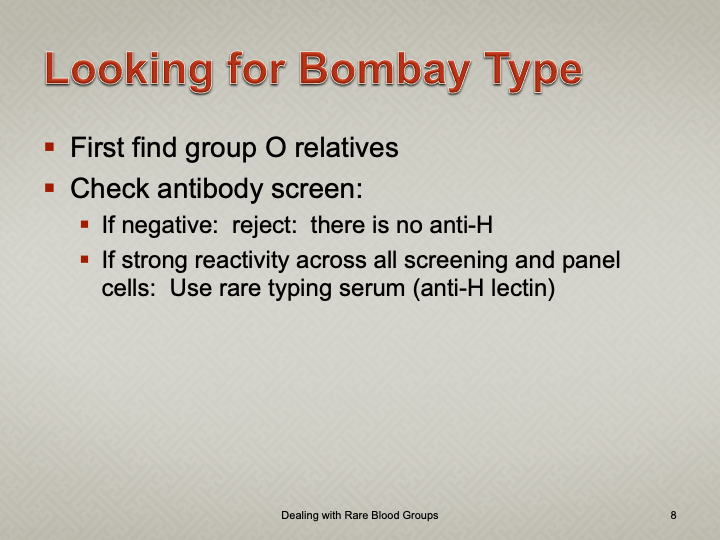
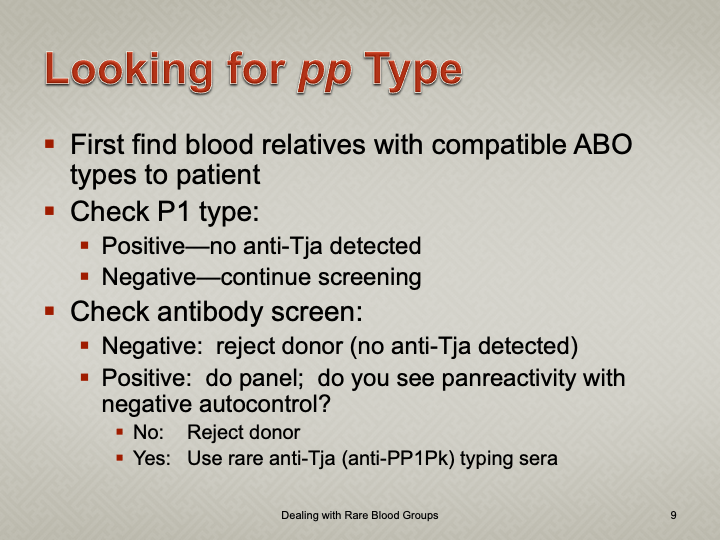
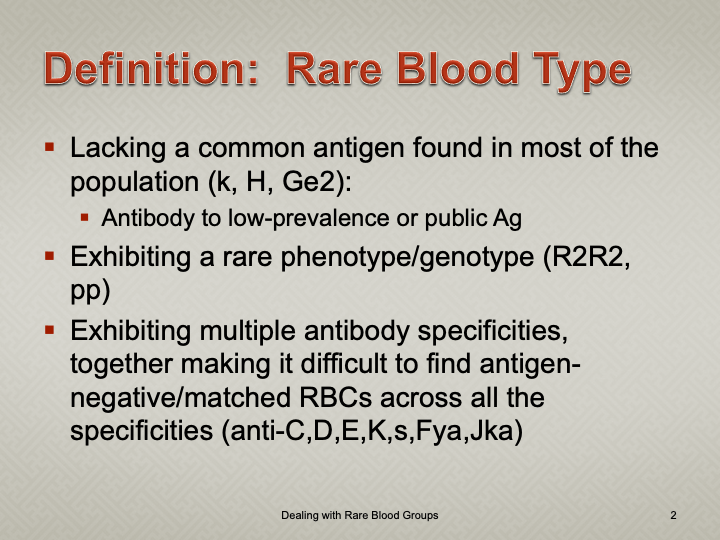
This is an update of a presentation I gave while working as Head of Transfusion Medicine for Saudi Arabian National Guard Affairs, King Abdulaziz Medical City at Riyadh. I used this strategy there and later at HMC Doha.
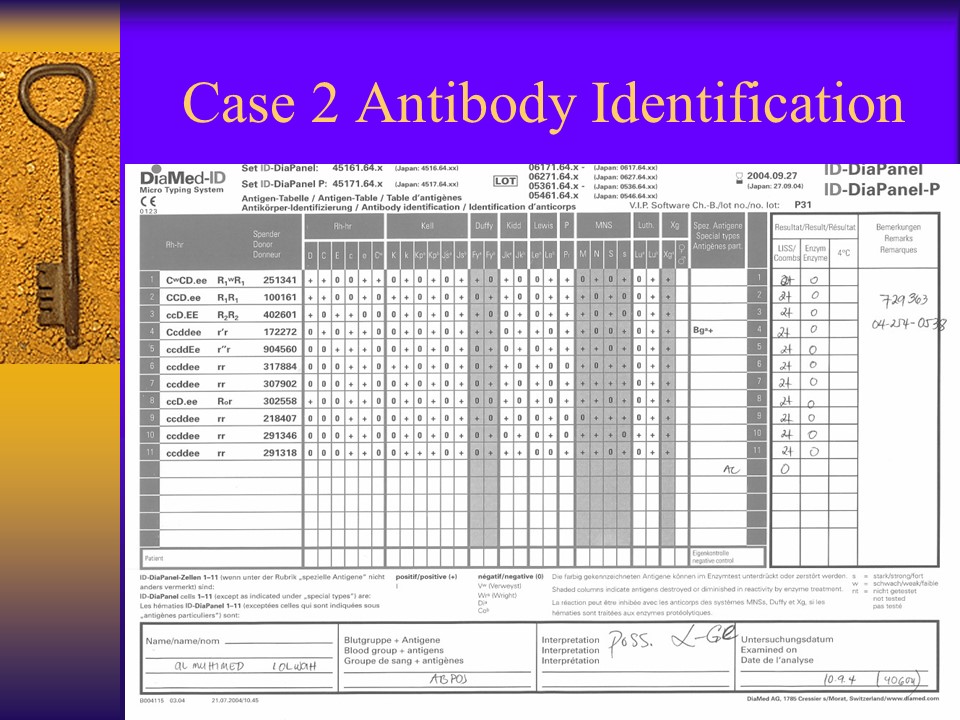
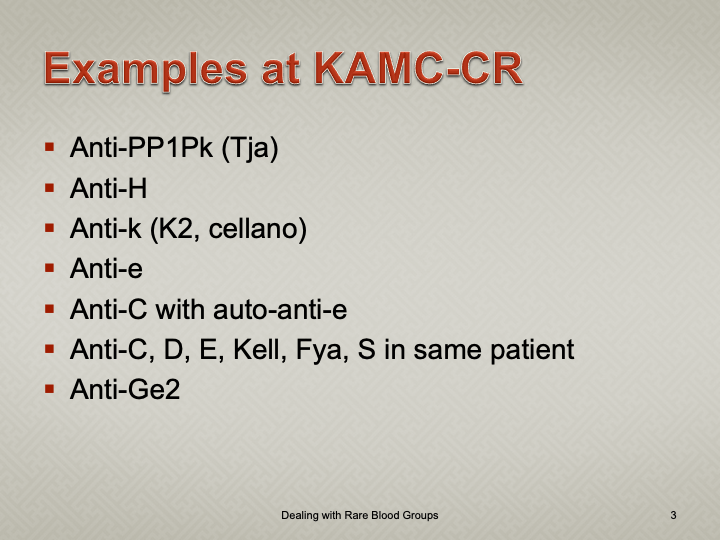
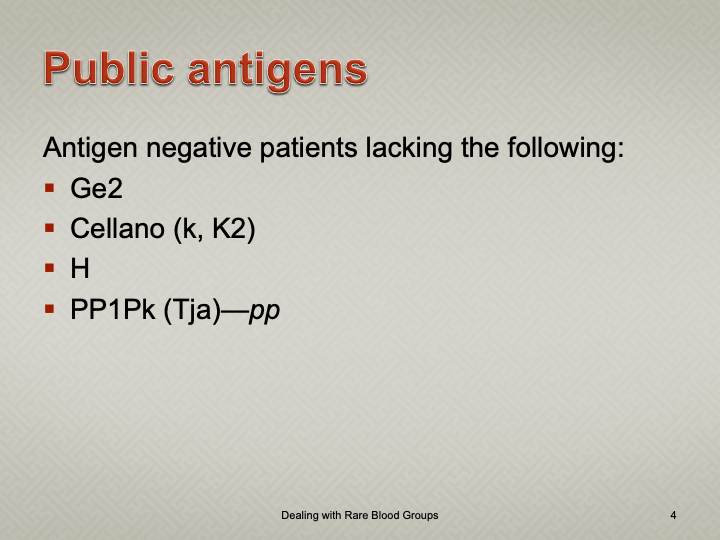
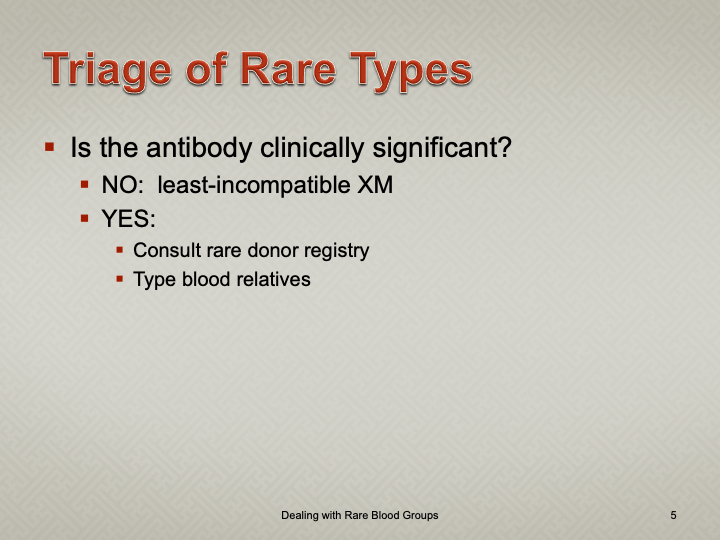
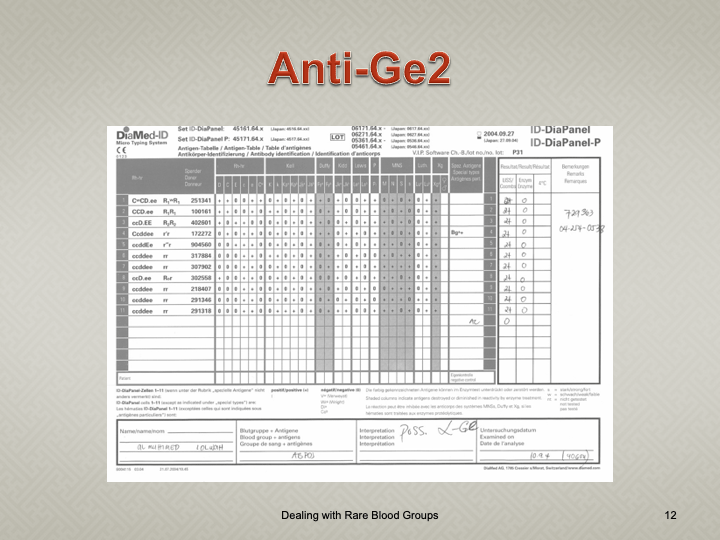
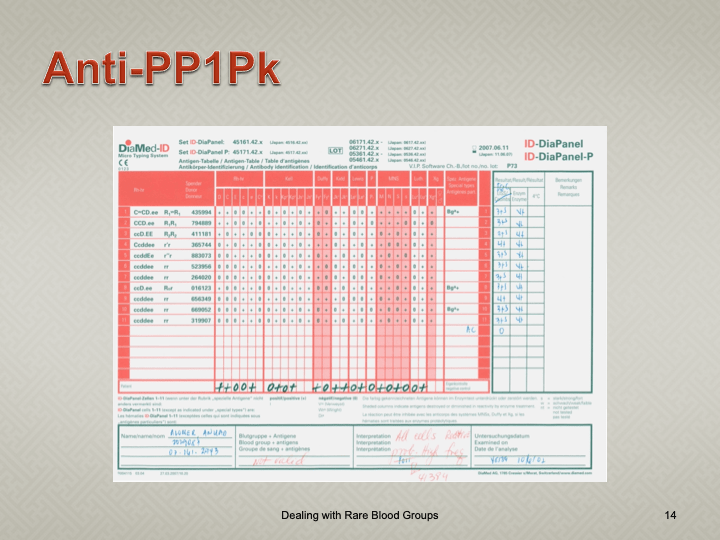
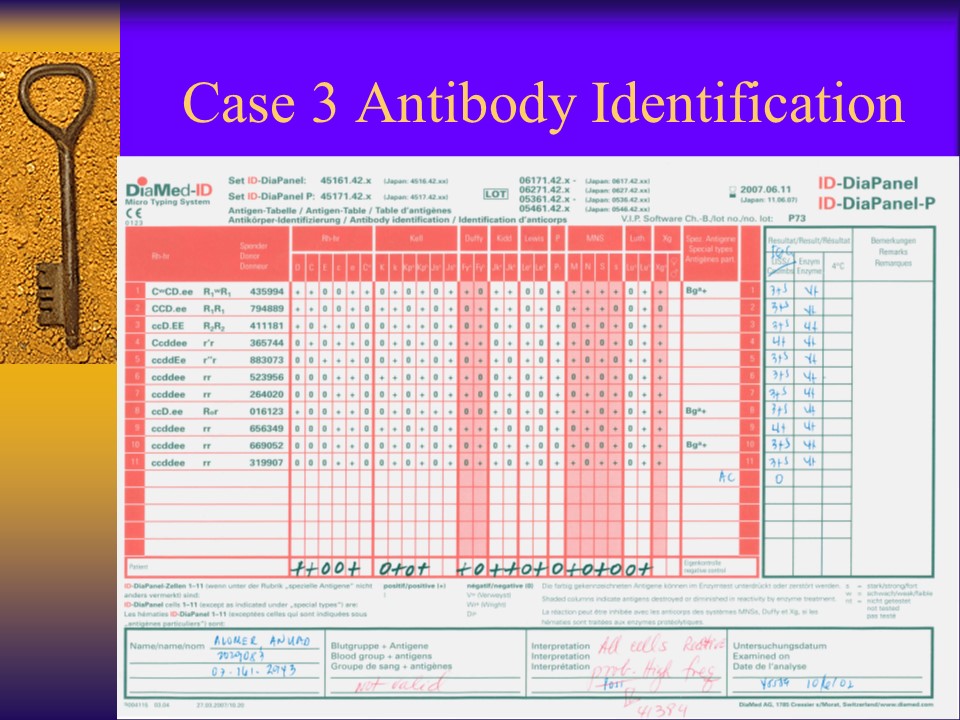
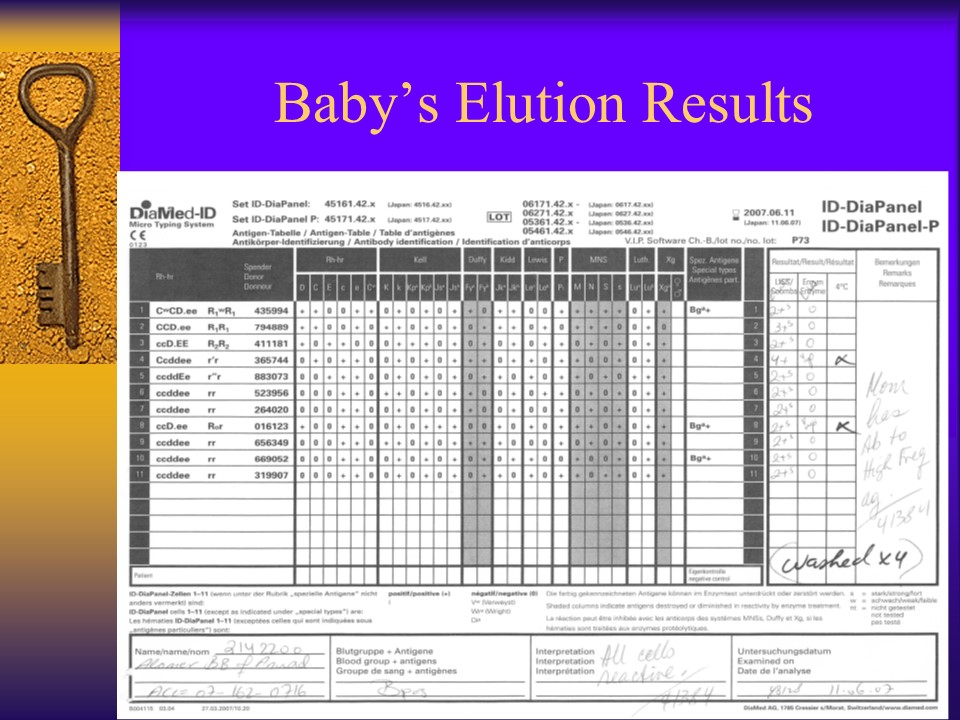
Fortunately we had access to rare antisera such as anti-Tja (anti-PP1Pk) which we could purchase from Diamed AG and its successor Biorad. I emphasize that we only sparingly used these rare antisera AFTER ruling out more common high-incidence antibodies.

Teaching Document: Irradiating RBCs from Outside Transfusion Medicine

This is a teaching document of a process to irradiate RBC components when our irradiators are not functioning.  In our system, we used Mirasol pathogen-inactivation so our RBC units were affected.  The number of units for advance irradiation was based on our historical usage of irradiated units across our system.  The workweek is Sunday-Thursday so on Thursday special effort was made to have the minimum number of irradiated units available.

We used irradiated units for compatibility testing to avoid the possibility that the unit would be released without irradiation.

Emergency Interim Procedure:

  1. Verify the patient’s diagnosis/location:  All Hematology-Oncology patients should receive irradiated blood.  Refer to the list of diagnoses for which irradiation is indicated (attached).
  2. Only PRBCs need to be irradiated.  Mirasol-treated (pathogen-inactivated) platelets can be used directly without irradiation in accordance to Council of Europe CE regulations.
  3. Attach radiation indicator labels to the selected units as per the irradiation procedure.
  4. Send the units for irradiation to the Radiation Oncology department.
  5.  Verify that the proper dose of irradiation was received while in the Radiation-Oncology department.
  6. Keep a minimum stock of 20 group O-positive units irradiated at the start of each day AND before the start of the weekend on Thursday afternoon.  Irradiate that number of group O-positive units plus any other specific requests for blood.
  7. You should use the irradiated units for crossmatching.  DO NOT CROSSMATCH FIRST BEFORE IRRADIATING!!  If the antibody screen is positive, refer the specimen to the Transfusion Service for further processing and selection of units.
    1. Note:  If a special antigen typing is needed, we may have to irradiate after selecting the antigen-matched unit if it is not found in the group of irradiated units.
  8. If a unit is required for a child < 20 kg, it must be washed before release if the unit was irradiated more than 24 hours previously according to our irradiation policy.

Nonspecific Reactions due to Reagents Near Expiration Date

This is an updated version of a previous post.

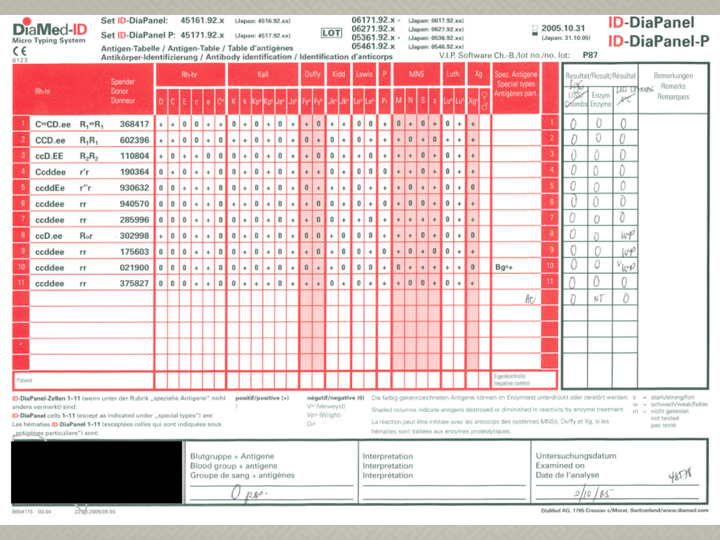
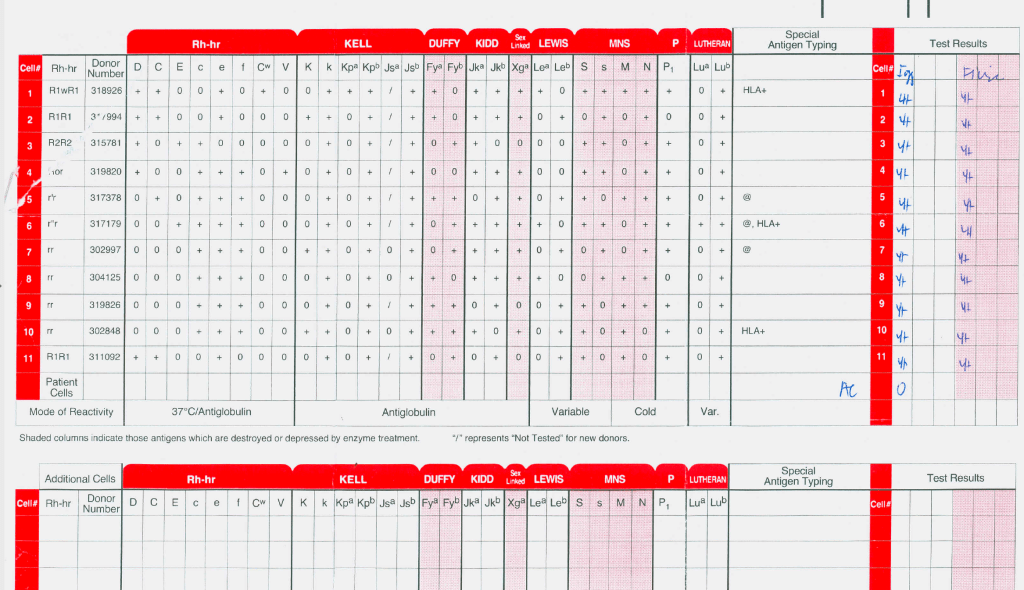
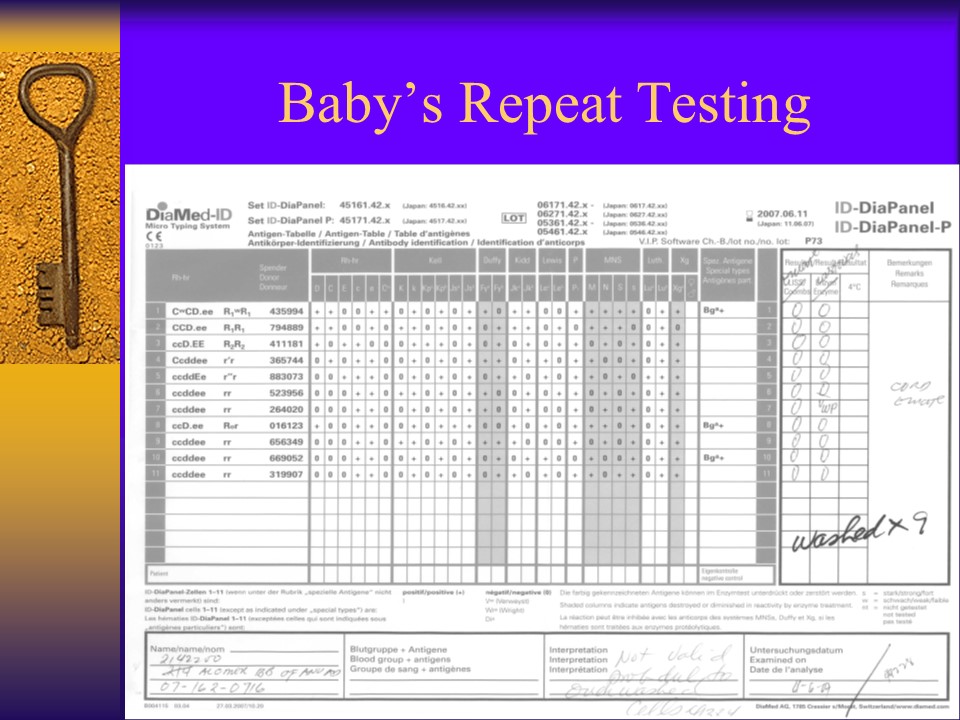
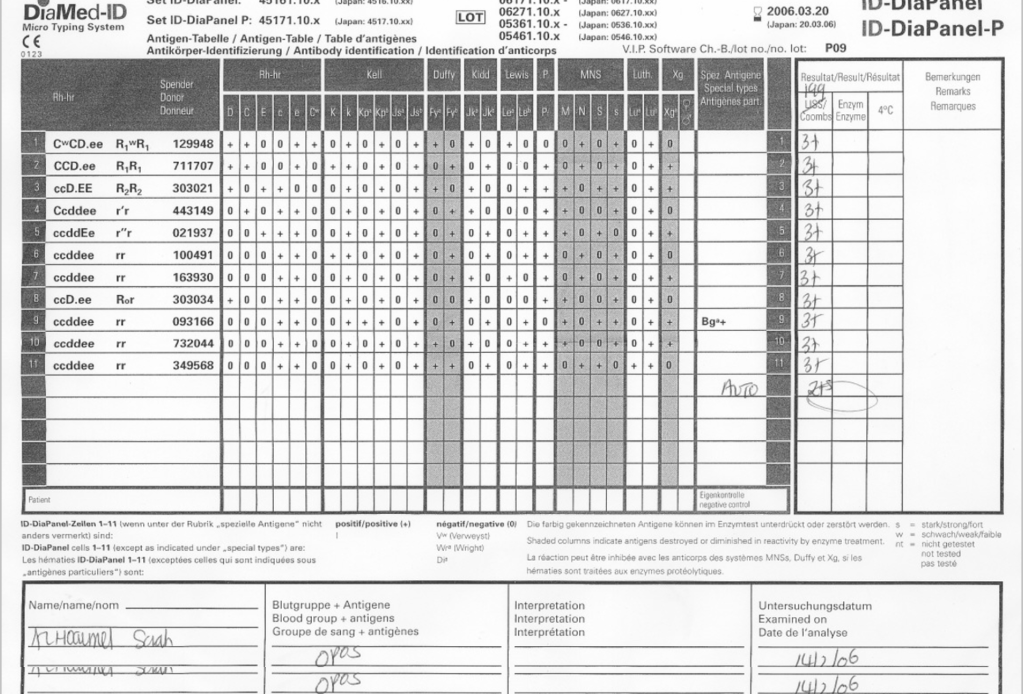
Whenever I had a “nonspecific” antibody, I had to first rule out issues with the reagents themselves. The following example shows weak to 2+ reactions in the panel cells and autocontrol.

The variability in the reactions made me initially uncomfortable about called this WAIHA. I then checked the panel details: the testing was done only six days before the panel outdate.

I told my staff to repeat the workup with the new panel expiring five weeks later. The difference is astounding!!

Remember:  if you work in the Middle East, the environmental conditions can be extreme in summer (>50C).  Do you know how your reagents were handling during transport?

My advice: if you are concerned there is a clinically significant antibody but cannot confirm it, consider repeating the workup using fresh reagents and a fresh specimen. Repeating the workup after a few days may make the detection clearer.

Original Panel with Near Expiry Reagents:

Test performed 7/2/06, reagents expire 13/2/06:

Same Patient with New Reagents and New Sample:

Test Performed 14/2/06, reagents expire 20/306:

Rare Jka Antibody

This is a repost of this rare antibody with a few new additional comments.

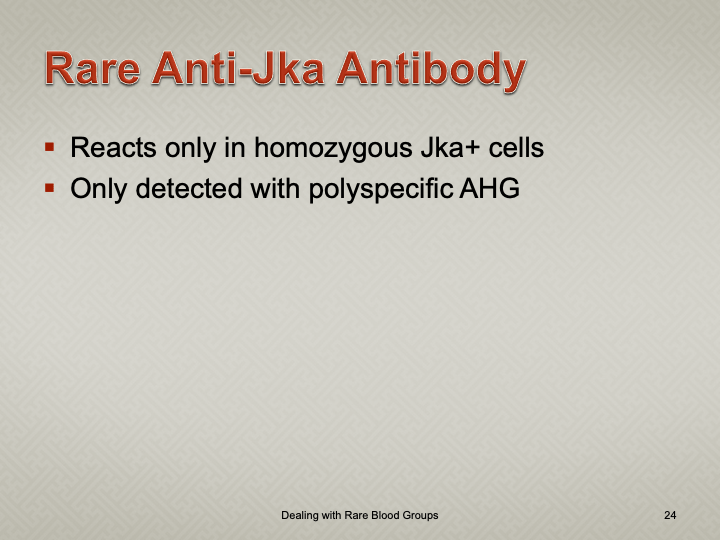
This is a rare anti-Jka antibody that only reacts with polyspecific AHG and only in homozygous Jka+ cell.  In the past three decades, I have only seen three of these.

Almost all anti-Jka and anti-Jkb antibodies can be detected using heavy-chain gamma specific AHG.  I prefer to use this reagent since it minimizes interference from cold antibodies.

Whenever you have a nonspecific antibody, never discount the possibility of a Kidd antibody.  Consider doing extended phenotyping and include Jka and Jkb typing and always check for dosage effect.  I have a specific post on my approach to nonspecific antibodies.

Select antibody screening cells including homozygous Jka+ and homozygous Jkb+.  This usually requires a three-cell screen.

Never forget that a negative result only means not-detected.  If there is other evidence for hemolysis, consider performing additional studies.

Physician Comments in Medinfo

Principle:

There are several different types of comments in HIIG:

  • Donor Global
  • Patient Global
  • Analytical Comments
  • Result Comments

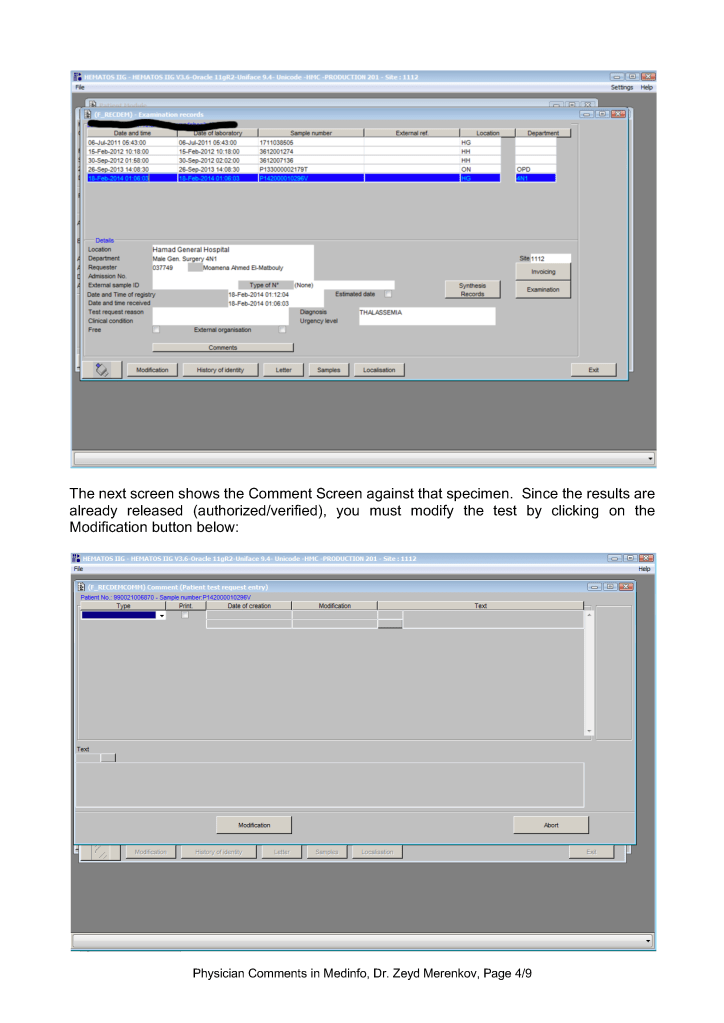
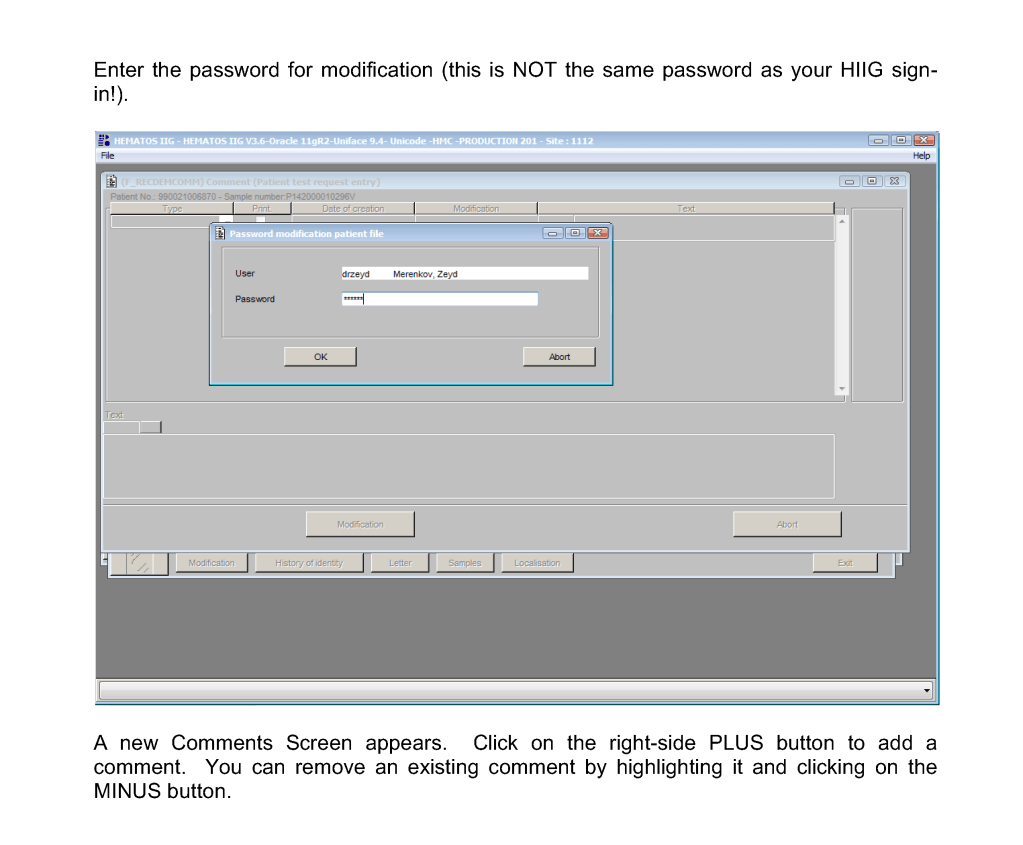
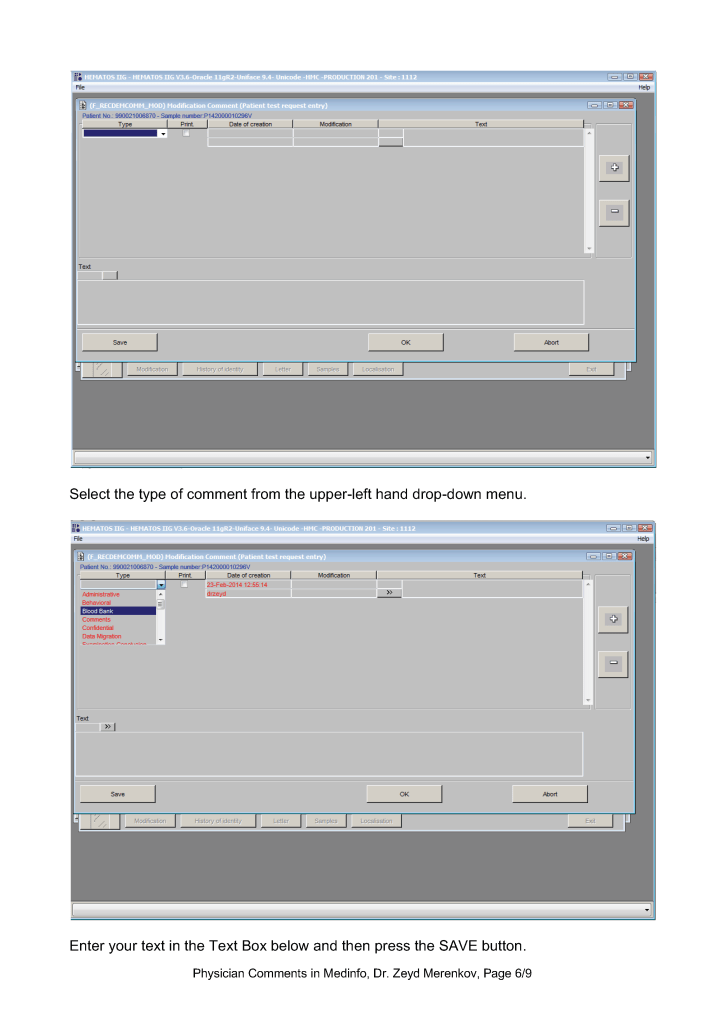
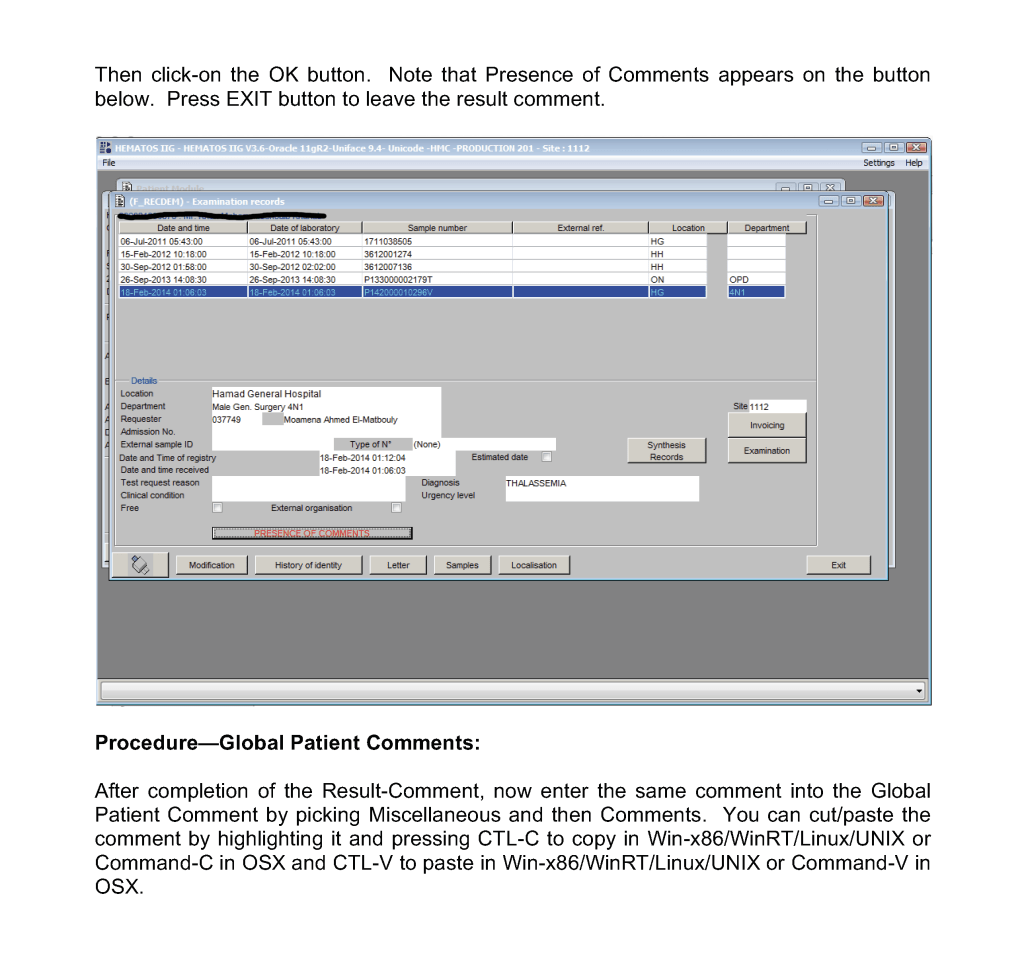
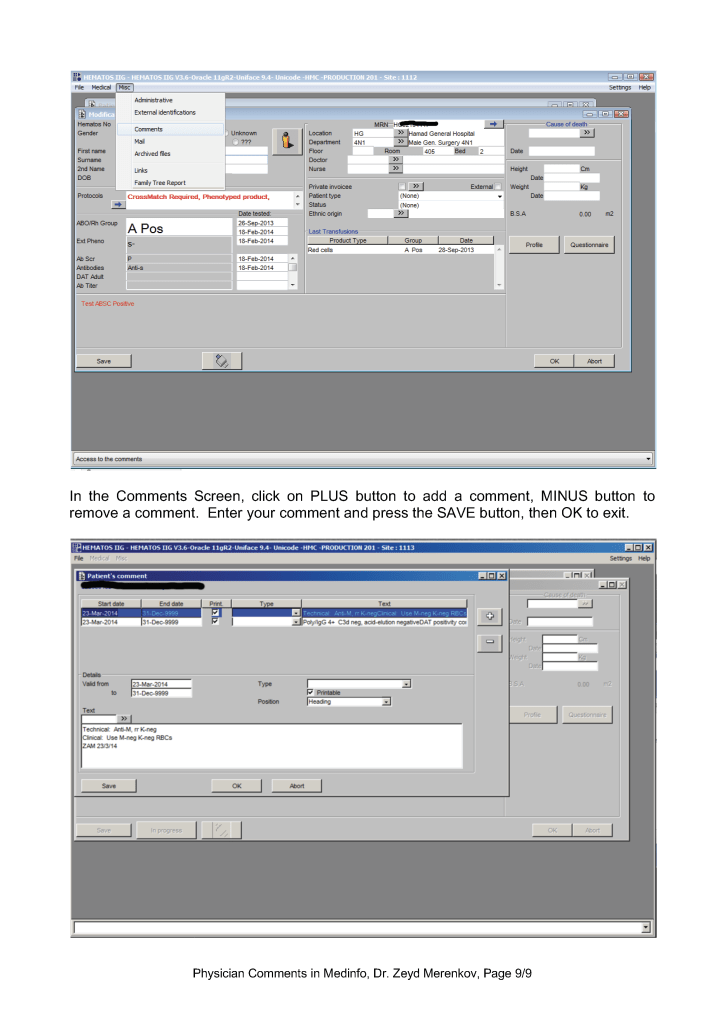
Physicians may enter any of these comment types.  Comments may be entered before or after a test is authorized/verified.  If entered after authorization, the test must be modified to accept the comment.  Only result comments are visible in the patient’s medical record.

Policy:

  1. Physicians should use comments in the following situations:
    1. Interpretations of DAT, antibody identification, ABO discrepancies
    2. Instructions for the selection of specific and/or modified blood components
    3. Donor eligibility issues (e.g. donor marker testing abnormalities and disposition)
    4. Donor reactions
    5. Telephone call documentation
    6. Donor counseling documentation
    7. Any special instructions to staff
    8. Any other situation where the transfusion physician determines it is desirable to enter a comment
  2. Copy all result-comments and also enter then as global comments against the patient or donor record as applicable.

Procedure—Patient Result Comments After Results are Authorized/Verified:

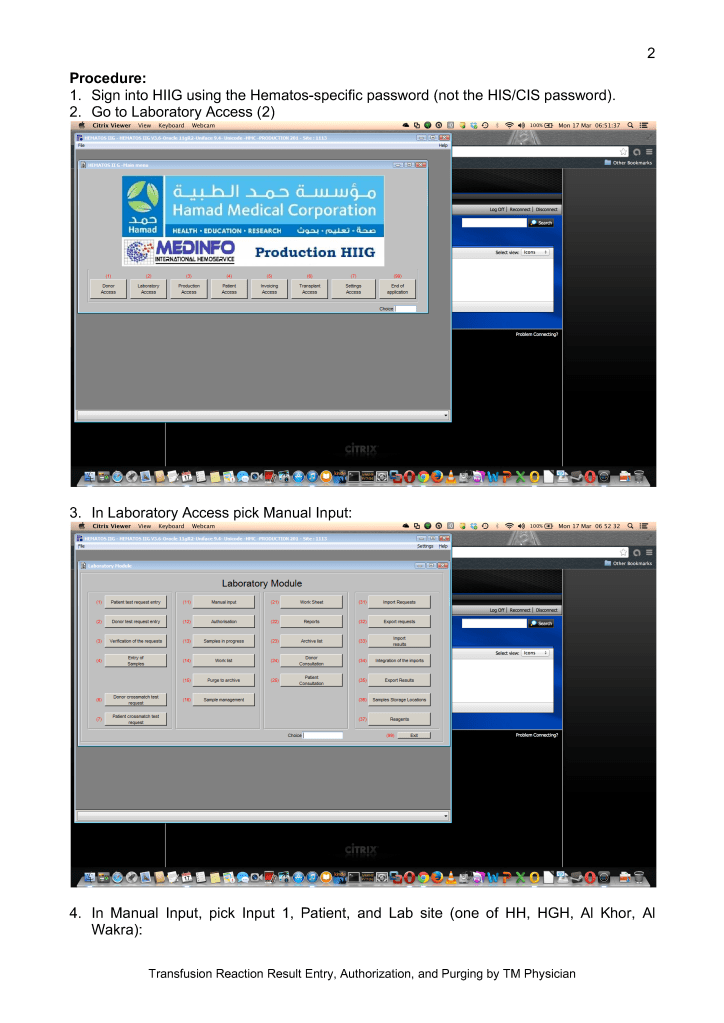
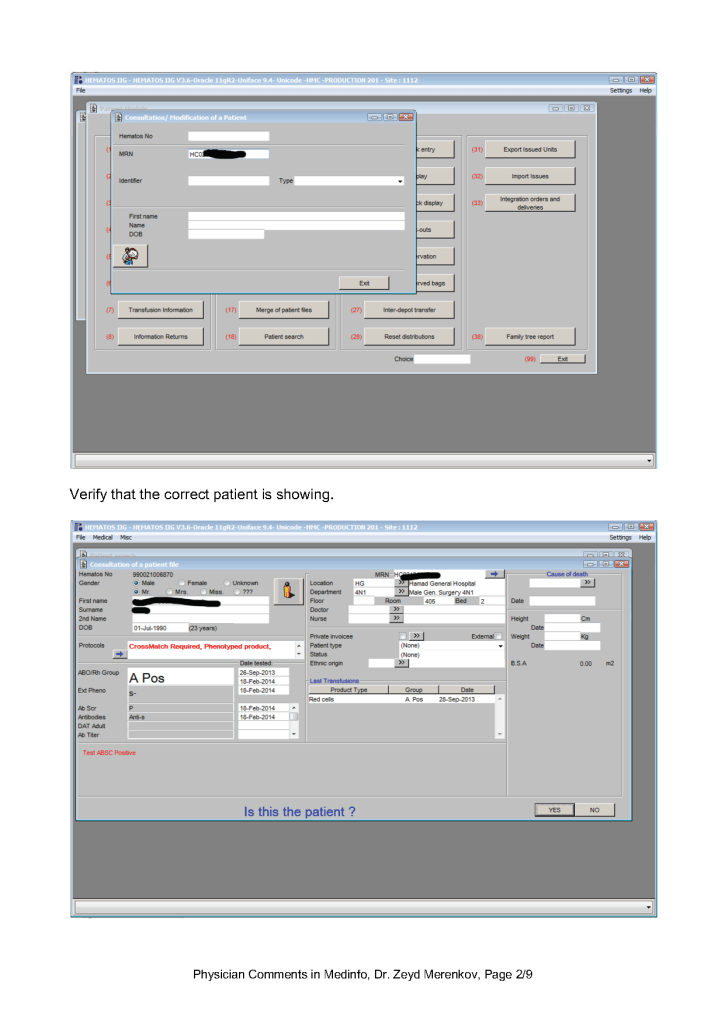
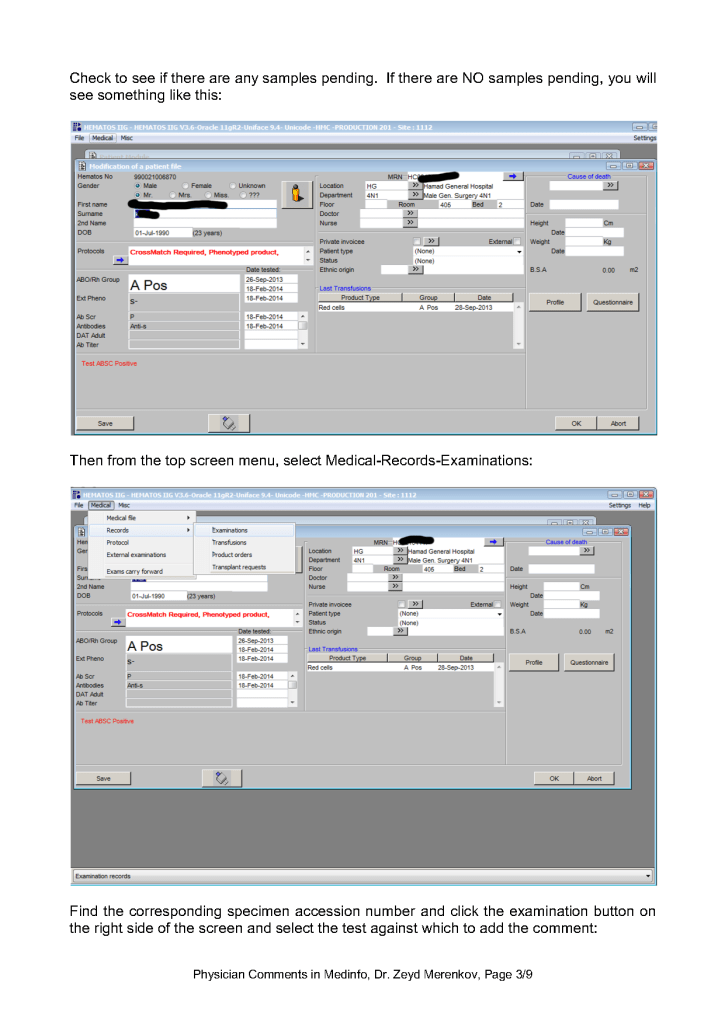
Sign into HIIG and select Patient module, Patient Consultation, and enter the patient hospital HC number.