Processes and Software Building 56: Multi-Site Patient and Donor Considerations

As our hospital network expanded, there were many patients who moved between locations.  They might first start in an emergency room and then be transferred to a specialty hospital.  These locations might be served from different hospital blood banks/transfusion services.  What happens if work is progress from one site when the new site receives the patient.  Must the previous workup be repeated or could it be used for transfusion at the next site?

For example, the ABO typing could be performed at one site and the antibody screen at a second site, and the antibody identification at still another site.  Could the results be used across the entire system?

I had multiple hospital blood banks and blood donor centers.  The general and specialty laboratories had multiple sites.  The hospital information system was set up so that the various tests could only be performed at specific designated sites.  This posed problems as patients were moved around or if some site(s) became inoperative since the specimens then had to transported at great distances for testing.  Only a few basic STAT tests were available at all sites.

It was my decision to allow all test categories at all sites, e.g. a DAT request from any site, any methodology, could be used to satisfy the order.  Similarly, all donor processes were available at all donor centers (the processes could be completed at one or more sites).  Different hospital blood banks had different equipment but all the test categories were the same across site—the methodologies might differ.  We had at least four different DATs across our system.

The interface between the blood bank and hospital system worked as follows:  In the hospital information system HIS, test orders pointed to a category of testing and any methodology for that category at any site could be used in the blood bank system for testing and reporting back to the HIS.  Any test in a category from any site could be used to satisfy the test request.  Blood bank staff would choose the particular test methodology to use.  It was NOT specified by the HIS!

In summary, for blood banks and donor centers within our system, the work could be flexibly moved between sites.  There was no need to repeat testing when a patient transferred to a new site.  The only type the work was repeated if testing was done at an institution outside our system.
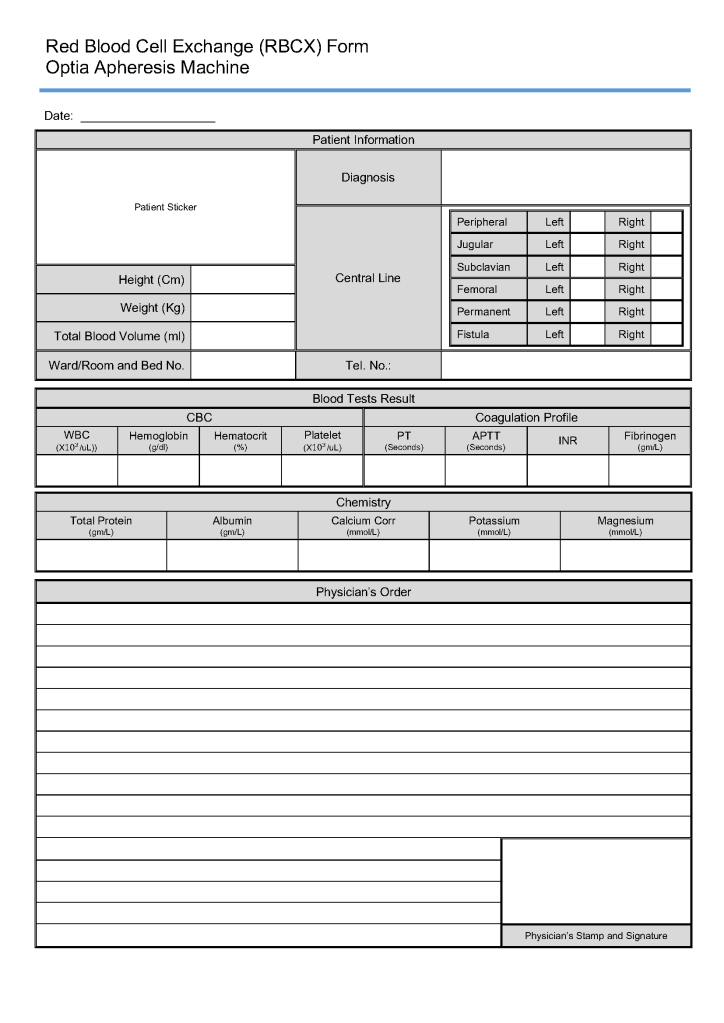
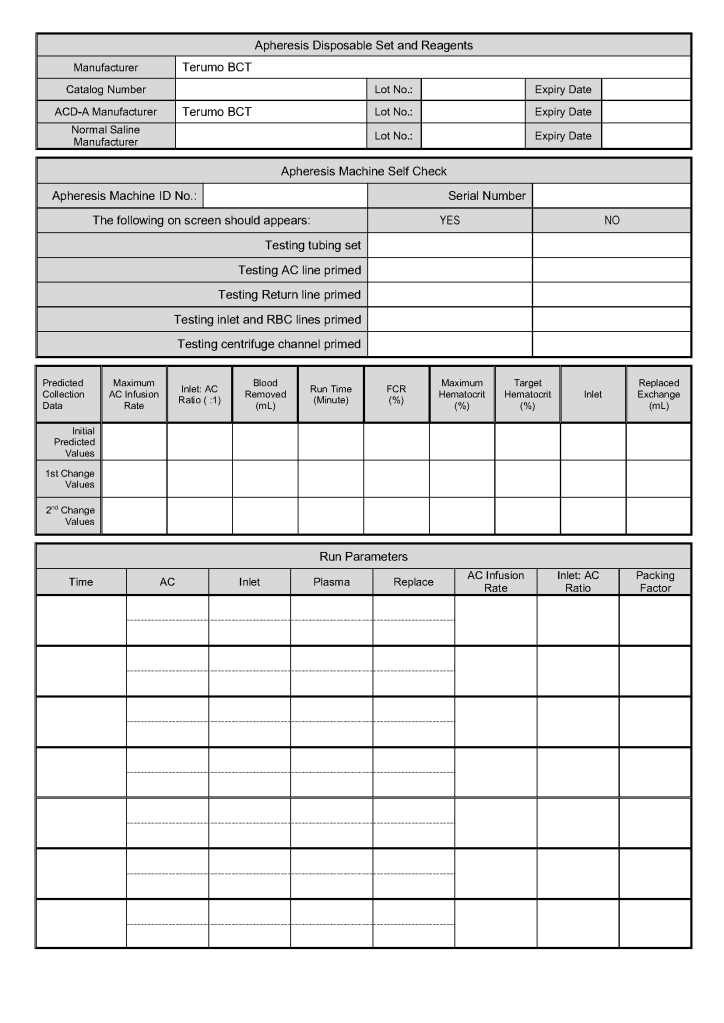
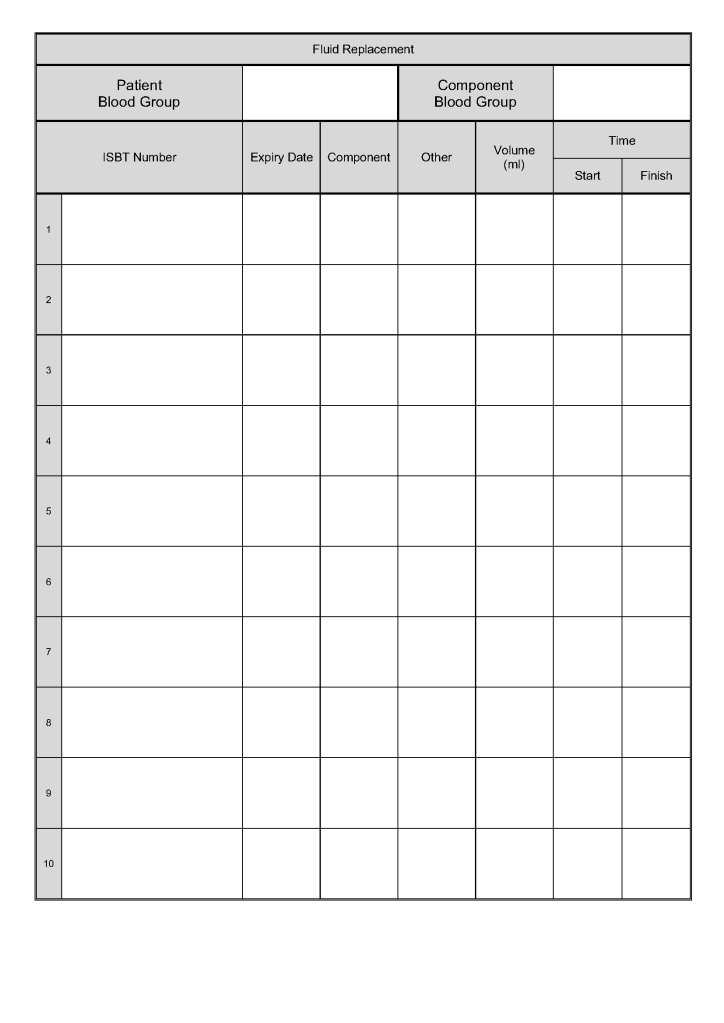
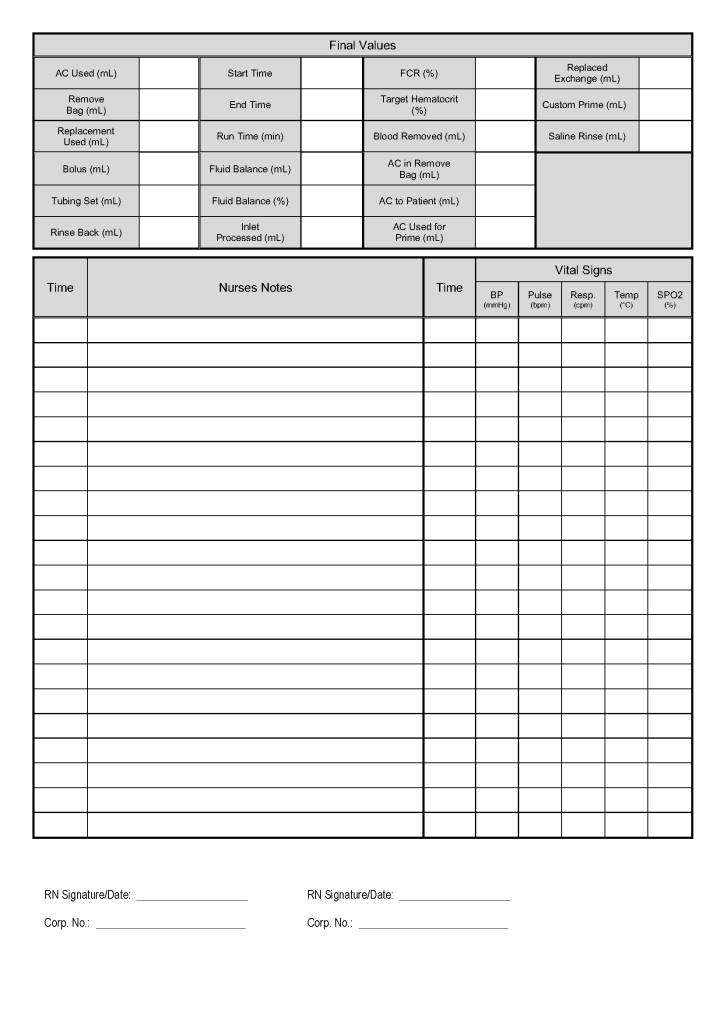
Sample RBC Exchange Form

This form was developed by my senior apheresis staff at HMC Doha in conjunction with me. It organizes the data to minimize the time needed to put the data in place so that the apheresis nurse can concentrate on the patient. It can serve as a good template from which to build a computer form.

I want to thank Ms. Mini Paul, Head Apheresis Nurse, and Dr. Saloua Al Hmissi, Consultant Transfusion Medicine for all their efforts.

ABO Antibodies

Principle:

Historically, the Lui-Freeze-Thaw elution method was used to detect ABO antibodies in suspected cases of ABO hemolytic disease of the fetus/newborn HDFN.  However, the detection of such antibodies does not mean that they are clinically significant.  If a clinically significant antibody is suspected, perform acid elution instead.  If you want to detect ABO antibodies in a neonate or in a transplant setting, you can use this eluate against reagent A and B cells.

Policy:

  1. For suspected cases of significant ABO antibodies (HDFN, organ transplant), perform acid-elution:
    1. For ABO antibodies, test the eluate against reagent A and B cells using antiglobulin phase.
      1. If the mother is ABO-incompatible with the neonate and the neonate’s DAT is positive with a negative eluate against panel cells, then test against A and B cells to rule out ABO antibodies
      2. The same applies to organ transplant cases to detect ABO antibodies.
  2. For detection of non-ABO antibodies, test the eluate against an antibody panel (i.e. group O cells).

References:

  1. Technical Manual, Current Edition, AABB, Bethesda, MD, USA
  2. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  3. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

Training Future Transfusion Medicine Physicians: Need for Technical-Medical Expertise

In a previous post, I discussed transfusion training for hematology fellows and general pathology residents.  I have no expectations that most of them have any interest in the field so I suggested concentrating on the interpretation of the direct antiglobulin test DAT and turn-around-times for services.

In contrast, the transfusion medicine physician in-training needs to understand in detail all processes, donor and patient—especially test interpretation so that he/she can make medical decisions and variances.

During my training, I was fortunate to be in a residency training program that also had an American Specialist-in-Blood Bank SBB training program.  To a large extent, I attended the SBB program and even worked on the ā€œwetā€ specimens.

I had no delusions that I would ever function as technologist or SBB in the blood bank.  However, that extended blood bank training has made me the physician I am.  I can correlate advanced, even reference, procedures to my medical knowledge and thus provide a unique offering.  In contrast, even the SBB is not a physician and cannot make the medical correlations.  Recently, I was flattered at an AABB meeting when the speaker thought that I was an SBB.

In certain regions where reference immunohematology laboratories and SBBs or equivalent are rare, the transfusion medicine should have sufficient technical background to help fill this gap.  In my practice, I review all antibody and DAT workups and make interpretative comments for the physicians and nursing staff.  These comments are entered into the blood bank computer system.

I personally tutor the trainees and make certain that they understand potentially dangerous patterns such as antibodies to high-incidence antigens, significance of the autocontrol in panreactivity, and assessing for fatal acute transfusion reactions—both hemolytic and non-hemolytic.

It also helps when I can discuss with my technical staff my interpretations and choices for clinical management.  They get a better idea how important their work is for patient care and understand how any errors may adversely affect the patient.

In regions where there are good immunohematology reference laboratories, some of this may be less necessary.  I lament that transfusion medicine physicians may not maintain these skills and must rely on others to their detriment.  Even if one is comfortable with this, the physician is still ultimately responsible for making the clinical decision.

ABO Subgroup Testing for Organ Donors

Principle:

Organ donors with a history of RBC transfusion within the past three months must have ABO subgroup (weak A as detected by A2 cells and anti-A1 lectin) if the transfusion included group A RBCs.

Policy:

  1. Organ donors who are typed as A should be tested to distinguish group A1 from weak subgroups of A.
  2. Use anti-A1 lectin and A2 cells as indicated.

Reference:

Standards for Blood Banks and Transfusion Services, AABB, Current Edition, Bethesda, MD, USA

Sample Validation Change Protocol: Donor Hgb Levels

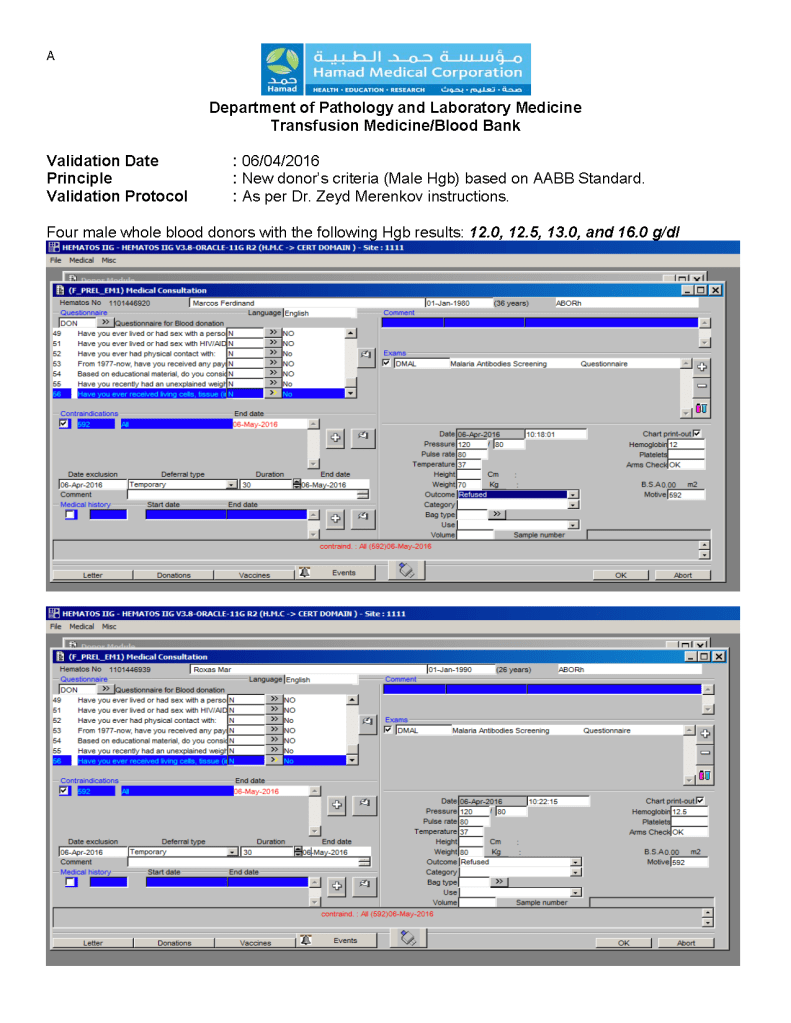
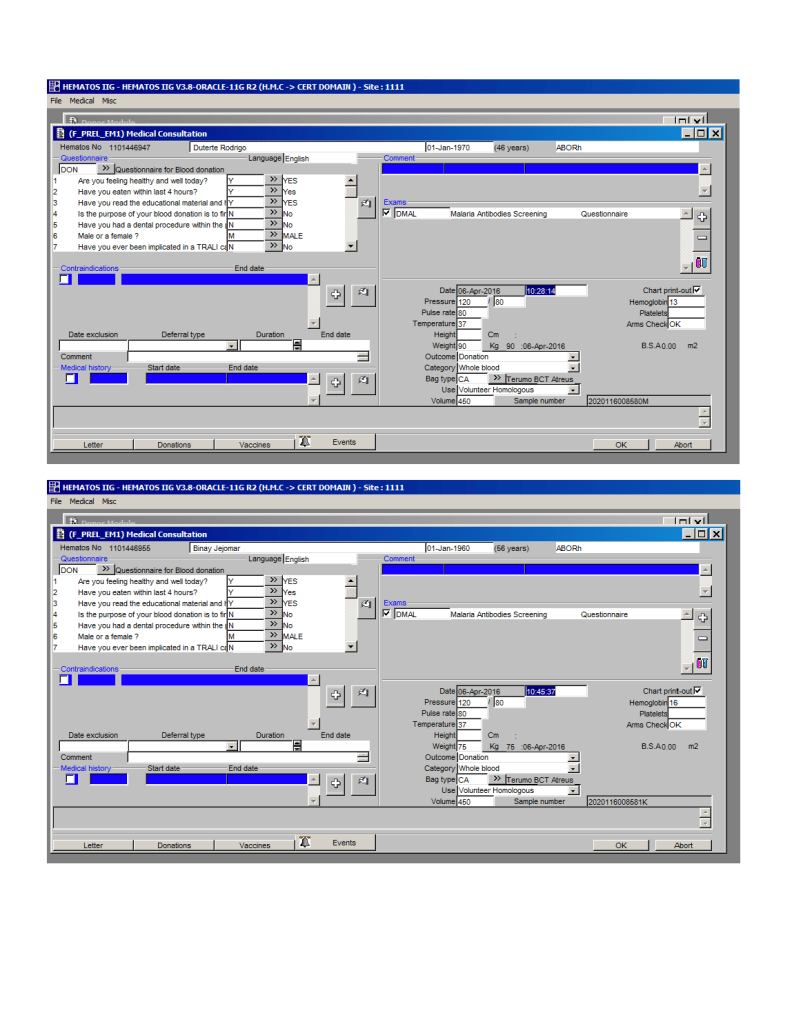
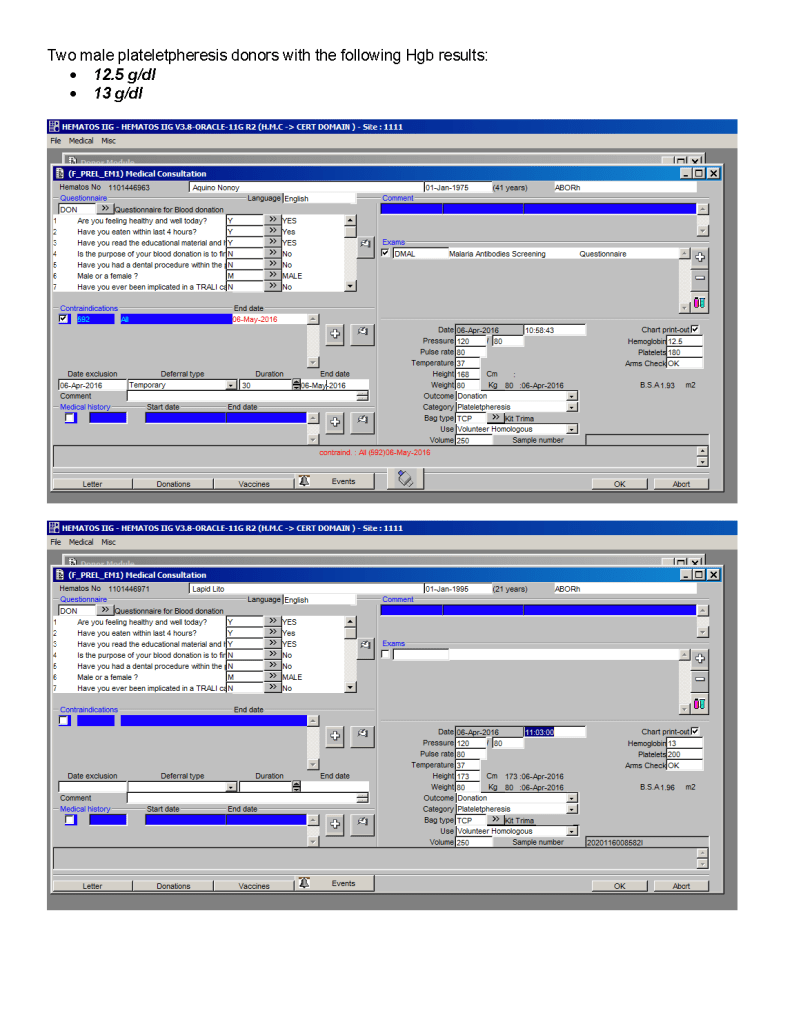
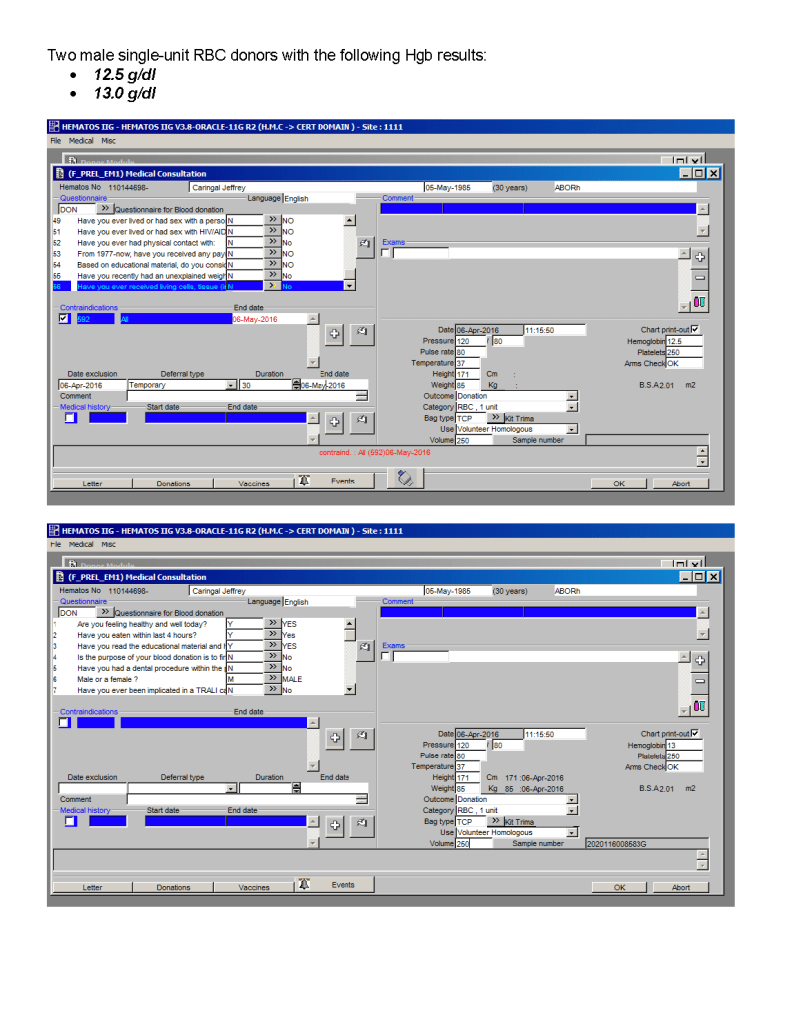
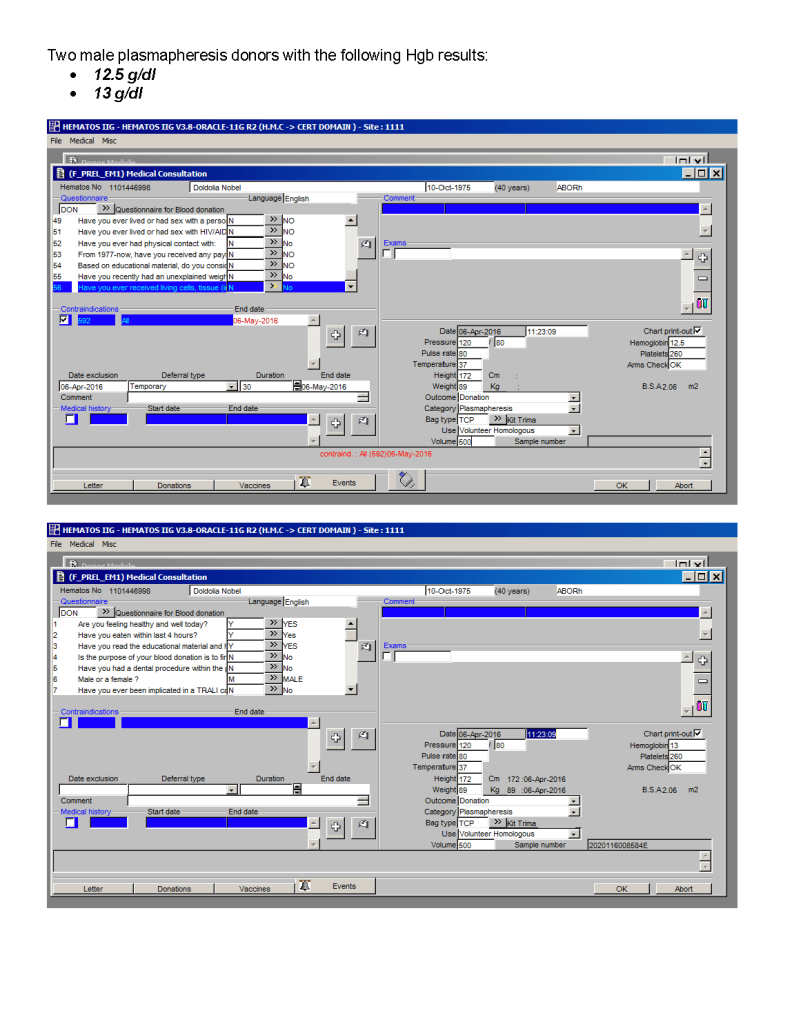
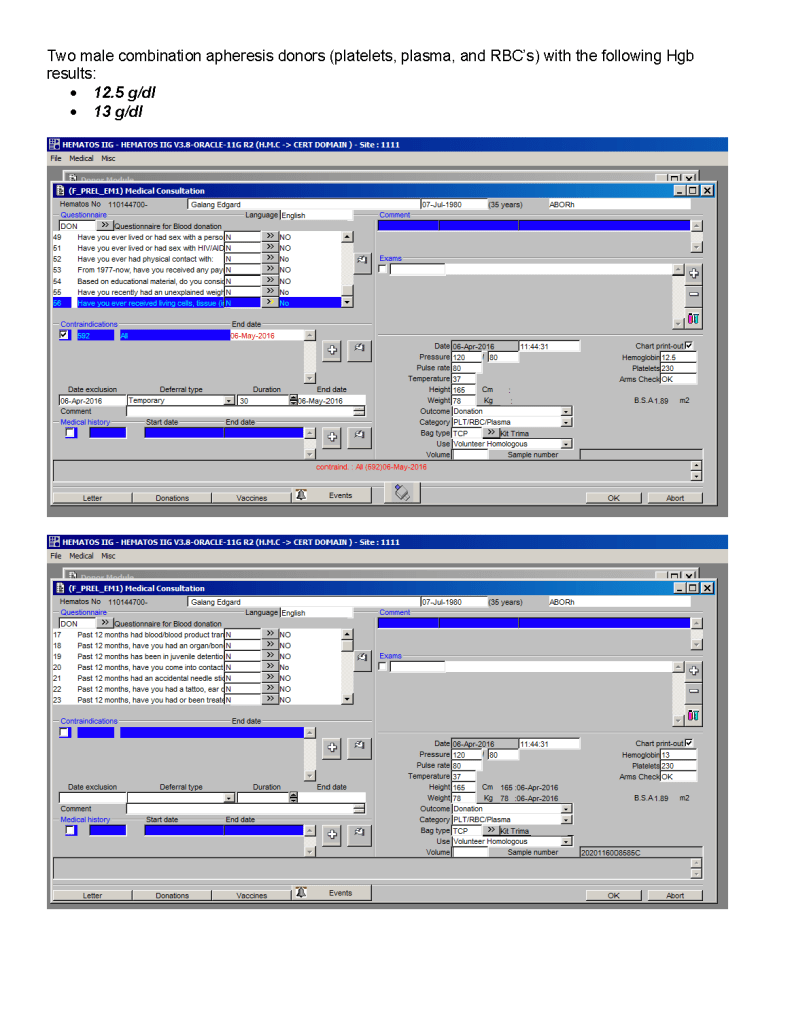
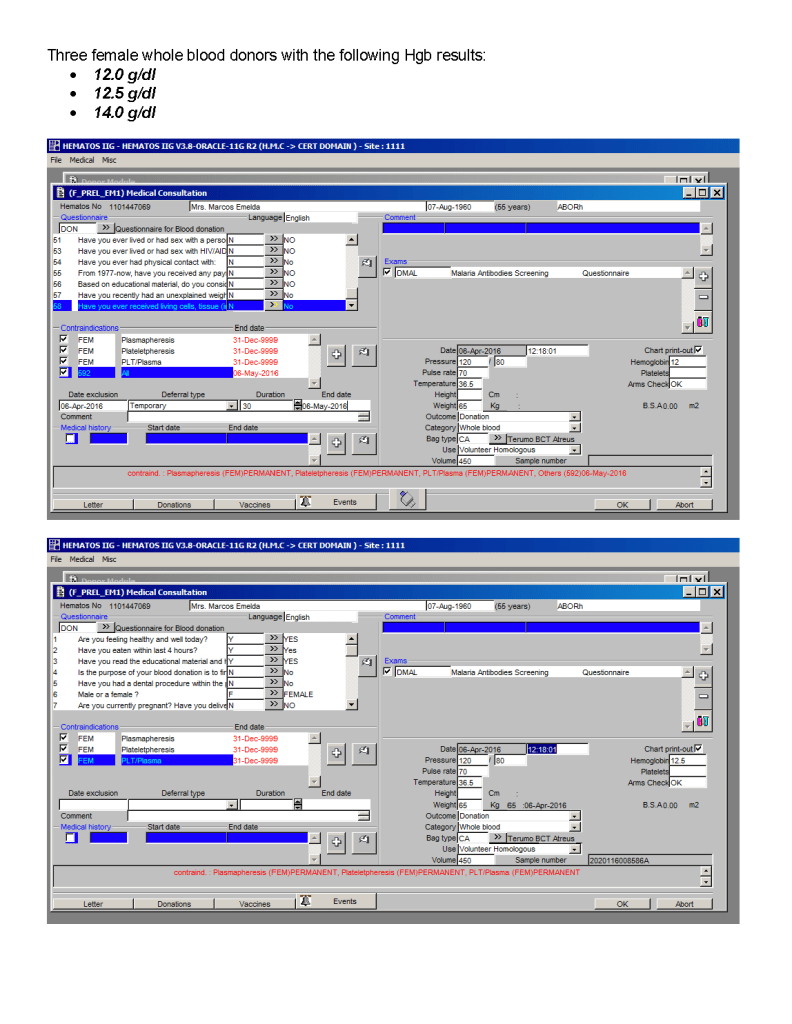
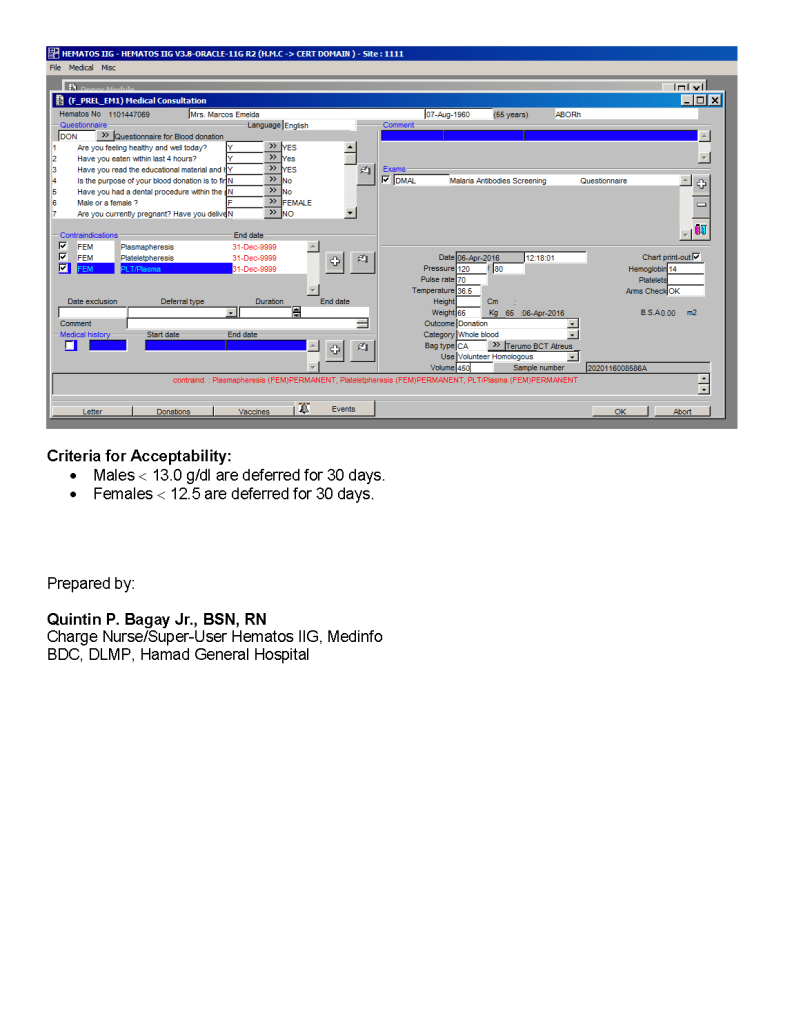
Changes to donor criteria can occur at any time.  This example is the change in donor criteria for males to 13.0 g/dl based on AABB Bulletin #16-05.

I made a validation protocol, which was subsequently performed by a Donor Center Medinfo Super-User.   The data was then sent to me for review and then accepted.

Note that females were included in the testing for regression purposes.Ā  Females were only permitted to donate RBCs—all other components were discarded in production. Contraindication information appears in RED.

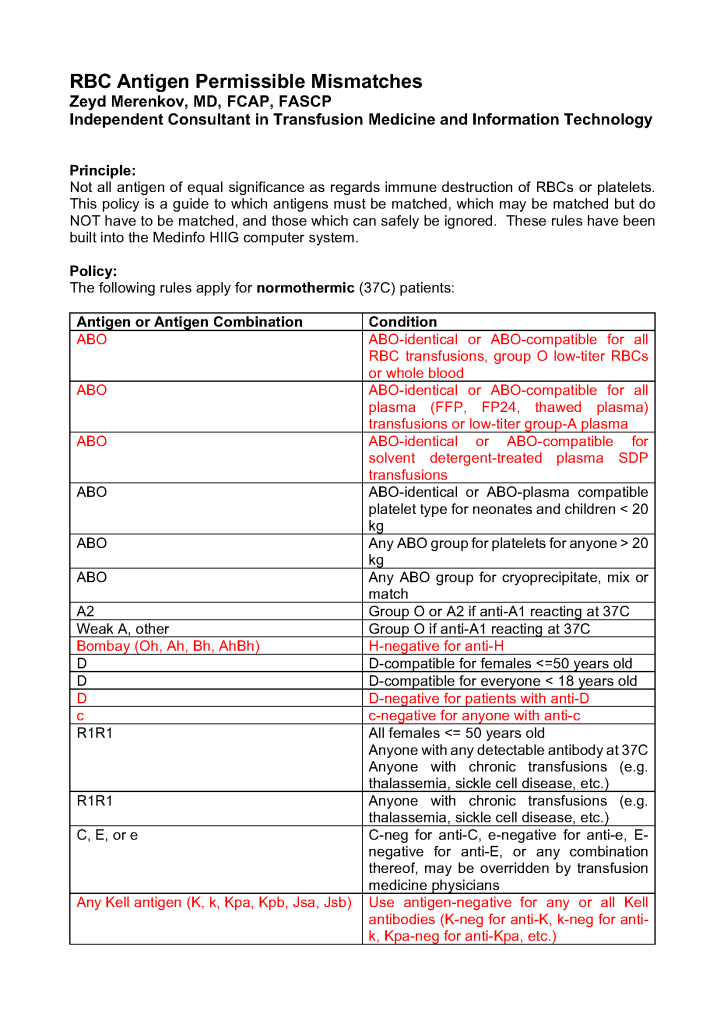
Permissible RBC Type Mismatching

The following was my interim policy at HMC for permissible matching and mismatching. This assumes that the patient is not being transfused while in a hypothermic state.

The prohibited options were blocked in the Medinfo Hematos IIG computer system. WAIHA least-incompatible release required physician approval. This protocol did not apply to low-titer group A or low-ABO-titer whole blood units, which were not available at the time.

Biologic Product Deviations

Principle:

Any nonconforming product that is released for patient use must be reported through the official channels.  Since there is no equivalent to the US CBER, this policy outlines the process for the HMC organization, the only provider of blood components for the State of  Qatar.

Definition:

Nonconforming Blood Component:  Any blood component not meeting the production criteria set in the policies, processes, or procedures of Transfusion Medicine.  Some examples include:

  • Low-volume RBC or FFP/FP24 units
  • Reduced yield platelet units
  • Units made with materials/supplies that have been recalled by the manufacturer
  • Units produced on equipment or tested with reagents that the manufacturer has recalled from use
  • Units contaminated during the production process

Policy:

  1. Nonconforming components must not be released unless they are reviewed and approved by the Head, Transfusion Medicine.
    1. Full written documentation of the review and the reasons for acceptance must be recorded.
    2. Such acceptance must be exceptional—there must be emergency reasons to resort to using such components.
      1. Minor nonconformances such as units with low volume or reduced platelet levels may be considered for use at times of critical shortage of blood components if they otherwise meet acceptability criteria.
  2. If anyone suspects there has been release of a nonconforming blood component, they should immediately contact the Division Head, Transfusion Medicine.
  3. The Division Head, Transfusion Medicine will conduct an immediate investigation to determine the veracity of the allegation.
  4. If the suspicion is confirmed, the Division Head, Transfusion Medicine will immediately contact the Chairperson, Pathology and Laboratory Medicine.
  5. The Chairperson in conjunction with Head, Transfusion Medicine, will inform the Medical Director and other senior administrative officials as indicated.
  6. A lookback will be initiated to determine if any patients have received the nonconforming components.
  7. The results of the lookback will be reported to the Chairperson, Pathology and Laboratory Medicine and the Medical Director.

References:

  1. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda MD, USA
  2. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

Body Fluid Exposures

Principle:

New rules have been approved by US FDA CBER for body fluid exposure, tattooing, body fluid exposure, and body-piercing.Ā  By similar logic we will extend this also to HIJAMA.Ā  We will not make any changes to our sexual history/practices or history of sexually transmitted disease treatment or clotting factor deferrals (except fibrinogen.)

Policy:

  1. Effective immediately, we will accept donors AFTER THREE MONTHS from the following activities:
    1. HIJAMA (ritual blood-letting)
    2. Tattooing
    3. Body piercing (e.g. piercing for ear-rings)
    4. Contact with blood of another individual through percutaneous inoculation such as a needle stick or through contact with a donor’s open wound or mucous membranes
  2. A TWELVE-MONTH DEFERRAL still applies after receiving a blood component or blood derivative except clotting factors (excluding fibrinogen concentrate.)
  3. Transfusion of clotting factors remains a permanent/indefinite deferral.

Reference:

Revised Recommendations for Reducing the Risk of Human Immunodeficiency Virus Transmission by Blood and Blood Products, Guidance for Industry,  U.S. Department of Health and Human Services, Food and Drug Administration, Center for Biologics Evaluation and Research, April 2020

Physician Review and Data Entry of Transfusion Reactions

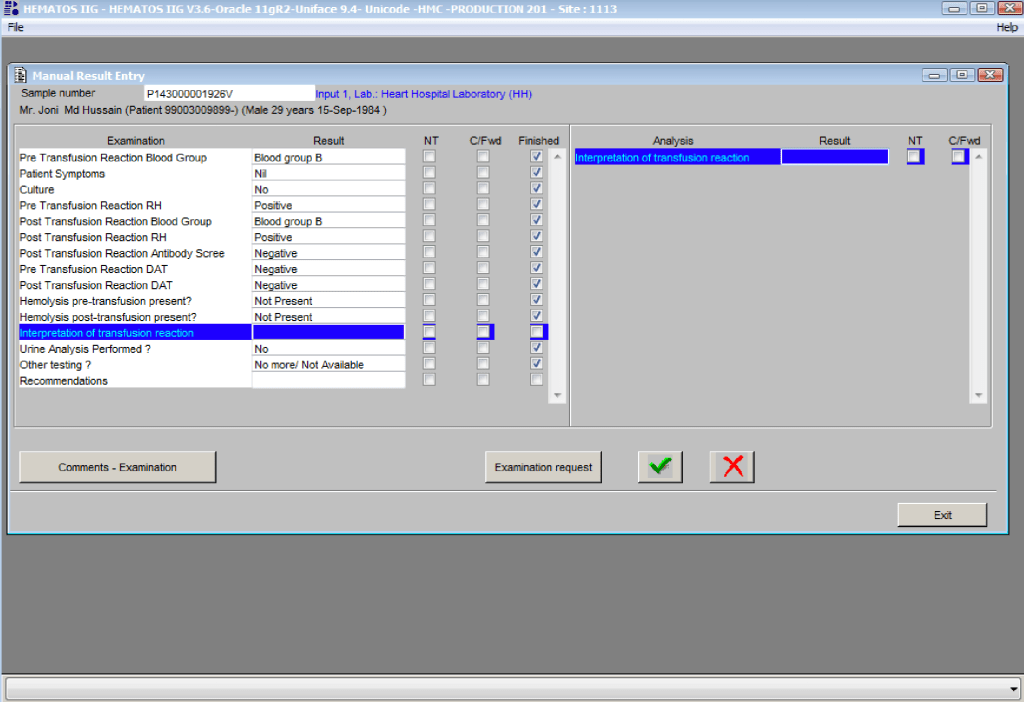
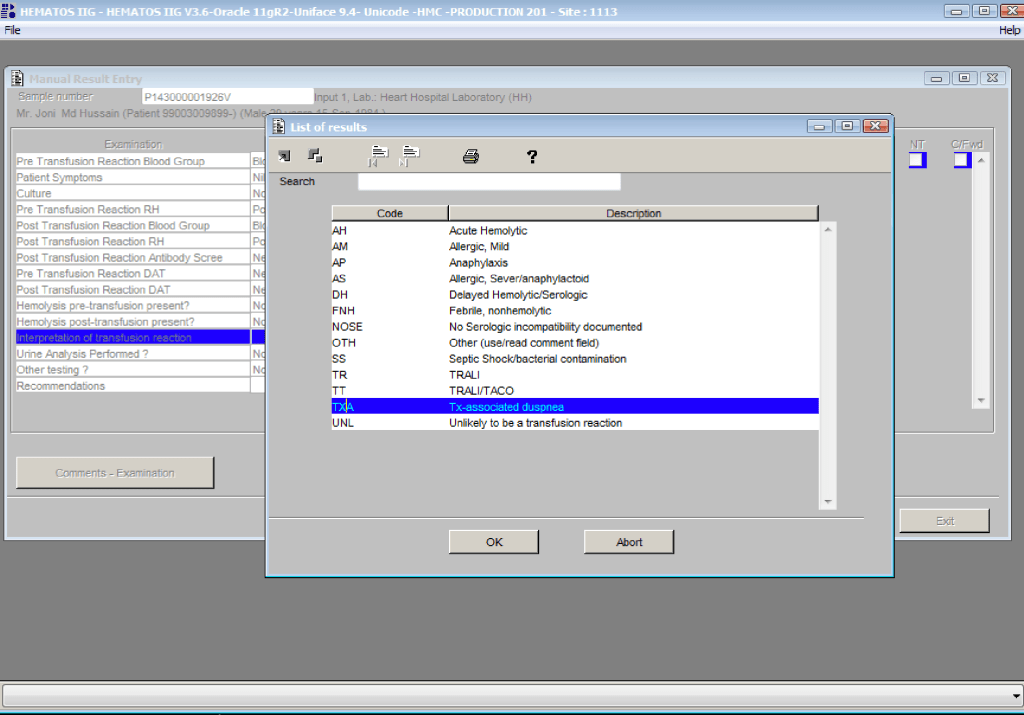
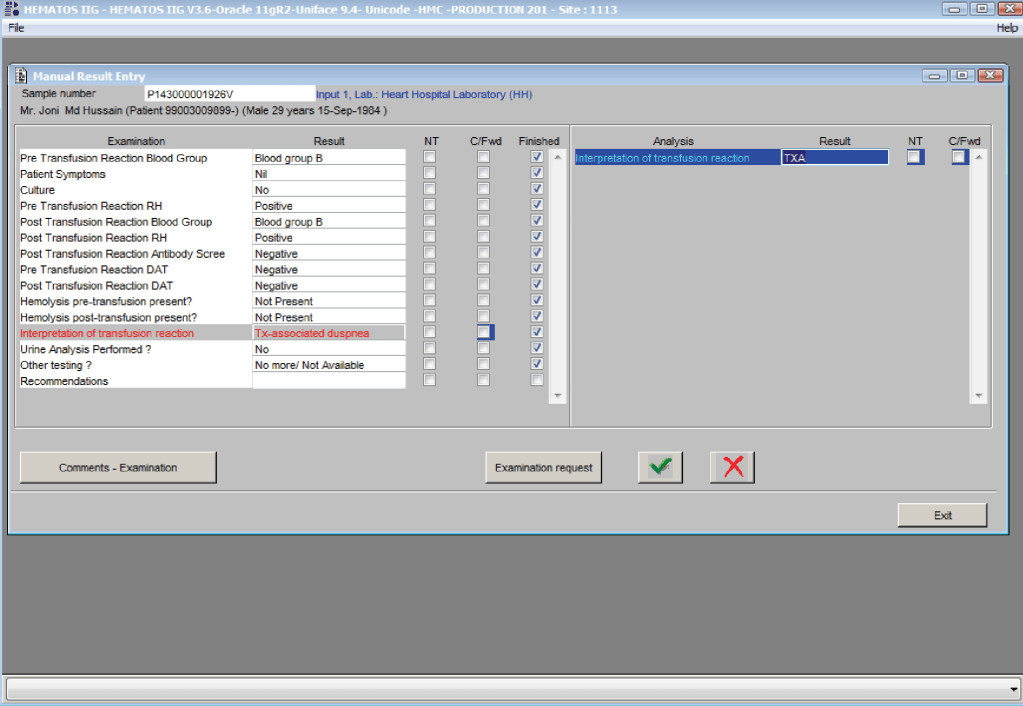
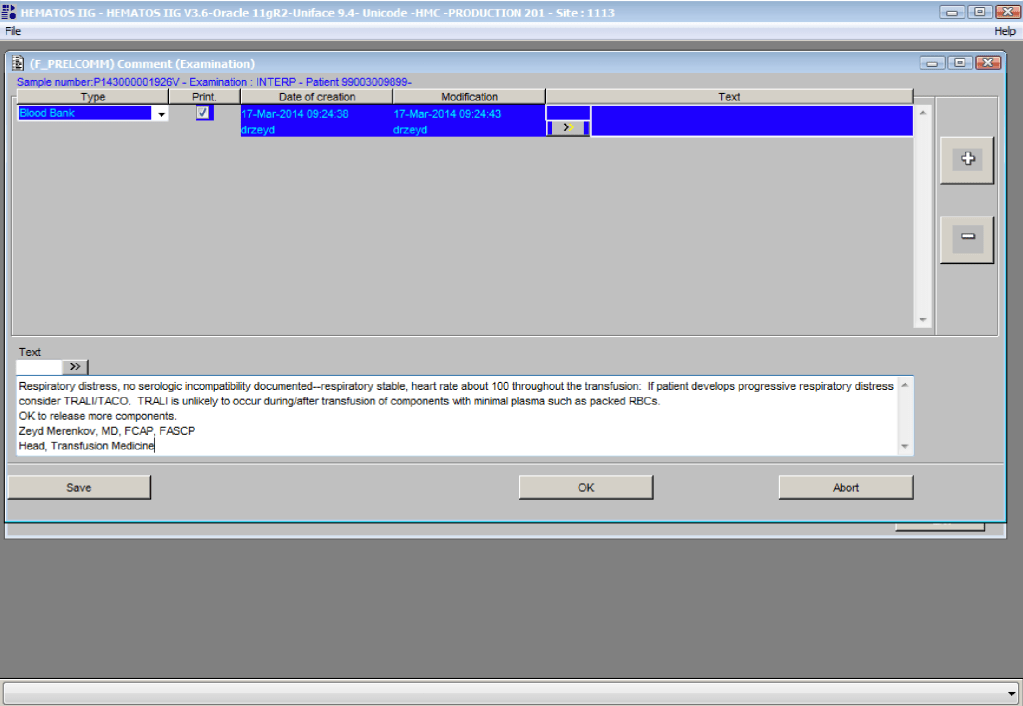
Physicians must enter their interpretations and recommendations for each transfusion reaction review.Ā  In addition, they may enter comments against any of the data.Ā  This post shows the process used in Medinfo Hematos IIG.

By highlighting Interpretation (left side), they then click on the Result Field (right side) and select their interpretation from the drop-down menu.  They can also select other and then enter a comment.

References:

  1. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  2. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition