Bacterial Risk Control Strategies for Platelets—USA

I am attaching the US Center for Biologics Evaluation and Research CBER Guidance for Industry revision dated December 2020 to replace the one issued in September 2019.

This is a very detailed document that will require US blood centers to comply with newer more stringent safeguards to minimize the risk of bacterial contamination of platelet components.

The easiest way to comply is to universally pathogen-inactivate all platelet components:  then the rest of the algorithm does not apply.  I am happy that for over 10 years I have used pathogen-inactivation (riboflavin-based Mirasol, Terumo BCT) and not experienced any bacterial sepsis from platelet or plasma components.

For those of us practicing outside the USA, please note:

The US still does not permit pooled, buffy coat platelets to have either a 5 or 7 day outdate.  For pooled components stored at 20-24 C, the FDA only allows a four-hour outdate, regardless what the rest of the world permits.  Thus, the USA mainly uses apheresis platelets.

If you have pathogen-inactivated platelets, you are so fortunate that you don’t have to follow these other recommendations to have a low risk of bacterial contamination.

Reference:

Bacterial Risk Control Strategies for Blood Collection Establishments and Transfusion Services to Enhance the Safety and Availability of Platelets for Transfusion, Guidance for Industry, U.S. Department of Health and Human Services, Food and Drug Administration, Center for Biologics Evaluation and Research, September 2019 updated December 2020

CBER Guidance for Bacterial Contamination Guidance, Revised December 2020 (PDF)
COVID-19 Convalescent Plasma CCP Series Introduction

I will be posting a detailed series about the manual and software-enhanced COVID-19 processes that I set up in Qatar at HMC Doha in March-April 2020.

In this series I will provide you with screen shots of my Medinfo Hematos IIG software design for each step in the process:  collection, processing, testing, inter-depot transfer, and hospital transfusion service/blood bank release.

This GMP-compliant software-enhanced system is based on the manual system I set up in early March 2020 at HMC.

I want to thank Medinfo Hematos IIG for their rapid response to building this parallel system based on my standard processes in so short a time (two weeks) and my special thanks to the software engineering team at Vital Health Technologies, the agent for Medinfo in Qatar.

To start the series, I am providing the basic workflow for the system.  As is normal in Medinfo software design, a full mapping of the processes are made.  This workflow shows the new CCP ISBT codes and the quarantine collection and processing steps.  The donor testing (marker and immunohematology) processes are similar to those for regular donor units.

This is basically the same process both manually and in the software.  I always say:

A good software process is based on a good manual process!!

Please note the following workflow for our initial discussion.

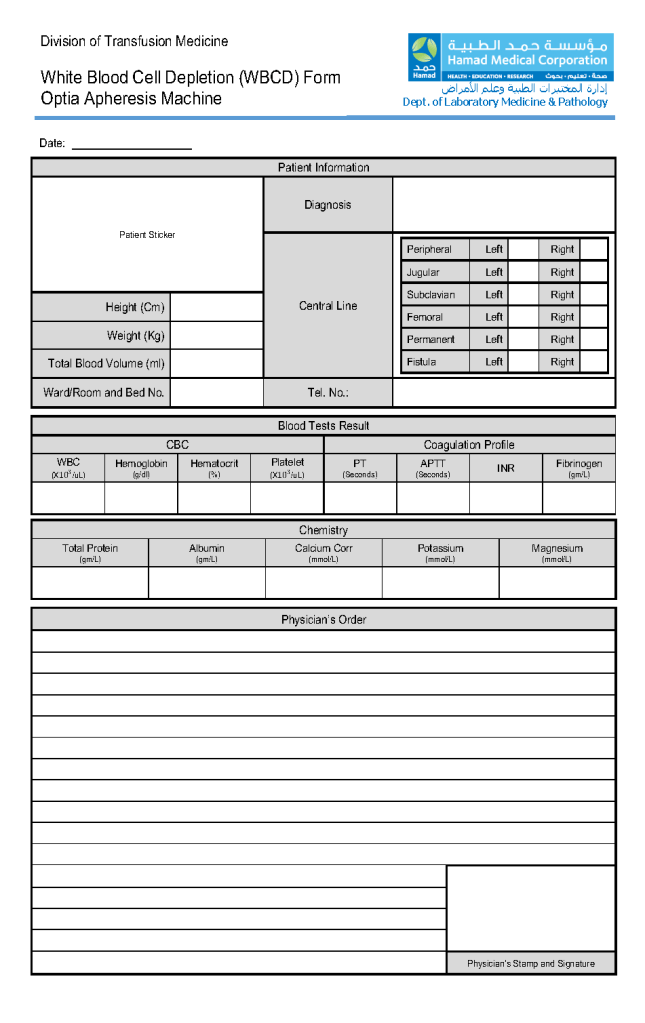
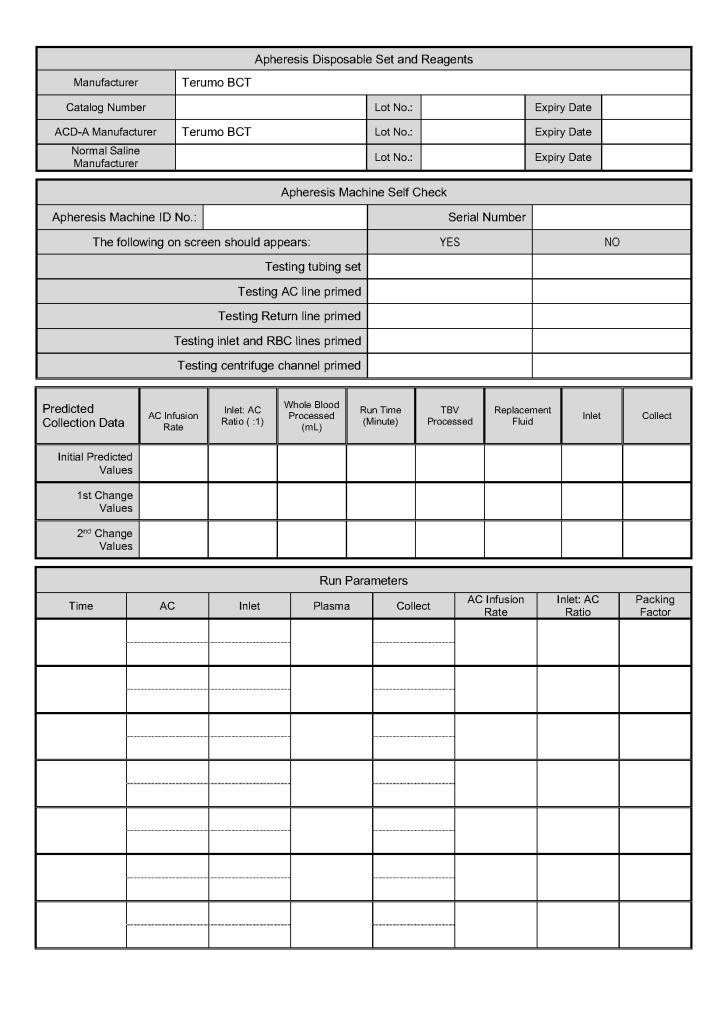
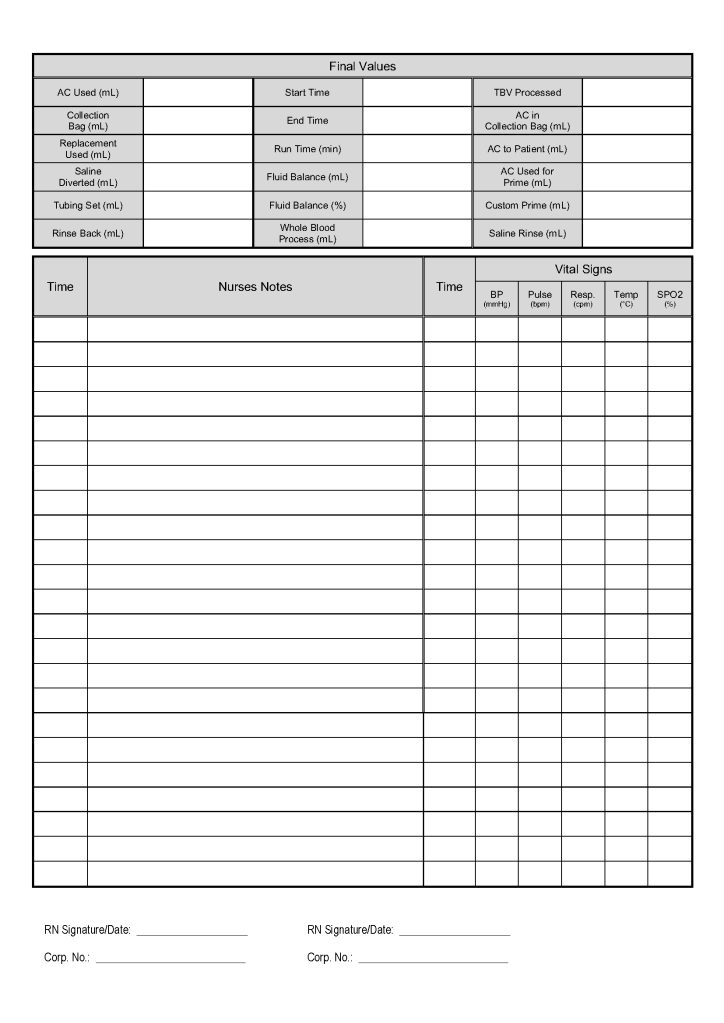
Leukodepletion Apheresis Form

This form is the result of a collaborative effort between my therapeutic apheresis team and me. I want to thank Dr. Saloua Al Hmissi, Consultant, Transfusion Medicine, and Ms. Mini Paul, Head Apheresis Nurse for all their efforts.

This form can be readily converted into a computer data entry form–depending on your software’s capabilities.

Use of Universal Low-Titer Group A Plasma

Principle:

Since group AB plasma is in short supply, use of group A plasma with low anti-B titers may be substituted based on inventory levels.

Policy:

  1. If the AB inventory is low, we will test group A donors at the time of collection for anti-B titers.
    1. The numbers to be tested will depend on the level of the shortage and the availability of equipment to perform titration.
  2. Use the automated analyzer to perform saline anti-B.
    1. If the saline titer is less than or equal to 1:64, the plasma may be used for recipients of any ABO blood group and will be labelled as group AU—A Universal.
  3. Process the unit routinely and perform pathogen-inactivation.
  4. Medinfo Hematos IIG will only label for universal use if the titer is below the cutoff.
    1. The ISBT label must explicitly show group AU plasma and the actual anti-B titer.
  5. Allocation rules for low-titer group A plasma will be identical to group AB except:
    1. For neonates, preferentially use group AB.
    2. For children < 20 kg, use ABO-compatible plasma (non-group AB) before selecting group AB or if not available, low-titer A in that order.
  6. Donors must have a new anti-B titer performed each donor encounter.

References:

  1. Technical Manual, Current Edition, Bethesda, MD, USA
  2. Standards for Blood Banks and Transfusion Services Current Edition, AABB, Bethesda, MD, USA

Framework for Establishing the Use of Universal Low-Titer Group A Plasma

This post outlines a framework for establishing the use of low-titer group A plasma as a universal donor.  Manual titering large number of donor specimens in my organization is not practical.  Using an automated system will also increase the precision of the results.

Process:

  1. Select a cut-off anti-B titer.  This should be determined by the blood bank medical director.
    1. I selected saline 1:64 based on recent THOR (Thrombosis Hemostasis Oxygenation Research) meetings
  2. Perform a survey of the anti-B titers in your blood donor population.
    1. At my sites, about 50% had titers less than or equal to 1:64.
    2. Determine how stable the titer is:
      1. For serial donor plasmapheresis, how long could you accept the donor as low-titer?
      2. Does the titer change between whole blood donations?
  3. Determine the target inventory level for universal plasma (group AB and low-titer A) based on current/past usage.
  4. Assess availability of automated immunohematology analyzers for titration.
    1. Titration may take up to 30 minutes per sample, during which time the machine cannot be used for any other purpose.
  5. Add a new blood type AU (for group A universal) for plasma in your blood typing algorithm.
    1. AU should be used interchangeably with group AB.
  6. Software:
    1. Set up new truth table in your blood bank computer system.
    2. Validate the modification in your blood bank donor and patient modules.
    3. Update ISBT code for this new product, verify your transfusion service module can read this.

Special notes:

  1. At my last location, we had only 3 analyzers capable of doing the titration.  Thus, we could only do 6 titrations per hour at the expense of stopping all other testing.  You will have to coordinate the titration with your other immunohematology testing.  Also, verify if all these equipment interface to your production software.  In my system, any test (including titration) could be performed at any location and its results be used for production purposes.
  2. Donor ABO antibody titers may fluctuate.  I would not use previous results to qualify a donor to be AU.  I would repeat the anti-B titer each donor encounter.  If I collect donor plasmapheresis, I would determine for how long the titer can be used (see 2.2.1 above).

References:

  1. Technical Manual, Current Edition, Bethesda, MD, USA
  2. Standards for Blood Banks and Transfusion Services Current Edition, AABB, Bethesda, MD, USA
  3. Medinfo Hematos IIG Donor Production Module

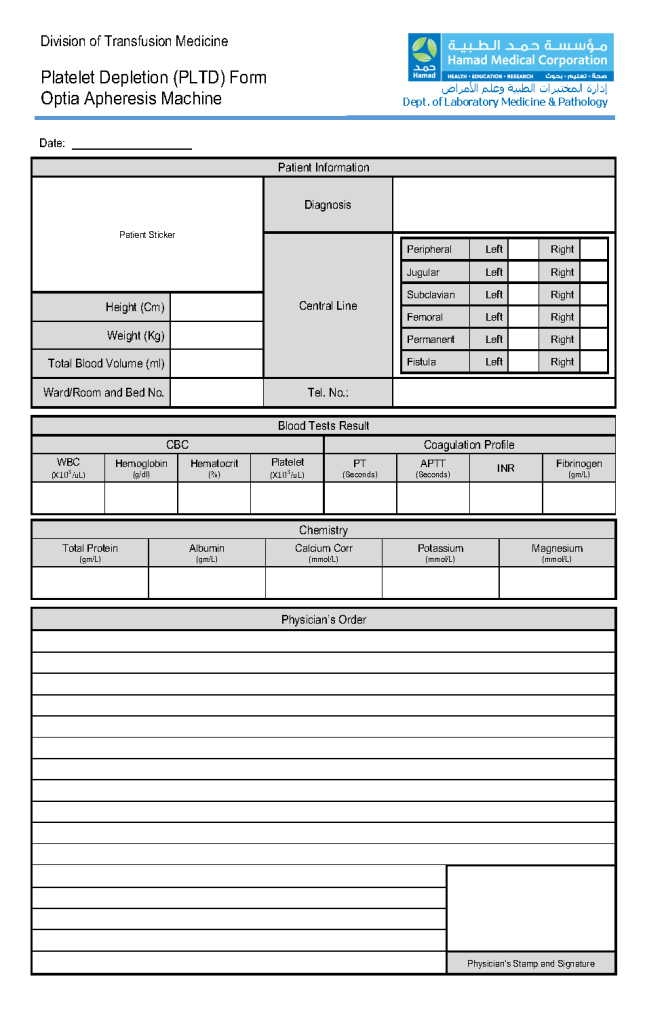
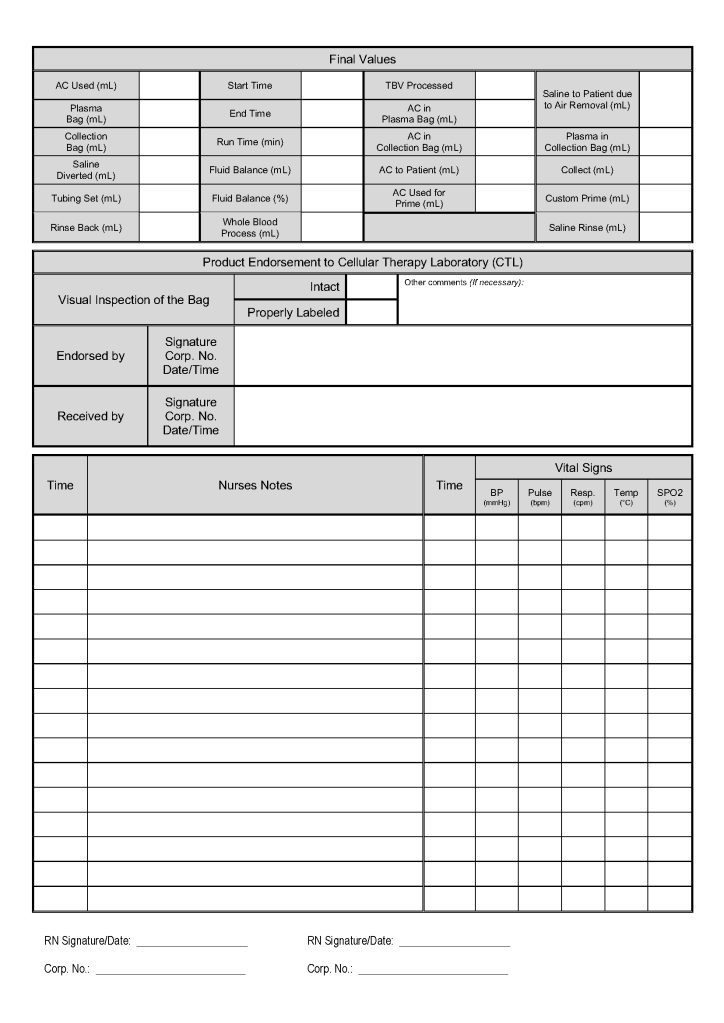
Platelet Depletion Apheresis Form

This is the apheresis form used for reductive thrombapheresis developed by my apheresis team and me. In particular, I want to thank Dr. Saloua Al Hmissi, Consultant Transfusion Medicine, and Ms. Mini Paul, Head Apheresis Nurse, all their hard work.

The attached form can be developed into a computer entry form if one has a suitable hospital information system. It is organized so that the apheresis nurse can quickly enter the data on one screen. Never forget that our goal is treat the patient–not spend all of our time on data entry!!

20/12/20

Data Entry Verification: Updated Version

This is an update from the previous version posted to include low-titer group A FFP/FP24 and low ABO-titer group O whole blood.

Principle:

This policy outlines steps taken to minimize the risk of data entry errors and is based on a dualistic approach:  review of results by a senior technologist and/or supervisor and various computer safeguards built into the Medinfo Hematos IIG blood bank computer HIIG system.  This policy also discusses the verification (here called authorization) and purge processes of HIIG.

Policy:

  1. Review by senior technical, supervisory, or transfusion medical staff:
    1. Designated test procedures require review by a second technologist before authorization.
    2. Complex immunohematology testing and specimens showing aberrant results (e.g. ABO/D discrepancies) are reviewed by the supervisors or designates and ultimately a transfusion medicine physician before authorization.
  2. Computer system HIIG rules:
    1. Privileges:
      1. System restricts which staff can perform specific tests
    2. Patient/donor identity:
      1. System asks end-users to verify patient/donor identity before starting any access to the patient/donor record.
      2. System performs historical database checking and flags any inconsistencies (e.g. historical ABO/D typing differences, etc.)
    3. Testing:
      1. Only selected staff have privileges to authorize or purge.
      2. ABO/D testing algorithms require entry of reactions, not interpretation of results and are compared to a truth table.
        1. Aberrant results require special review before ABO/D typing results can be authorized/purged.
        2. D-controls must be negative to allow D typing results to be authorized for liquid D-typing reagents.
      3. DAT results require appropriate controls to meet truth-table criteria.
      4. Eluates require last wash to be negative before authorization
    4. Blood components:
      1. Selection of RBC or plasma units requires two independent sample determinations within 72 hours of each other.
      2. ABO-incompatible RBC or FFP/FP24 transfusions are not allowed.
      3. Titer-based ABO blood group selection:
        1. Low titer group A FFP may be used as universal plasma like group AB.
        2. Group O whole blood with low anti-A and anti-B titers may be used for all ABO types.
        3. Acceptable titer threshold is specifically defined as parameters in Medinfo.
      4. Donors with any detectable clinically significant antibodies are permanently deferred.
      5. Depending on the patient’s antibody history, release of RBC units may require antigen-matched units.  Examples:
        1. Mandatory matching (only antigen negative matched units allowed—no antigen positive or antigen-untyped units):  Antibodies against H, D, c, K, k, Kpa, Kpb, Jsa, Jsb, Jka, Jkb antigens, anti-PP1Pk
        2. Priority matching (incompatible or untested can be approved by a transfusion medicine physician):  C,E, e, Fya, Fyb, M, S, s
        3. Antigen matching not required:  Lea, Leb, N
      6. Least-incompatible crossmatch require special authorization to release
      7. Protocols to force irradiation or other modified components can be setup in HIIG.
    5. Donors:
      1. Donor tests have same criteria as the same test used in patient testing for controls, etc.
      2. Donor demographics are read directly from the Ministry of Interior database—no manual entry (bar code only used).

References:

  1. Workflows for Hematos IIG (1001 through 1005), 2013-2020
  2. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  3. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

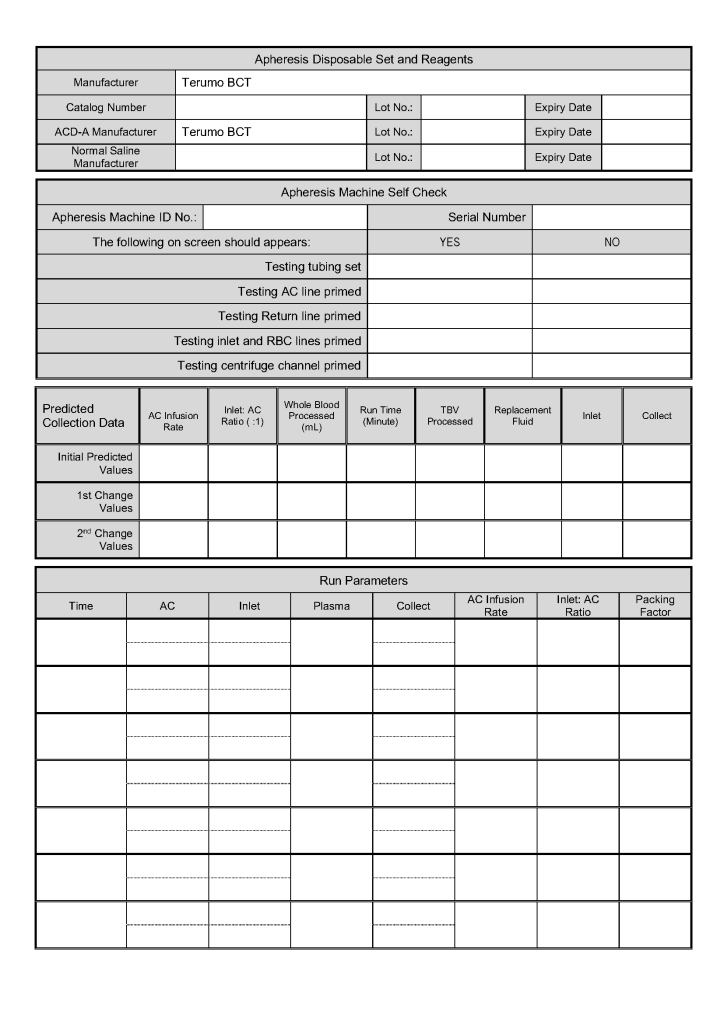
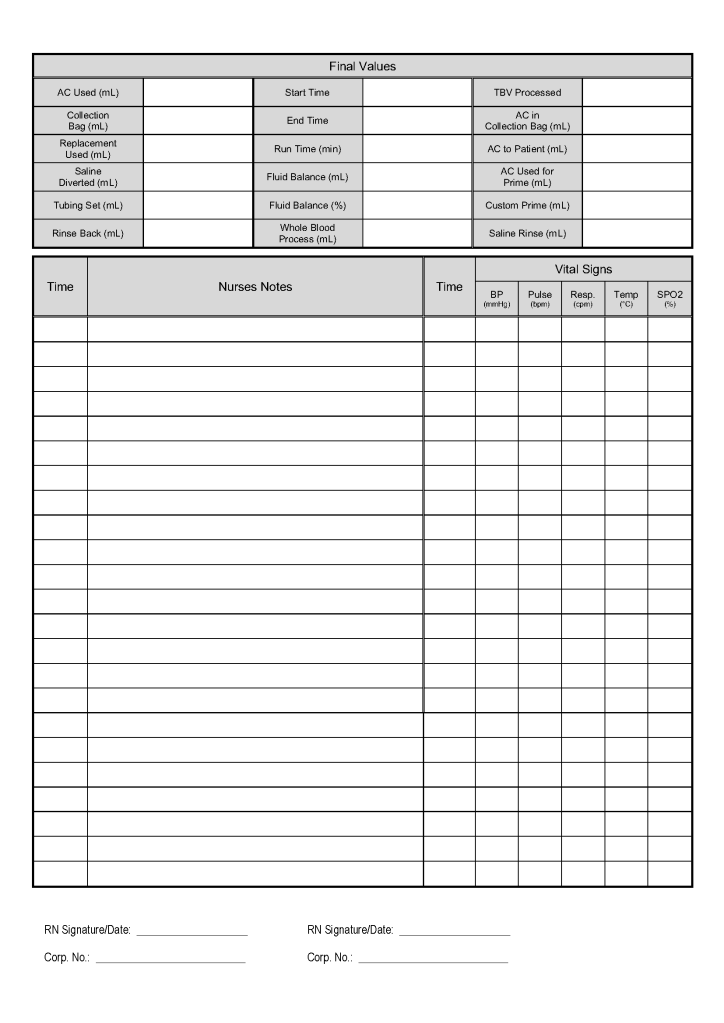
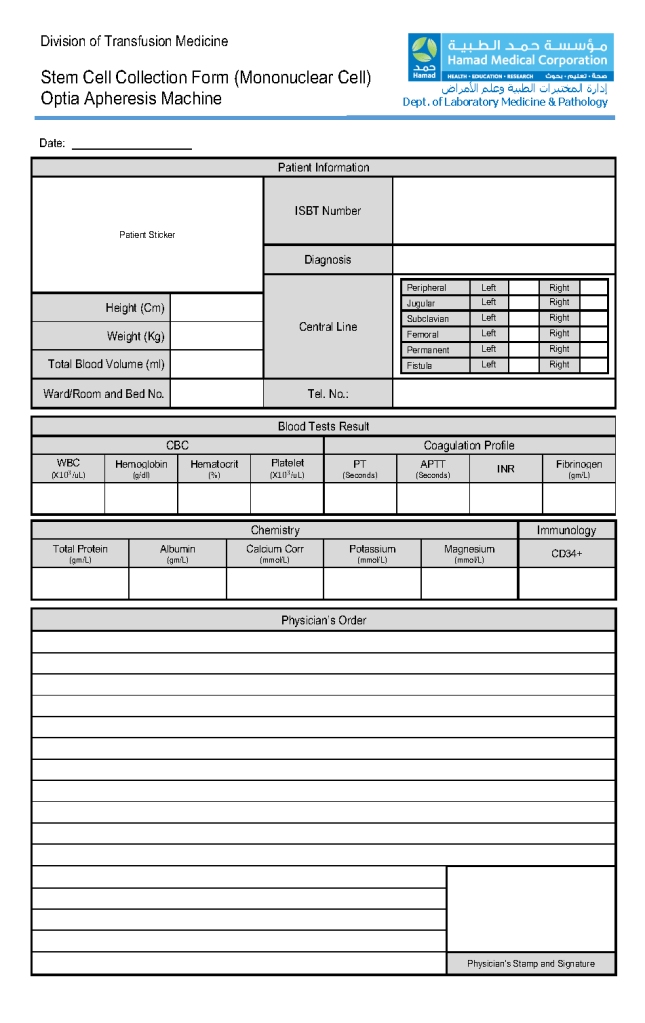
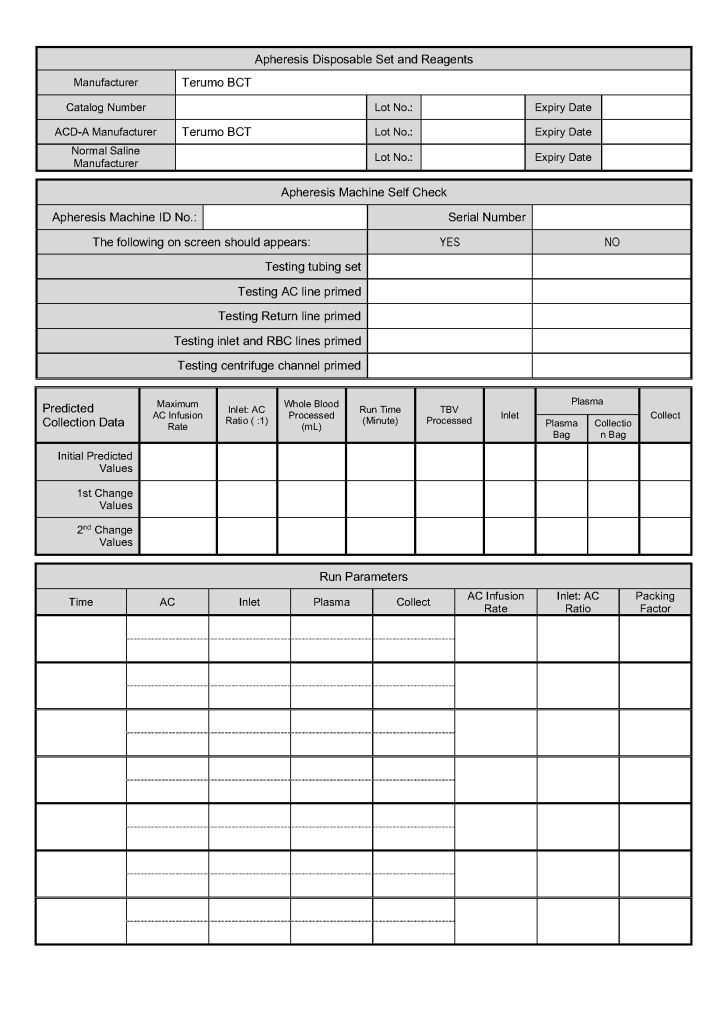
Sample Stem Cell Collection Apheresis Form

This is a sample of the stem cell therapeutic apheresis form that my apheresis team and I developed. It can be readily made into an electronic form. I want to thank Dr. Saloua Al Hmissi, Apheresis Consultant, and Ms. Mini Paul, Head Apheresis Nurse, for their efforts in making this form a success.

Preventing Graft vs. Host Hemolytic Anemia

Principle:

Donor lymphocytes in an organ transplant may make antibodies and cause a clinically significant hemolytic anemia, i.e. a graft vs. host hemolytic anemia GVHHA.  Optimal handling in these cases should include antibody screening/identification for all potential donors and recipients.  The transfusion medicine physician should review the results for possible issues of antibody/antigen incompatibilities to proactively select matched blood components and avoid GVHHA.

In the Medinfo blood bank computer system, we can make custom rules to ensure release of only antigen-matched units as needed.

Policy:

  1. Perform antibody screen and identification (if indicated) for all prospective organ donors and recipients.
  2. If the organ donor has clinically significant antibodies, check if the recipient has the corresponding antigens.  If so, select RBC units negative for the donor antibody specificities. 

Example:  Donor has anti-Kell (K1) and patient is K1-positive.  Use only K1-negative RBCs post-transplant.

  • Send the case to the transfusion medicine physician to review.  He will contact the clinicians as indicated.
  • Create a rule in Medinfo forcing the antigen matching.

References:

  1. Technical Manual, Current Edition, Bethesda, MD, USA
  2. Standards for Blood Banks and Transfusion Services Current Edition, AABB, Bethesda, MD, USA

Patient D-Typing Algorithm Using Ortho Monoclonal Cocktail Reagents

Principle:

We must select D-negative RBC units for transfusion if the patient is truly D-negative or if he/she is a partial D since transfusion of a partial D positive unit may induce antibodies against any part of the D molecule.  Thus, for patients, we will consider patients with partial D as D-negative.  Note that this is NOT the usual practice in the USA;  however, AABB Standards do allow that we do NOT test patients for weak D and give D-negative RBCs instead.

Background:

Ortho Diagnostics Reagents use two different monoclonal antibody cocktails that react variably with the antigen D (Rh1)—these are found on the card:  Anti-A/B/A,B/D/D/Ctrl:

Anti-D/Anti-RH1—IgM monoclonal antibody clone D7B8 can detect most examples of weak and partial D including weak D types 1, 2, 3, 4.0, and D categories II, III, IV, V, VII, DBT, and R0Har.  It does NOT detect category VI.  Retest positive reactions of 2+ or less by an alternate method.

Anti-D/Anti-RH1—IgM monoclonal antibody RUM1 can detect most examples of weak and partial D including weak D types 1, 2, 3, 4.0, and D categories II, III, IV, V, VII, DBT, and R0Har.  It does NOT detect category VI.  Retest positive reactions of 2+ or less by an alternate method.

Policy:

  1. Follow the manufacturer’s instruction for storage, handling, and usage of all reagents.
  2. If the D-control is positive, the reactions are indeterminate, repeat by another method.
  3. Run both anti-D reagents listed—do not use the donor typing algorithm or reagents.
  4. Use the following table for interpretation and further actions if needed:
Pattern #Anti-D/D7B8Anti-D RUM1D-Interpretation
1PositivePositiveD-positive
2PositiveNegativeDo additional testing
3NegativePositiveDo additional testing
4NegativeNegativeD-negative  

If the reaction is 2+ or less with either the Ortho anti-D/D7B8 reagent or anti-D/RUM1 or if the patterns 2 or 3 above, repeat by another manufacturer’s reagents.  In the meantime, consider the patient as D-negative.

Medinfo-Ortho interface settings for Patient Testing:

Anti-D/D7B8Anti-D RUM1D-Interpretation
3, 43, 4D-positive
3, 40~
03, 4~
00D-negative
~~~

Note all of the following:

  1. If the result is D-indeterminate, use D-negative RBCs.
  2. No reagents may be able to detect all D variants.
  3. ~ means any other value for that reagent (1+, 2+, mf, hemolyzed)
  4. Note that this new algorithm makes a 2+ reactivity as indeterminate with Anti-D/D7B8 or Anti-D/RUM1.

References:

  1. Publication e631300291, Product Insert, Anti-A/B/A,B/D/CDE/Control Card, 2010, Ortho Clinical Diagnostics, High Wycombe, Buckinghamshire/UK
  2. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA