Weak D Phenotype

I prepared this policy for HMC Qatar, which did not perform genotyping.

Principle:

Weakened expression of the D antigen may be due to either quantitative or qualitative defects.  Qualitative defects (partial or mosaic D) are uncommon.

Patients with quantitative defects have the whole D molecule and will not make anti-D upon exposure to D-positive RBCs.

Patients with partial or mosaic D may form antibodies against the portion of the D molecule they lack.  However, not all partial D types may make anti-D upon exposure.  Since we cannot specifically test for this condition, we shall consider females of child-bearing age with weak D as potentially partial D and use D-negative RBCs.

Genotyping for the D gene may define better which partial D types need to receive RhIG or D-negative transfusions.

Definition:

Weak D is defined as weak (1+ or weaker) reactions with one or more routine reagents or reactions only at antiglobulin phase (i.e. Du testing).

Policy:

  1. All donor units must be tested by a method to detect weak D phenotype.  If such testing is positive, the donor unit must be labelled as D-positive and be used routinely for D-positive patients.
  2. Weak-D females of child-bearing ages (<50) should receive D-negative RBCs.
  3. Weak-D males may receive D-positive RBCs unless they are a potential recipient of chronic transfusions (e.g. thalassemia, sickle cell disease, etc.)

References:

Technical Manual, Current Edition, American Association of Blood Banks, Bethesda, Maryland, USA

Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA

Universal Low-Titer Group O Whole Blood

Principle:

Fresh group O whole blood has viable platelets, plasma, and RBCs.  Fresh whole blood may provide better resuscitation than individual components.  It can replace MTP component therapy of separate RBCs, plasma, and platelets.  We will use low ABO-titer whole blood units (here called O universal OU) in selected trauma cases, based on availability.

Testing for low-titer (both low-titer anti-A and anti-B) units is time-consuming and monopolizes the automated immunohematology analyzers.  This is the rate-limiting step.

Policy:

  1. Stock a limited number of OU whole bloods at the trauma/emergency room sites—based on inventory needs.
  2. Allow up to 2 doses (2 OU units/patient) before reverting to the MTP protocol.
  3. Prepare allocation rules to allow group OU whole blood and group O RBCs to be used for ALL ABO types except Oh, Ah, Bh.
  4. Medinfo Hematos IIG will use the new allocation rules for OU in emergency release situations only.  It will not be allowed for routine use.

References:

  1. Technical Manual, Current Edition, Bethesda, MD, USA
  2. Standards for Blood Banks and Transfusion Services Current Edition, AABB, Bethesda, MD, USA

Setting Up Universal Low-Titer Group O Whole Blood

This post outlines a framework for establishing the use of universal group O whole blood.  Manual titering large number of donor specimens in my organization is not precise.  Using an automated system will also increase the precision of the results.  The rate-limiting step is the ability to do the anti-A and anti-B titers.

Process:

  1. Select cut-offs for anti-A anti-B titer.  This should be determined by the blood bank medical director.
    1. I recommend saline 1:64 for both titers based on recent THOR (Thrombosis Hemostasis Oxygenation Research) meetings
  2. Assess availability of automated immunohematology analyzers for titration.
    1. Titration may take up to 30 minutes per sample, during which time the machine cannot be used for any other purpose.
  3. Perform a survey of the anti-A and anti-B titers in your blood donor population.
    1. At my sites, about 50% had titers less than or equal to 1:64.
    2. Determine how stable the titer is:
      1. Does the titer change between whole blood donations?
  4. Prepare as follows:
    1. Collect whole blood units in CPD.
    2. Filter with a platelet-sparing whole blood leukodepletion filter.
  5. Add a new blood type OU (for group O whole blood universal) for plasma in your blood typing algorithm.
  6. Establish new allocation rules to permit group OU whole blood for all ABO types.
  7. Software:
    1. Set up new truth table in your blood bank computer system.
    2. Validate the modification in your blood bank donor and patient modules.
    3. Update ISBT code for this new product, verify your transfusion service module can read this.
  8. Determine the target inventory level for universal plasma (group AB and low-titer A) based on current/past usage.
    1. I started with a trial of a small inventory of 8 units to cover 4 patients each receiving a maximum of 2 units at one trauma site.
    2. Consider a dose of two as equivalent to an MTP dose in an adult.
    3. If more than 2 units  are needed, revert to the MTP protocol.

Special notes:

  1. At my last location, we had only 3 analyzers capable of doing the titration.  Thus, we could only do 6 titrations per hour at the expense of stopping all other testing.  You will have to coordinate the titration with your other immunohematology testing.  Also, you must verify if all these equipment can interface to your production software.  In my system, any test (including titration) could be performed at any location and its results be used for production purposes.
  2. Donor ABO antibody titers may fluctuate.  I would not use previous results to qualify a donor to be OU.  I would repeat the anti-A and anti-B titer each donor encounter.

References:

  1. Technical Manual, Current Edition, Bethesda, MD, USA
  2. Standards for Blood Banks and Transfusion Services Current Edition, AABB, Bethesda, MD, USA

  3. Medinfo Hematos IIG Donor Production Module

Teaching Document: Validation Process

This is a teaching document for medical technology and transfusion fellows to explain the general structure of a validation.

Principle:

All validations must be planned.  A validation protocol must be prepared with specific criteria for acceptance.  All validations with attached evidence must approved by the Head, Transfusion Medicine.

Policy:

  1. A written validation protocol must be prepared in the advance and at least including the following:
    1. Specific parameters and number of iterations to be performed
    1. Designated staff to perform validation
    1. Documentary evidence of the testing
    1. Specific acceptability criteria
  2. The completed validation protocol must be submitted to the Division Head, Transfusion Medicine, or designee for review.
  3. Once the validation plan has been reviewed, it must be performed by the designated staff.
    1. Software validations will be performed in a specific test environment, not in the live, production system.
  4. The completed validation document, including screenshots of the software functionality if applicable, must be submitted to the Division Head, Transfusion Medicine for review.
  5. The equipment or software may only be used if the acceptability are met AND the validation is approved by the Division Head, Transfusion Medicine or designee.
  6. The completed validation protocol will be stored in the document control system.

Reference:

Standards for Blood Banks and Transfusion Services, Current Edition, Bethesda, MD, USA

Blood Component Variances

Principle:

AABB Standards requires that all variances are documented and investigated and corrective actions taken when necessary.  Any time a blood component is found to be defective (e.g. broken seal, leaking, discoloration, clots, etc.), mislabeled, or testing results incomplete or not documented,  the cause should be investigated by the Donor Center and reported back to the initiator of the report in writing.

Policy:

  1. All transfusion services must inspect all blood components upon receipt (e.g. for leakage, broken seals, improper temperature, clots, discoloration, gas, etc.).
  2. Labels must be compared to the consignment sheet for complete concordance.
  3. If units are found that are not listed or mislabeled, they must be reported in writing to the Donor Center and returned as-is for investigations.
    1. If the unit is leaking or broken, ensure standard/universal precautions are taking to minimize contact with the fluids.
    2. Damaged blood components must not be used.  Units with mislabelings or other discrepancies between the labels and the consignment sheets may be used when such errors are corrected and officially reported by the Donor Center.
  4. Use the standard incident (occurrence variance) report form (OVA) for each and every variance.
  5. The submitting location should keep a copy of the OVA and immediately forward the original to the Transfusion Quality Section.
  6. The Donor Center should investigate the variance and prepare a written investigative report and submit to the Division Head, Transfusion Medicine.
    1. Donor Center investigations should be completed within one calendar week.
  7. The Donor Center should forward a copy of the completed written investigation to the transfusion service which initiated the investigation.
  8. The copy of the investigation report should be attached to the OVA and kept at the local site.
  9. Transfusion Quality shall include these variances in its monthly reports.

References:

Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, Maryland, USA

Bedside Monitoring of Transfusion

Once the blood component has left the hospital blood bank, it should be directed transported to the patient’s bedside for immediate transfusion.

At the bedside, the transfusionist (usually a nurse or doctor) must verify the information on the blood component labels (both the ISBT and specific reservation one for the patient).  With a bedside device, this includes:

  1. Scan the patient armband for hospital number
  2. Scan ISBT label:
    1. ABO/D type and any other antigen typings
    2. Blood component type (RBCs, platelets, plasma, etc.)
    3. Expiration date/time of the component
  3. Verify Reservation Label (on back of unit)— centrally performed in blood bank computer system based on #1 and #2 above:
    1. Intended recipient name and hospital number
    2. Compatibility status (compatible, least-incompatible, etc.)
    3. Expiration date/time of the compatibility testing/crossmatch
  4. Record Documentation During Transfusion:
    1. Physical inspection of the unit
    2. Time stamp of transfusion start
    3. Vital signs before starting transfusion
    4. Periodic vital signs during transfusion
    5. Time stamp of stopping transfusion
    6. Any adverse effects during the transfusion
    7. Any adverse effects after the transfusion (remote vital signs, oxygen saturation, EKG lead—if appropriate monitoring device attached to patient (e.g. Umana T1 device).

All of these parameters can be entered into a hand-held device that transmits them to the blood bank computer system (e.g. Medinfo Hemotrace.)

The Blood bank computer system (patient module) should verify that this is the proper unit for the intended recipient and that the transfusion is starting within the reservation limit of the unit and serves to verify the information on the reservation label attached on the back of the blood unit.

With a device such as  the new Umana T1 device from the GPI group, the vital signs together with an EKG lead and oxygen saturation can be automatically uploaded into the handheld device that feeds into the blood bank computer system such as Medinfo Hematos IIG and/or directly transmitted to the blood bank software.  This device can continuously record this information for several days and detect post-transfusion adverse effects such as TRALI/TACO and delayed hemolytic transfusion reactions.

Note:

Some other nursing hand-held devices are available for recording patient data but many cannot read the ISBT unit number or descriptor information.  They also do not check with the blood bank computer system to check if the right unit of blood is being offered to the patient during the validity of the transfusion period (four hours after leaving the blood bank).

Washed RBCs

Note:  This is an updated version of a previous post.

Principle:

Washing RBCs removes plasma and reduces the leukocyte count only by 1 log.  For leukodepletion, we must rely on filtration to reduce the WBCs to less than 1 x 10⁶ per unit according to CE rules.  Red cells or platelets in additive solution contain only minimal plasma (about 35 ml).  There are few definite indications for washing RBCs and it should be rarely necessary.

Policy:

Washing RBCs should only be done in the following circumstances:

  1. Deglycerolization of frozen RBCs.
  2. Severe allergic or anaphylactic reactions to plasma proteins
  3. IgA deficiency with anti-IgA
  4. Paroxysmal nocturnal hemoglobinuria PNH—relative indication (often these patients receive RBCs before the diagnosis of PNH is confirmed)
  5. Transfusing a previously irradiated RBC unit for pediatric use if more than 24 hours has passed since it was irradiated.
  6. Any other time when so designated by a transfusion medicine consultant.

Note:

  1. If anyone requests washed RBCs and it does not fit into one of the above categories, contact the transfusion medicine consultant.
  2. Washed RBCs are NO substitute for leukodepleting RBCs by filtration NOR can they be used in place of irradiation for prophylaxis against transfusion-associated-graft-versus-host disease TAGVHD.  Using the Reveos automated component processing system, all components are leukodepleted—RBCs are released in SAGM.

Reference:

Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA

Clinical Significance of a Negative DAT

In my opinion, the direct antiglobulin test is the most important concept that a transfusion medicine physician or technologist must understand in interpreting complex serology patterns.

Like all other testing, the DAT must not be interpreted alone but rather in the context of other laboratory and clinical results.  Still, it is very important to understand the significance of the DAT in hemolysis.

The mere presence of immunoglobulin on the RBC surface does not necessarily mean severe hemolysis.  The DAT strength increases with increased immunoglobulin coating of the RBCs but does not necessarily indicate how quickly the RBCs will be cleared.  That depends on the class and subclass of the antibody, whether and if so, how avidly it fixes complement, etc.

One trick question I give in my lessons to staff is, “What is the clinical significance of a negative DAT?”

In my career, I have seen severe hemolysis with either negative or weak DAT, the latter especially if there is weak C3 staining.  The DAT can be negative because there is no significant antibody OR there is a highly destructive antibody causing massive hemolysis, leaving only the antigen-negative cells (and in that case, there is still the possibility of innocent bystander hemolysis).

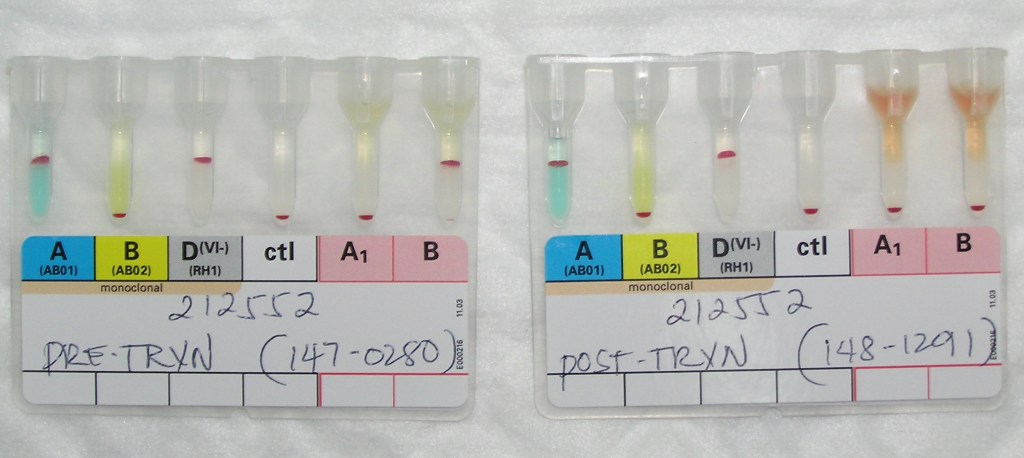
I show them the following case of an ABO-incompatible acute hemolytic transfusion reaction:

OLYMPUS DIGITAL CAMERA

In this case, a group A patient received a group B RBC unit intended for a patient with a similar name who was group B and was in a bed next to him.

Notice the patient’s complete loss of the reaction to group B cells in the reverse type and the supernatant hemolysis.  The DAT was negative.  The transfused B cells were not even present in the post-transfusion gel.

Here is the urine specimen from that case showing gross hematuria:

OLYMPUS DIGITAL CAMERA

So, in severe, life-threatening hemolysis, even antibody-mediated, you may have a negative DAT.  DAT negativity may also be seen in non-immune hemolysis.  I will discuss causes of DAT-negative hemolytic anemia is a future post.

In summary when doing a hemolysis investigation, a negative DAT does not mean everything is all right.  Everything must be interpreted in the context of the clinical and other laboratory findings.

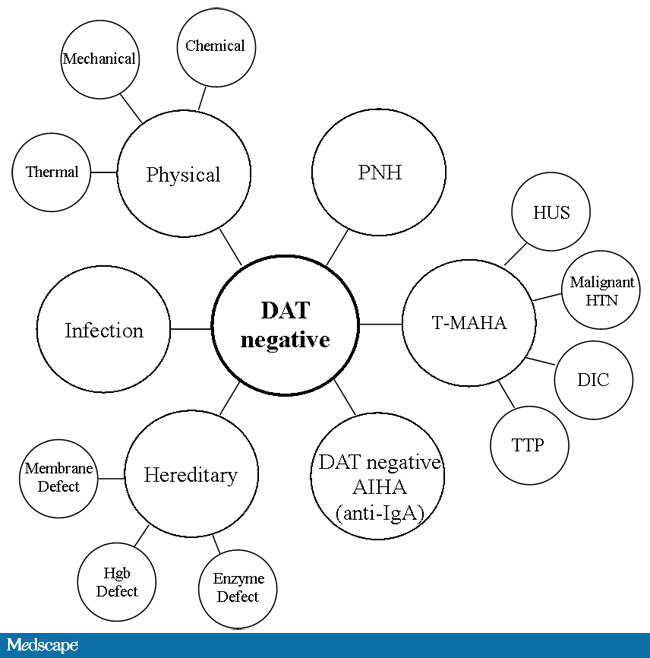
DAT-Negative Hemolytic Anemias

This is a summary diagram for the causes of DAT-negative hemolytic anemia, both immune and non-immune. For immune cases, a negative DAT may indicate “not-detected” with the amount of immunoglobulin on the RBC being below the threshold of the test methodology being used. Also rare IgA associated cases will not be detected unless a specific alpha-heavy chain monospecific reagent is used.