My Opinion: Separate Transfusion Medicine from the Laboratory

Transfusion Medicine includes laboratory and non-laboratory functions.  The non-laboratory and purely clinical functions are unique and have no analogy within the general laboratory.

The transfusion service/hospital blood bank laboratory is the closest to a laboratory operation, but there is component modification and complex manual testing, especially for reference immunohematology testing.  The staff must make detailed manual decisions, the errors for which could be life-threatening for the patient.

The blood donor center manufactures a pharmaceutical, i.e. blood components with collection, donor qualification, donor abnormal results review, infectious disease marker testing, component production, and donor immunohematology testing—all subject to Good Manufacturing Practices.  Never forget:  Blood is a drug!!

No other laboratory section is directly responsible for treatment of critically ill patients.  Therapeutic apheresis is essential for organ and stem-cell transplants, nephrology, neurology, etc.  No other laboratory section is directly responsible for treatment of critically ill patients.  Transfusion Medicine physicians are functioning as intensivists.  There is no hiding in the laboratory from clinical medicine.

There may also be an industrial manufacturing plant to extract various blood derivatives (e.g. factor concentrates, albumin, Rh immune globulin, etc.)  This is pharmaceutical manufacturing on a large-scale basis.  There is medical, technical, and special administrative expertise.

Many functions may operate 24/7.  The transfusion medicine physician may be on-call for donor issues and review of complex immunohematology problems to acutely decide which blood component (and phenotype) should be given as well as review all adverse reactions to transfusion.

The unique blend of clinical skills is unlike anything else in the laboratory.  Also, those outside the blood bank rarely have the skills or judgments for the best course of action for transfusion medicine or for its operations.

The clinical transfusion medicine physician must make acute, life-threatening decisions unlike anyone else in the laboratory.  The blood bank technologist is at the cutting edge of the battle with his testing and interpretations.  No other area of the laboratory is at such risk for injuring or even killing the patient.  There is high stress and burn-out.

I have talked with many blood bankers and many seem to share the exasperation that the laboratory does not understand us.  The latter looks at blood bank testing like that coming off a hematology or chemistry analyzer—although patients rarely would have severe morbidity or mortality like the blood bank from errors in those analyzers.

No laboratory pathologist has the pressure of the blood bank physician on-call.  It really is 24/7 and requires a broad, clinical background to make the right decisions.  It is very stressful and does not permit a good night’s sleep.

Thus, I make my case to separate us from the laboratory.  We can form our own more effective administrative organization and optimize our own planning.  Regretfully, I have never worked in such an administrative structure.  I also am a realist that cost-containment nowadays makes it much less likely high administration would permit this change for a mere cost center.  This will probably never happen during my career.

Finally, Transfusion Medicine is an essential service.  Blood components are essential drugs.  The operations and staff must be free of political influences.  This is a service for the entire region or country like the fire department, civil defense, etc.

8/8/20
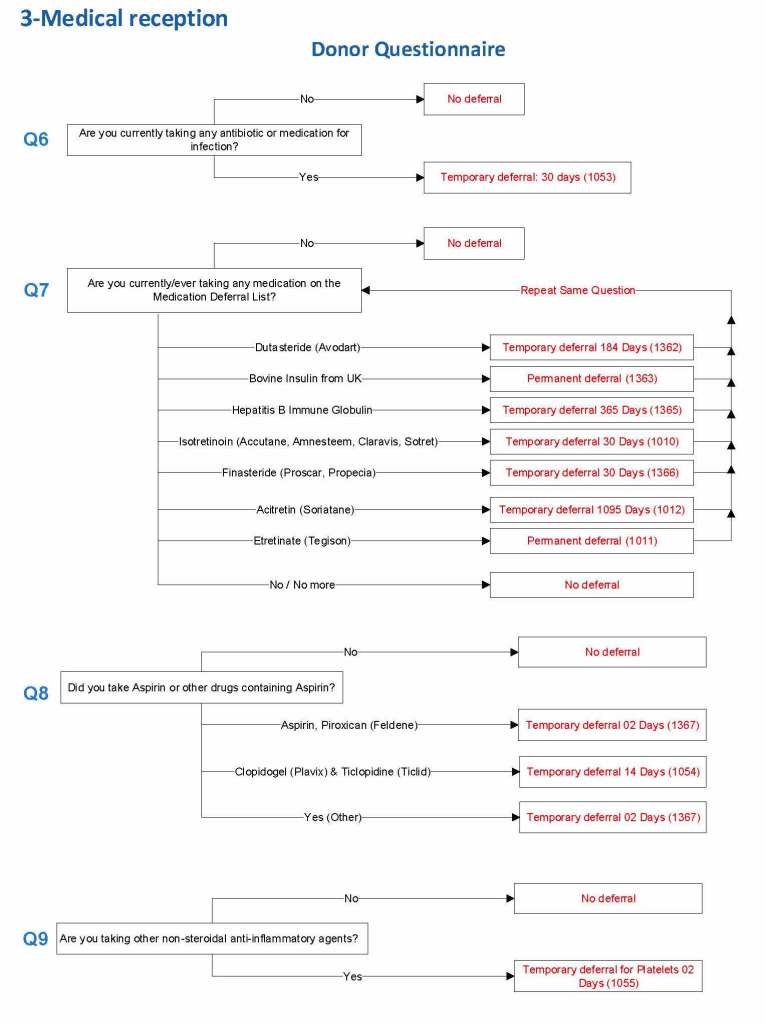
Processes and Software Building 28: Donor Questionnaire

Donor Collection 6

I started building this using the Uniform Donor Questionnaire UDQ from the AABB;  however, I modified it to include coverage for Chikungunya, Zika, etc. and to include enhanced processes for malaria based on the Australian Red Cross.

For each screening question, I prepared the exact wording (usually the UDQ’s) and set the deferral to temporary (how many days) or permanent.

Some questions were more open-ended, and the interviewer manually entered a medication, surgical procedure, etc.  The transfusion physician would review this and assign a temporary (specifying the interval) or permanent deferral.

The questionnaire was constantly being updated by changes.  My role was to review different accreditation systems (AABB, CE, etc.) and the World Health Organization’s websites.  I would then prepare an interim policy and pass the specifications for the changes to the Medinfo software engineer and when ready, finally to the Super Users for testing.  If there was an urgent change, the whole process could be completed in less than one day including validation testing.

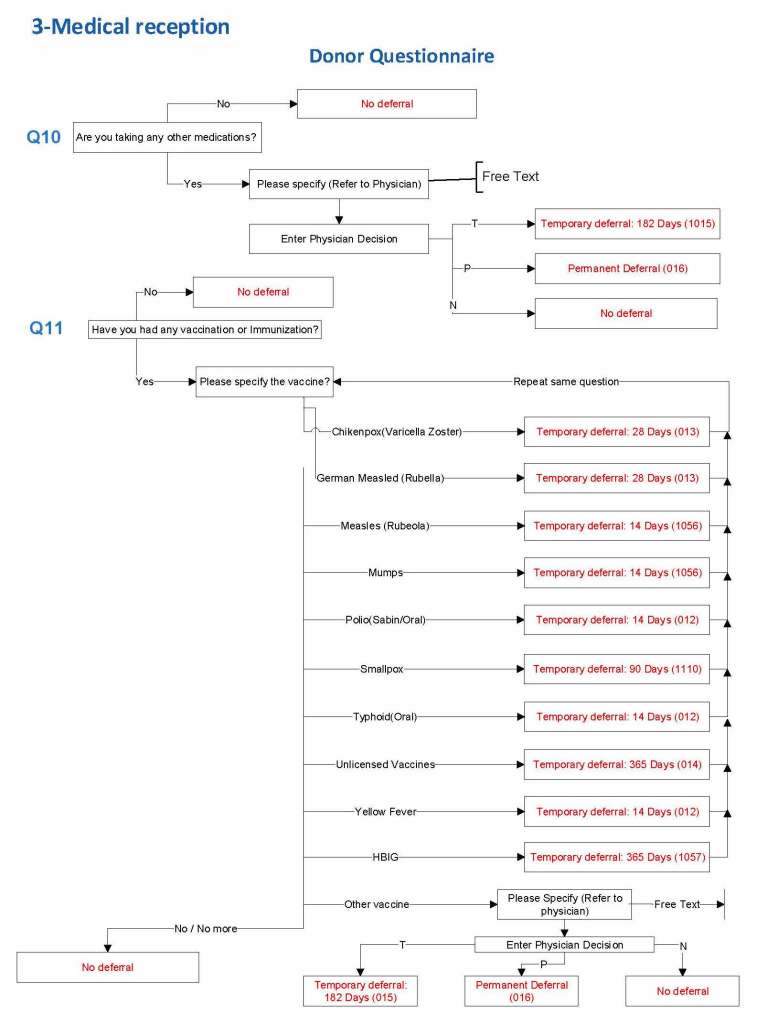
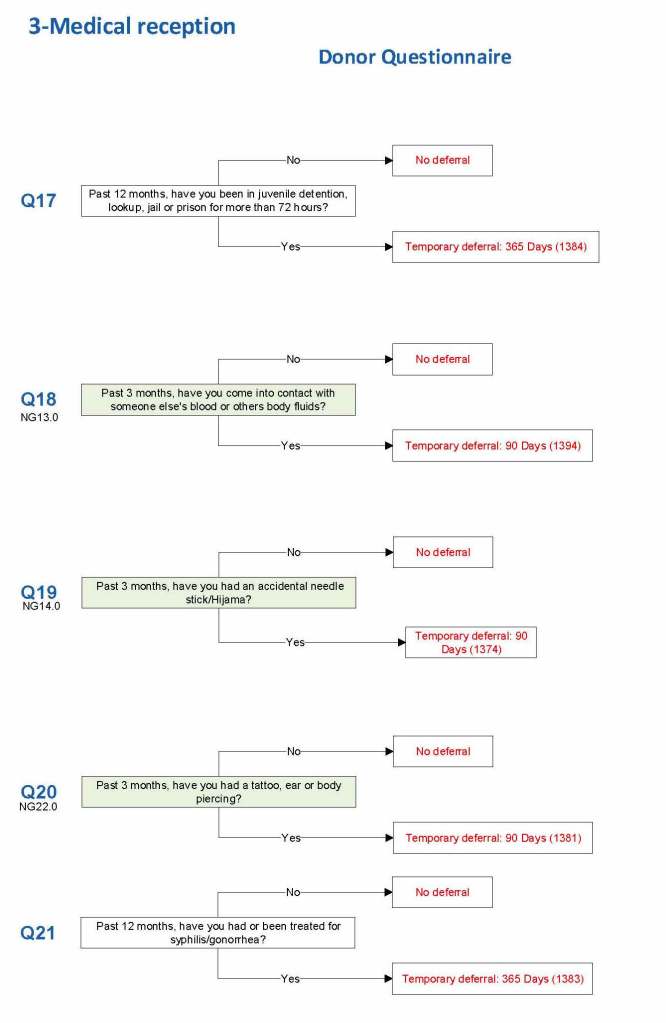
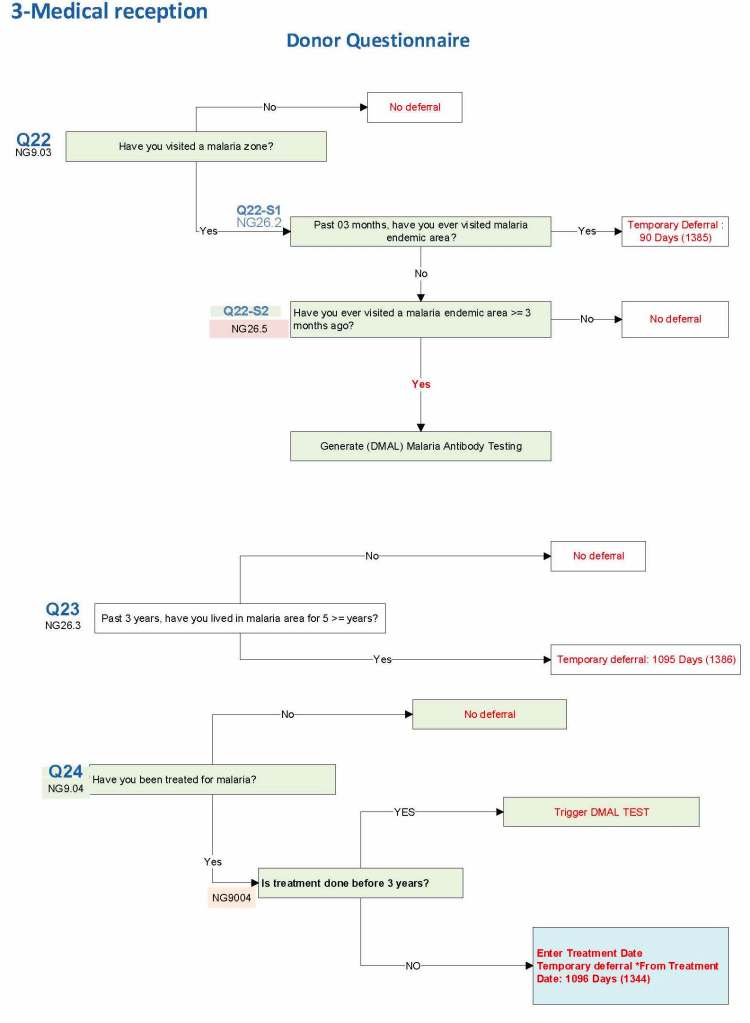
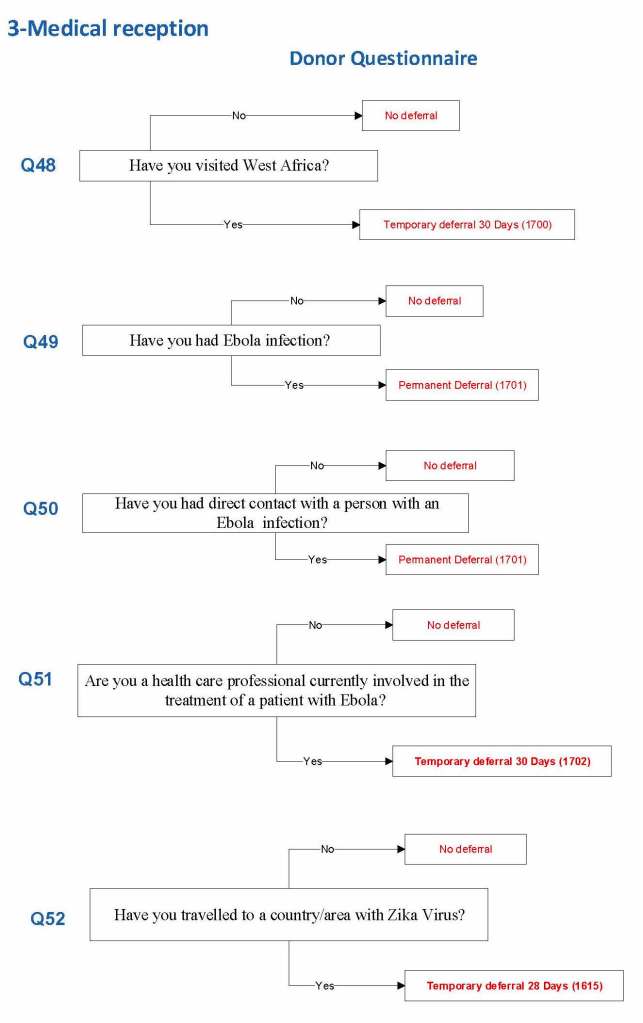
The following shows examples of the software processes:

  1. Medications
  2. Body fluid exposures
  3. Vaccinations
  4. Malaria
  5. Ebola/Zika

I emphasize that all of these settings are user-definable (at least in jurisdictions that permit all open, non-turnkey software).

Medication Questions:

Vaccinations:


Blood and Body Fluid Exposures:

Malaria Example:  DMAL refers to the malaria antibody test.


Ebola and Zika Examples:

7/8/20

Neonate Born to Bombay Oh Mother

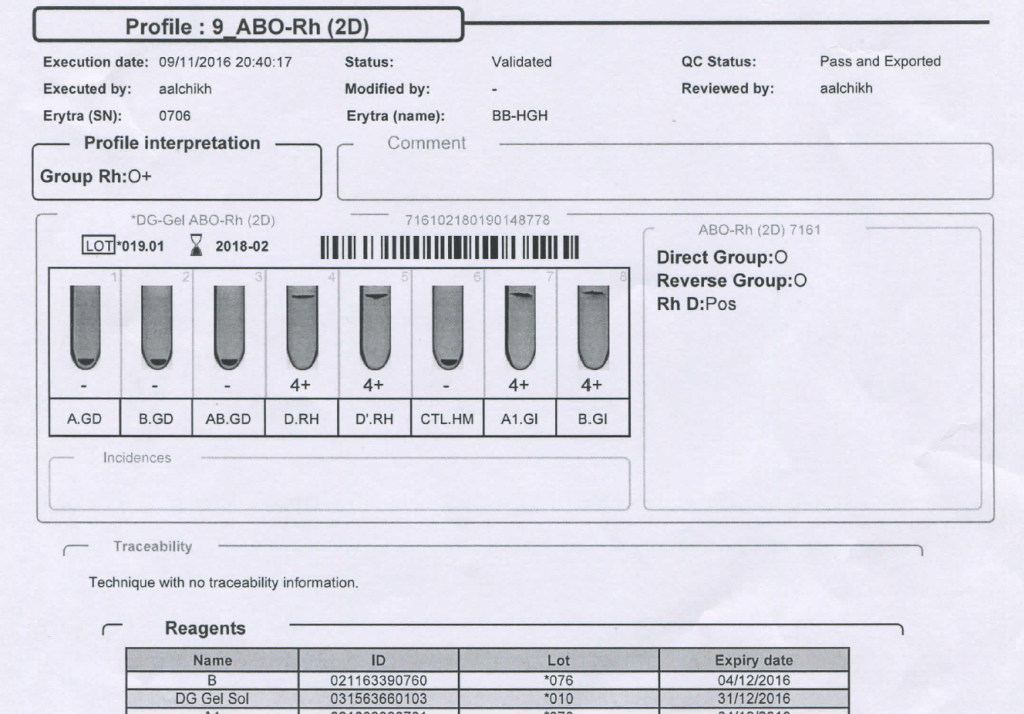
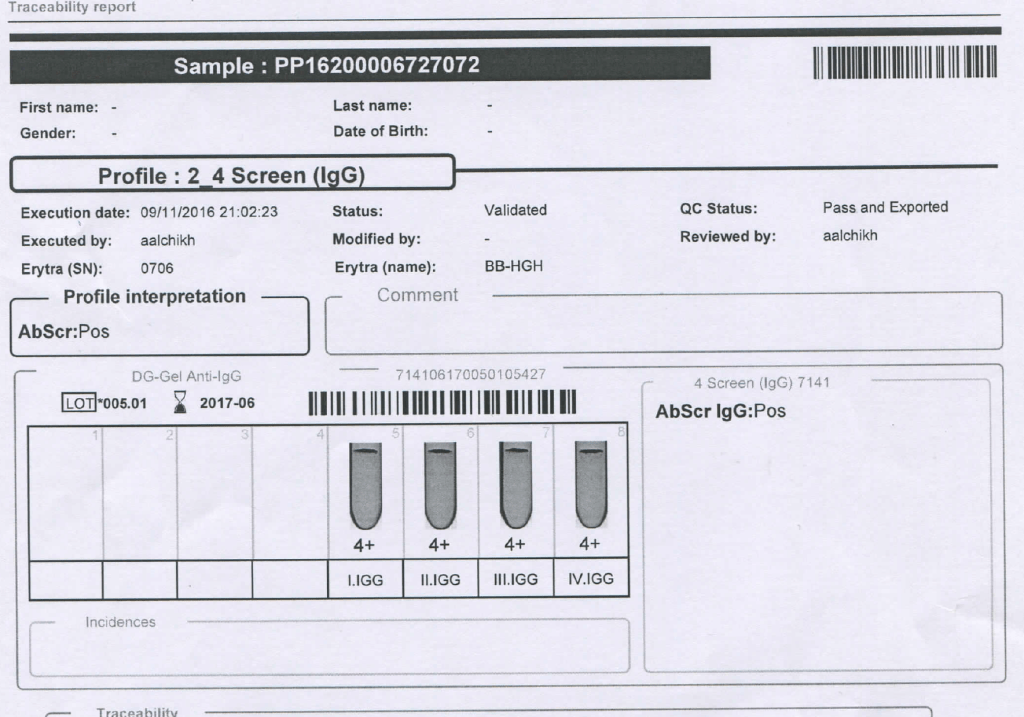
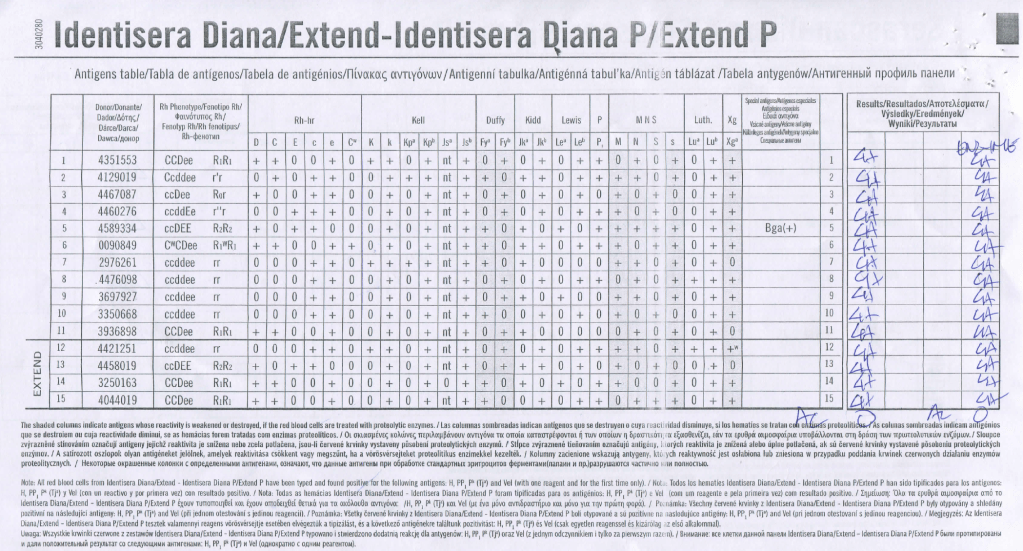
We had a mother (R1R1 K-neg) from Tamil Nadu who had several visits to our hospital.  Anti-H lectin was negative.  Here is a summary of her workup:

Mother’s ABO/D Typing:

Mother’s Antibody Screen:

Mother’s Antibody Identification:

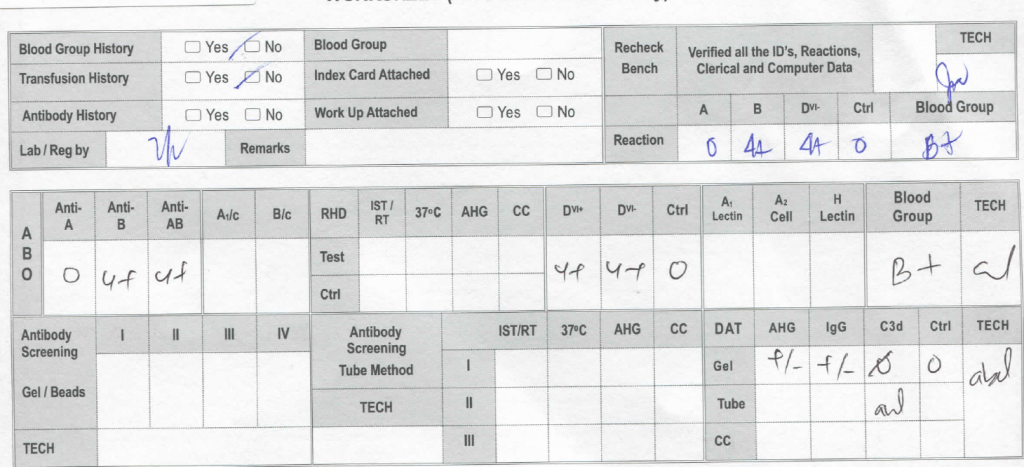
She gave birth to a baby girl, group B, R1R1 K-neg.  This is the neonate’s workup:

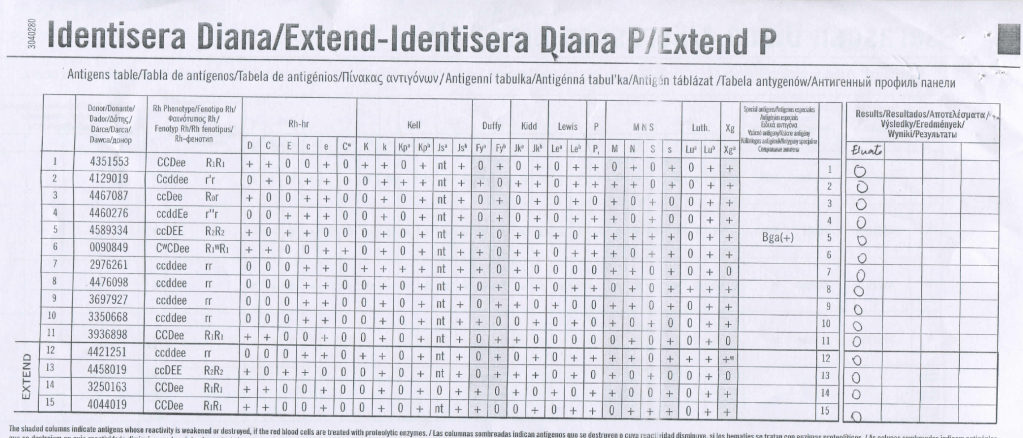
Despite the weakly positive IgG DAT, the eluate was negative.  The neonate was asymptomatic.

Anti-H is mainly an IgM antibody and does not cross the placenta, thus no HDFN was noted.

6/8/20

Processes and Software Building 27 Donor Center 5

Building the Software Processes for the Donor Collection 5: Donor Physical Examination and Adverse Reaction Reporting

Donor Physical Examination and Adverse Reactions

Donor physical examination, along with the donor questionnaire, are important both for donor and patient safety.  In general:

Is it safe for the donor to donate?

Is it safe for the patient to receive the blood even if it is safe for the donor to donate.

Any donor who does not feel well must not donate.  This may be the single most important step in ensuring a safe blood supply.

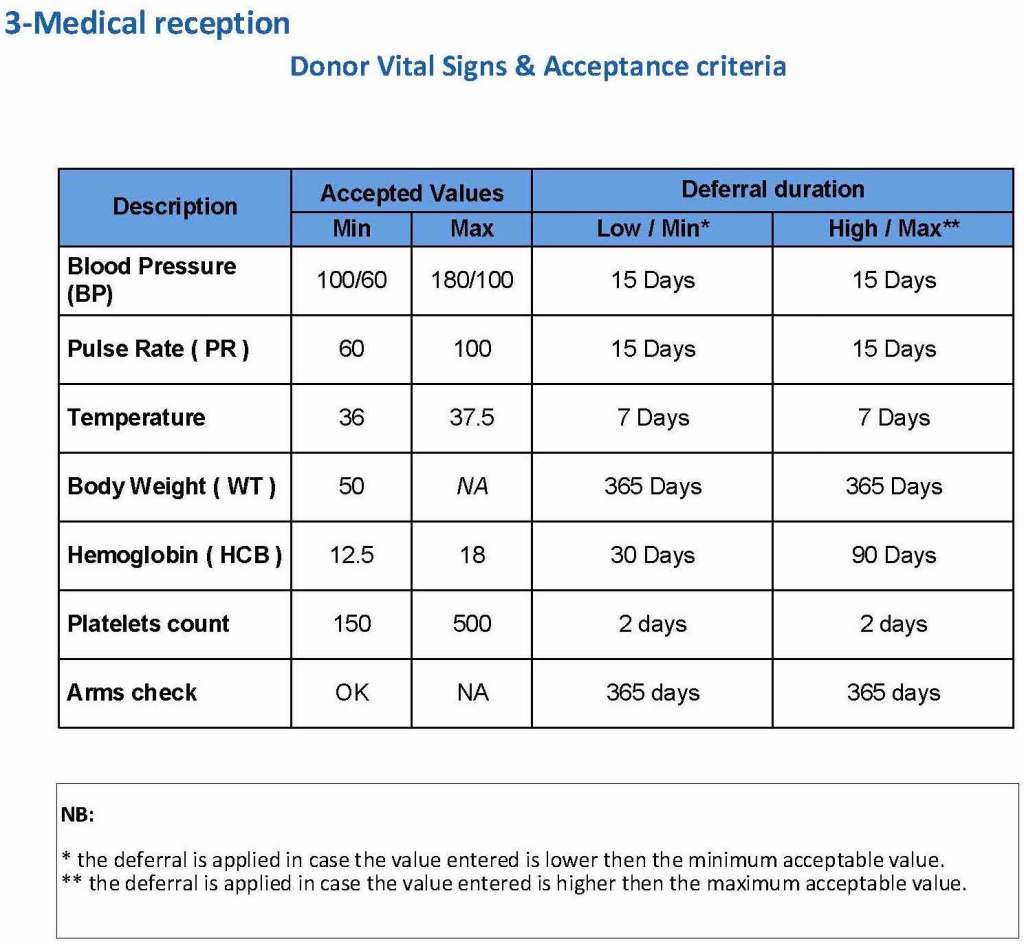
The donor physical examination includes the vital signs (blood pressure, pulse, temperature, heart rate, and temperature).  I have attached a sample set of criteria for review.  All are user-definable.  Note how the arm examination is also included (looking for scarring, skin lesions, etc.)

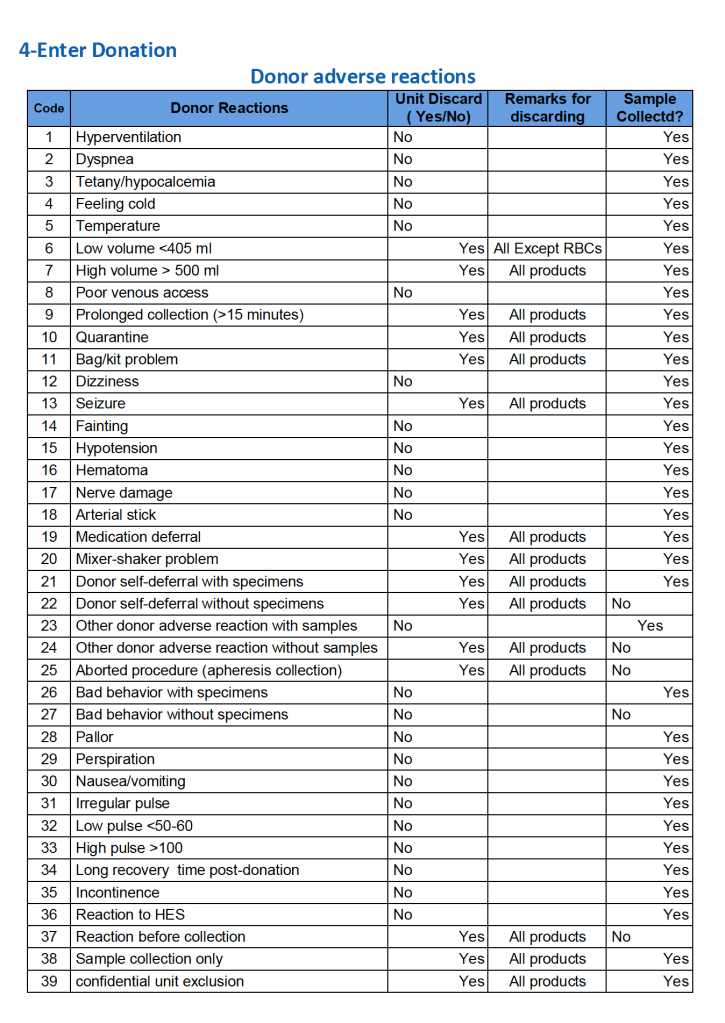
For all types of donations, there may be adverse reactions.  These must be documented in the record along with the disposition of the donation.  Will the donor need an extended deferral if the RBCs in the apheresis run are not returned?  This can be built from the reaction documentation.  Note the following sample table of reactions.

To Be Continued

5/8/20

Time: Appreciating How Long Testing Takes

I have had many medical students, residents, and fellows rotate through my Transfusion Medicine department.  Hardly anyone has had any interest in making my discipline his/her career.  It is a required rotation or an “easy” rotation during which the trainee may take his vacation.  The trainee will cram for the examination and then promptly forget it.

I left practice in the USA in 1990, in what I consider the golden age of laboratory medicine.  We had supervisors for each laboratory section.  In the blood bank, we had many staff with SBBs or who were SBB students.  We were very self-sufficient in handling immunohematology problems except for rare blood types or antibodies to high incidence/prevalence antigens.

When I returned to visit my old laboratory.  I sensed a deprofessionalization of the laboratory and blood bank in particular.  Blood Bank now is a cost center, not an area of revenue.  Why hire experienced blood bankers for most hospitals?  Send the antibody workups to the Blood Center.  There are limited jobs for transfusion medicine consultants.  Minimize testing, don’t do extended antigen typings, etc.

Nowadays, I feel like one of the dinosaurs marching into oblivion as in Walt Disney’s Fantasia film, the section called The Rite of Spring.  Who will replace those of us retiring?  Have you ever noted the average age of attendees at the AABB annual convention?  I feel young when I go there (and don’t worry about the gray hair!)

I want to attract new doctors and scientists to Transfusion Medicine.  I really try, but most have no interest and look on their rotations as a necessary evil.

I have lowered my expectations for most medical trainees in Transfusion Medicine.  They don’t like it, they just want to pass it, and move on.  What must I impress them with for their future careers?  What is essential for them to remember?

I have had both pathology and non-pathology trainees.  Surgical and ob/gyn doctors used to spend one month whereas the hematology and pathology residents/fellows spent on average three months.  The few interested in the field might do multiple rotations.

I still gave them lectures on a variety of topics, especially how to transfuse blood components, basic ABO/Rh antigens, compatibility testing, and direct antiglobulin testing.  They would forget most of this, but I wanted them to remember TURN-AROUND-TIMES:

How long does it take to perform the test?

Find compatible blood?

Thaw the plasma?

Release a massive transfusion protocol shipment?

Complete a transfusion reaction workup before releasing more blood?

I am not discouraging people from entering the field, but I am a realist to know that few will share my passion for serology or want to take call on difficult immunohematology cases.  At least if they understand the pressure the technical staff are in and these turn-around-times this will make both their work as clinicians and mine as transfusion medicine more congenial.

Processes and Software Building 26: Donor Collection 4

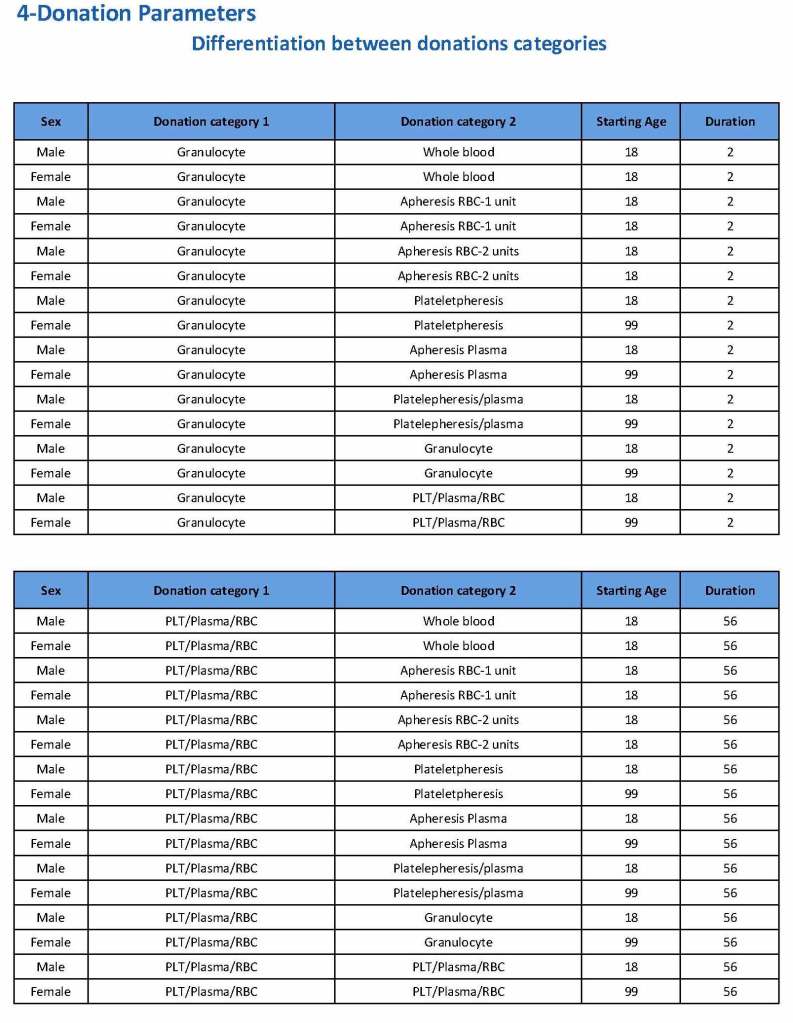
Deferral Intervals for Each Donation Type

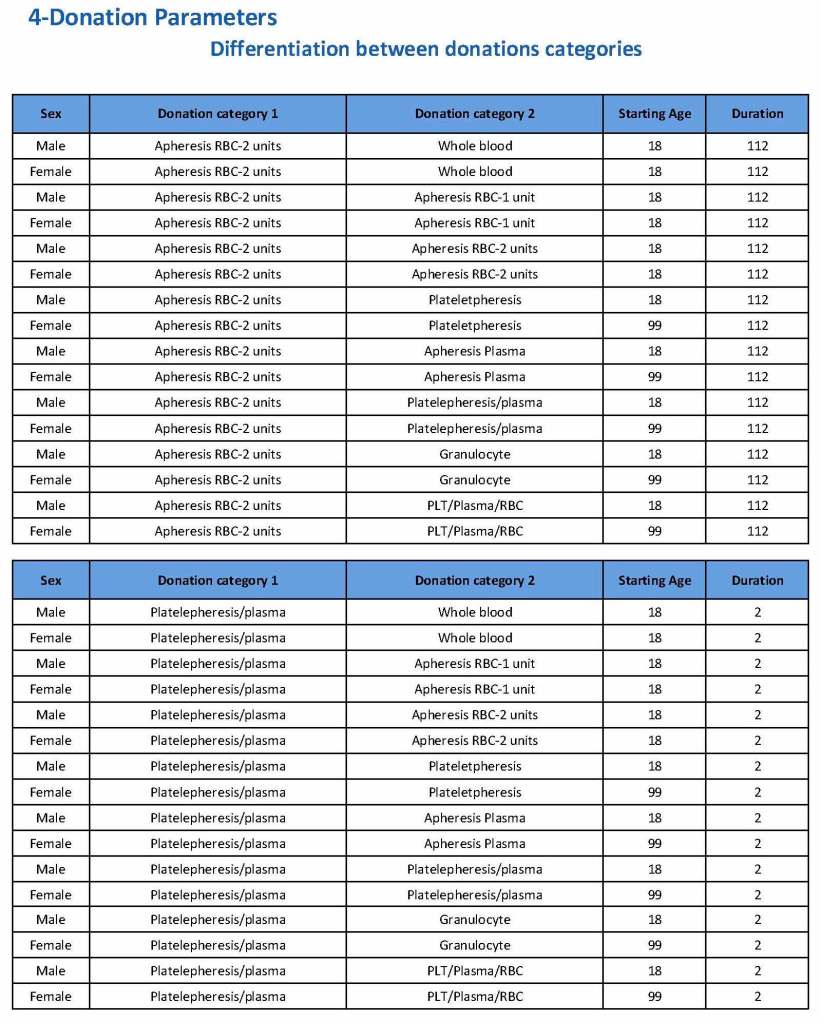
Donation can be whole blood or apheresis-based.  The sex and age for each donation type is specified.  At HMC, we did not accept females for platelet or plasma donations, so the starting age is listed as 99 years.  Otherwise, in accordance with Qatari law, the starting age for donation is 18.  All these parameters are user-definable, and a transfusion medicine physician can override the rules if necessary.

For each and every combination of donations, the deferral interval must be specified.  Examples follow.  The temporary deferral period is in days:

Previous donation whole blood, current donation whole blood:  56

Previous donor platelets, current donation whole blood:  2

Previous donation whole blood, current donation platelets:  56

Also note how for each possible combination there is an entry for male AND female.  Females are restricted to whole blood donation and only RBCs will be made from the collection.

If there is a collection incident and the apheresis procedure is not completed, the interval will be set to 56 days.  This will be covered in the post on donor adverse effect reporting.

To Be Continued:

3/8/20

Daratumumab Anti-CD38 Interference with Compatibility Testing

Principle:

Daratumumab is a monoclonal antibody that binds to CD38 antigen, which is expressed weakly on the surface of all RBCs.  It may thus cause a positive direct antiglobulin test DAT and so interfere with compatibility testing if an antiglobulin phase is required.

This effect may persist up to 6 months after discontinuing the drug.  The monoclonal antibody does not interfere with routine ABO/D typing.

Special techniques (neutralization of CD38 antibodies by CD38 anti-idiotypic antibodies, or soluble CD38 antigen) may remove the panreactivity but are not generally available.  DTT, a sulfhydryl reagent may denature the native CD38 antigen on RBCs but it should be used under a biologic hood.

Kell antigens will be denatured so Kell antibodies cannot be detected after treatment so Kell-negative RBCs should be used.  In the Gulf Area, this is about 72% of RBCs. In the Medinfo software a rule to require K-negative RBCs has been built.

Policy:

  1. The clinical services must inform Transfusion Medicine of patients who will be receiving daratumumab therapy BEFORE treatment is started.
  2. Transfusion Medicine staff will enter a general comment (i.e. not associated with a particular result) in the patients Medinfo HIIG record:  PATIENT ON DARATUMUMAB.
  3. If not already done, Transfusion Medicine staff will perform an extended antigen typing:  at least C, c, E, e, K, k, Kpa, Jka, Jkb, Fya, Fyb ,M, N, S, s, Lea, Leb, P1—even if no antibodies are currently identified.
  4. Transfusion Medicine staff will send each such patient’s record to a Transfusion Medicine Physician to determine the blood type including extended antigens to match for future transfusions.
  5. When compatibility testing is requested, perform it as per our SOPs.
  6. If available, prepare DTT-treated cells for testing but realize that this will denature Kell antigens.  Use K-nell RBCs.
    1. Medinfo has a rule to automatically require K-negative RBCs if this medication is used.
  7. Release least “incompatible” RBCs must be approved by the Transfusion Medicine Physician.
  8. When the DAT becomes negative (i.e. up to SIX months after cessation of Daratumumab therapy), routine compatibility testing and RBC selection will apply.

References:

Trick or Treatment, Anti-CD38 Reactivity and How to Treat It, AABB Satellite Symposium transcript, U. Cincinnati and RedMedEd, October, 2015 (attachment)

Processes and Software Building 25–Donor Collection 3

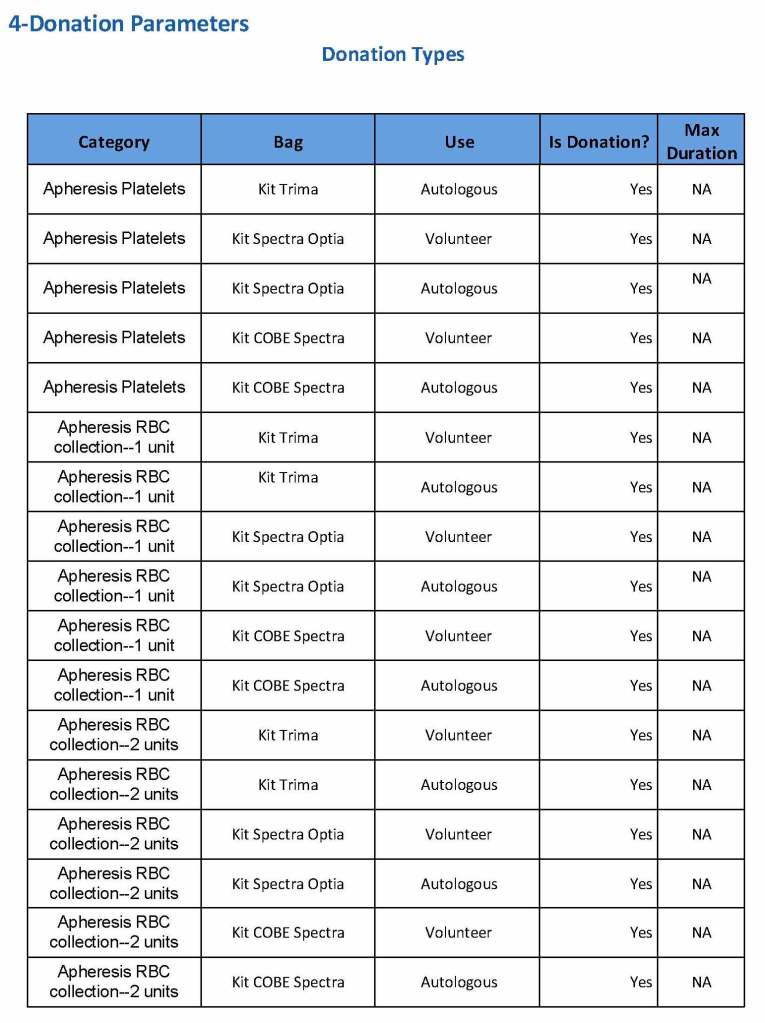
Donation Type and Bag Parameters

At the time of registration, the type of donation must be specified.  In my last position, this could include whole blood for automated Reveos, whole blood for cryoprecipitate, plasmapheresis, COVID 19 convalescent plasmapheresis, plateletpheresis, concurrent platelet and plasmapheresis, concurrent platelet, plasma, and RBC apheresis, RBC apheresis-one unit, and RBC apheresis-2 units.

There is also a specimen-only donation without actual collection that includes database check, assignment of an ISBT specimen number, donor questionnaire, physical examination, and specimen collection only..

We specified which bag or kit could be used for each type of donation so when it was selected, only that bag type would be accepted by Medinfo

For each of these types we must specify what type of donation is permitted:  volunteer, autologous, or directed.

Finally, we must indicate the maximum length of the procedure permitted.  This applied to whole blood only and we set this at 15 minutes—this is user definable.

The following are a sample set of parameter settings for the above:

Note how we included contingencies for old bag sets and equipment (that we later discontinued) and for granulocyte collection (which we did not actually perform).

To Be Continued:

1/8/20

Processes and Software Building 24: Data Entry Verification

Principle:

This policy outlines steps taken to minimize the risk of data entry errors and is based on a dualistic approach:  review of results by a senior technologist and/or supervisor and various computer safeguards built into the Medinfo Hematos IIG blood bank computer HIIG system.  This policy also discusses the verification (here called authorization) and purge processes of HIIG.

Policy:

  1. Review by senior technical, supervisory, or transfusion medical staff:
    1. Designated test procedures require review by a second technologist before authorization.
    2. Complex immunohematology testing and specimens showing aberrant results (e.g. ABO/D discrepancies) are reviewed by the supervisors or designates and ultimately a transfusion medicine physician before authorization.
  2. Computer system HIIG rules:
    1. Privileges:
      1. System restricts which staff can perform specific tests
    2. Patient/donor identity:
      1. System asks end-users to verify patient/donor identity before starting any access to the patient/donor record.
      2. System performs historical database checking and flags any inconsistencies (e.g. historical ABO/D typing differences, etc.)
    3. Testing:
      1. Only selected staff have privileges to authorize or purge.
      2. ABO/D testing algorithms require entry of reactions, not interpretation of results and are compared to a truth table.
        1. Aberrant results require special review before ABO/D typing results can be authorized/purged.
        2. D-controls must be negative to allow D typing results to be authorized for liquid D-typing reagents.
      3. DAT results require appropriate controls to meet truth-table criteria.
      4. Eluates require last wash to be negative before authorization
    4. Blood components:
      1. Selection of RBC or plasma units requires two independent sample determinations within 72 hours of each other.
      2. ABO-incompatible RBC or FFP/FP24 transfusions are not allowed.
      3. Donors with any detectable antibodies are permanently deferred.
      4. Depending on the patient’s antibody history, release of RBC units may require antigen-matched units.  Examples:
        1. Mandatory matching (only antigen negative matched units allowed—no antigen positive or antigen-untyped units):  Antibodies against H, D, c, K, k, Kpa, Kpb, Jsa, Jsb, Jka, Jkb antigens, anti-PP1Pk
        2. Priority matching (incompatible or untested can be approved by a transfusion medicine physician):  C,E, e, Fya, Fyb, M, S, s
        3. Antigen matching not required:  Lea, Leb, N
      5. Least-incompatible crossmatch require special authorization to release
      6. Protocols to force irradiation or other modified components can be setup in HIIG.
    5. Donors:
      1. Donor tests have same criteria as the same test used in patient testing for controls, etc.
      2. Donor demographics are read directly from the Ministry of Interior database—no manual entry (bar code only used).

References:

  1. Workflows for Hematos IIG (1001 through 1005), 2013
  2. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  3. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition