Projective Exercise 2

As a transfusion medicine physician, I must know if I can trust my staff’s interpretation of immunohematology testing.  I may be called at night and they will provide me with results and I must use these to make a medical judgment.  If their interpretation is flawed, I might make a decision that harms the patient.

I really don’t like multiple-choice questions, but nowadays this is often the norm.  For my staff, especially senior staff and those who want to be promoted to senior staff, I have developed a series of projective exercises to help me understand their thought processes.

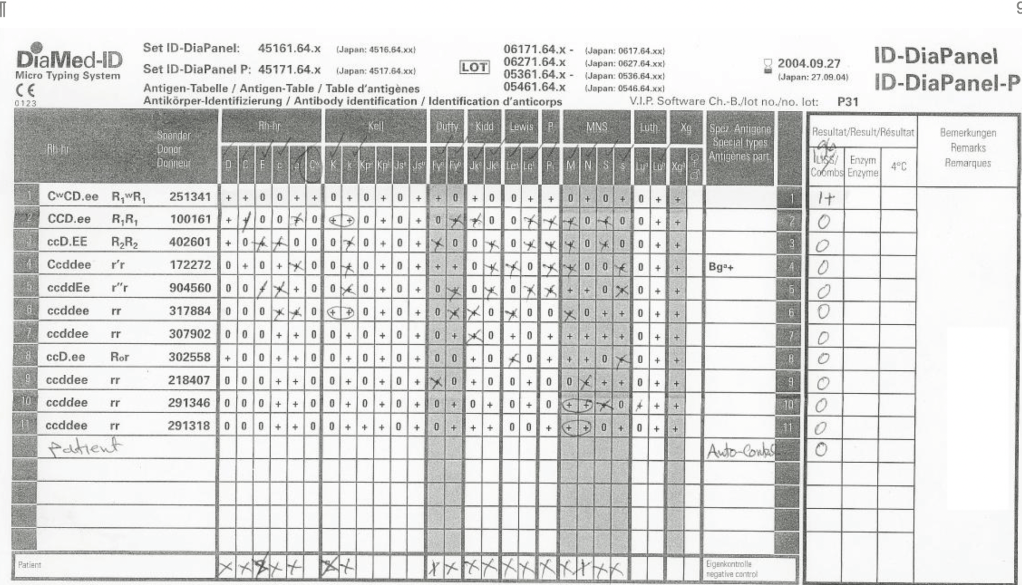
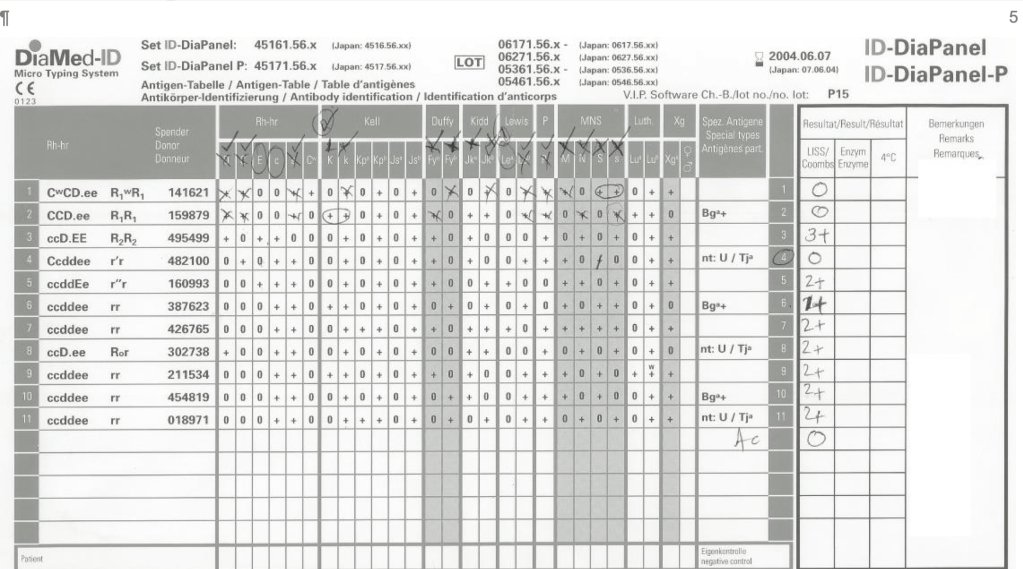
Here is another exercise, usually given to base medical technologists.  I have the staff review this panel and tell me to interpret it:

Many staff called this anti-E and anti-c.  They did not note that there is no E-positive c-negative cell.  Also, many did not see that one c-positive cell had no reaction—they did not notice that the c was heterozygous (C+c+ not c+c+).

A medical technologist must not be sloppy, but rather very meticulous.  If there are discrepancies in the panel, they must rule out dosage, zygosity, etc.  They should not name an antibody specificity with only one antigen-positive cell.

To Be Continued:

22/8/20

Projective Exercise 1

As a transfusion medicine physician, I must know if I can trust my staff’s interpretation of immunohematology testing.  I may be called at night and they will provide me with results and I must use these to make a medical judgment.  If their interpretation is flawed, I might make a decision that harms the patient.

I really don’t like multiple-choice questions, but nowadays this is often the norm.  For my staff, especially senior staff and those who want to be promoted to senior staff, I have developed a series of projective exercises to help me understand their thought processes.

Here is a sample exercise.  I have the staff review this panel and tell me to interpret it:

Most of them answer that this is an anti-Cw without hesitation.  However, they are basing that on only one Cw-positive cell.

More astute ones indicate it might be anti-Cw but ask to test additional Cw-positive cells and perform an enzyme panel.  These are the ones that I will consider for promotion now.

Neonate Born to Bombay Oh Mother

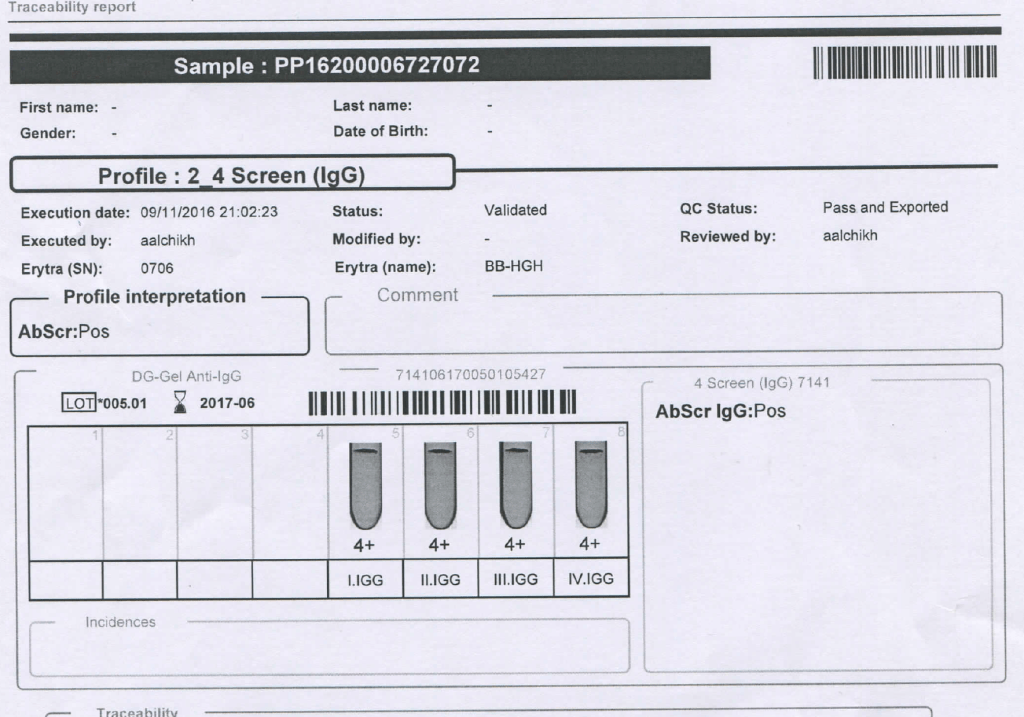
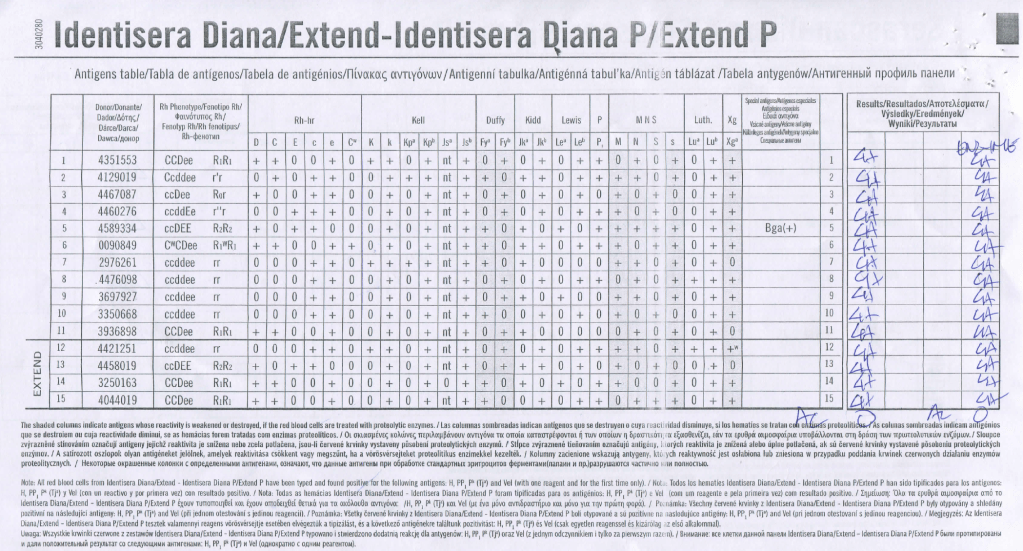
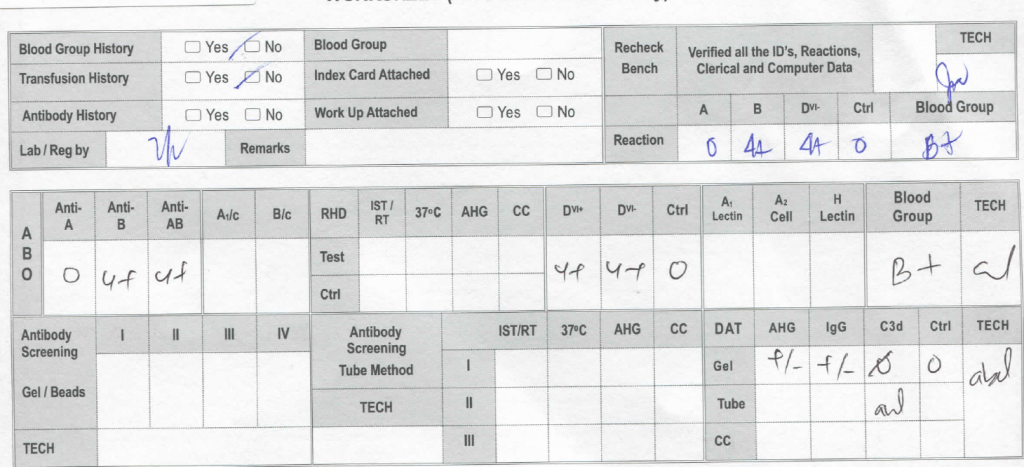
We had a mother (R1R1 K-neg) from Tamil Nadu who had several visits to our hospital.  Anti-H lectin was negative.  Here is a summary of her workup:

Mother’s ABO/D Typing:

Mother’s Antibody Screen:

Mother’s Antibody Identification:

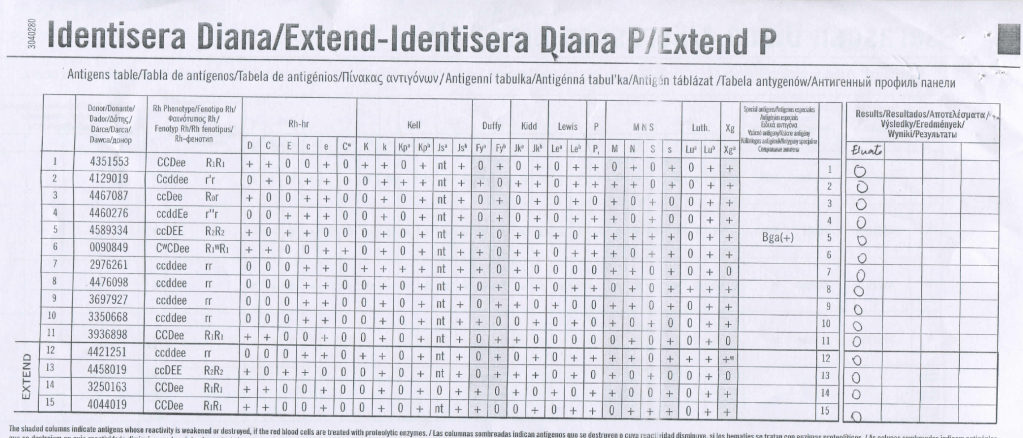
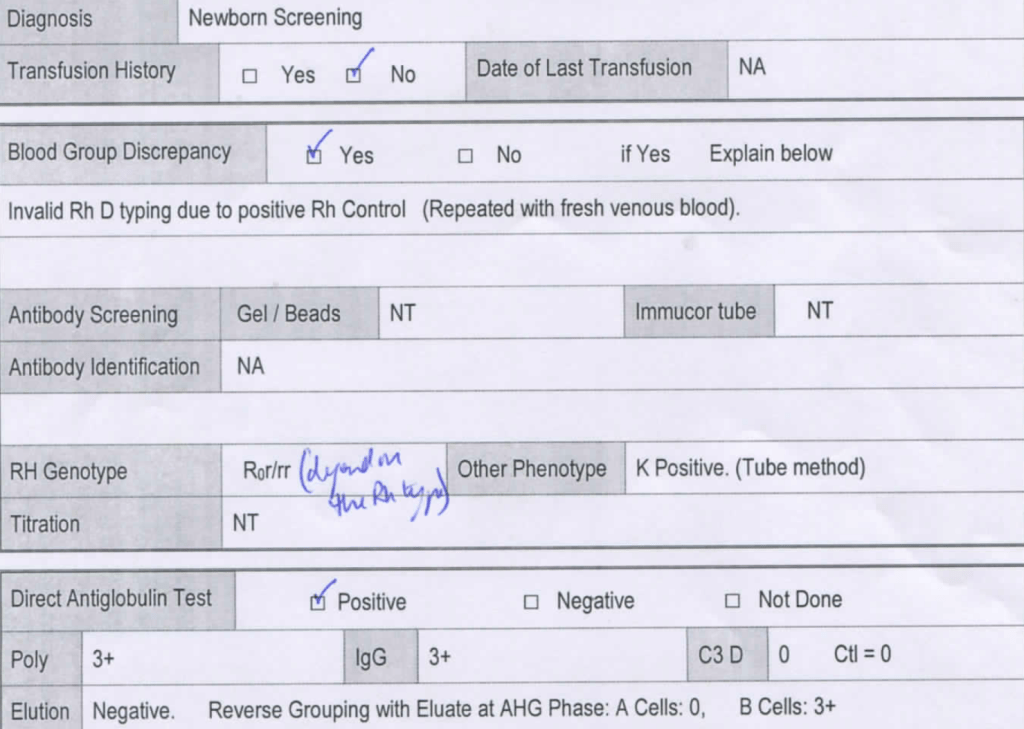
She gave birth to a baby girl, group B, R1R1 K-neg.  This is the neonate’s workup:

Despite the weakly positive IgG DAT, the eluate was negative.  The neonate was asymptomatic.

Anti-H is mainly an IgM antibody and does not cross the placenta, thus no HDFN was noted.

6/8/20

Time: Appreciating How Long Testing Takes

I have had many medical students, residents, and fellows rotate through my Transfusion Medicine department.  Hardly anyone has had any interest in making my discipline his/her career.  It is a required rotation or an “easy” rotation during which the trainee may take his vacation.  The trainee will cram for the examination and then promptly forget it.

I left practice in the USA in 1990, in what I consider the golden age of laboratory medicine.  We had supervisors for each laboratory section.  In the blood bank, we had many staff with SBBs or who were SBB students.  We were very self-sufficient in handling immunohematology problems except for rare blood types or antibodies to high incidence/prevalence antigens.

When I returned to visit my old laboratory.  I sensed a deprofessionalization of the laboratory and blood bank in particular.  Blood Bank now is a cost center, not an area of revenue.  Why hire experienced blood bankers for most hospitals?  Send the antibody workups to the Blood Center.  There are limited jobs for transfusion medicine consultants.  Minimize testing, don’t do extended antigen typings, etc.

Nowadays, I feel like one of the dinosaurs marching into oblivion as in Walt Disney’s Fantasia film, the section called The Rite of Spring.  Who will replace those of us retiring?  Have you ever noted the average age of attendees at the AABB annual convention?  I feel young when I go there (and don’t worry about the gray hair!)

I want to attract new doctors and scientists to Transfusion Medicine.  I really try, but most have no interest and look on their rotations as a necessary evil.

I have lowered my expectations for most medical trainees in Transfusion Medicine.  They don’t like it, they just want to pass it, and move on.  What must I impress them with for their future careers?  What is essential for them to remember?

I have had both pathology and non-pathology trainees.  Surgical and ob/gyn doctors used to spend one month whereas the hematology and pathology residents/fellows spent on average three months.  The few interested in the field might do multiple rotations.

I still gave them lectures on a variety of topics, especially how to transfuse blood components, basic ABO/Rh antigens, compatibility testing, and direct antiglobulin testing.  They would forget most of this, but I wanted them to remember TURN-AROUND-TIMES:

How long does it take to perform the test?

Find compatible blood?

Thaw the plasma?

Release a massive transfusion protocol shipment?

Complete a transfusion reaction workup before releasing more blood?

I am not discouraging people from entering the field, but I am a realist to know that few will share my passion for serology or want to take call on difficult immunohematology cases.  At least if they understand the pressure the technical staff are in and these turn-around-times this will make both their work as clinicians and mine as transfusion medicine more congenial.

Daratumumab Anti-CD38 Interference with Compatibility Testing

Principle:

Daratumumab is a monoclonal antibody that binds to CD38 antigen, which is expressed weakly on the surface of all RBCs.  It may thus cause a positive direct antiglobulin test DAT and so interfere with compatibility testing if an antiglobulin phase is required.

This effect may persist up to 6 months after discontinuing the drug.  The monoclonal antibody does not interfere with routine ABO/D typing.

Special techniques (neutralization of CD38 antibodies by CD38 anti-idiotypic antibodies, or soluble CD38 antigen) may remove the panreactivity but are not generally available.  DTT, a sulfhydryl reagent may denature the native CD38 antigen on RBCs but it should be used under a biologic hood.

Kell antigens will be denatured so Kell antibodies cannot be detected after treatment so Kell-negative RBCs should be used.  In the Gulf Area, this is about 72% of RBCs. In the Medinfo software a rule to require K-negative RBCs has been built.

Policy:

  1. The clinical services must inform Transfusion Medicine of patients who will be receiving daratumumab therapy BEFORE treatment is started.
  2. Transfusion Medicine staff will enter a general comment (i.e. not associated with a particular result) in the patients Medinfo HIIG record:  PATIENT ON DARATUMUMAB.
  3. If not already done, Transfusion Medicine staff will perform an extended antigen typing:  at least C, c, E, e, K, k, Kpa, Jka, Jkb, Fya, Fyb ,M, N, S, s, Lea, Leb, P1—even if no antibodies are currently identified.
  4. Transfusion Medicine staff will send each such patient’s record to a Transfusion Medicine Physician to determine the blood type including extended antigens to match for future transfusions.
  5. When compatibility testing is requested, perform it as per our SOPs.
  6. If available, prepare DTT-treated cells for testing but realize that this will denature Kell antigens.  Use K-nell RBCs.
    1. Medinfo has a rule to automatically require K-negative RBCs if this medication is used.
  7. Release least “incompatible” RBCs must be approved by the Transfusion Medicine Physician.
  8. When the DAT becomes negative (i.e. up to SIX months after cessation of Daratumumab therapy), routine compatibility testing and RBC selection will apply.

References:

Trick or Treatment, Anti-CD38 Reactivity and How to Treat It, AABB Satellite Symposium transcript, U. Cincinnati and RedMedEd, October, 2015 (attachment)

Case Report: Blocking Anti-B

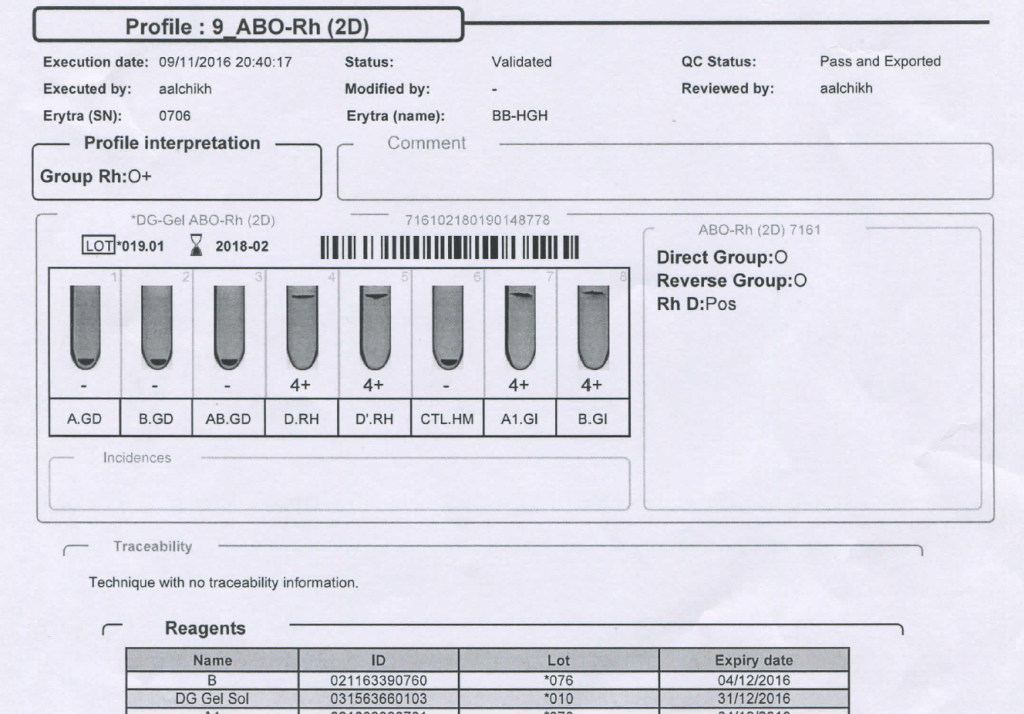
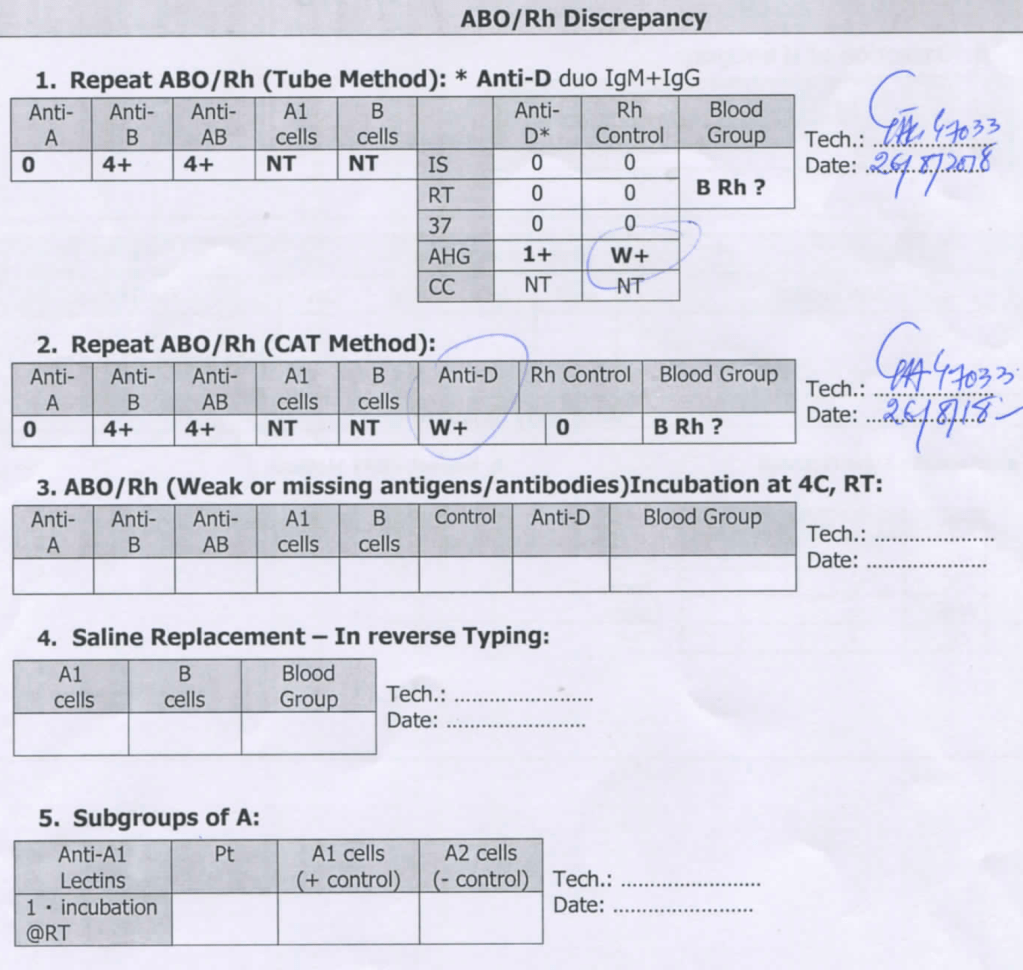
Recently, I had a case where the blocking antibody was not an anti-D, but rather an anti-B in a case of ABO hemolytic disease of the fetus/newborn HDFN.  The D typing result was weak but the D control in the gel was positive so the result was indeterminate.  DAT was 3+ IgG and anti-B was identified in the eluate (mother was antibody screen negative, regular elution panels (group O cells) were negative.  Some of the actual workup follows:

29/7/20