This is a continuation of yesterday’s post.
The following is a sample validation performed by the Super Users for the upgrade of the blood bank software Medinfo Hematos IIS from version 3.8 to 5.0:




Teaching medical and technical staff transfusion medicine
This is a continuation of yesterday’s post.
The following is a sample validation performed by the Super Users for the upgrade of the blood bank software Medinfo Hematos IIS from version 3.8 to 5.0:
Processes and Software Building—Part Three
This is an updated version of a previous post.
Using the current state to build a new work flow can be a difficult task and balancing act. If one changes it too much, it may be difficult for the staff to cope. If too little, then why bother at all? Still, we had to take the time to analyze our current system and identify areas of improvement. When building a new computer system, we didn’t want to capture our current system with its flaws in concrete. Buying a new system is costly and it would be very hard to change it again, This had to be done right.
Also, whether or not you have a pre-existing software may affect your choices. In my opinion, it is easier to learn something new than to make some changes to a system that everyone has already learned. Learning is easier than unlearning and relearning.
First, I studied the new system’s capabilities and took note of the features I would like to adopt to improve the current processes. I did this especially at the critical control points. I also studied our incident reports: where had there been nonconformances? How could I change things for the better, i.e. with increased safety and compliance to international standards?
I did not want to throw out a successful manual system, just to optimize it. I tried to pick out those manual processes that worked and build those into the new workflows. What I wanted was a system recognizable and familiar to the staff but with enhancements with the least amount of change to reach our goals.
Although the vendor did some initial testing, this was insufficient to accept the system. I didn’t want the vendor to just show me some scenarios that they concocted. I was always suspicious why the vendor chose these examples and not others. Could it be that the other processes did not work as desired? I always insisted that I give the vendor representative scenarios and have them show me how the system reacted.
It is daunting task to know what settings to make. At one of my previous institutions, the administration recognized that they needed additional expertise from someone experienced in the new system. They hired an outside firm in addition to the software vendor. Still, even this was not sufficient to make the proper settings and testing. We had to rely on ourselves!
Ultimately, the Laboratory had to thoroughly test the system, The only way to do this was to use our own resources. Only we could test its actual functionality to the proper degree to ensure safety. Still, where could we get the resources to do this? Outside consultants were very expensive, especially if they have to live on-site for extended periods. The only answer was to make use of our internal resources, i.e. our staff.
In old days of only polyclonal reagents, QC of reagents took significant time. This has been simplified and easier since the introduction of monoclonal cocktail reagents.
Controls may be explicit (a specific control provided by the manufacturer) or implicit (implied by at least one negative reaction in the well of a gel card).
In order to properly interpret test results:
Make certain test results meet the criteria for interpretation. Do not accept negative results for IAT typing if DAT is strongly positive (blocking antibody).
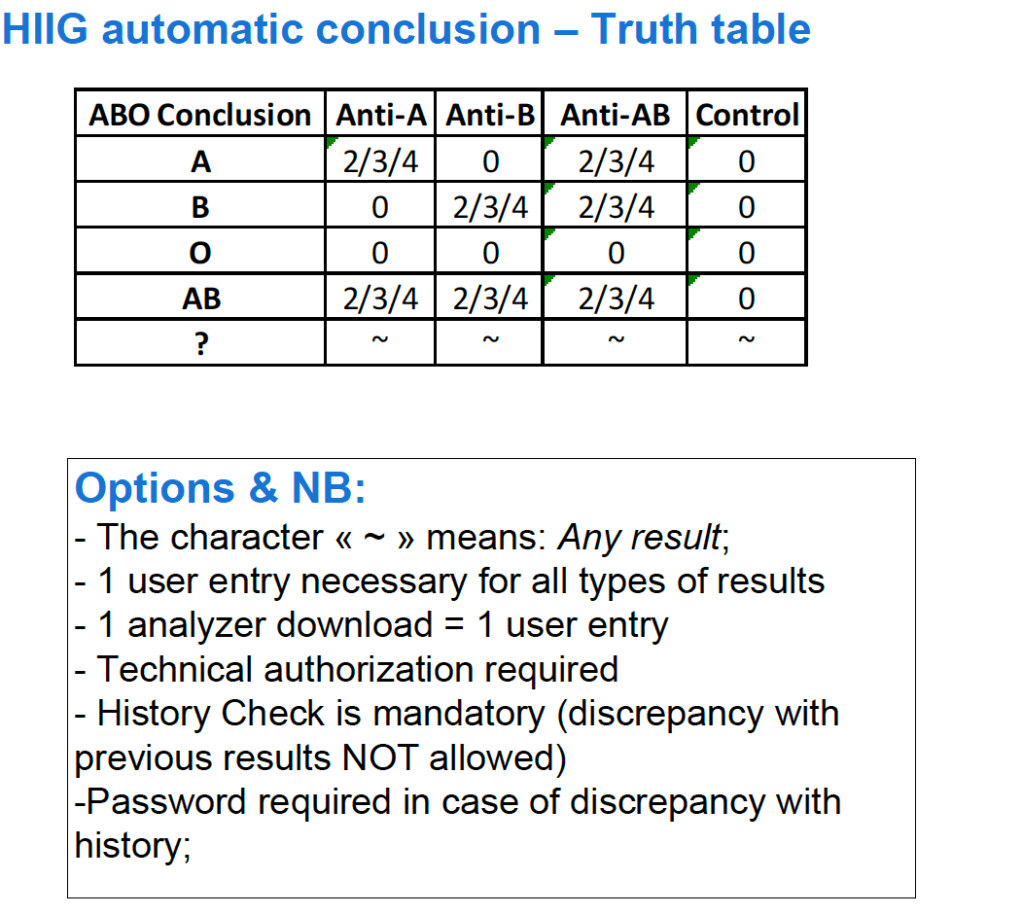
For both manual and automated tests, you can build the control criteria directly into your blood bank computer system’s truth table of results. This way the system will enforce the criteria and prevent false interpretations:
Example of control for ABO typing:
This is a revised version of a previous post.
This is a revised version of a previous post.
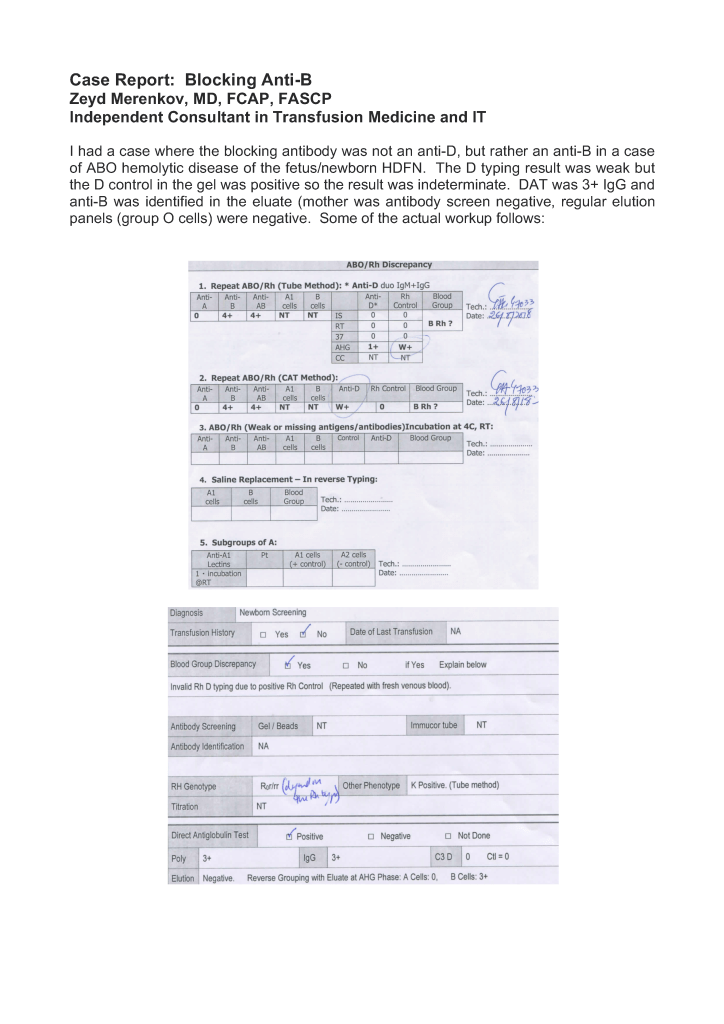
If there is strong antibody binding to an RBC, this may interfere with a typing reagent attaching to the cell and cause a false-negative, i.e. a “blocking” antibody. Such cells may interfere with the indirect antiglobulin test IAT, i.e. the antibody screen. The autocontrol and direct antiglobulin test DAT will be strongly positive.
The manufacturer’s instructions for using its reagents should be strictly followed in the presence of a strongly positive DAT. If there is no reaction with the typing reagent, the result must be indeterminate.
One could try a (relatively) nondestructive elution method such as gentle-heat elution to remove some of the antibody and then retype the cells. I have found this to be a simple and effective method for my staff to use. Just remember that despite being “gentle,” there will still be some hemolysis present, but here it is the cells we are trying to save.
Usually, we find this situation in a neonate born of a mother with anti-D. The baby has a strong DAT but the D typing is negative. Check the D control carefully: if it is positive, the result is indeterminate, try another method. Usually gel/glass bead methods are subject to less interference. Finally, there is always the classic saline anti-D!
In Medinfo software with a blocking antibody, a nonnegative control will trigger a manual review of the results. There will be no automatic release.
Here is my process for handling blocking antibodies, which I set up for HMC Doha:
INTERIM POLICY: ANTIGEN TYPINGS IN PRESENCE OF STRONGLY POSITIVE DIRECT ANTIGLOBULIN TEST (DAT): RULE OUT BLOCKING ANTIBODY
Principle:
Antigen typing of cells with large amounts of coating antibody (i.e. strongly positive DAT 3-4+) may not always be possible because the bound antibody may block available antigen sites. This policy is to clarify how to recognize and handle such situations.
Policy:
References:
One has to learn when enough is enough. There are times when there are staff shortages but the conscientious staff wants to be the Super-Tech and handle all the work, whether or not there are sufficient resources. This is a big gamble, and there may be serious consequences for the over-achiever and for the patient.
Anecdote #1: Chicago Blizzard of 1979 (13-14 January):
When I was in my residency training in Chicago, I was in the blood bank during the blizzard of January, 1979. The following tragedy occurred.
Suse was one of the best blood bank technologists that I have ever known, extremely conscientious and very meticulous—and very fast at doing things. She was a workaholic. Suse’s whole life centered on her job at our academic medical center—so much so that she had an apartment near the hospital complex. In mid-January, a snow storm was predicted with an estimated snowfall of about 5 cm. total. Actually, that night a blizzard developed and around a meter of snow fell with white-out conditions and zero visibility. Preoperative patients had been admitted the night before based on the low snowfall prediction.
The next day was chaos. Essentially only staff who lived near the hospital complex could report to work. Suse came in and saw all the pending preoperative blood requests. She decided to “double-up” and work on two cases at one time. In the rush, she mixed up test tubes and issued ABO-incompatible blood for a surgical case. The surgeon noted the abnormal oozing of blood at the operative site and stopped the transfusion. Hematuria developed, but the patient survived.
Suse was suspended pending investigation. Based on her excellent work record, she was offered to return to work. Unfortunately, she became very depressed and was afraid to return since she feared she would make another mistake. She never worked in the blood bank again.
Anecdote #2: Shortage of Blood at Major Hospital:
1991 in another country, a large hospital complex was suffering a shortage of blood. A large number of donors were called and the available staff were overwhelmed with work. One donor phlebotomist decided to collect whole blood from two different donors simultaneously and in the confusion, mixed up the sample tubes for donor marker testing.
Unfortunately, one of those donors was HBsAg positive, but with the specimen mix-up was marked as negative. The unit of blood was transfused, and the recipient developed fulminant hepatitis B and died.
Analysis:
In both these systems, there were processes in effect not to work on two patient specimens or collect two donors at one time, but the staff took short-cuts.
No one is super-human. Don’t try to cut corners and handle more than one patient at a time. Your intention may be good, but you will be judged by the consequences. No one will care about the extenuating circumstances. You will be blamed. I tell my staff that if they cannot handle the workload, they should contact me as the Division Head, Transfusion Medicine, to triage the cases for them. My role is to bring these events to the higher authorities to get the resources we need to do the work properly and safely.
This is an update of a previous post.
Principle:
All therapeutic apheresis procedures are potentially life-threatening and must only occur by an order from a transfusion medicine physician with experience/competence in such procedures.
Definitions:
Policy:
References:
This is a revision of a previous post.
Documenting Processes:
My previous post emphasized how important it is to map the current state across all processes as the first step to optimize current operations and prepare for a new computer system.
One non-blood bank vendor submitted the following as a complete representation of all current processes—across more than 4,000 tests and hundreds of instruments:
This was the same for each of the tests in the different sections of the laboratory—be it blood bank, anatomic pathology, chemistry, hematology, etc. I was flabbergasted! What were we paying for?
As Head of the Laboratory Information Systems, I rejected this. I would have been ashamed to submit this to a client as a sufficient current state. Even more astounding was the fact that that vendor actually mainly used the same four-step flow chart for the tests in their new computer build!!
As painful and time-consuming as it is, one must develop a specific flow for each process. This could include:
When we built our first dedicated blood bank computer system, the company would take a module and completely map out the current processes collaboratively with me. After this, I analyzed the critical control points and started to map out the improved computer processes that would take over. I did not want to throw out the successful manual system, just to optimize it. After that we would build that those limited processes in the software and test it. If it failed, we would correct it, and the vendor didn’t charge us extra for the corrections. It was a beautiful collaboration.
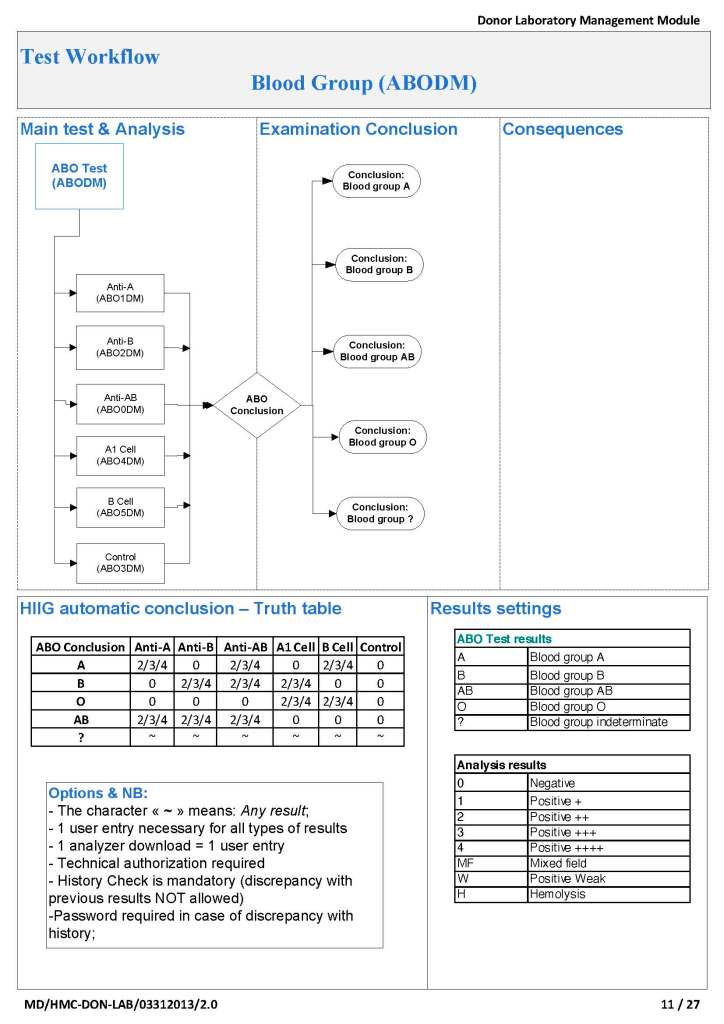
To illustrate these points, I am showing two process flows from our Medinfo Hematos IIG build: one for the ABO typing (forward and reverse) for donors and the other a complex testing algorithm flow for HCV donor marker testing. These are from previous builds and have been updated subsequently.
ABO Typing: Attachment One
This consisted of six individual tests forward (anti-A, anti-B, anti-A,B), two reverse (A1 cells and B cells) and a control. The acceptable tests for automatic typing were in {0, 2, 3, 4}, other results (mixed field, weak, 1+, hemolysis) required a manual interpretation. There is a truth table for interpretation of all six results together.
Donor HCV Testing: Attachment Two
This is a more complicated flow that includes multiple tests (HCV-antibody EIA, HCV-LIA, and HCV-NAT). Results may trigger reflex testing immediately (abnormal HCV EIA triggers HCV-LIA, abnormal HCV-NAT triggers HCV-LIA, etc.) or repeat testing after six months for indeterminate results.
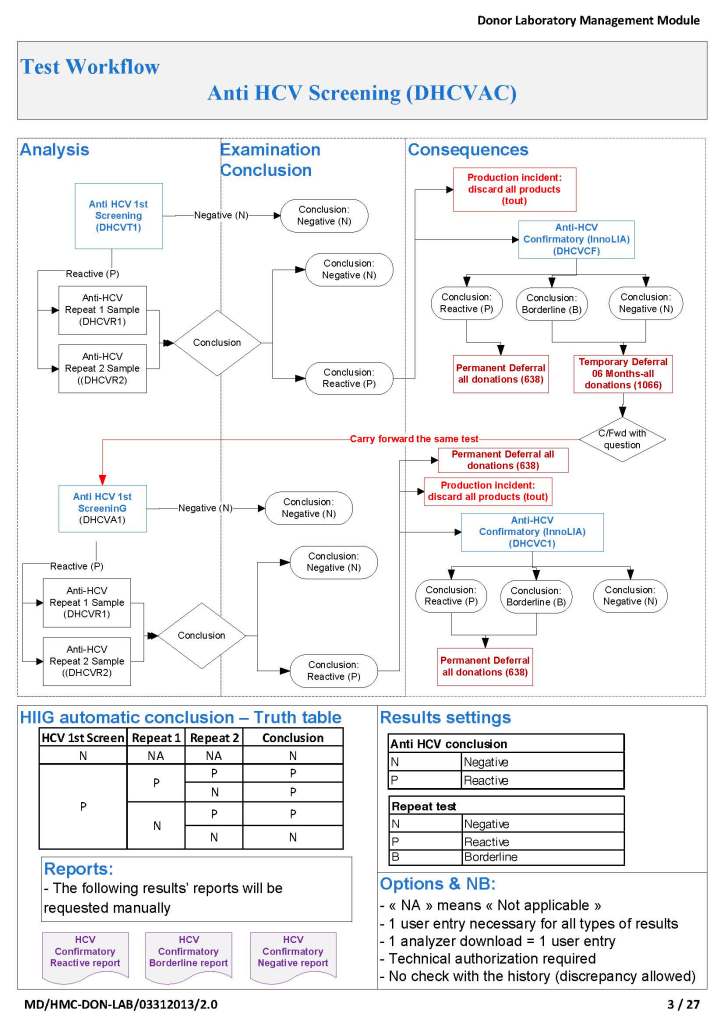
In each case, every possible result is listed and its interpretation and acceptability criteria.
In summary, it may take considerable time to map out all your processes, but this is time well spent and allows you build your system accurately. There will be few surprises this way.
Note: This is a repost.
I cannot emphasize enough proper technique in doing the washing during the elution process. We are usually concerned about too little washing and thus possibly residual reactions in the last wash. However, aggressive overwashing may remove the bound antibody resulting in a negative result.
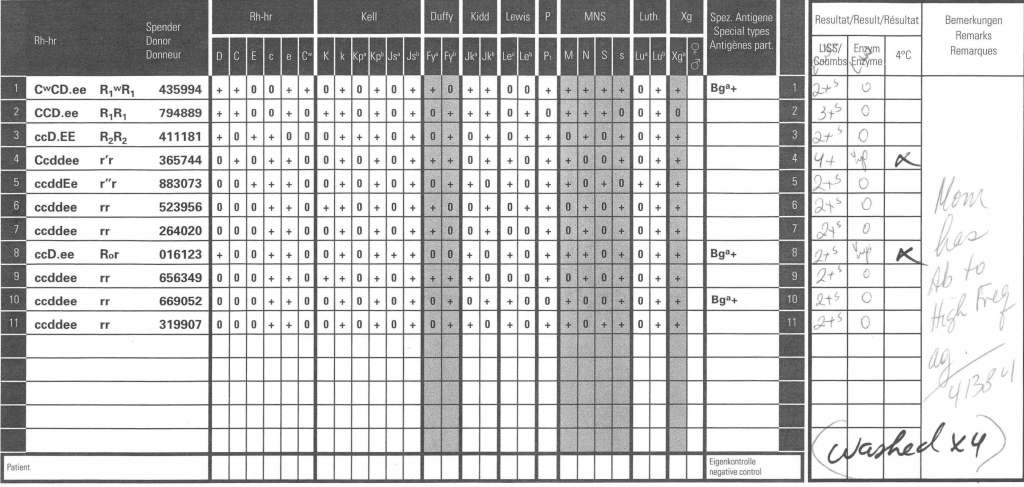
Here is an example of anti-PP1Pk (alias anti-Tja). The mother’s panel shows an antibody to a high prevalence/incidence antigen with negative autocontrol and no lability at enzyme phase:

The neonate’s DAT was weak positive at polyspecific and IgG monospecific phases. An eluate was performed. Here is the result after washing four (4) times:
Since 2 cells in the last wash were very weakly positive, the washing was continued for a total of 9 times with the following results:
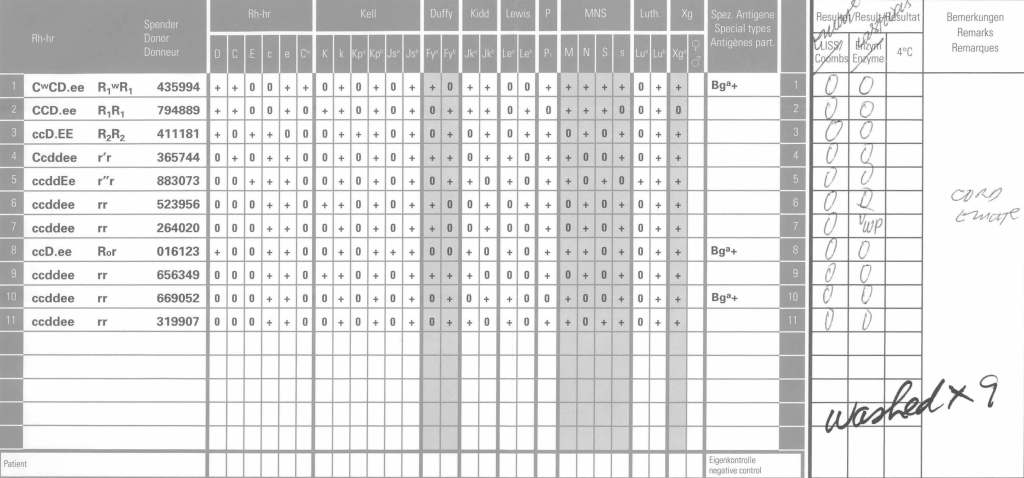
Even then there was very weak positivity in one cell, but the eluate was negative. We had washed away the attached antibodies.
My practice across the globe has exposed me different rationales to performing antibody titration. In my American training and practice (and also at international institutions following the American version of AABB accreditation), I only routinely performed titration of anti-D for Rh(D) hemolytic disease of the newborn and anti-A/anti-B for ABO-incompatible stem cell transplants AND ABO-incompatible renal transplants.
I have had heated arguments with some physicians who insisted they wanted titers for other antibodies. The AABB Standards do not require this but leave it to the discretion of the Transfusion Service Medical Director.
In my entire career, I never worked in a blood bank or blood center which had optimal staffing or resources. I focused on what was medically/technically necessary and even then still had shortages. If performing a test does not change the clinical treatment, why perform it unless you are doing a research project!
Titration is a time-consuming, and until recently, a tedious manual task. Recently some of the automated immunohematology analyzers offer a titration program. We used the Ortho Vision Max which could perform both IgG and IgM titers within one hour—walk away!! However, during that time, the titration procedure monopolized the analyzer.
Nowadays, low-anti-B-titer group A universal plasma and low-titer (anti-A and anti-B) group O whole blood may be offered as components. At HMC Qatar, a preliminary study showed about 50% of units could be classified as low-titer (defined as a saline titer <1:128). The amount of titration will require an automated analyzer.
The ABO-incompatible renal transplant program at HMC Qatar was modelled after Sweden’s Karolinska Institute. However the latter site performed manual IgG and IgM titrations using Biorad/Diamed gels.
I did not have sufficient resources to commit staff to manual titration at HMC so I did a comparison study between the Ortho Max and the Biorad manual gel methods. We were able to get good correlation and used the automated method for the transplant.
I still don not perform against performing titrations for antibodies other than anti-D. I always ask, ‘Does the titration correlate with clinical severity?’ Unlike anti-D, antibodies such as anti-Kell and anti-c may be low titer but cause death. Can anyone show me a definitive study that titers are useful except for transplants and Rh(D) hemolytic disease of the fetus/newborn?
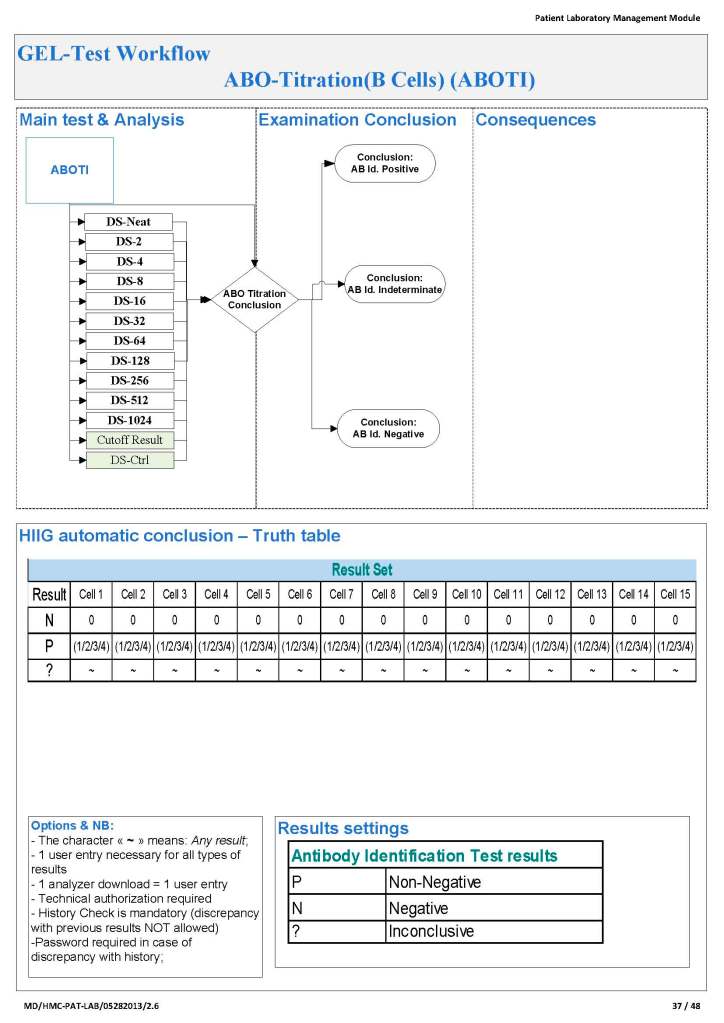
Since the method was working well on the Ortho equipment, I next established an interface to Medinfo. The test was performed separately for IgG and IgM antibodies. Medinfo recorded the reactions in all the wells. The last well showing a 1+ reaction was interpreted as the titer (e.g. if 1:64 were the last 1+ reaction, then the titer was 64 in Medinfo).
The Medinfo process is shown below.