Projective Exercise 1

As a transfusion medicine physician, I must know if I can trust my staff’s interpretation of immunohematology testing.  I may be called at night and they will provide me with results and I must use these to make a medical judgment.  If their interpretation is flawed, I might make a decision that harms the patient.

I really don’t like multiple-choice questions, but nowadays this is often the norm.  For my staff, especially senior staff and those who want to be promoted to senior staff, I have developed a series of projective exercises to help me understand their thought processes.

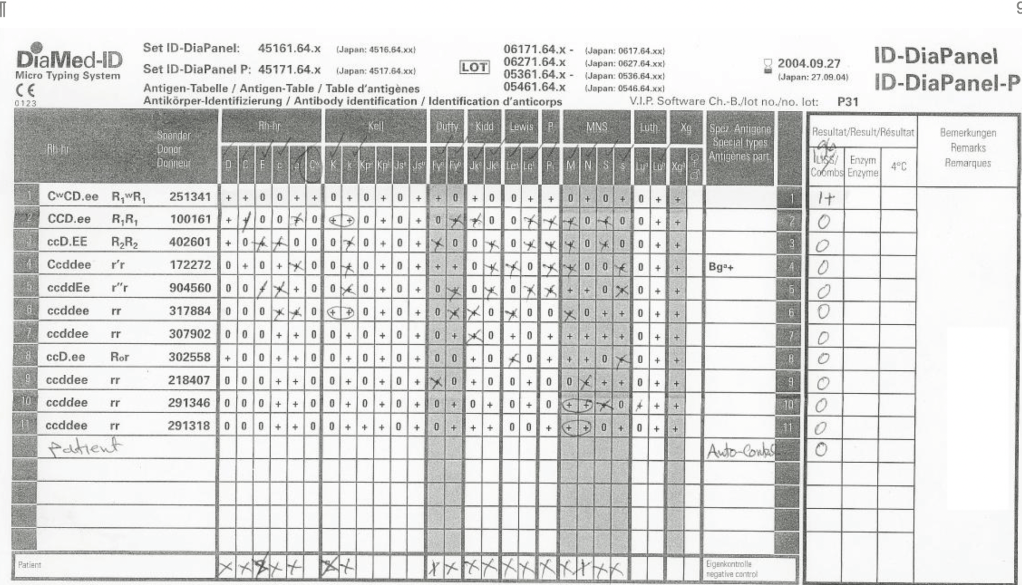
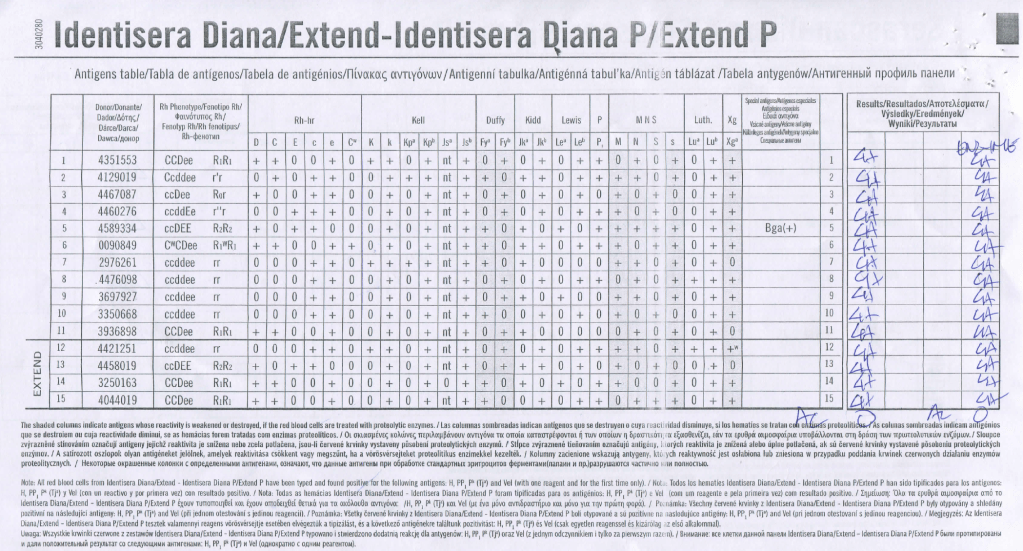
Here is a sample exercise.  I have the staff review this panel and tell me to interpret it:

Most of them answer that this is an anti-Cw without hesitation.  However, they are basing that on only one Cw-positive cell.

More astute ones indicate it might be anti-Cw but ask to test additional Cw-positive cells and perform an enzyme panel.  These are the ones that I will consider for promotion now.

Whole Blood

In my long career, there have been cycles in transfusion practice.  Today’s dogma becomes yesterday’s heresy and then later again the dogma.  Just consider the selection of blood components before the introduction of cyclosporine for intended renal transplant recipients.

In training, I was told NEVER, NEVER use the intended donor’s blood for the renal recipient.  This would immunize him against the donor tissue antigens and cause the transplant to fail.

Several years later after cyclosporine, we were doing a booming business of directed RBC transfusions from the donor to his/her recipient.

Just a few years ago, I used blood component therapy for all, especially trauma patients.  Give the victim what he lacks:  for oxygen-carrying capacity, RBCs;  for volume crystalloid;  for low protein albumin;  for coagulopathy FFP, factor concentrates, cryoprecipitate;  for thrombocytopenia, platelets.

Most recent studies now mention the danger of giving too much crystalloid, etc.  It talks about using fresh whole blood to provide all of the above in less volume.  Results from trauma and military studies are encouraging and may be better than individual component therapy.

There are special considerations for whole blood:

  1. 21-day outdate for the RBCs
  2. Platelet functionality limited after 7 days
  3. Use of group O, low-ABO-titer

Pathogen-inactivation of whole blood is CE-approved by riboflavin (Mirasol).  Terumo BCT is developing an exciting technology to first use Mirasol and then make components using the Reveos automated component system—RBCs, plasma, and platelets.  This is an ongoing project so for now the only CE-approved project is use as whole blood.  Such Mirasol-treated whole blood has been shown to prevent malaria transmission in Ghana.

From my review of the literature, these are my specifications as of this date 18/8/20:

  1. Use/ordering restricted to trauma and selected ICU/surgery suites
  2. Only male donors
  3. 7 day outdate
  4. Group O, Anti-A and anti-B IgM titers, both <= 1/256
  5. Leukodepleted < 1E6 residual WBCs

What level of anti-A and anti-B titers is acceptable?  The titer was set as low as 1:32 but at recent THOR meeting 1:256 has been used.  In Qatar in a pilot study, I found that about 50% of our donors had titers < 1:256.  The issue is that each time the donor presents himself/herself, we must repeat the titer—it is not stable.

Of course, performing even just a saline-titer is time consuming.  The only practical way for us in Doha would have been to use an automated titration option on an immunohematology analyzer—in our case, the Ortho Vision MAX, which could perform 1 titration run in about 30 minutes, and the instrument cannot be used for any other testing during the process.

I personally would perform leukodepletion to conform to CE, but you need a special whole blood filter that removes WBCs but spares the platelets.  Terumo BCT has such a filter that achieves <1E6 residual WBCs.  Never use a standard RBC leukodepletion filter since it will remove BOTH platelets and WBCs—this would defeat the purpose of using whole blood.

At HMC Doha, female donors were only used for packed RBC production—all plasma and platelets were discarded.  Some centers do HLA antibody screens and allow negative females to donate.

Finally, many groups do not leukodeplete at all.  I am concerned about the risk of adverse reactions and TRALI so I would conform to CE and do it.

Whichever conditions you stipulate, it is easy to create the process in Medinfo.  The most important thing is to know what you want to specify.

19/8/20

Handling of Placenta Previa in the Blood Bank

The following protocol is the one I made for National Guard Health Affairs in Riyadh and has been updated to include the use of a blood bank computer system.

Medinfo has an emergency mode that facilitates release of blood components even if all the usual testing is not available

If Medinfo software is used, one can write a protocol based on the diagnosis of placenta previa to automatically allocate the blood and keep it on hold at all times.

Ward Responsibilities:

  1. As soon as a patient with high-risk placenta previa is identified, order type and crossmatch for 4 units PRBCs.
  2. Immediately forward the specimen and its requisition to the blood bank for expedited processing.  BE CERTAIN TO INDICATE ON THE FORM AND/OR IN THE COMPUTER SYSTEM THAT THIS IS A PLACENTA PREVIA CASE!!
  3. Send a new specimen for crossmatching every 3 days until delivery.
  4. Phone the blood bank immediately when blood is needed for the patient before coming to the Blood Bank.  DO THIS BEFORE SENDING SOMEONE TO THE BLOOD BANK TO PICK UP THE BLOOD!

Blood Bank Responsibilities:

  1. Check the order comments for placenta previa.
  2. Handle all such requests as emergency or STAT.
  3. Enter a comment in the computer that this is a placenta previa case.
  4. Verify that the specimen has been properly collected and labelled.
  5. If the specimen is not acceptable, request new specimen.
  6. In emergencies, use emergency release/emergency mode in Medinfo.
  7. If specimen valid:
    1. Perform ABO/Rh typing and antibody screen if one is not available within the past 3 days.
    1. Check for previous history of ABO/Rh typing and antibodies—performed by blood bank computer system.
  8. Allocate 4 units, electronic crossmatch or full AHG as indicated by our rules.
    1. Provide antigen-matched units accordingly.
  9. When the ward calls that a placenta previa patient needs blood, immediately prepare the blood for release.  This is an emergency request of the highest priority.  VERBAL REQUESTS FOR BLOOD IN THESE CASES ARE ACCEPTABLE.
    1. Use emergency mode/emergency release in Medinfo if all the testing is not done or current.

My Opinion: Separate Transfusion Medicine from the Laboratory

Transfusion Medicine includes laboratory and non-laboratory functions.  The non-laboratory and purely clinical functions are unique and have no analogy within the general laboratory.

The transfusion service/hospital blood bank laboratory is the closest to a laboratory operation, but there is component modification and complex manual testing, especially for reference immunohematology testing.  The staff must make detailed manual decisions, the errors for which could be life-threatening for the patient.

The blood donor center manufactures a pharmaceutical, i.e. blood components with collection, donor qualification, donor abnormal results review, infectious disease marker testing, component production, and donor immunohematology testing—all subject to Good Manufacturing Practices.  Never forget:  Blood is a drug!!

No other laboratory section is directly responsible for treatment of critically ill patients.  Therapeutic apheresis is essential for organ and stem-cell transplants, nephrology, neurology, etc.  No other laboratory section is directly responsible for treatment of critically ill patients.  Transfusion Medicine physicians are functioning as intensivists.  There is no hiding in the laboratory from clinical medicine.

There may also be an industrial manufacturing plant to extract various blood derivatives (e.g. factor concentrates, albumin, Rh immune globulin, etc.)  This is pharmaceutical manufacturing on a large-scale basis.  There is medical, technical, and special administrative expertise.

Many functions may operate 24/7.  The transfusion medicine physician may be on-call for donor issues and review of complex immunohematology problems to acutely decide which blood component (and phenotype) should be given as well as review all adverse reactions to transfusion.

The unique blend of clinical skills is unlike anything else in the laboratory.  Also, those outside the blood bank rarely have the skills or judgments for the best course of action for transfusion medicine or for its operations.

The clinical transfusion medicine physician must make acute, life-threatening decisions unlike anyone else in the laboratory.  The blood bank technologist is at the cutting edge of the battle with his testing and interpretations.  No other area of the laboratory is at such risk for injuring or even killing the patient.  There is high stress and burn-out.

I have talked with many blood bankers and many seem to share the exasperation that the laboratory does not understand us.  The latter looks at blood bank testing like that coming off a hematology or chemistry analyzer—although patients rarely would have severe morbidity or mortality like the blood bank from errors in those analyzers.

No laboratory pathologist has the pressure of the blood bank physician on-call.  It really is 24/7 and requires a broad, clinical background to make the right decisions.  It is very stressful and does not permit a good night’s sleep.

Thus, I make my case to separate us from the laboratory.  We can form our own more effective administrative organization and optimize our own planning.  Regretfully, I have never worked in such an administrative structure.  I also am a realist that cost-containment nowadays makes it much less likely high administration would permit this change for a mere cost center.  This will probably never happen during my career.

Finally, Transfusion Medicine is an essential service.  Blood components are essential drugs.  The operations and staff must be free of political influences.  This is a service for the entire region or country like the fire department, civil defense, etc.

8/8/20

Neonate Born to Bombay Oh Mother

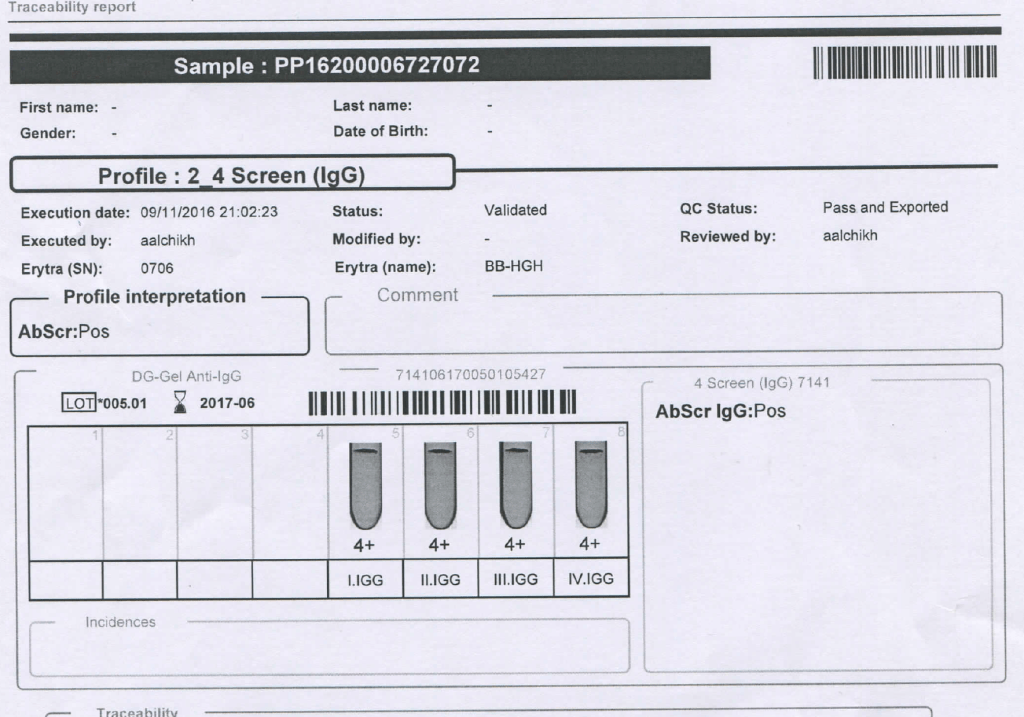
We had a mother (R1R1 K-neg) from Tamil Nadu who had several visits to our hospital.  Anti-H lectin was negative.  Here is a summary of her workup:

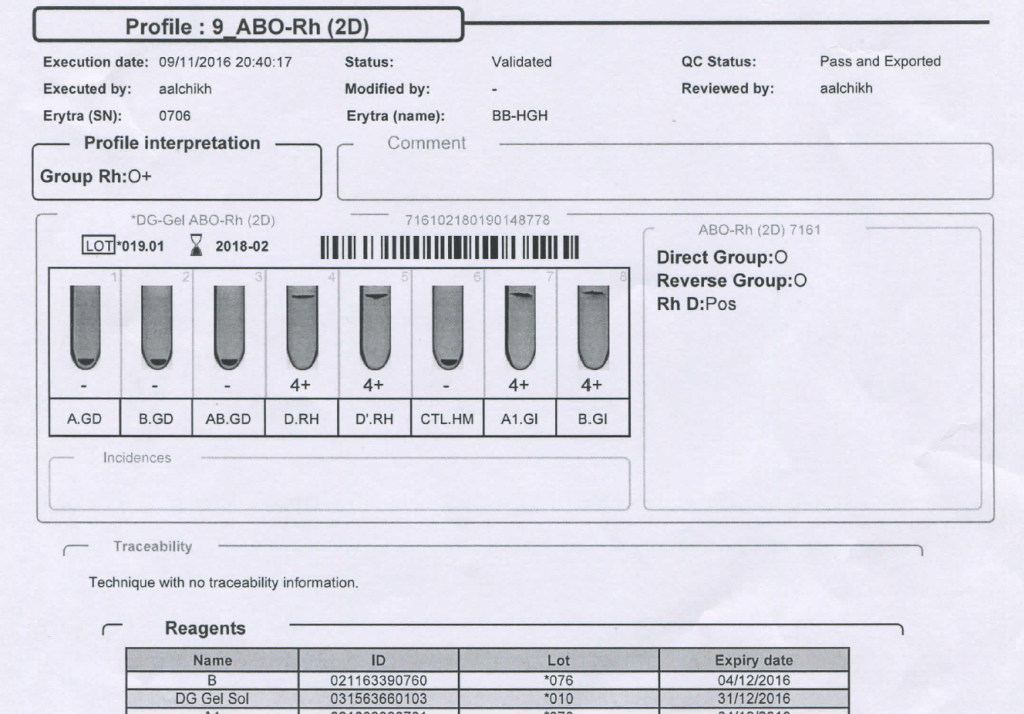
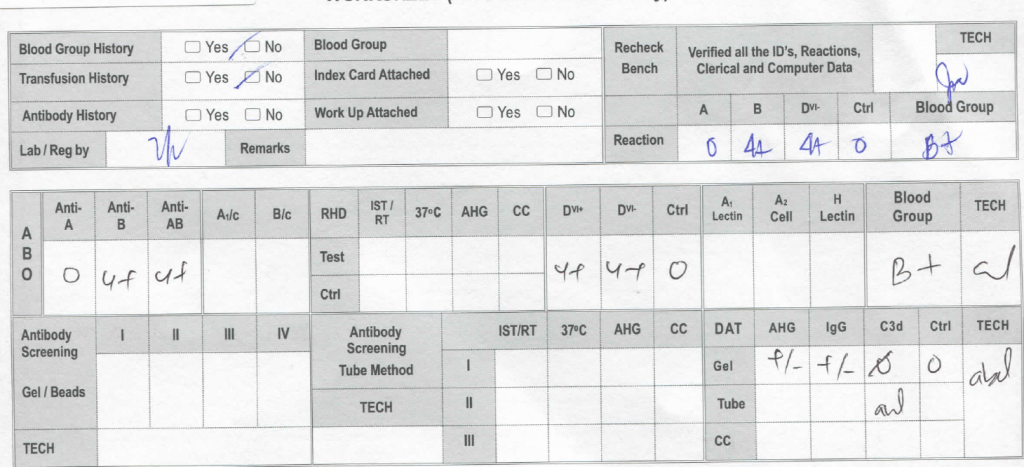
Mother’s ABO/D Typing:

Mother’s Antibody Screen:

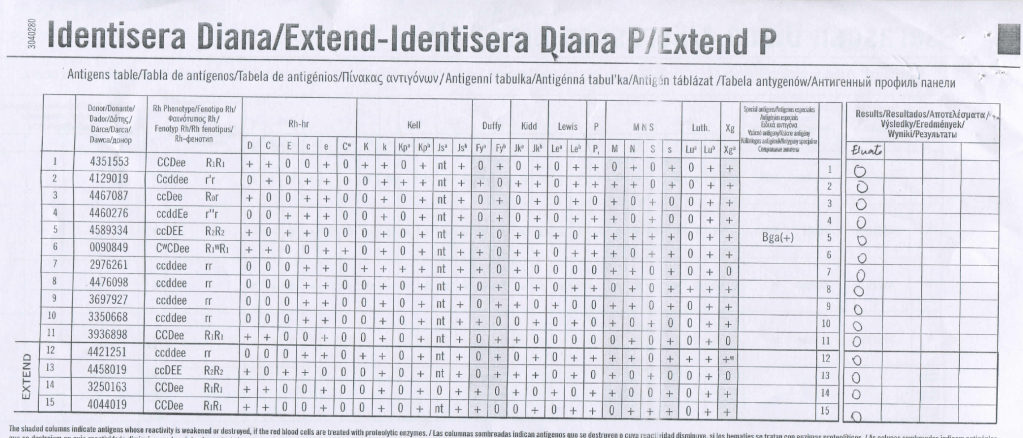
Mother’s Antibody Identification:

She gave birth to a baby girl, group B, R1R1 K-neg.  This is the neonate’s workup:

Despite the weakly positive IgG DAT, the eluate was negative.  The neonate was asymptomatic.

Anti-H is mainly an IgM antibody and does not cross the placenta, thus no HDFN was noted.

6/8/20

Time: Appreciating How Long Testing Takes

I have had many medical students, residents, and fellows rotate through my Transfusion Medicine department.  Hardly anyone has had any interest in making my discipline his/her career.  It is a required rotation or an “easy” rotation during which the trainee may take his vacation.  The trainee will cram for the examination and then promptly forget it.

I left practice in the USA in 1990, in what I consider the golden age of laboratory medicine.  We had supervisors for each laboratory section.  In the blood bank, we had many staff with SBBs or who were SBB students.  We were very self-sufficient in handling immunohematology problems except for rare blood types or antibodies to high incidence/prevalence antigens.

When I returned to visit my old laboratory.  I sensed a deprofessionalization of the laboratory and blood bank in particular.  Blood Bank now is a cost center, not an area of revenue.  Why hire experienced blood bankers for most hospitals?  Send the antibody workups to the Blood Center.  There are limited jobs for transfusion medicine consultants.  Minimize testing, don’t do extended antigen typings, etc.

Nowadays, I feel like one of the dinosaurs marching into oblivion as in Walt Disney’s Fantasia film, the section called The Rite of Spring.  Who will replace those of us retiring?  Have you ever noted the average age of attendees at the AABB annual convention?  I feel young when I go there (and don’t worry about the gray hair!)

I want to attract new doctors and scientists to Transfusion Medicine.  I really try, but most have no interest and look on their rotations as a necessary evil.

I have lowered my expectations for most medical trainees in Transfusion Medicine.  They don’t like it, they just want to pass it, and move on.  What must I impress them with for their future careers?  What is essential for them to remember?

I have had both pathology and non-pathology trainees.  Surgical and ob/gyn doctors used to spend one month whereas the hematology and pathology residents/fellows spent on average three months.  The few interested in the field might do multiple rotations.

I still gave them lectures on a variety of topics, especially how to transfuse blood components, basic ABO/Rh antigens, compatibility testing, and direct antiglobulin testing.  They would forget most of this, but I wanted them to remember TURN-AROUND-TIMES:

How long does it take to perform the test?

Find compatible blood?

Thaw the plasma?

Release a massive transfusion protocol shipment?

Complete a transfusion reaction workup before releasing more blood?

I am not discouraging people from entering the field, but I am a realist to know that few will share my passion for serology or want to take call on difficult immunohematology cases.  At least if they understand the pressure the technical staff are in and these turn-around-times this will make both their work as clinicians and mine as transfusion medicine more congenial.