Processes and Software Building 33: HBV Donor Testing

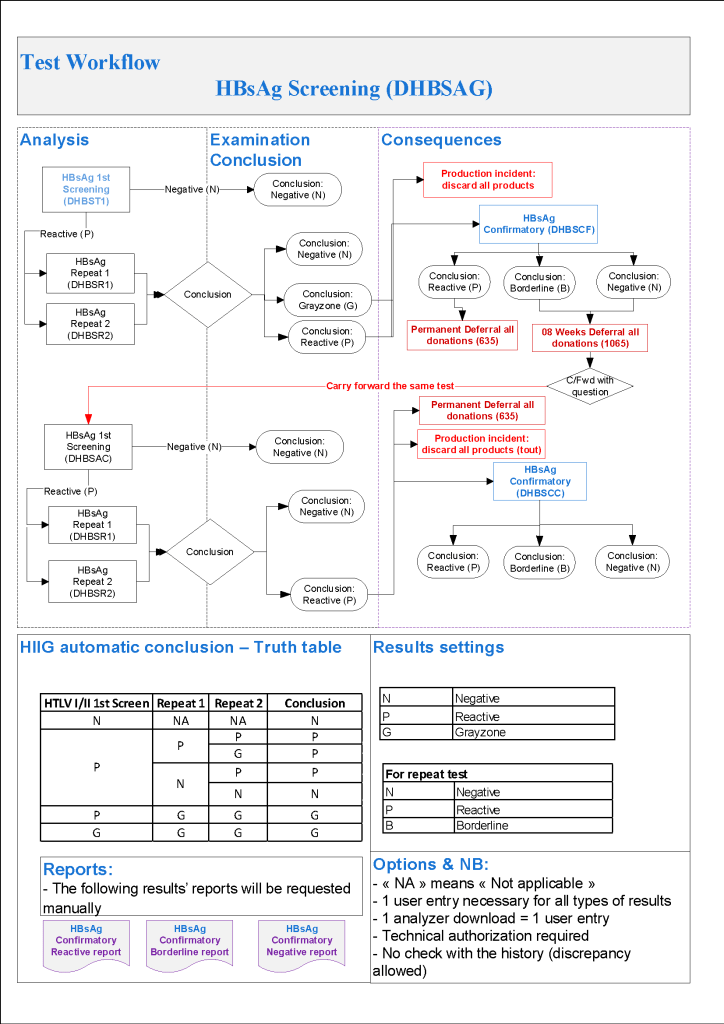
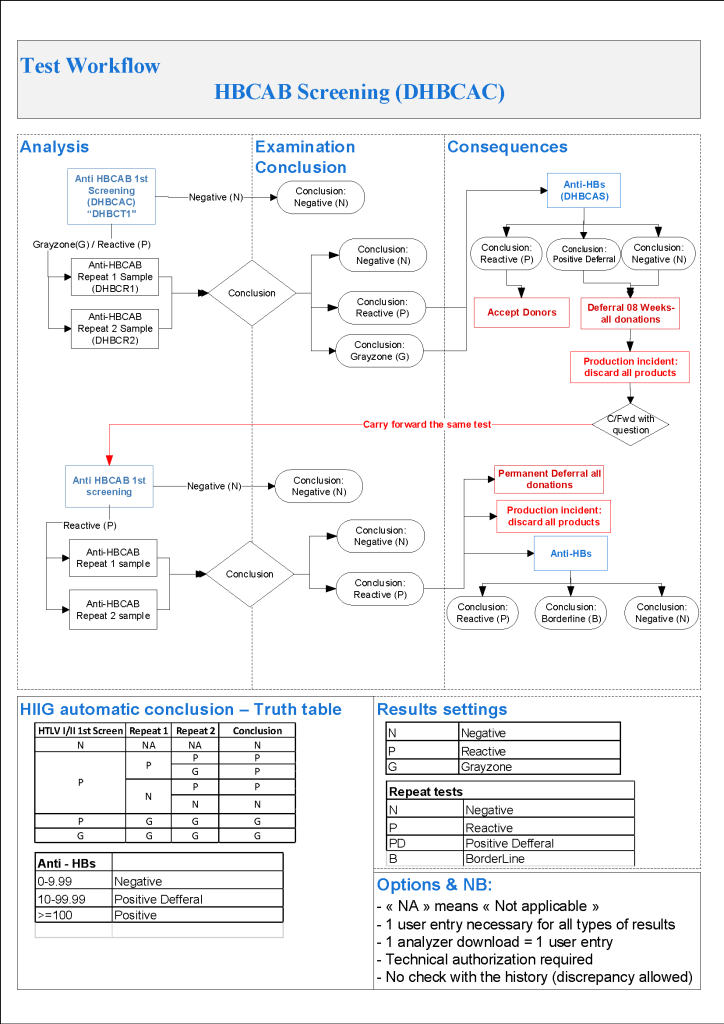
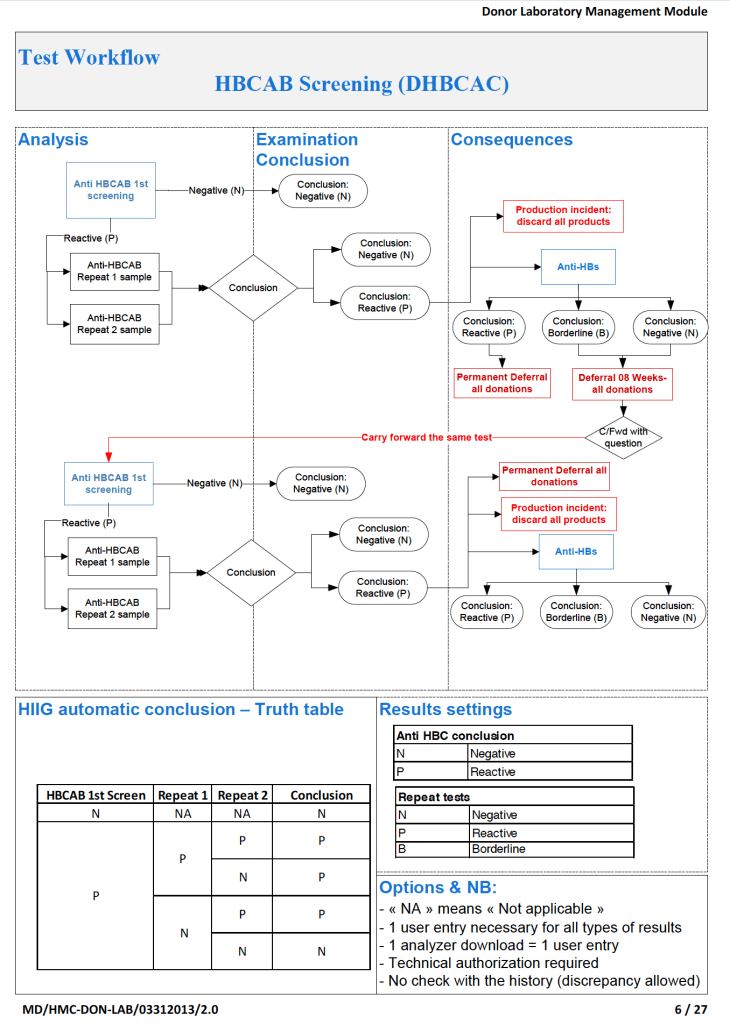
Hepatitis B donor screening consists of HBsAg and HBcAb for all donors, the latter to detect the window period.  In the USA, a non-negative HBcAb result will trigger a deferral.  In the Gulf area/KSA, there HBV was positive higher than in the West so there was a high rate of HBcAb positivity often from recovered HBV infection.

Here was my last algorithm before I left HMC Doha, which allowed use of donors with protective titers of HBsAb.  Note that the WHO cut-off for this is 10 IU/L whereas we used 100 IU/L as our threshold:

  1. Hepatitis B:
    1. HBsAg non-negative, then:
      1. HBsAg positive with HBsAg confirmatory positive, regardless of other results:  permanent deferral, refer to Infectious Disease clinic
      2. HBsAg positive with HBsAg confirmatory borderline or negative, repeat all HBV testing after 8 weeks
      3. HBsAg borderline:  repeat all HBV testing after 8 weeks
      4. HBV-DNA positive confirmed, regardless of other results:  permanent deferral, refer to Infectious Disease clinic
    2. If HBcAb positive, repeat after 8 weeks
    3. Repeat Hepatitis B Testing After 8 weeks:
      1. HBsAg positive with HBsAg confirmatory positive:  permanent deferral, refer to Infectious Disease clinic
      2. HBsAg positive with HBsAg confirmatory borderline or negative:  permanent deferral, refer to Infectious Disease clinic
      3. HBsAg borderline, permanent deferral, refer to Infectious Disease clinic
      4. HBV-DNA positive confirmed:  permanent deferral, refer to Infectious Disease clinic
      5. HBcAb positive or borderline with negative HBsAg and negative HBV-DNA:  review HBsAb level:
        1. If HBsAb level >= 100 mIU/mL (100 IU/L), donor may be reentered
        2. If HBsAb level < 100, then recommend to donor to receive booster HBV vaccine
          1. After HBV vaccine administration, retest after 30 days:
            1. If HBsAb level >= 100, donor may be reentered
            2. If HBsAb level < 100, donor is indefinitely deferred
      6. HBsAg, HBcAb, HBsAb all negative:  reenter into donor pool

Here is the HBcAb and HBsAb part of the algorithm:
Previously, we had we had disqualified any donor with a nonnegative HBcAb:
To Be Continued: 

18/8/20
Processes and Software Building 32: HIV-1/HIV-2 Donor Screening

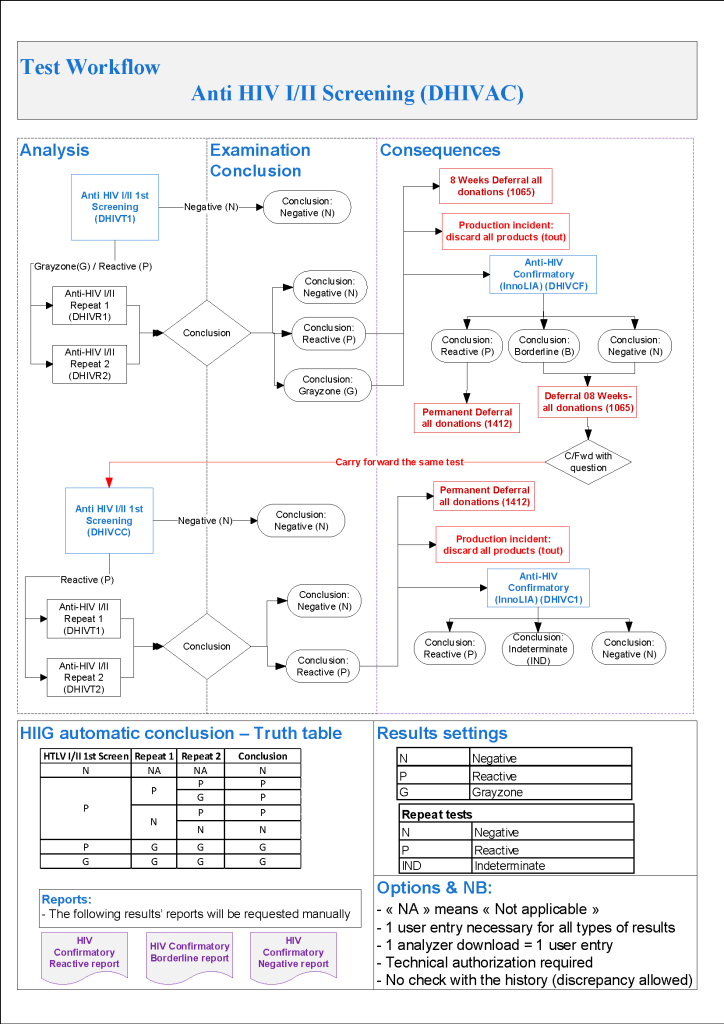
As I designed this in Medinfo, this is algorithm uses an HIV- /HIV-2 antibody EIA screening test, HIV p24 antigen test, and a confirmatory linear immunoblot assay LIA that can discriminate between type HIV-1 and type HIV-2.  If there is an indeterminate result, a repeat test is ordered after 8 weeks.  A reentry protocol is also included (1.6.3 below).

  1. HIV Testing:
    1. HIV-RNA positive confirmed, regardless of other HIV results:  permanent deferral and do HIV-InnoLIA, refer to Infectious Disease clinic
    2. HIV-RNA borderline:  do HIV-InnoLIA
    3. HIV-InnoLIA positive, regardless of other HIV results:  permanent deferral and refer to Infectious Disease clinic
    4. HIV-InnoLIA indeterminate:  repeat all HIV testing after 8 weeks
    5. HIV Ab positive with negative HIV-RNA and/or borderline/negative HIV-InnoLIA:  repeat testing after 8 weeks
    6. Repeat HIV Testing After 8 Weeks:
      1. HIV RNA positive and/or HIV-InnoLIA positive, regardless of other HIV results:  refer to Infectious Disease clinic
      2. HIV-InnoLIA and/or HIV antibodies indeterminate:  permanent deferral, HIV infection not confirmed
      3. HIV Ab negative and HIV-RNA negative and HIV-InnoLIA negative:  reenter into donor pool

This algorithm is represented in Medinfo as follows:

To Be Continued:

17/8/20

My Experience with Medinfo Hematos IIG Software for Patients and Donors

HMC Doha 2011-2020:  Set-up of both donor and patient modules including inter-depot transfer:

Donor:

Implemented COVID-19 convalescent plasma CCP production at HMC Doha over two-week period, February-March, 2020 including full integration with software

Donor collection, donor marker testing, donor immunohematology testing, inter-depot transfer between production site and hospitals and hospital-hospital transfers, ISBT labelling and specimen

Collection Interface (read-only) with Qatar Ministry of Interior to obtain both English and Arabic demographic information from donors

Establishing world’s first interfaces (bidirectional as required) with Terumo BCT Atreus and Reveos automated blood processing equipment, Mirasol pathogen-inactivation/platelet additive solution, Terumo Trima Accel donor apheresis machine, Terumo mixer-shaker donor collection device

Patient:

Implemented a CCP quarantine patient blood bank separate from regular hospital blood banks) for thawing and releasing of CCP plasma

Patient module including all compatibility testing, ABO/D typing, extended antigen typings, direct and indirect antiglobulin testing (antibody screens), antibody identifications, eluate, component modifications (thawing, pooling, aliquoting), interfacing of Diamed automated gel testing

Establishing algorithms for emergency release, electronic crossmatching, automated patient specimen titration with Ortho Vision MAX, prophylactic antigen matching, ensuring irradiation of blood components or use of pathogen-inactivation as required, allocation rules by algorithm, required and optional antigen matching in presence of antibodies

Development of bidirectional interface between Medinfo patient module and Cerner Millennium laboratory module (permitting order of transfusion tests and blood component orders in Cerner, transmission to Medinfo patient module for testing and allocation of components, and then sending test results and component status back to Cerner)

Common:

Developing current and future states to develop the workflows to prepare software processes

Validation testing, initial/user acceptance testing, follow-up validations

NGHA Riyadh 2009-2010:  Set up of both donor and patient modules including inter-depot transfer:

Donor:

Collection, marker testing, immunohematology testing, component production, inter-depot transfer between production site and hospitals and hospital-hospital transfers, ISBT labelling and specimens

Patient:

Patient module including all compatibility testing, ABO/D typing, extended antigen typings, direct and indirect antiglobulin testing (antibody screens), antibody identifications, eluate, component modifications (thawing, pooling, aliquoting), interfacing of Diamed automated gel testing

Please refer to my website https://drzeydbloodbank.com for specific posts on Medinfo software process building.  On the right hand side from the bottom TAGS menu, pick Medinfo Hematos IIG to see those articles.

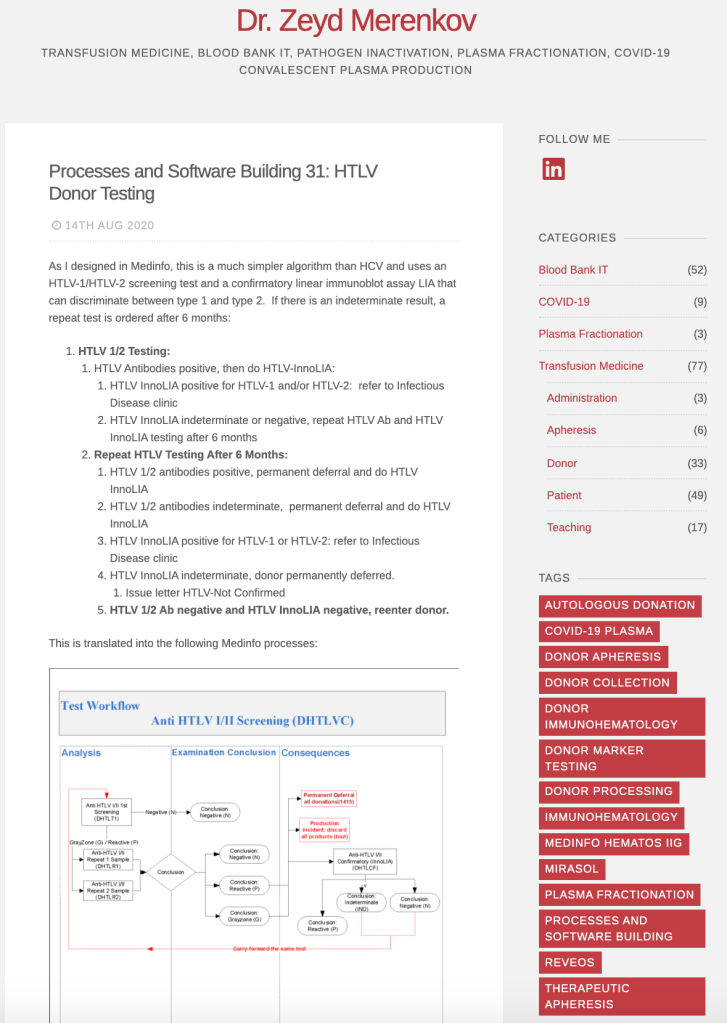
Processes and Software Building 31: HTLV Donor Testing

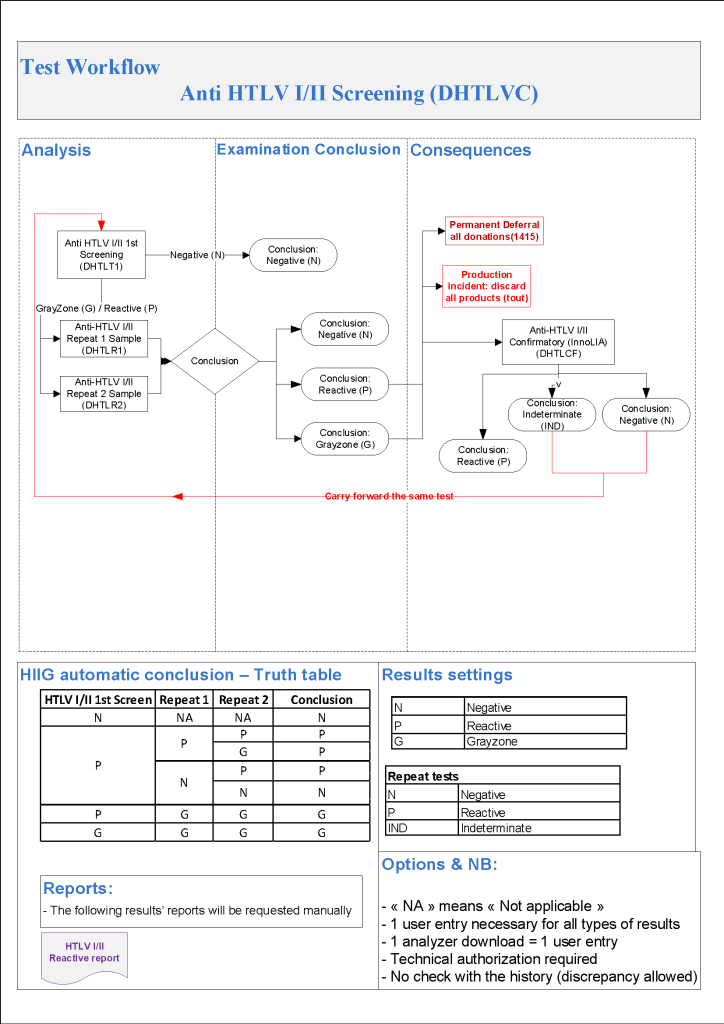
As I designed in Medinfo, this is a much simpler algorithm than HCV and uses an HTLV-1/HTLV-2 screening test and a confirmatory linear immunoblot assay LIA that can discriminate between type 1 and type 2.  If there is an indeterminate result, a repeat test is ordered after 6 months:

  1. HTLV 1/2 Testing:
    1. HTLV Antibodies positive, then do HTLV-InnoLIA:
      1. HTLV InnoLIA positive for HTLV-1 and/or HTLV-2:  refer to Infectious Disease clinic
      2. HTLV InnoLIA indeterminate or negative, repeat HTLV Ab and HTLV InnoLIA testing after 6 months
    2. Repeat HTLV Testing After 6 Months:
      1. HTLV 1/2 antibodies positive, permanent deferral and do HTLV InnoLIA
      2. HTLV 1/2 antibodies indeterminate,  permanent deferral and do HTLV InnoLIA
      3. HTLV InnoLIA positive for HTLV-1 or HTLV-2: refer to Infectious Disease clinic
      4. HTLV InnoLIA indeterminate, donor permanently deferred.
        1. Issue letter HTLV-Not Confirmed
      5. HTLV 1/2 Ab negative and HTLV InnoLIA negative, reenter donor.

This is translated into the following Medinfo processes:

To Be Continued:

15/8/20

Handling of Placenta Previa in the Blood Bank

The following protocol is the one I made for National Guard Health Affairs in Riyadh and has been updated to include the use of a blood bank computer system.

Medinfo has an emergency mode that facilitates release of blood components even if all the usual testing is not available

If Medinfo software is used, one can write a protocol based on the diagnosis of placenta previa to automatically allocate the blood and keep it on hold at all times.

Ward Responsibilities:

  1. As soon as a patient with high-risk placenta previa is identified, order type and crossmatch for 4 units PRBCs.
  2. Immediately forward the specimen and its requisition to the blood bank for expedited processing.  BE CERTAIN TO INDICATE ON THE FORM AND/OR IN THE COMPUTER SYSTEM THAT THIS IS A PLACENTA PREVIA CASE!!
  3. Send a new specimen for crossmatching every 3 days until delivery.
  4. Phone the blood bank immediately when blood is needed for the patient before coming to the Blood Bank.  DO THIS BEFORE SENDING SOMEONE TO THE BLOOD BANK TO PICK UP THE BLOOD!

Blood Bank Responsibilities:

  1. Check the order comments for placenta previa.
  2. Handle all such requests as emergency or STAT.
  3. Enter a comment in the computer that this is a placenta previa case.
  4. Verify that the specimen has been properly collected and labelled.
  5. If the specimen is not acceptable, request new specimen.
  6. In emergencies, use emergency release/emergency mode in Medinfo.
  7. If specimen valid:
    1. Perform ABO/Rh typing and antibody screen if one is not available within the past 3 days.
    1. Check for previous history of ABO/Rh typing and antibodies—performed by blood bank computer system.
  8. Allocate 4 units, electronic crossmatch or full AHG as indicated by our rules.
    1. Provide antigen-matched units accordingly.
  9. When the ward calls that a placenta previa patient needs blood, immediately prepare the blood for release.  This is an emergency request of the highest priority.  VERBAL REQUESTS FOR BLOOD IN THESE CASES ARE ACCEPTABLE.
    1. Use emergency mode/emergency release in Medinfo if all the testing is not done or current.

Processes and Software Building 30: Donor HCV Screening Tests

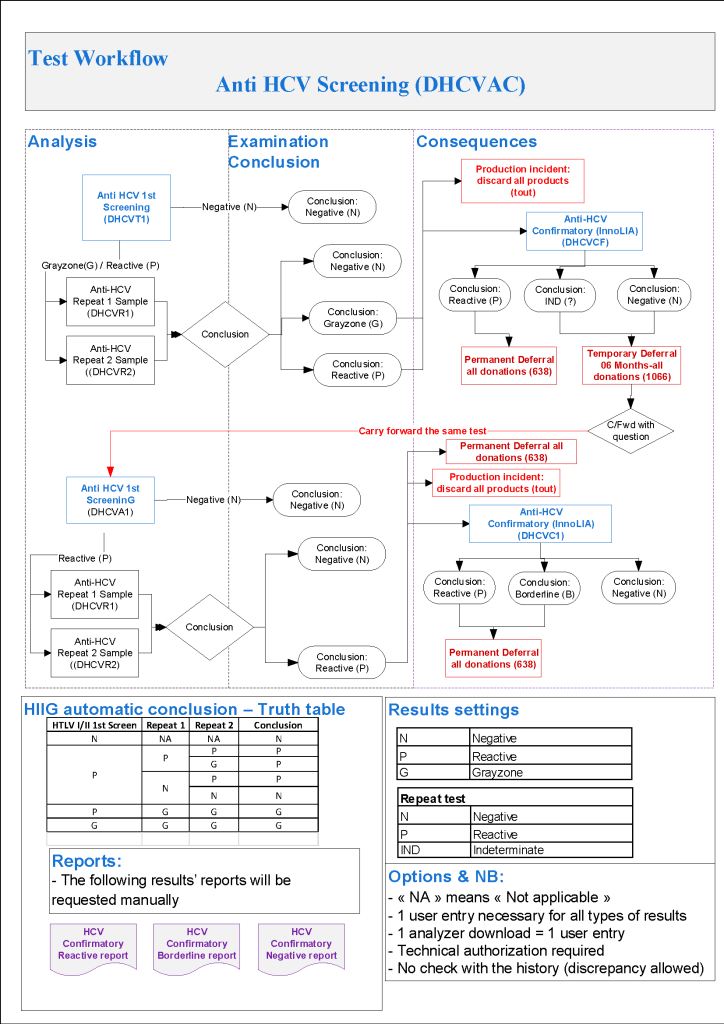
The testing algorithms may trigger additional testing, repeat of current testing at some future date, or permanent deferral.  One of the most complex processes is for HCV testing.  The following criteria are based on US FDA CBER guidelines, but are modified for the availability of test methodologies not licensed in the USA.

For HCV, we use the following testing in all donors:

  1. HCV antibody EIA
  2. HCV NAT
  3. If any of the tests are non-negative, then we do the HCV LIA immunoblot assay. 

HCV LIA is more sensitive than RIBA-3 (now no longer performed in the USA) but is not available in the USA.  This test has been incorporated into the testing algorithm from CBER:

  1. Hepatitis C:
    1. HCV-RNA positive confirmed, regardless of other HCV results:  permanent deferral, refer to Infectious Disease clinic
    2. HCV-RNA borderline:  repeat all HCV testing after 6 months
    3. HCV-InnoLIA positive, regardless of other HCV results:  permanent deferral, refer to Infectious Disease clinic
    4. HCV-InnoLIA indeterminate:  repeat all HCV testing after 6 months
    5. HCV-Ab positive, HCV-RNA negative, do HCV-InnoLIA:
      1. If HCV-InnoLIA positive, permanent deferral, refer to Infectious Disease clinic
      2. If HCV-InnoLIA indeterminate or negative, repeat all HCV testing after 6 months
    6. Repeat Hepatitis C Testing After 6 months:
      1. HCV-RNA or HCV-InnoLIA positive:  permanent deferral, refer to Infectious Disease clinic
      2. HCV-RNA or HCV-InnoLIA borderline:  permanent deferral, HCV infection not confirmed
      3. HCV-Ab positive or borderline without positive HCV-RNA or positive HCV-InnoLIA:  permanent deferral, HCV infection not confirmed
      4. HCV-Ab negative, HCV-RNA negative, HCV-InnoLIA negative:  reenter donor into donor pool

Note that indeterminate HCV results may be carried forward repeatedly by CBER rules but I decided to permanently defer the donor after 2 cycles of indeterminate results.  The donor must wait SIX MONTHS before the next round of testing.  Should he/she return before that time, those results may not be used for determining donor eligibility (unless the results have become clearly positive).

To Be Continued:

10/8/20