COVID-19 Convalescent Plasma Revisited:

In February, 2020, I developed a program for convalescent COVID-19 plasma at Hamad Medical Corporation in Doha.  In early March, 2020, our program started collecting CCP by apheresis.  We started before the software modifications were completed since there were urgent requests by the clinicians for the product.

I proposed the software specifications and our vendor Medinfo Hematos IIG implemented them within 2-3 weeks, after which they were implemented/validated

Thus, now we have 8 month experience has been 8 months since starting manually and more than 7 months using a specific modification of our blood bank software Medinfo.

A complete manual system was implemented with quarantined registration, screening, collection, processing, and release.  Only the donor marker testing was shared with the regular donors.  This was built into the computer system.

Upon review, these are my current thoughts on our processes:

  1. Actively monitor supply requests:  Keep good communication between ordering/treating physicians and apheresis unit to optimize the stock according to patient needs.
  2. Collect/process/release separately from regular donations.
  3. Use dedicated quarantine equipment (apheresis, processing, storage refrigerators)
  4. Collect manufacturer’s recommended maximum of plasma based on body weight.
  5. Use pre-donation screening to allow quick release of components and avoid wasting apheresis kits.
  6. Repeat testing on the new specimen collected at the time of apheresis donation.
  7. Process units by same processes used for normal donations, including pathogen-inactivation.
  8. Use standard processes for release of blood components to end-users.
  9. Restrict ordering to designated treating COVID-19 physicians (enforce in computer system)
  10. Restrict release of CCP to designated non-blood bank staff from the quarantine storage location (enforce in computer system)

Notes:

  1. Include COVID-19 antibody testing and establish a threshold level (e.g. 1:128 titer) for donor qualification.  Do not collect if low-titer or absence of COVID-19 antibodies.   Store titer information with donation record.  Add antibody results to donation records that occurred before the assay was available.
  2. Review of donor criteria:  are there increased risks using these recovered donors:  cardiac or respiratory risk?  Is there a way to continuously monitor CCP donors’s vital signs during the donation?
  3. Collect apheresis components only in pre-screened donors:  Apheresis kits are expensive, use them only if the donor is prequalified, continue to retest when actual apheresis donation occurs
  4. Allow use of units directly after collection/processing as long as the other donor processing steps have been completed (allow blood bank computer system to use pre-donation specimen for marker testing criteria).

Irradiation of Blood Components

Principle:

The use of irradiated components is to inactivate antigen-processing cells, which have been implicated in transfusion-associated graft versus host disease (TAGVHD).  This condition is may be fatal and has been reported in a variety of clinical settings, both in immunocompromised and immunocompetent hosts.

Since we pathogen-inactivate platelet components, we are only irradiating RBC components.  There is no need to irradiate any plasma components (e.g. FP24, thawed plasma, cryoprecipitate, or cryo-poor plasma.)

WARNING:  Do not irradiate stem cell units!!

Policy:

  1. Irradiation of packed RBCs will be given to the following patients:
    1. All candidates for stem cell transplantation SCT or patients post-SCT
    1. All severely immunosuppressed, excluding AIDS patients including:
      1. Congenital immunodeficiency states
      1. Intrauterine (i.e. fetal) transfusions
      1. Premature (less than 1500 grams or 28 weeks gestation) infant transfusions
    1. Neonatal Intensive Care Unit patients
    1. All hematopoietic tumors, including
      1. Hodgkin’s disease/lymphoma
      1. Non-Hodgkin’s lymphomas
      1. All acute leukemias
      1. Myelodysplastic states
      1. Myeloproliferative states
      1. Histiocytosis X, Langerhans histiocytosis
      1. Aplastic anemia
    1. All recipients of directed donations of any type, i.e. apheresis or components prepared from whole blood
    1. Recipients of HLA-selected platelets or platelets known to be HLA homozygous
  2. Irradiation Specification:
    1. Irradiate just prior to release if possible to minimize potassium leakage.
    1. Target 2500 cGy (rads) of gamma irradiation to the mid-plane of the canister of a free-standing irradiator is used or to the central mid-plane of the irradiation field if a radiotherapy instrument is used
  3. Using returned irradiated RBCs:
    1. If an irradiated unit is returned and otherwise meets re-release criteria, it may be used for up to 28 days after the irradiation or the normal outdate limit, whichever is less.
    1. For pediatric use (< 20 kg.), if the component was irradiated more than 24 hours previously, wash it prior to transfusion.

If you are uncertain whether to irradiate, ask the supervisor or the transfusion medicine physician.

References:

  1. Standards for Blood Banks and Transfusion Services, Current Edition, American Association of Blood Banks, Bethesda, MD, USA.
  2. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

4/11/20

Donor Unit Discrepancies

Principle:

All donor unit mislabeling is potentially life-threatening and must be stringently investigated as soon as possible after the discrepancy is detected.  Most importantly, if there is one error, there may be possibly ADDITIONAL donor unit errors (e.g. switch of donor tubes or units, etc.).  All donor units processed in the same batch must be also quarantined until the discrepancies are resolved.

The blood bank computer system will detect many errors;  however, if the donor unit or its samples are mislabeled in the beginning, these may not be detected.  Medinfo enforces checks on the final ISBT label and will compare current results to the historical record and will alert to any errors. Additionally, the use of ISBT specimen labels will obviate the risk of barcode reading errors.

Definitions:

Responsible blood bank physician:  specialist or consultant physician on-call at the time the discrepancy is detected

Policy Details:

The following steps MUST be performed as soon as possible:

  1. The Component Processing Supervisor or Senior Technologist must be IMMEDIATELY notified of any discrepancy.
  2. The Blood Bank Supervisor will inform the Division Head, Transfusion Medicine.  If the Head is not available, notify the Transfusion Medicine on-call.
  3. Quarantine ALL donor units collected and processed in the same batch.
  4. Obtain copies of all testing including photos of the gel/glass bead cards documenting the discrepancy.
  5. Obtain copies of all worksheets used in donor processing for the affected batch.
  6. Perform repeat ABO/D typing of ALL DONOR UNITS in the affected batch.  Any further discrepancies must be investigated and resolved.
  7. Identify all staff who were involved in handling the donor unit (phlebotomist, blood bank technicians processing and labelling the unit).  Identify those associated directly with the error.
  8. Submit all documents and photos to the Blood Bank Supervisor or designate.
  9. Prepare an occurrence/variance OVA report documenting all the data, findings, and interpretations.
  10. All investigations must be reviewed by the Supervisor, responsible blood bank physician, and one of the senior consultants.
  11. All such investigations must then be finally reviewed and approved by the Division Head, Transfusion Medicine or his designate.  Only when the issue(s) are completely resolved and investigation is approved may the donor unit be properly relabeled and released into available stock.  Also, only at that time may the other units in the affected batch be released into available stock!!
  12. Photograph the correctly relabeled unit and attach it to the other documentation of the incident.
  13. If the discrepancy cannot be resolved, ALL units in the affected batch must be discarded.
  14.  The implicated staff’s personnel record should be reviewed for previous errors.   Appropriate disciplinary action should be taken and documented in the personnel record.  If a verbal warning is given, it should still be documented in the written record.
  15. If there is a systemic cause for the error, appropriate measures should be taken to minimize reoccurrence.
  16. All actions must be in accordance with the institution’s policies and regulations.

2/11/20

Nipah Virus and Blood Donation

Principle:

Nipah virus NiV is a paramyxovirus that may cause a fatal encephalitis in infected patients.  Transmission to humans may occur after direct contact with infected bats, infected pigs, or from other infected humans.  ELISA, NAT, and direct culture may be used for confirmation of diagnosis, but there is no available licensed donor test.  The geographical distribution of this virus corresponds generally to the areas of malaria exclusion used for blood donor screening.  Most cases are fatal, and survivors may have neurologic sequelae.

The incubation period is 5-14 days with illness presenting 3-14 days of fever, headache, followed by drowsiness, disorientation, and confusion.  These findings may progress to coma within 24-48 hours.  Some patients also develop a respiratory illness.  Latent infections with subsequent reactivation of the virus have occurred months to years after exposure.

Policy:

  1. The current exclusion for travel to malaria endemic areas will be used to exclude donors with possible NiV exposure.
  2. Any donor with a history of Nipah virus infection will be permanently deferred.
  3. As per current SOP, any donor not feeling well must not donate blood or blood components.

Blood Bank Software is Dynamic, NOT Static

I was recently talking with one of the hospital software system administrators from my previous site.  He had originally worked on building the Medinfo system, but was then reassigned to the laboratory modules of the hospital information system.

His alarming comment to me was that the Medinfo build was completed so there was no need to worry about it now—it was finished.  I guess he was looking from the perspective of the general laboratory software.  There is no need to make major changes to the build, just update interfaces and troubleshoot.

I was surprised.  He had no idea of how many times we have to update the structure for new rules and regulations, and changes in blood bank practice—let alone emerging pathogens such as ZIKA, dengue, Chikungunya, and most recently, COVID-19.

My daily morning routine was to survey several blood bank websites with changes to blood donor criteria including US FDA CBER, read the transfusion journals (Transfusion, Vox Sanguis, etc.), AABB, and ASFA.  If there were any changes pertinent to our organization, I had to make interim policies and procedures, and finally prepare specifications for changes in the Medinfo software.

The Medinfo engineers would prepare flow charts of the proposed changes and implement them in a test environment for the Super-Users to test.  I had to prepare validation protocols for the testing, and then review the validation results and finally approve the adoption of the changes.

I cannot remember even a month going by without some revision in the donor protocols.  When COVID-19 came, I had to prepare a parallel, but separate, processing and allocation/release system.

This was a never-ending story that kept the Super Users and the local Medinfo engineers busy.  I always reminded the hospital information system staff that playing with blood bank software was like playing with fire:  there is a good chance you will get burned if you do not set it up properly.

31/10/20

Opinion: International Perspective

In all my years practicing medicine outside the United States, I have come to appreciate working with a diverse group of health care professionals from many countries and cultures and with many different primary languages.

I learned that there are many different international standards and not all agree with each other.  Yet, despite the apparent contradictions, they all work to improve patient care and were generally successful.  It made me reconsider my roots and think less dogmatically and be willing to learn from other perspectives.

This applies in many ways.  First, which English should we use?  Most people are at least somewhat aware of American English, but there are differences with British, Australian, and international English—even the term “blood bank” may have different meanings:  is it a hospital transfusion service, is it a donor center, or some combination of the two?

I have worked at many sites where I was the only person native in English.  I always tried to conceive how difficult it could be for someone non-native to understand and communicate in a highly technical and highly Germanic structured language.  I considered the scenario where I had to work in another language exclusively and perform all my tasks—I highly respect my staff having to cope with this.

English technical writing includes a lot of passive voice, subjunctive mode, perfect tenses, and participles.  How formidable a barrier are these to staff whose native languages may not use these structures?

I am not saying that English is the best language to perform the work in, but it is most prevalent one so everyone must cope with it.  I told many of my staff to learn German to better understand English grammar.

What bothers me is that certain software vendors and visiting lectures send speakers and staff who ONLY think in American English and American culture.  I can think of several anecdotes:

One speaker was talking about hyperlipidemia and used non-SI units.  He kept stating cholesterol > 200 and LDL-cholesterol > 120 to an audience who only used SI units.  Could the audience quickly convert to cholesterol > 5 and LDL > 3?  Did they know what a temperature of 104 F was 40 C?

Another speaker for a software company used an analogy of collecting maple sap and making maple syrup—in a presentation in the Middle East.  How many in the audience even knew what maple syrup is?

In building a series of software modules, some company staff used 24-hour clock and others used 12-hour clock.  It was chaos trying to define a 24-hour interval between the different modules.

Finally, I think of the Aesop’s fable about the mother who gave birth to a very ugly child, but to her, he was the most beautiful child in the world—so much so that she entered him into a beauty contest.  Well, each of us is the “mother” to our documents and memos.  The writing looks good to us and is perfect, but do our staff interpret it the same way we do?

I had my staff read my documents and then explain back to me what I was trying to say.  I was shocked at the differences in many cases.  After this, I always included a validation step to have other people read and interpret what I was saying—and correct any misconceptions in the writing before I finally released the document.

In summary, it is a whole new world outside the United States.  Don’t assume everyone thinks the same way or uses the same criteria to accomplish goals.  Be open to this and you will have a rewarding international career.

30/10/20

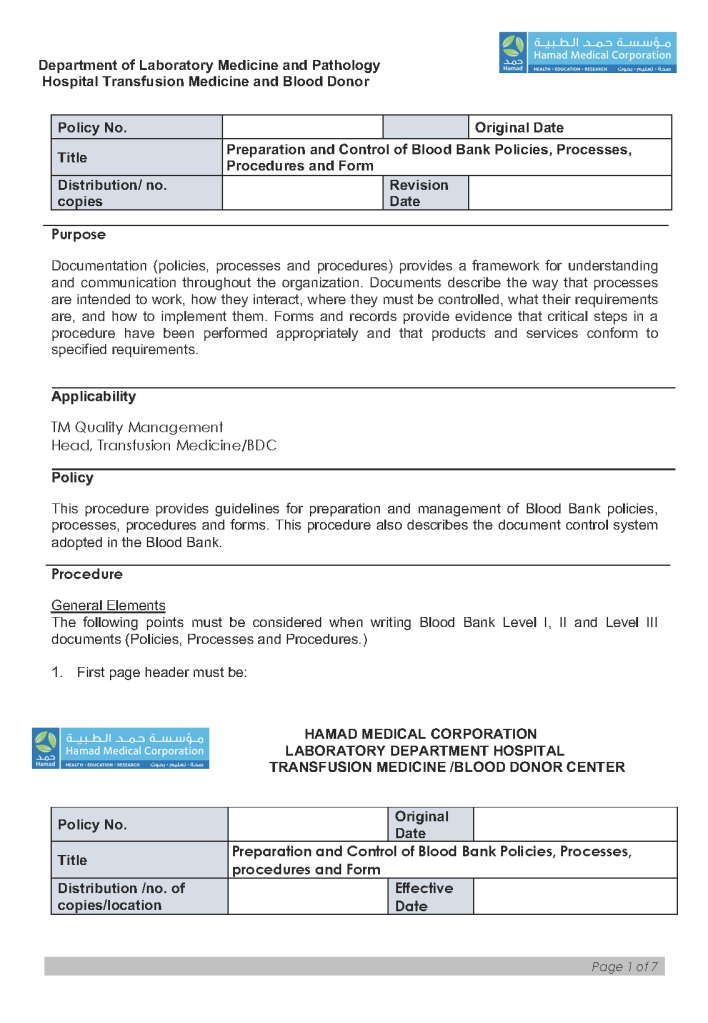
Document Specification

There should be a clear specification of how to prepare documents (policies, processes, procedures, and forms for Transfusion Medicine. The following is a draft document prepared by Transfusion Quality Management and myself for HMC in Doha. I want to thank Ms. Editha Durante, then Quality Manager and Quality Reviewer at HMC for all her work on this.

29/10/20

Directed Donations

Principle:

Directed donations are used for dedicated components from a particular donor for a specific patient.

Policy:

  1. All requests for directed donations must be specifically approved by one of the Transfusion Medicine physicians.
  2. Indications—patient has need of a rare component type, including:
    1. Antibody to a high-incidence/prevalence RBC antigen (e.g. anti-PP1Pk)
    2. Neonatal isoimmune thrombocytopenia or other platelet antibody situation (anti-HLA or platelet-specific)
    3. IgA-deficient plasma
  3. Other requests:
    1. If #2 above does not apply but someone wants to donate on behalf of a particular patient, the final decision to proceed will be made by the transfusion medicine physician.
  4. All directed donations must be registered as such in the Medinfo Hematos IIG computer system to ensure that the proper ISBT label is generated.
  5. Directed donors must meet the same eligibility criteria as regular donors.
  6. Special conditions apply to apheresis components from a dedicated donor:
    1. If a directed apheresis donor passes initial donor testing and is dedicated for one particular donor, then additional plateletpheresis donations may be accepted for 30 days without further testing.
  7. The platelet apheresis component may be directly released without further testing if it is an emergency situation.  Otherwise, we will proceed with full donor testing before release.
  8. Exceptions to the above policy can only be made by the Transfusion Medicine Consultants or designate;  all exceptions must be documented in writing.
  9. All RBC and platelet components from directed donations will be irradiated before release.

Please note:

  1. Plateletpheresis donations may be collected twice weekly from the same donor, 48 hours apart, for a maximum of 24 times per year.
  2. If more than 200 ml RBC loss occurs within an 8-week period from apheresis component collection, that donor must be deferred for 8 weeks.

Reference:

Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA

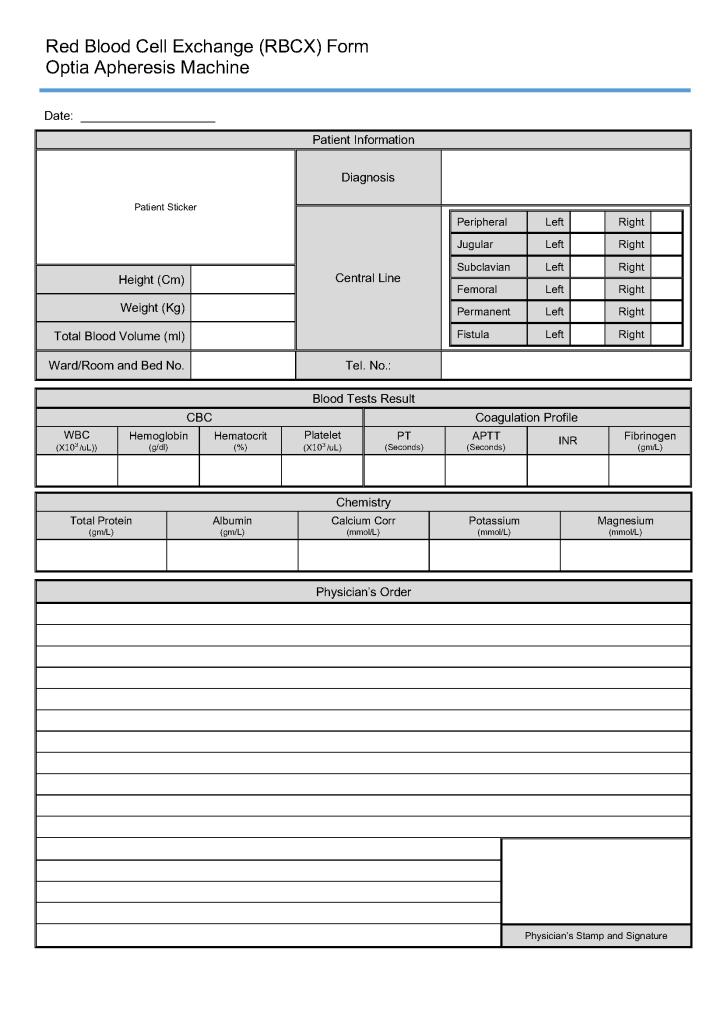
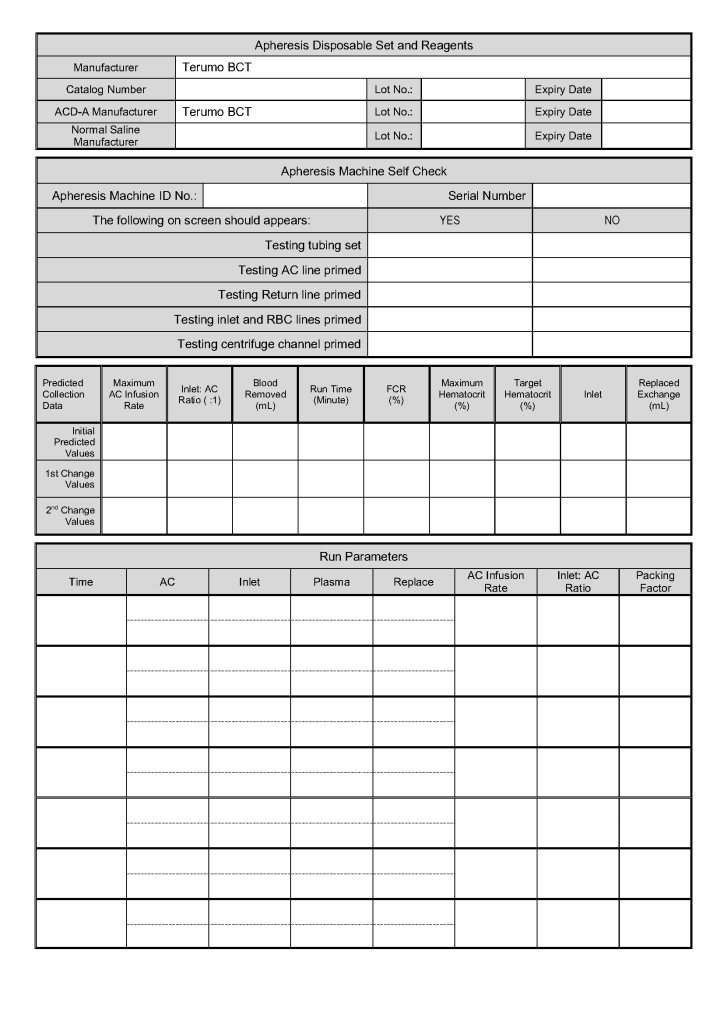
RBC Exchange Form

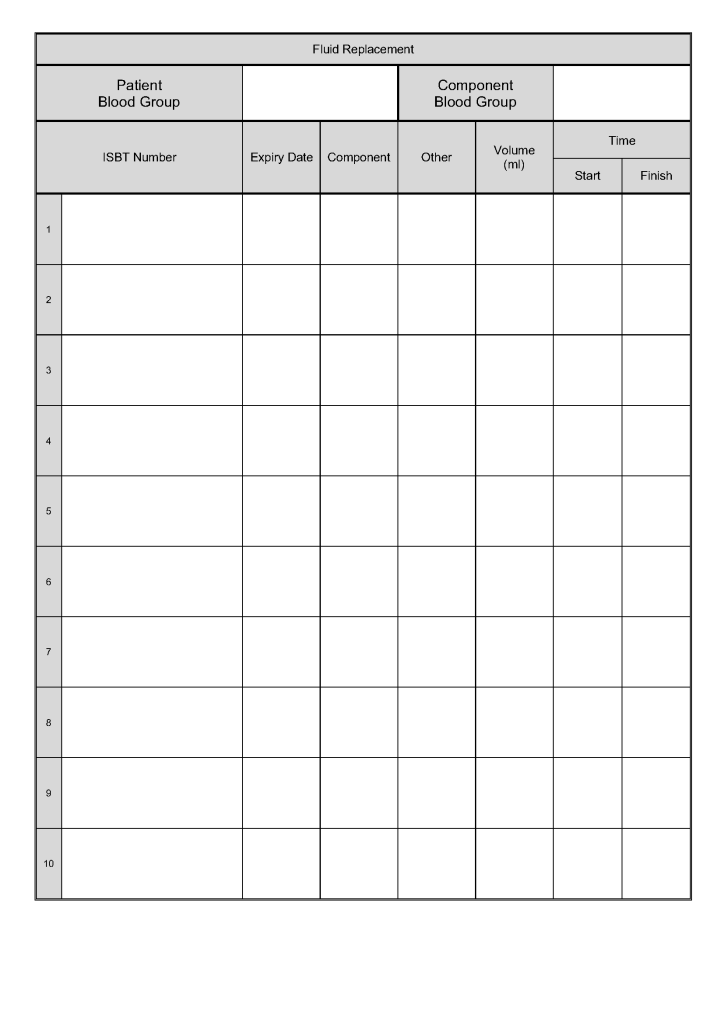
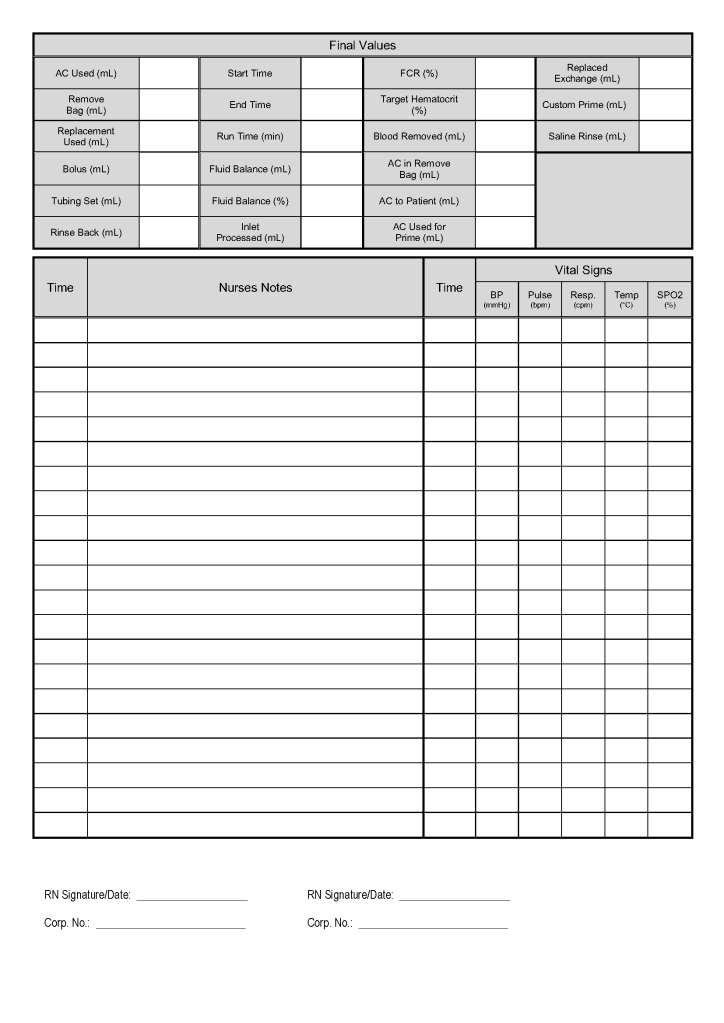
This was the RBC Exchange Form developed by my Head Apheresis Nurse Ms. Mini Paul and Dr. Saloua Al Hmissi at my previous position. It is easy to find all the important information and enter the parameters during the actual procedure: it does NOT require the apheresis nurse to flip back and forth and allows her/him to concentrate on the patient.

27/10/20

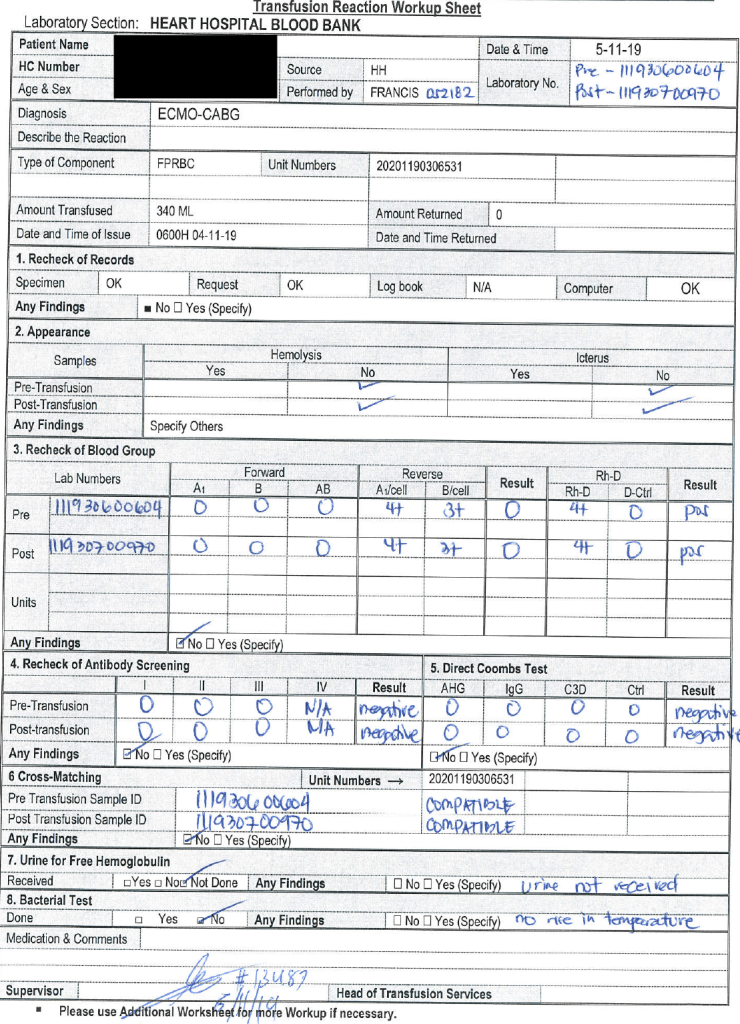
Transfusion Reaction Manual Data Collection Form

In my opinion, the key to using data effectively is to organize it efficiently.  A modern blood bank software like Medinfo is a great help;  however, a good manual system—if nothing else but a manual form during a computer downtime—is essential.  Also, a good manual system allows you to build an even better software!

Over the years of my practice at sites in the United States and the Middle East, the following form has emerged.  It started as a manual reporting form and was repeatedly updated to all the changes in the AABB Standards.  At my last site, it was used as a data collection form to present to the Transfusion Medicine Physician reviewing the final transfusion reaction workup.  Antibody results, elution, microbiology cultures, etc. would be attached as needed.  .   The actual transfusion vital signs and patient symptoms on a separate transfusion data sheet were also provided.

Like the computer system, this form enforces a consist set of testing be performed before submitting it for the final disposition for the case.  However, like all transfusion reaction workups, the transfusion physician is called with the data of the clinical symptoms, clerical check, DAT, repeat ABO/D typing, antibody screen, visual pre- and post-hemolysis findings so that within one hour the physician can rule out life-threatening hemolysis.

In a future post, I will explore the data entry and interpretative reporting performed in Medinfo.

26/10/20