Data Entry Verification

Principle:

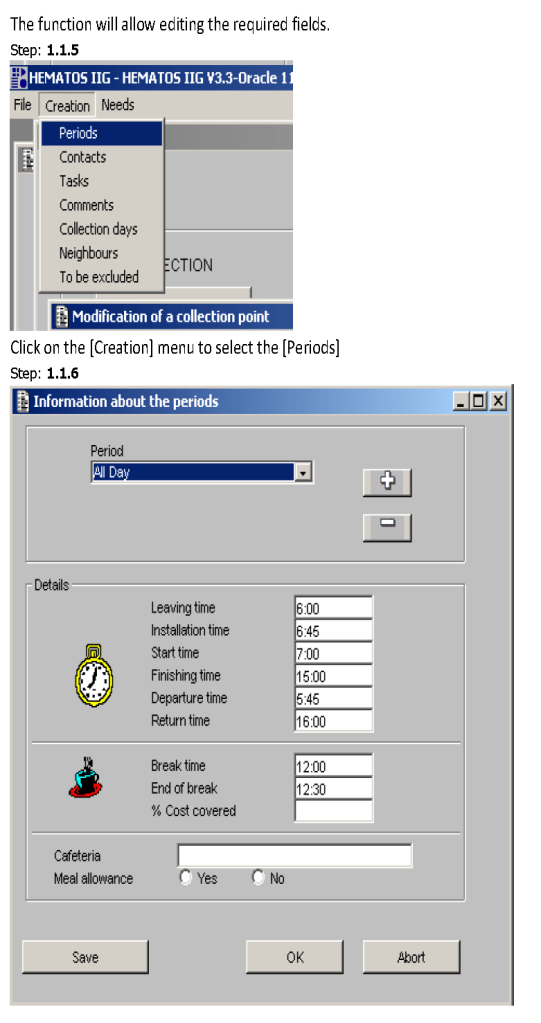
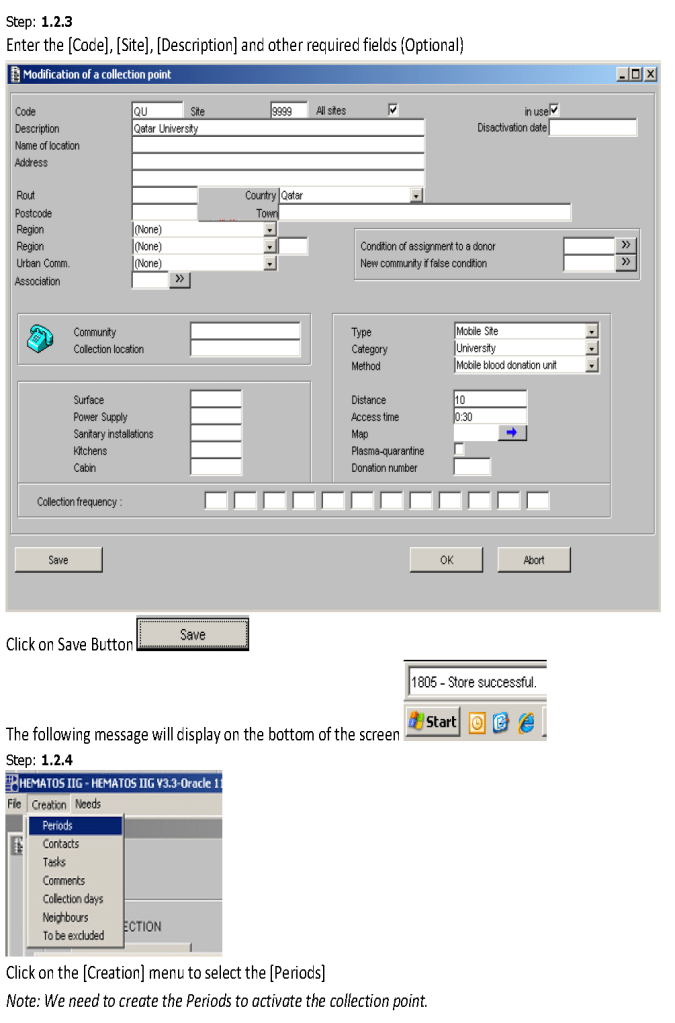
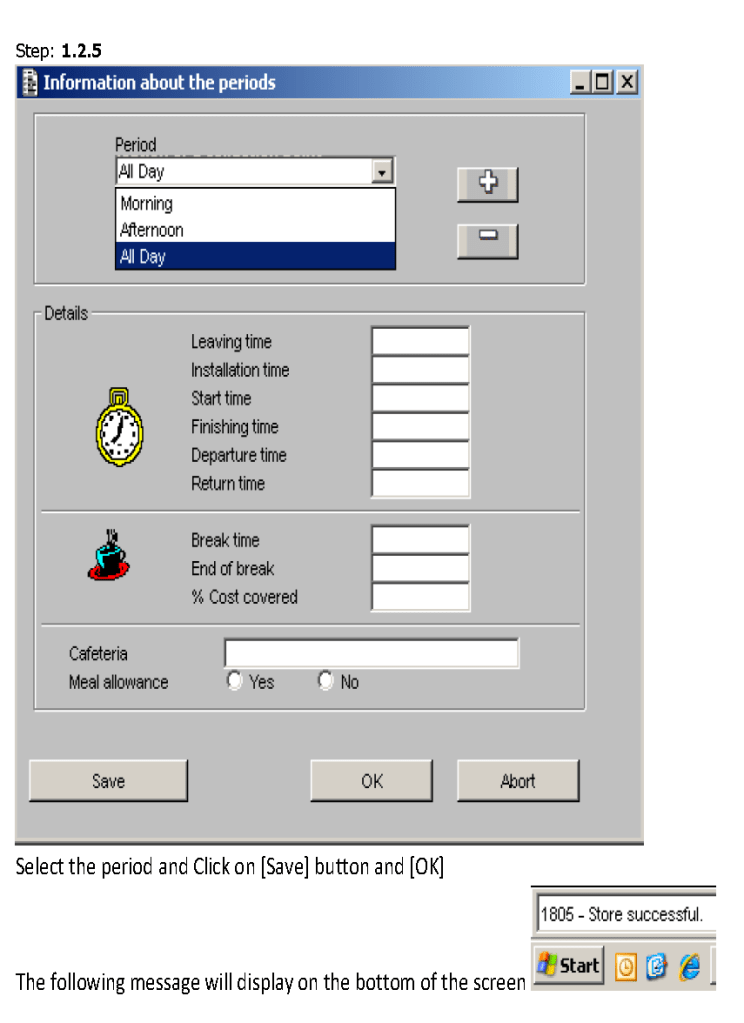
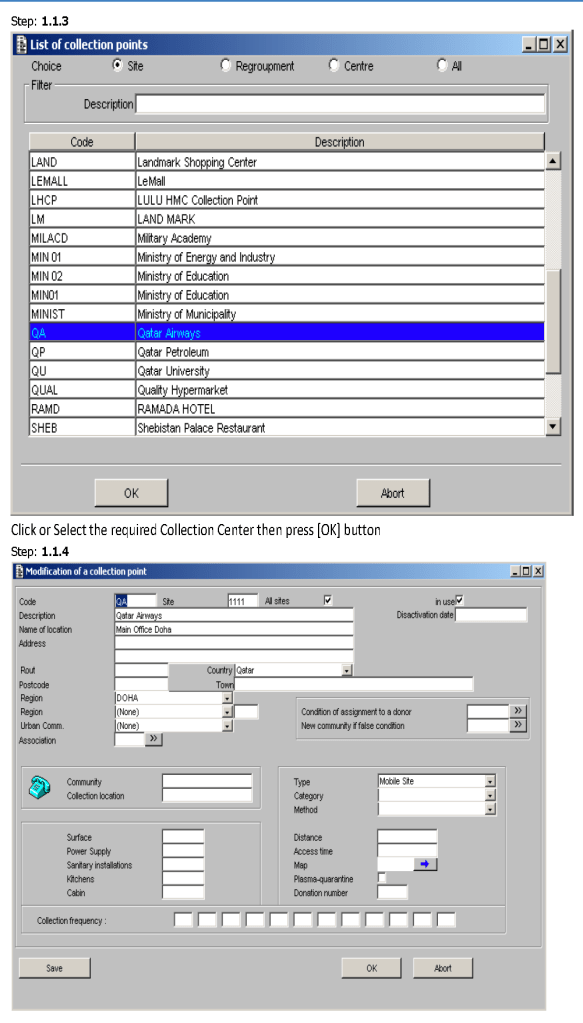
This policy outlines steps taken to minimize the risk of data entry errors and is based on a dualistic approach:  review of results by a senior technologist and/or supervisor and various computer safeguards built into the Medinfo Hematos IIG blood bank computer HIIG system.  This policy also discusses the verification (here called authorization) and purge processes of HIIG.

Policy:

  1. Review by senior technical, supervisory, or transfusion medical staff:
    1. Designated test procedures require review by a second technologist before authorization.
    2. Complex immunohematology testing and specimens showing aberrant results (e.g. ABO/D discrepancies) are reviewed by the supervisors or designates and ultimately a transfusion medicine physician before authorization.
  2. Computer system HIIG rules:
    1. Privileges:
      1. System restricts which staff can perform specific tests
    2. Patient/donor identity:
      1. System asks end-users to verify patient/donor identity before starting any access to the patient/donor record.
      2. System performs historical database checking and flags any inconsistencies (e.g. historical ABO/D typing differences, etc.)
    3. Testing:
      1. Only selected staff have privileges to authorize or purge.
      2. ABO/D testing algorithms require entry of reactions, not interpretation of results and are compared to a truth table.
        1. Aberrant results require special review before ABO/D typing results can be authorized/purged.
        2. D-controls must be negative to allow D typing results to be authorized for liquid D-typing reagents.
      3. DAT results require appropriate controls to meet truth-table criteria.
      4. Eluates require last wash to be negative before authorization
    4. Blood components:
      1. Selection of RBC or plasma units requires two independent sample determinations within 72 hours of each other.
      2. ABO-incompatible RBC or FFP/FP24 transfusions are not allowed.
      3. Donors with any detectable antibodies are permanently deferred.
      4. Depending on the patient’s antibody history, release of RBC units may require antigen-matched units.  Examples:
        1. Mandatory matching (only antigen negative matched units allowed—no antigen positive or antigen-untyped units):  Antibodies against H, D, c, K, k, Kpa, Kpb, Jsa, Jsb, Jka, Jkb antigens, anti-PP1Pk
        2. Priority matching (incompatible or untested can be approved by a transfusion medicine physician):  C,E, e, Fya, Fyb, M, S, s
        3. Antigen matching not required:  Lea, Leb, N
      5. Least-incompatible crossmatch require special authorization to release
      6. Protocols to force irradiation or other modified components can be setup in HIIG.
    5. Donors:
      1. Donor tests have same criteria as the same test used in patient testing for controls, etc.
      2. Donor demographics are read directly from the Ministry of Interior database—no manual entry (bar code only used).

References:

  1. Workflows for Hematos IIG (1001 through 1005), 2013-2020
  2. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  3. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

Pre-Screening for CCP Patients

This is a review/update of this document prepared early in the course of our COVID-19 Convalescent Plasma CCP collections.  It now includes testing of specimens not only for donor marker testing but also COVID-19 antibody titers.

All blood components are considered medications and are subject to Good Manufacturing Practices as mandated by international accreditation standards.  The whole process must be done reproducibly and precisely by specific personnel trained and documented to be competent.  This includes collection of convalescent COVID-19 plasma.

Transfusion Medicine will provide staff who are deemed competent for the entire process of the collection, manufacture, and release of this unlicensed, emergency-contingency component.

It will help greatly if all candidates are prescreened to exclude the following candidates:

  1. Administrative:
    • Donors must come with a valid Qatari identity card:  no ID means no screening
  2. Sex:
    • Males only to minimize the risk for transfusion-associated lung injury TRALI
  3. Donor Feeling:
    • If the donor does not feel well, he should not come for screening/collection.
  4. Food/Drink:
    • Donor must have eaten/drunk fluids within 4 hours of arrival for screening/collection.
  5. Medication exclusions:
    • Antibiotics within the past 14 days
    • ACE inhibitors in the past 48 hours
    • Beta blockers
    • Anticoagulants
    • Anti-anxiety or other psychotropic medications
    • Other medications on the Unified Donor Questionnaire Deferral List
  6. Medical exclusions:
    • Stable vital signs
    • History of seizures
    • History of dementia or other chronic neurologic disorder
    • Family history of dementia or other chronic neurologic disorder
    • Significant cardiac arrhythmias
    • History of hepatitis B, hepatitis C, HIV, brucellosis, Ebola
  7. Travel history:
    • 5 years cumulative residence in Europe including Ireland and France 1980-2001
    • 3 months cumulative residence in the UK (and/or all its territories) 1980-1996
    • Any visit(s) to West Africa
  8. Testing:
    • Antibody titers should be performed to exclude candidates with low-titer or absence of antibodies.
    • Regular donor marker testing (excluding malaria and HTLV 1/2)

All processes will continue to be performed in the dedicated blood bank computer system. The COVID-19 antibody titers will be part of the donation record.

This is NOT a complete list of criteria.  Transfusion Medicine personnel will screen according to the full donor criteria.  Thus, donors passing the pre-screening may still be otherwise disqualified based on the detailed process.

8/11/20

Advice to Transfusion Medical Directors on the Selection of Blood Bank Software

Most Transfusion Medical Directors are not information technology IT people.  Still, regardless if you direct a hospital blood bank/transfusion service, a blood donor center, or both, you will still have to evaluate software for your operations.  You will probably have to sign off on the selection of a system and on the final build before going live.

This can be a formidable task, especially since none of us were trained in IT.  In my opinion, you can still do this based on your knowledge and experience and make a successful choice.

The most important thing is to KNOW YOUR OPERATIONS!!  Someone in your organization should map out all your processes, preferably as flow charts.  Optimize your manual processes.  Look at your critical control points:  How does the software enhance operations and safety?  How does the candidate system enhance security and consistency?  Does it bolster the critical control points?

My experience has been that the best software build is the one based on a good manual system.  Study the new candidates:  how do they enhance your operations?  Now reconstruct your processes with the enhanced features of the new system.

Don’t be afraid to ask for help.  Check your local resources and/or consider outside consultants if necessary.  The latter should have experience in working with blood bank systems and ideally have worked with your candidate vendors.

Human beings are not consistent creatures.  We often do not like following a series of steps in a processes, we like to skip around.  All of this is very dangerous to patient care.  The ideal system enforces consistency and integrity.  I actually like it when my staff complain that the software is merciless—they cannot take shortcuts.  They must follow each step in order!

Choosing a module from within a laboratory or hospital information system LIS/HIS will facilitate integration with the rest of system.  However, such modules (mainly limited to hospital blood banks) do not have all the features that a dedicated blood bank software has  For example, will they prevent release of unphenotyped or Kell-positive units in a patient with anti-Kell?

If you choose the dedicated system option, you must determine if a functioning interface to the LIS/HIS exists.  If not, what is the time frame to make the connection?  Very importantly, check that your specifications are actually built into the interface.  Almost every LIS/HIS vendor says that they can make an interface, but are they communicating what you need?  If you talk English and they answer you in Sanskrit, are you effectively communicating?

I prefer a dedicated blood bank system for both patients and donors, especially one that allows you to create rules to handling different situations like electronic/computer crossmatch, irradiation, etc.  Integrating both patient and donor operations will facilitate operations, especially in times of disaster and product recalls/quarantines.

Make certain that there are interfaces available for your analyzers and blood production equipment (e.g. Ortho Vision Max, Reveos, Mirasol, etc.).  Check these out on a site visit.  Many vendors promise that they can communicate with your equipment, but you must verify this yourself.

You are the pilot.  Is the transfusion or donor information organized to facilitate your decision making? Is it available all on one screen?  Do you have to flip across many screens to get the information (e.g. transfusion history, transfusion reactions, DAT, antibodies, donor history, marker testing) you need?

If you are directing a donor center, you will most likely need a separate dedicated software.  Usually, donor center software does not directly integrate into the LIS/HIS.  However, at least your patient hospital blood bank module must be able to read your ISBT labels properly.

I recommend a visit to a site comparable to your current operations.  Look for ease of use, response time, and talk privately with the end-users at the site.  Ask your IT staff to help you select a site that uses the same operating and database software (e.g. Oracle) as you will be using.

How readily can the system be modified for new practices?  With COVID-19, SARS, ZIKA, etc. there have been many changes in regulations in a short time.  How long will it take your vendor to update your system?  Is the system compliant with your local regulations and international accreditation standards?

Structurally, the optimal system is one that is a framework where almost all changes can be handled by changing settings or parameters.  The underlying structure does not change so this facilitates making the modification.  There is no need to “hard code” the changes.  You are not writing a new software structure.  Warning:  many blood bank softwares do not have this framework or flexibility—it takes a long time often even to make minor changes or updates.

Using blood bank software is like playing with fire.  Defects in design can adversely affect patient care.  The vendor will install the software with settings, but it is still YOUR responsibility to verify it works according to the specifications.

I recommend engaging computer-literate end-users (nurses, doctors, medical technologists, recruitment staff) .from the very beginning of the actual software build.  These staff can become Super Users to handle minor issues and train other staff and can help perform your software validations.

In summary, you will have to accept the choice of vendor and the final software build.  Find resources to help you with these tasks.  Never forget that what you are doing could adversely affect patient care if you are not vigilant!

4/11/20

COVID-19 Convalescent Plasma Revisited:

In February, 2020, I developed a program for convalescent COVID-19 plasma at Hamad Medical Corporation in Doha.  In early March, 2020, our program started collecting CCP by apheresis.  We started before the software modifications were completed since there were urgent requests by the clinicians for the product.

I proposed the software specifications and our vendor Medinfo Hematos IIG implemented them within 2-3 weeks, after which they were implemented/validated

Thus, now we have 8 month experience has been 8 months since starting manually and more than 7 months using a specific modification of our blood bank software Medinfo.

A complete manual system was implemented with quarantined registration, screening, collection, processing, and release.  Only the donor marker testing was shared with the regular donors.  This was built into the computer system.

Upon review, these are my current thoughts on our processes:

  1. Actively monitor supply requests:  Keep good communication between ordering/treating physicians and apheresis unit to optimize the stock according to patient needs.
  2. Collect/process/release separately from regular donations.
  3. Use dedicated quarantine equipment (apheresis, processing, storage refrigerators)
  4. Collect manufacturer’s recommended maximum of plasma based on body weight.
  5. Use pre-donation screening to allow quick release of components and avoid wasting apheresis kits.
  6. Repeat testing on the new specimen collected at the time of apheresis donation.
  7. Process units by same processes used for normal donations, including pathogen-inactivation.
  8. Use standard processes for release of blood components to end-users.
  9. Restrict ordering to designated treating COVID-19 physicians (enforce in computer system)
  10. Restrict release of CCP to designated non-blood bank staff from the quarantine storage location (enforce in computer system)

Notes:

  1. Include COVID-19 antibody testing and establish a threshold level (e.g. 1:128 titer) for donor qualification.  Do not collect if low-titer or absence of COVID-19 antibodies.   Store titer information with donation record.  Add antibody results to donation records that occurred before the assay was available.
  2. Review of donor criteria:  are there increased risks using these recovered donors:  cardiac or respiratory risk?  Is there a way to continuously monitor CCP donors’s vital signs during the donation?
  3. Collect apheresis components only in pre-screened donors:  Apheresis kits are expensive, use them only if the donor is prequalified, continue to retest when actual apheresis donation occurs
  4. Allow use of units directly after collection/processing as long as the other donor processing steps have been completed (allow blood bank computer system to use pre-donation specimen for marker testing criteria).

Donor Unit Discrepancies

Principle:

All donor unit mislabeling is potentially life-threatening and must be stringently investigated as soon as possible after the discrepancy is detected.  Most importantly, if there is one error, there may be possibly ADDITIONAL donor unit errors (e.g. switch of donor tubes or units, etc.).  All donor units processed in the same batch must be also quarantined until the discrepancies are resolved.

The blood bank computer system will detect many errors;  however, if the donor unit or its samples are mislabeled in the beginning, these may not be detected.  Medinfo enforces checks on the final ISBT label and will compare current results to the historical record and will alert to any errors. Additionally, the use of ISBT specimen labels will obviate the risk of barcode reading errors.

Definitions:

Responsible blood bank physician:  specialist or consultant physician on-call at the time the discrepancy is detected

Policy Details:

The following steps MUST be performed as soon as possible:

  1. The Component Processing Supervisor or Senior Technologist must be IMMEDIATELY notified of any discrepancy.
  2. The Blood Bank Supervisor will inform the Division Head, Transfusion Medicine.  If the Head is not available, notify the Transfusion Medicine on-call.
  3. Quarantine ALL donor units collected and processed in the same batch.
  4. Obtain copies of all testing including photos of the gel/glass bead cards documenting the discrepancy.
  5. Obtain copies of all worksheets used in donor processing for the affected batch.
  6. Perform repeat ABO/D typing of ALL DONOR UNITS in the affected batch.  Any further discrepancies must be investigated and resolved.
  7. Identify all staff who were involved in handling the donor unit (phlebotomist, blood bank technicians processing and labelling the unit).  Identify those associated directly with the error.
  8. Submit all documents and photos to the Blood Bank Supervisor or designate.
  9. Prepare an occurrence/variance OVA report documenting all the data, findings, and interpretations.
  10. All investigations must be reviewed by the Supervisor, responsible blood bank physician, and one of the senior consultants.
  11. All such investigations must then be finally reviewed and approved by the Division Head, Transfusion Medicine or his designate.  Only when the issue(s) are completely resolved and investigation is approved may the donor unit be properly relabeled and released into available stock.  Also, only at that time may the other units in the affected batch be released into available stock!!
  12. Photograph the correctly relabeled unit and attach it to the other documentation of the incident.
  13. If the discrepancy cannot be resolved, ALL units in the affected batch must be discarded.
  14.  The implicated staff’s personnel record should be reviewed for previous errors.   Appropriate disciplinary action should be taken and documented in the personnel record.  If a verbal warning is given, it should still be documented in the written record.
  15. If there is a systemic cause for the error, appropriate measures should be taken to minimize reoccurrence.
  16. All actions must be in accordance with the institution’s policies and regulations.

2/11/20

Nipah Virus and Blood Donation

Principle:

Nipah virus NiV is a paramyxovirus that may cause a fatal encephalitis in infected patients.  Transmission to humans may occur after direct contact with infected bats, infected pigs, or from other infected humans.  ELISA, NAT, and direct culture may be used for confirmation of diagnosis, but there is no available licensed donor test.  The geographical distribution of this virus corresponds generally to the areas of malaria exclusion used for blood donor screening.  Most cases are fatal, and survivors may have neurologic sequelae.

The incubation period is 5-14 days with illness presenting 3-14 days of fever, headache, followed by drowsiness, disorientation, and confusion.  These findings may progress to coma within 24-48 hours.  Some patients also develop a respiratory illness.  Latent infections with subsequent reactivation of the virus have occurred months to years after exposure.

Policy:

  1. The current exclusion for travel to malaria endemic areas will be used to exclude donors with possible NiV exposure.
  2. Any donor with a history of Nipah virus infection will be permanently deferred.
  3. As per current SOP, any donor not feeling well must not donate blood or blood components.

Blood Bank Software is Dynamic, NOT Static

I was recently talking with one of the hospital software system administrators from my previous site.  He had originally worked on building the Medinfo system, but was then reassigned to the laboratory modules of the hospital information system.

His alarming comment to me was that the Medinfo build was completed so there was no need to worry about it now—it was finished.  I guess he was looking from the perspective of the general laboratory software.  There is no need to make major changes to the build, just update interfaces and troubleshoot.

I was surprised.  He had no idea of how many times we have to update the structure for new rules and regulations, and changes in blood bank practice—let alone emerging pathogens such as ZIKA, dengue, Chikungunya, and most recently, COVID-19.

My daily morning routine was to survey several blood bank websites with changes to blood donor criteria including US FDA CBER, read the transfusion journals (Transfusion, Vox Sanguis, etc.), AABB, and ASFA.  If there were any changes pertinent to our organization, I had to make interim policies and procedures, and finally prepare specifications for changes in the Medinfo software.

The Medinfo engineers would prepare flow charts of the proposed changes and implement them in a test environment for the Super-Users to test.  I had to prepare validation protocols for the testing, and then review the validation results and finally approve the adoption of the changes.

I cannot remember even a month going by without some revision in the donor protocols.  When COVID-19 came, I had to prepare a parallel, but separate, processing and allocation/release system.

This was a never-ending story that kept the Super Users and the local Medinfo engineers busy.  I always reminded the hospital information system staff that playing with blood bank software was like playing with fire:  there is a good chance you will get burned if you do not set it up properly.

31/10/20

Opinion: International Perspective

In all my years practicing medicine outside the United States, I have come to appreciate working with a diverse group of health care professionals from many countries and cultures and with many different primary languages.

I learned that there are many different international standards and not all agree with each other.  Yet, despite the apparent contradictions, they all work to improve patient care and were generally successful.  It made me reconsider my roots and think less dogmatically and be willing to learn from other perspectives.

This applies in many ways.  First, which English should we use?  Most people are at least somewhat aware of American English, but there are differences with British, Australian, and international English—even the term “blood bank” may have different meanings:  is it a hospital transfusion service, is it a donor center, or some combination of the two?

I have worked at many sites where I was the only person native in English.  I always tried to conceive how difficult it could be for someone non-native to understand and communicate in a highly technical and highly Germanic structured language.  I considered the scenario where I had to work in another language exclusively and perform all my tasks—I highly respect my staff having to cope with this.

English technical writing includes a lot of passive voice, subjunctive mode, perfect tenses, and participles.  How formidable a barrier are these to staff whose native languages may not use these structures?

I am not saying that English is the best language to perform the work in, but it is most prevalent one so everyone must cope with it.  I told many of my staff to learn German to better understand English grammar.

What bothers me is that certain software vendors and visiting lectures send speakers and staff who ONLY think in American English and American culture.  I can think of several anecdotes:

One speaker was talking about hyperlipidemia and used non-SI units.  He kept stating cholesterol > 200 and LDL-cholesterol > 120 to an audience who only used SI units.  Could the audience quickly convert to cholesterol > 5 and LDL > 3?  Did they know what a temperature of 104 F was 40 C?

Another speaker for a software company used an analogy of collecting maple sap and making maple syrup—in a presentation in the Middle East.  How many in the audience even knew what maple syrup is?

In building a series of software modules, some company staff used 24-hour clock and others used 12-hour clock.  It was chaos trying to define a 24-hour interval between the different modules.

Finally, I think of the Aesop’s fable about the mother who gave birth to a very ugly child, but to her, he was the most beautiful child in the world—so much so that she entered him into a beauty contest.  Well, each of us is the “mother” to our documents and memos.  The writing looks good to us and is perfect, but do our staff interpret it the same way we do?

I had my staff read my documents and then explain back to me what I was trying to say.  I was shocked at the differences in many cases.  After this, I always included a validation step to have other people read and interpret what I was saying—and correct any misconceptions in the writing before I finally released the document.

In summary, it is a whole new world outside the United States.  Don’t assume everyone thinks the same way or uses the same criteria to accomplish goals.  Be open to this and you will have a rewarding international career.

30/10/20

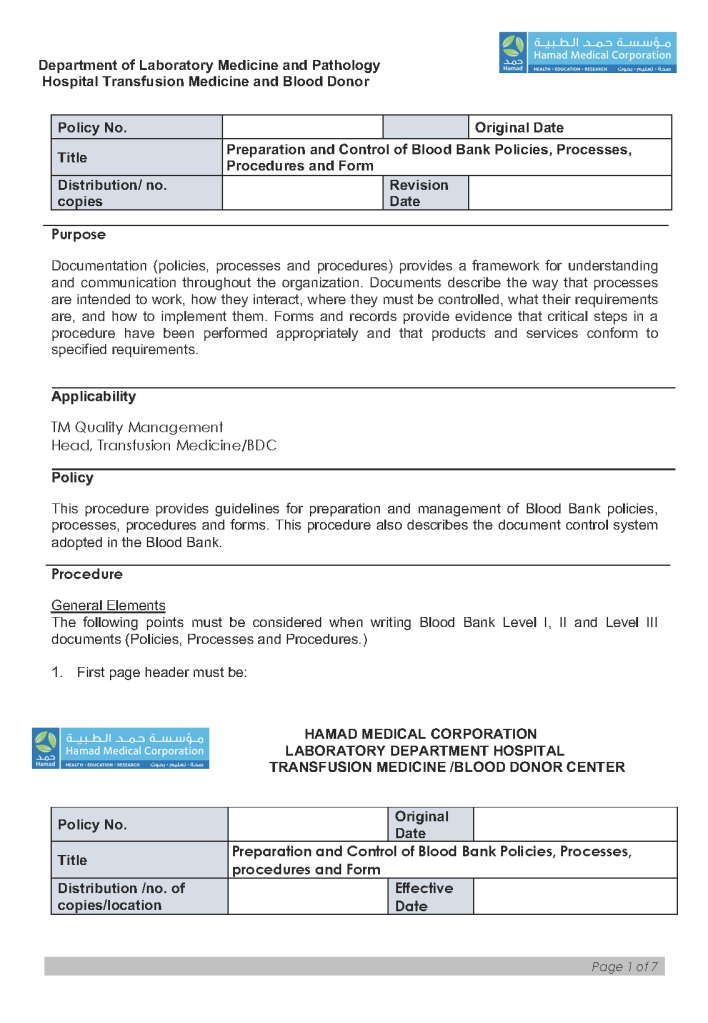
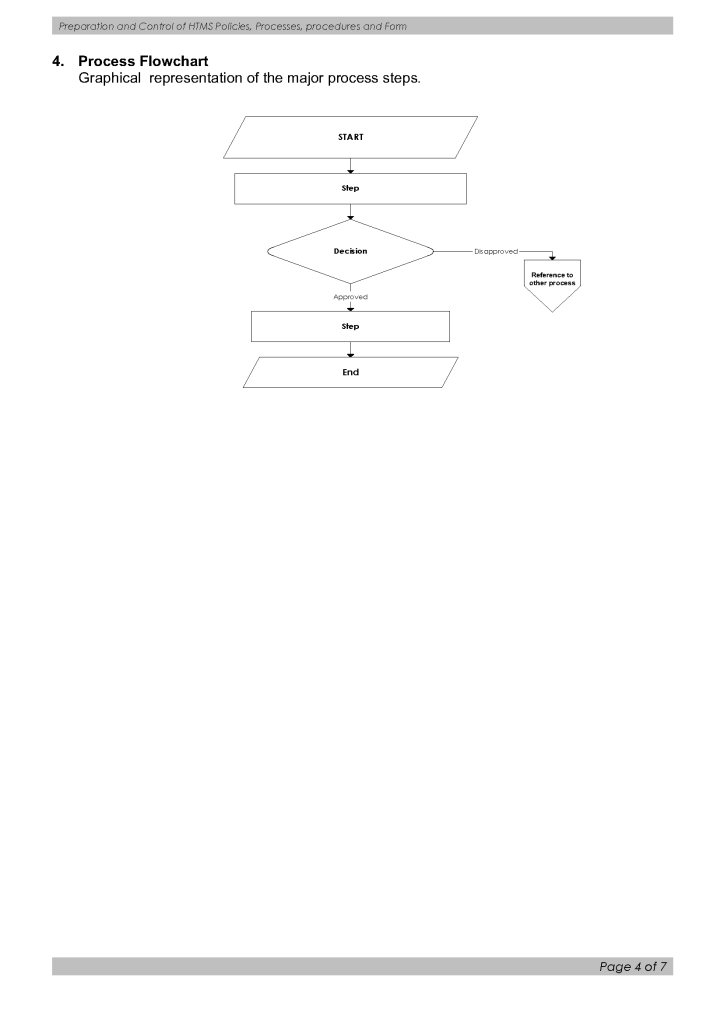
Document Specification

There should be a clear specification of how to prepare documents (policies, processes, procedures, and forms for Transfusion Medicine. The following is a draft document prepared by Transfusion Quality Management and myself for HMC in Doha. I want to thank Ms. Editha Durante, then Quality Manager and Quality Reviewer at HMC for all her work on this.

29/10/20