COVID-19 Convalescent Plasma CCP Series Introduction

I will be posting a detailed series about the manual and software-enhanced COVID-19 processes that I set up in Qatar at HMC Doha in March-April 2020.

In this series I will provide you with screen shots of my Medinfo Hematos IIG software design for each step in the process:  collection, processing, testing, inter-depot transfer, and hospital transfusion service/blood bank release.

This GMP-compliant software-enhanced system is based on the manual system I set up in early March 2020 at HMC.

I want to thank Medinfo Hematos IIG for their rapid response to building this parallel system based on my standard processes in so short a time (two weeks) and my special thanks to the software engineering team at Vital Health Technologies, the agent for Medinfo in Qatar.

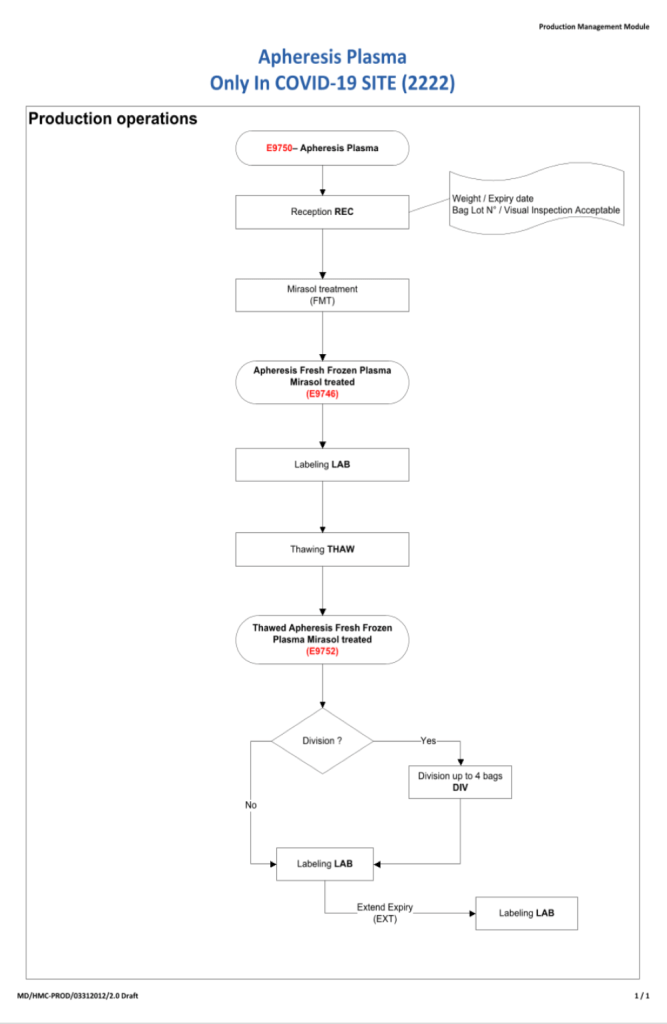
To start the series, I am providing the basic workflow for the system.  As is normal in Medinfo software design, a full mapping of the processes are made.  This workflow shows the new CCP ISBT codes and the quarantine collection and processing steps.  The donor testing (marker and immunohematology) processes are similar to those for regular donor units.

This is basically the same process both manually and in the software.  I always say:

A good software process is based on a good manual process!!

Please note the following workflow for our initial discussion.
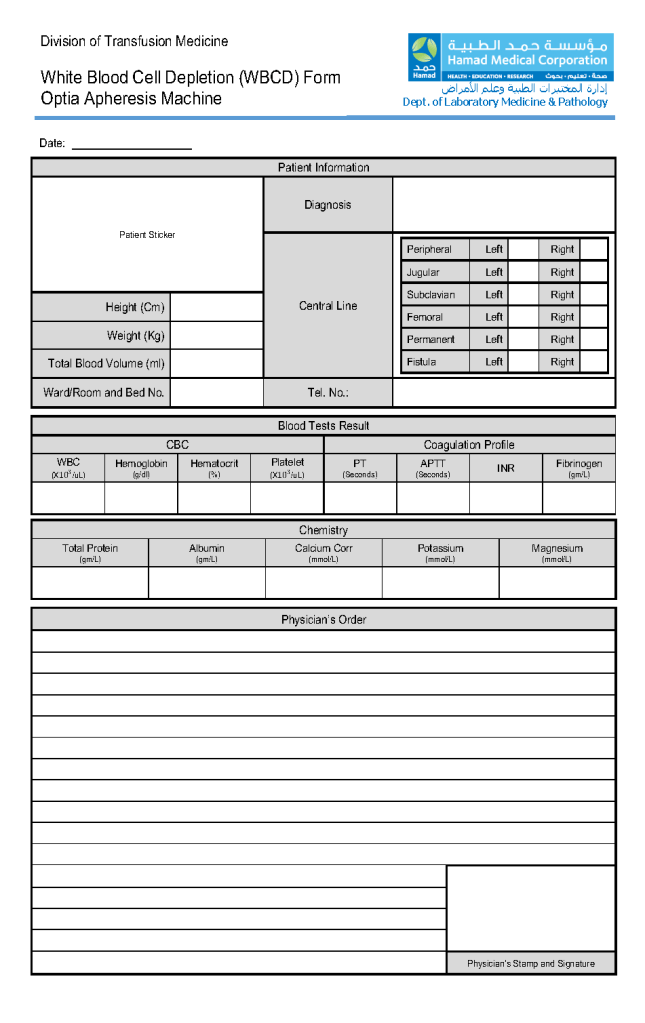
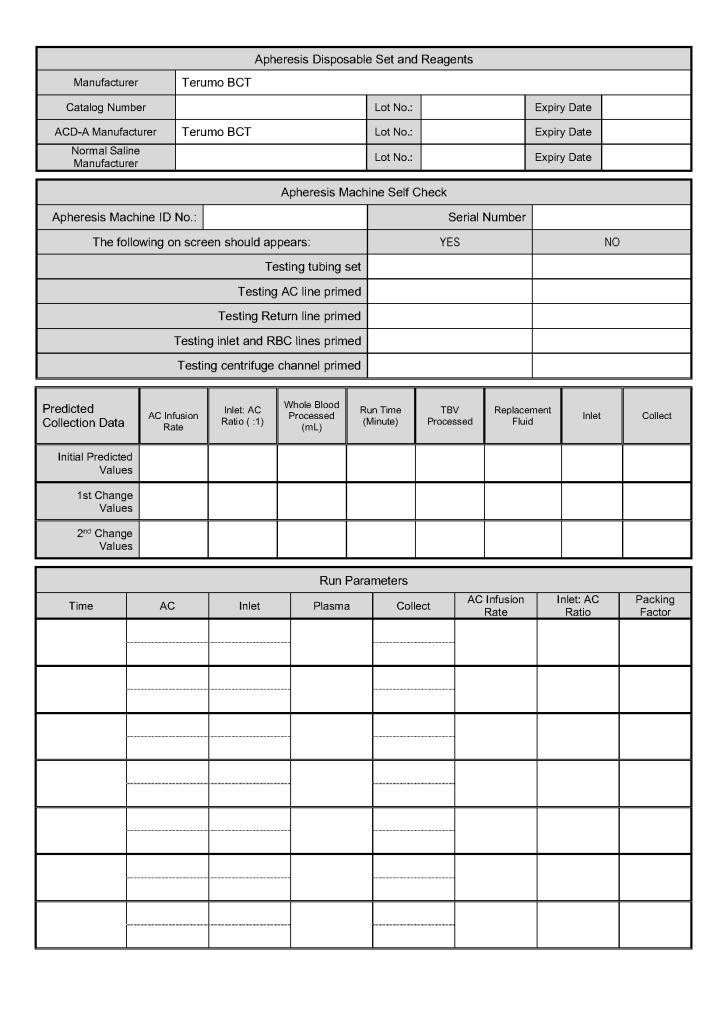
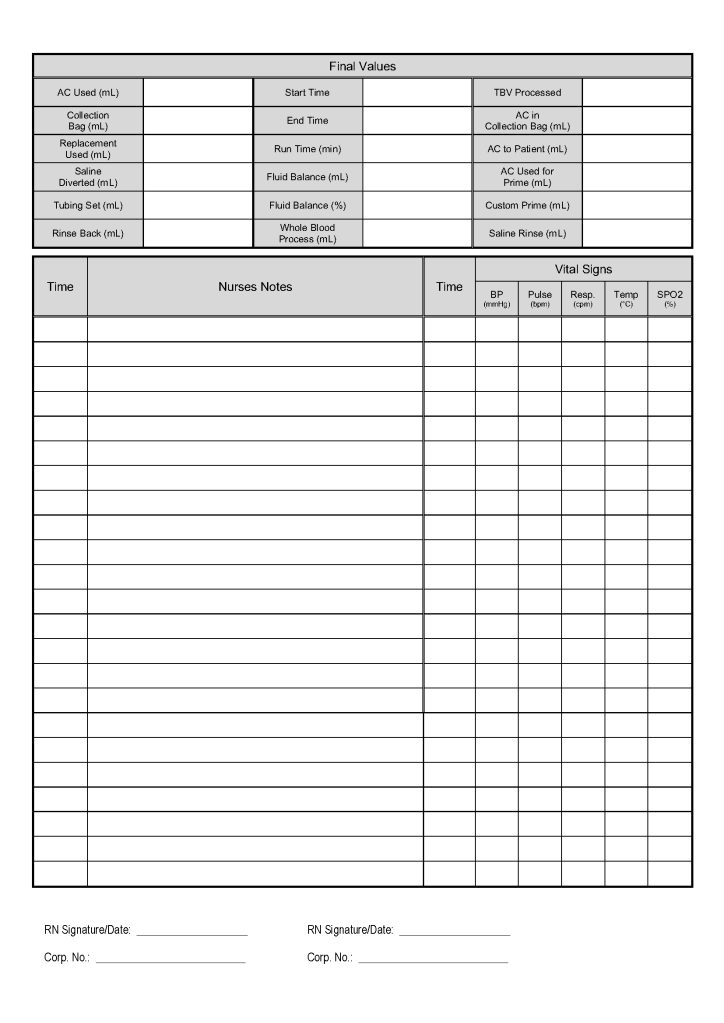
Leukodepletion Apheresis Form

This form is the result of a collaborative effort between my therapeutic apheresis team and me. I want to thank Dr. Saloua Al Hmissi, Consultant, Transfusion Medicine, and Ms. Mini Paul, Head Apheresis Nurse for all their efforts.

This form can be readily converted into a computer data entry form–depending on your software’s capabilities.

Use of Universal Low-Titer Group A Plasma

Principle:

Since group AB plasma is in short supply, use of group A plasma with low anti-B titers may be substituted based on inventory levels.

Policy:

  1. If the AB inventory is low, we will test group A donors at the time of collection for anti-B titers.
    1. The numbers to be tested will depend on the level of the shortage and the availability of equipment to perform titration.
  2. Use the automated analyzer to perform saline anti-B.
    1. If the saline titer is less than or equal to 1:64, the plasma may be used for recipients of any ABO blood group and will be labelled as group AU—A Universal.
  3. Process the unit routinely and perform pathogen-inactivation.
  4. Medinfo Hematos IIG will only label for universal use if the titer is below the cutoff.
    1. The ISBT label must explicitly show group AU plasma and the actual anti-B titer.
  5. Allocation rules for low-titer group A plasma will be identical to group AB except:
    1. For neonates, preferentially use group AB.
    2. For children < 20 kg, use ABO-compatible plasma (non-group AB) before selecting group AB or if not available, low-titer A in that order.
  6. Donors must have a new anti-B titer performed each donor encounter.

References:

  1. Technical Manual, Current Edition, Bethesda, MD, USA
  2. Standards for Blood Banks and Transfusion Services Current Edition, AABB, Bethesda, MD, USA

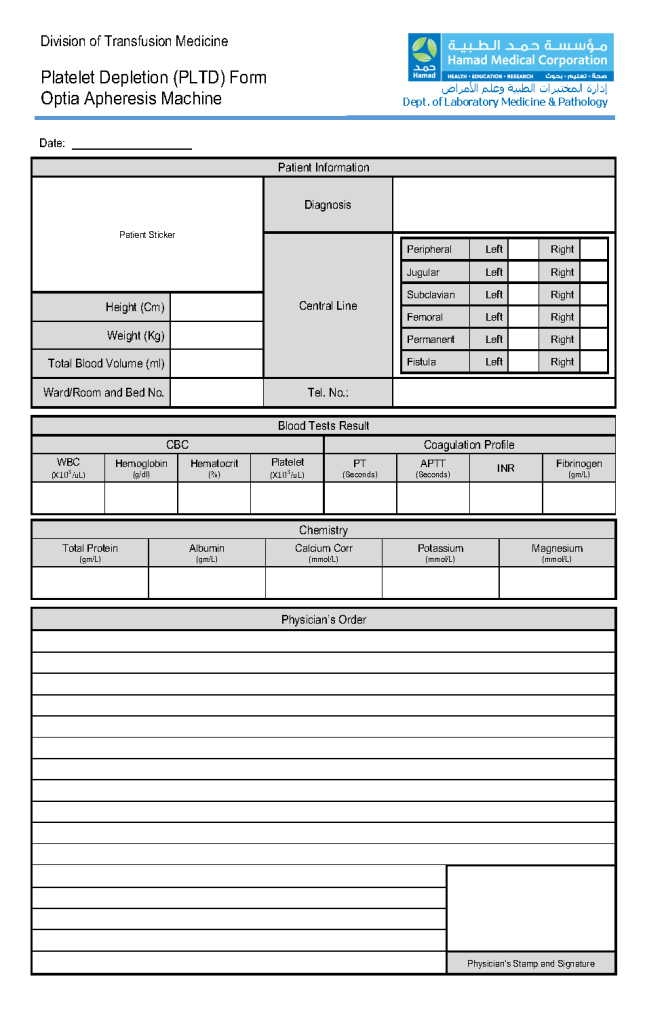
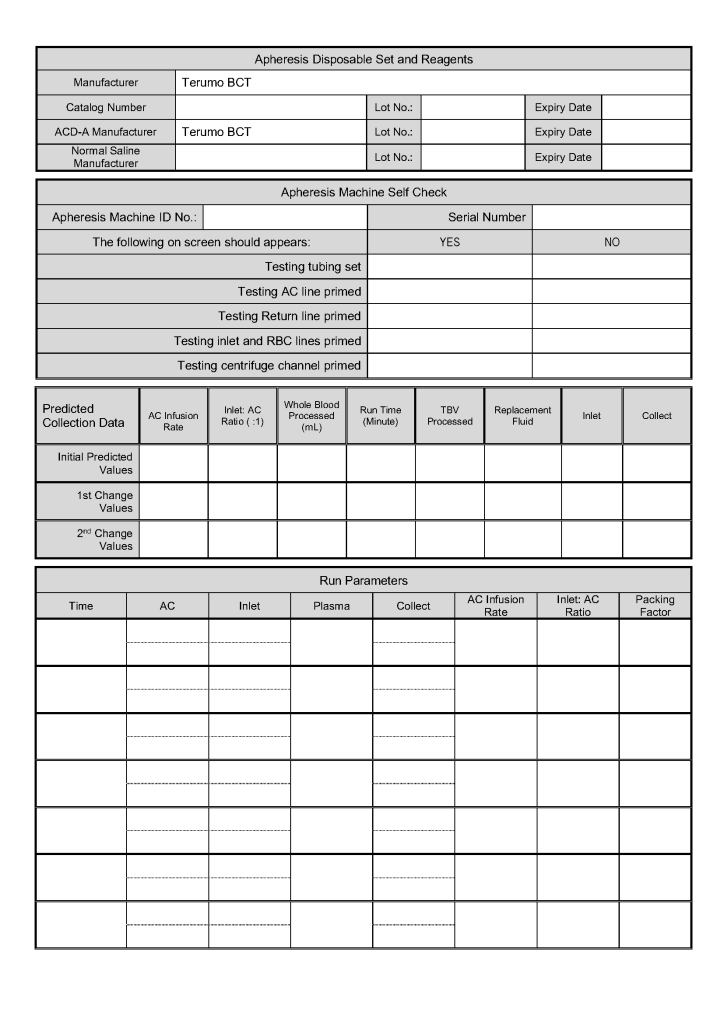
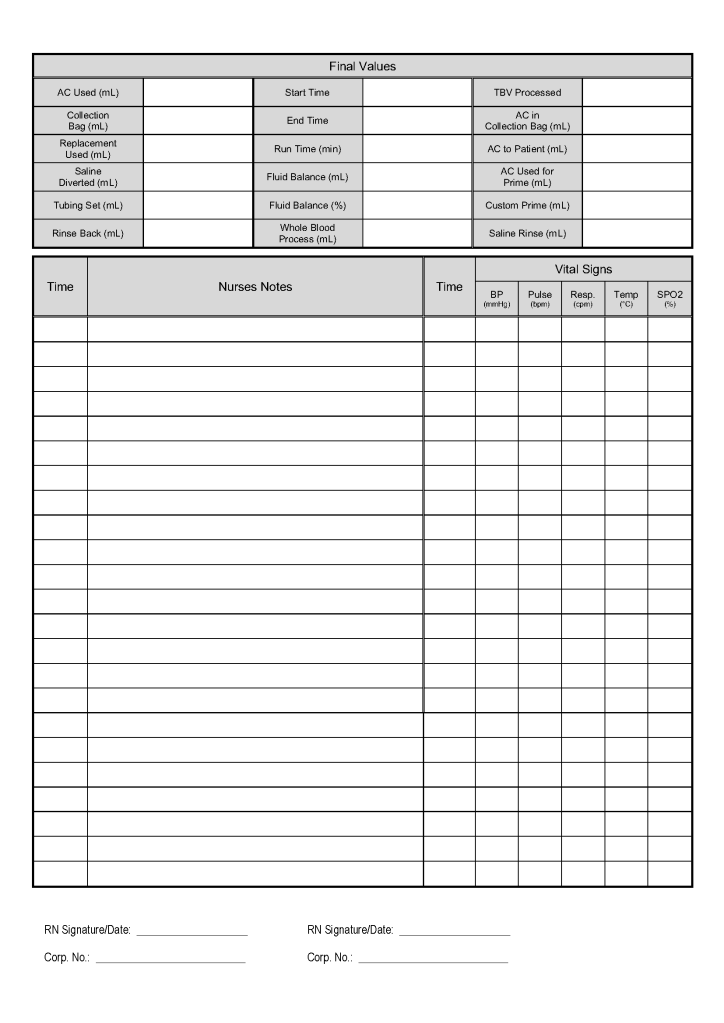
Platelet Depletion Apheresis Form

This is the apheresis form used for reductive thrombapheresis developed by my apheresis team and me. In particular, I want to thank Dr. Saloua Al Hmissi, Consultant Transfusion Medicine, and Ms. Mini Paul, Head Apheresis Nurse, all their hard work.

The attached form can be developed into a computer entry form if one has a suitable hospital information system. It is organized so that the apheresis nurse can quickly enter the data on one screen. Never forget that our goal is treat the patient–not spend all of our time on data entry!!

20/12/20

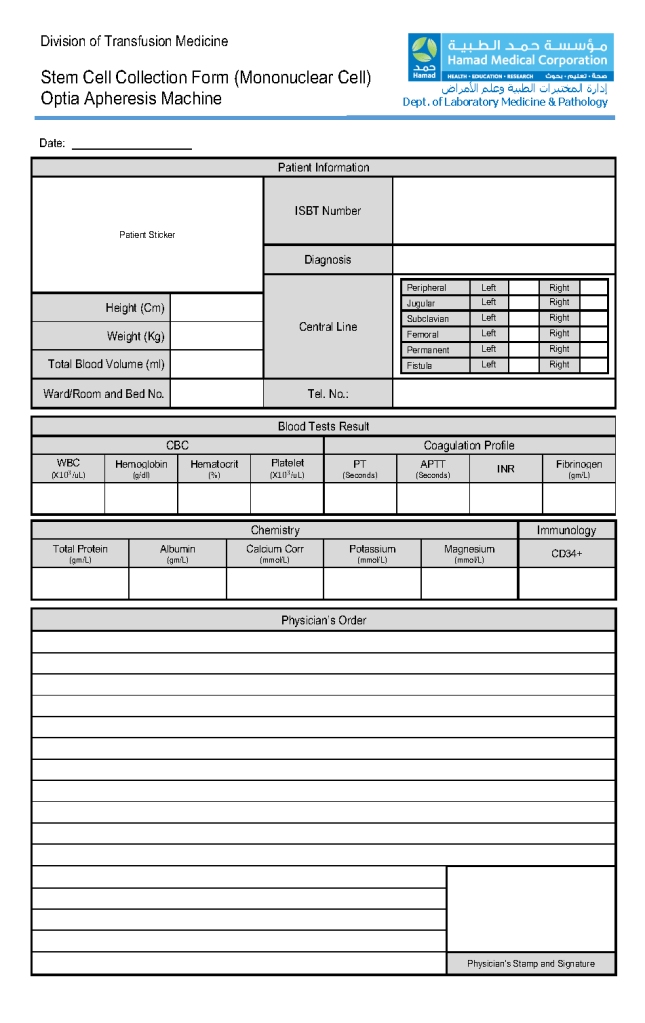
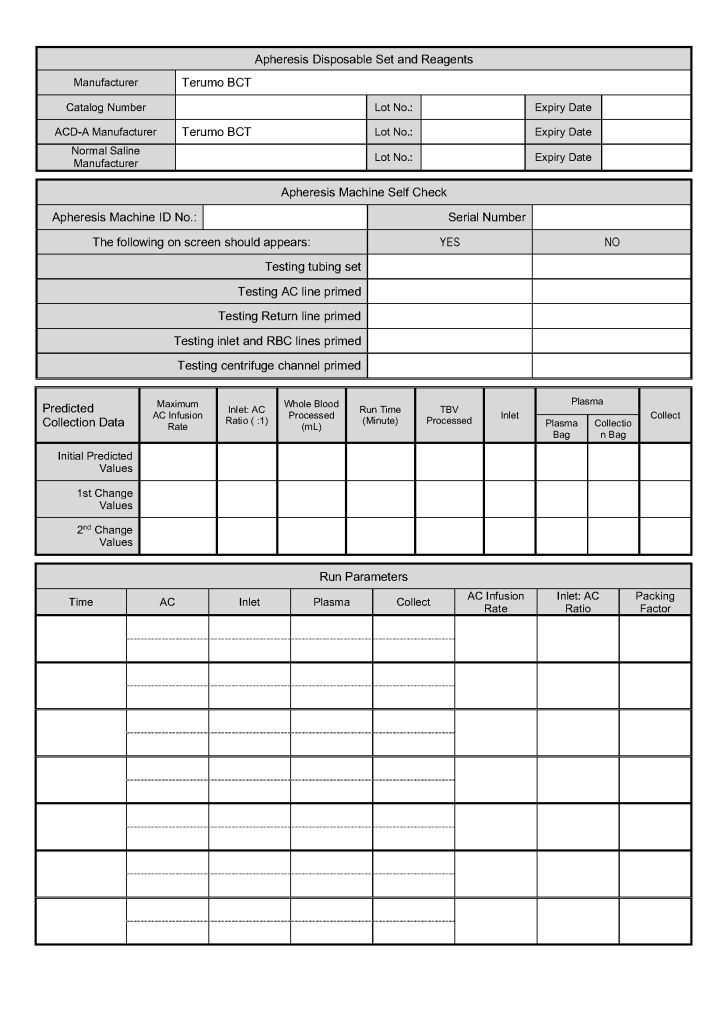
Sample Stem Cell Collection Apheresis Form

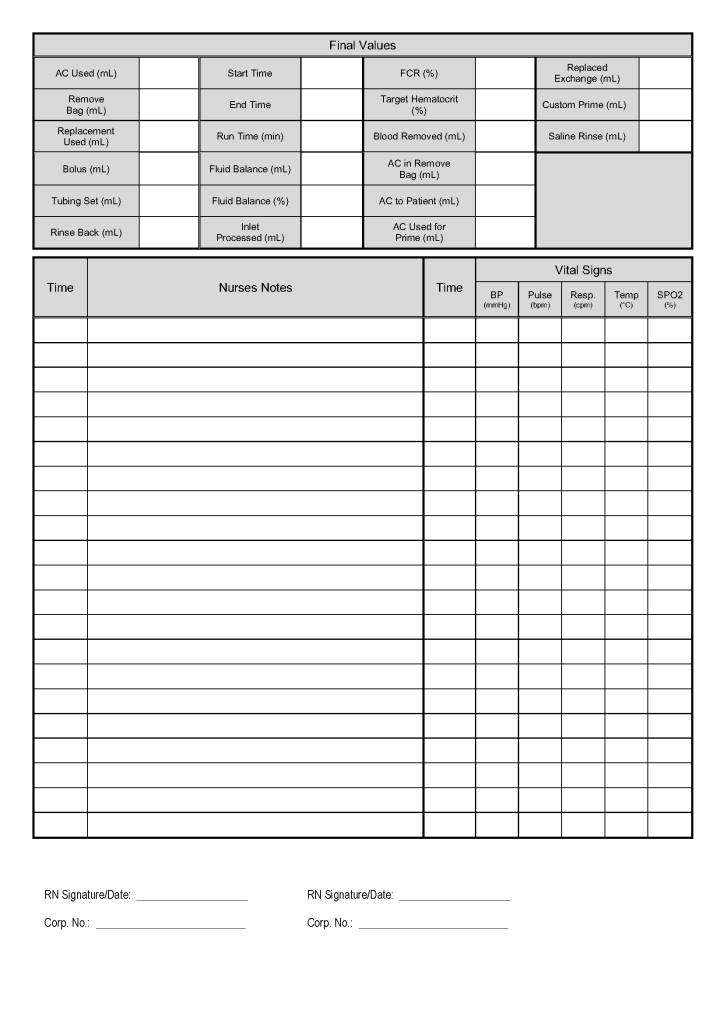
This is a sample of the stem cell therapeutic apheresis form that my apheresis team and I developed. It can be readily made into an electronic form. I want to thank Dr. Saloua Al Hmissi, Apheresis Consultant, and Ms. Mini Paul, Head Apheresis Nurse, for their efforts in making this form a success.

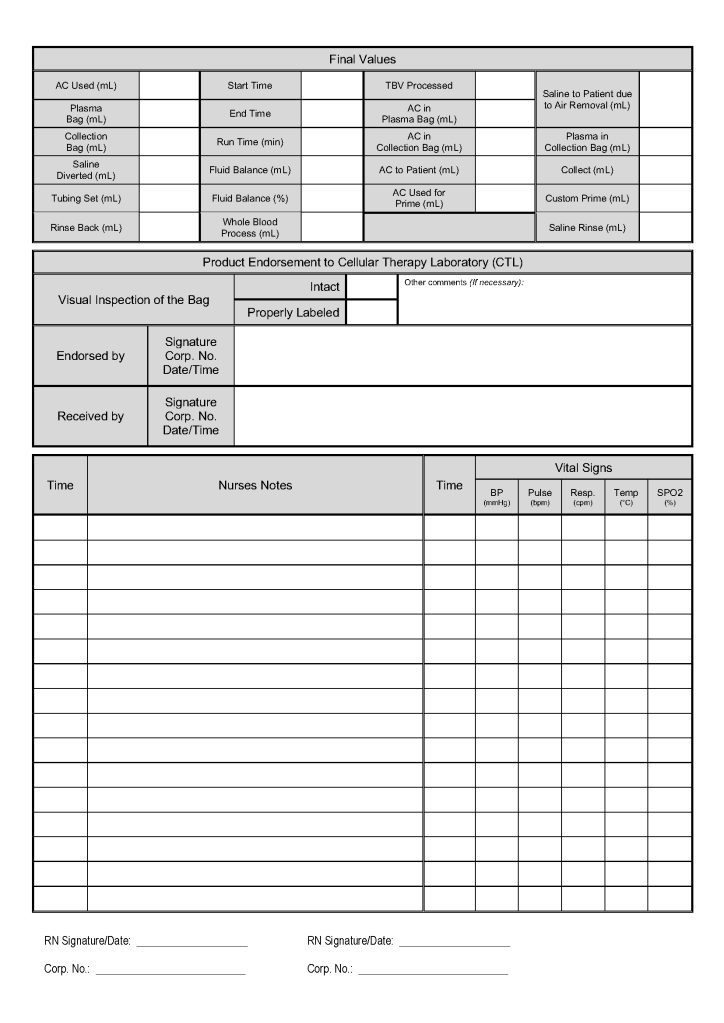
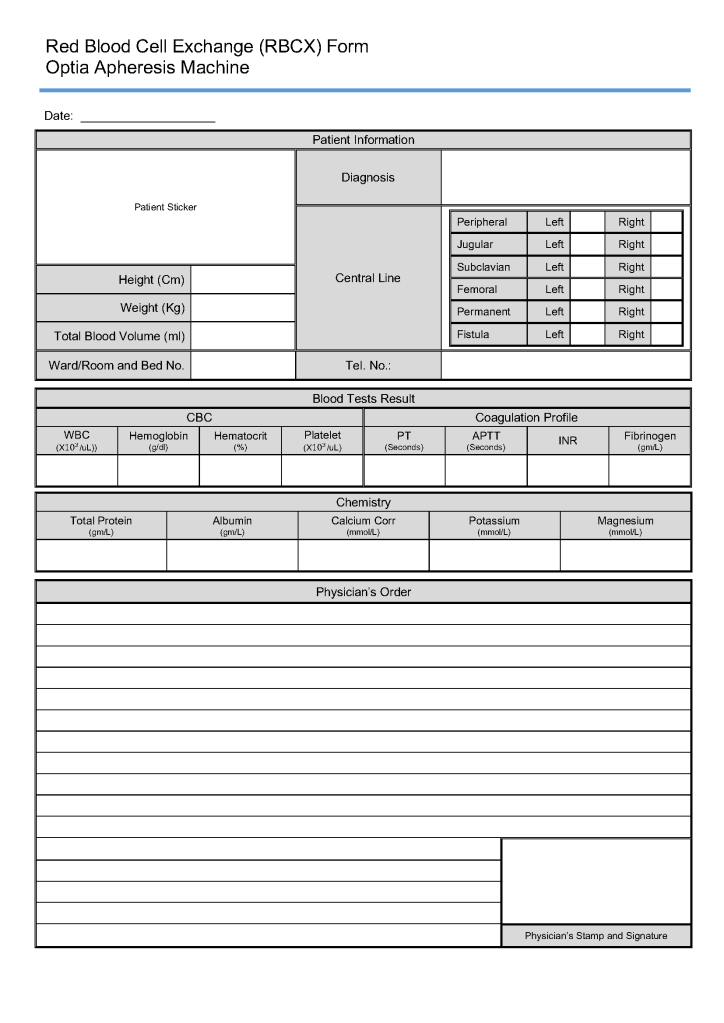
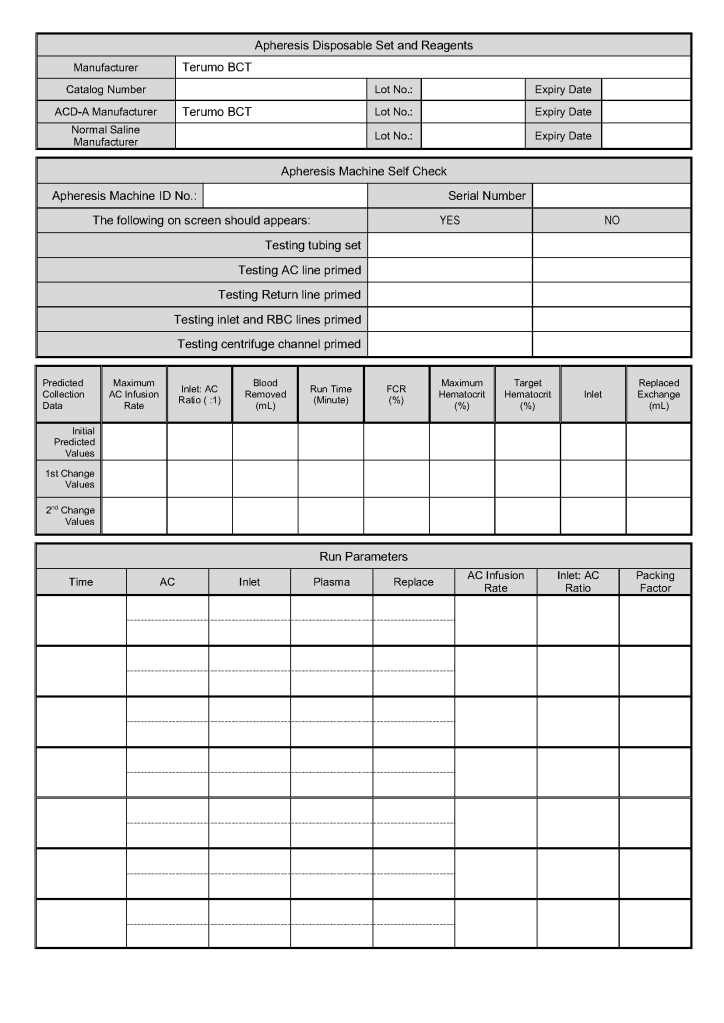
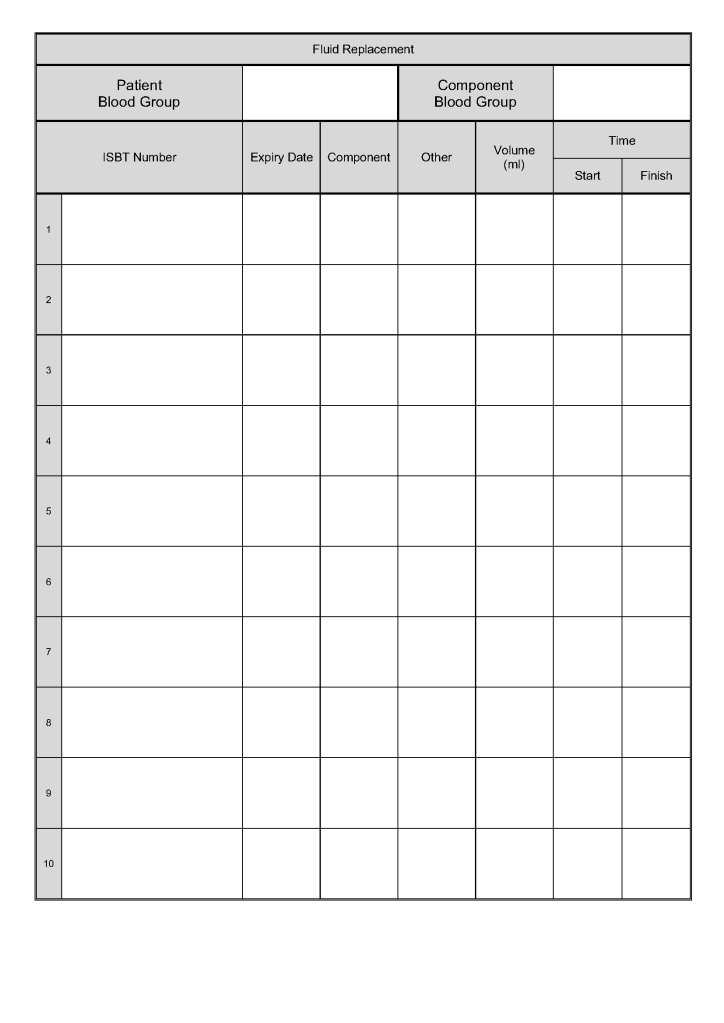
Sample RBC Exchange Form

This form was developed by my senior apheresis staff at HMC Doha in conjunction with me. It organizes the data to minimize the time needed to put the data in place so that the apheresis nurse can concentrate on the patient. It can serve as a good template from which to build a computer form.

I want to thank Ms. Mini Paul, Head Apheresis Nurse, and Dr. Saloua Al Hmissi, Consultant Transfusion Medicine for all their efforts.

Therapeutic Apheresis Volume Calculations

You can get the values off the therapeutic apheresis machine, but in the middle of the night when you have to write orders, it is convenient to estimate the volumes (whole blood, plasma, RBCs).  These are the values from my lectures to hematology fellows while I was at HMC Doha:

Whole Blood:

Weight in kg X 70 ml/kg = whole (whole) blood volume adult

Weight in kg X 85 ml/kg =whole blood volume for child (prepubertal)

Weight in kg X 100 ml/kg = whole blood volume for neonates/premature

Example:  70 kg adult has 4900 ml blood volume (I round up to 5 liters)

Plasmacrit + hematocrit = 1.00 in fractions (100%), ignore buffy coat volume

Plasmacrit = 1- hematocrit

Plasma volume:

Plasma volume = whole blood volume x plasmacrit = whole blood volume X (1-hematocrit)

RBC volume:

RBC volume = whole blood volume x hematocrit

Estimates for blood components:

The volumes will depend on the original amount collected (e.g. 450 vs 500 ml),  original preservative solution used (e.g. CPD), use of automated component production such as Terumo Atreus or Reveos, use of RBC additive solution (e.g. SAGM), leukodepletion, platelet additive solution, pathogen inactivation.

At HMC Doha, the average values were:

300 ml for leukodepleted RBCs in SAGM prepared by Reveos

300 ml for platelet pools in Mirasol and platelet additive solution (residual WBC < 1E6)

300 ml for plateletpheresis concentrate (2.4E11) in Mirasol and platelet additive solution

250 ml for leukodepleted, pathogen inactivated plasma

Pre-Screening for CCP Patients

This is a review/update of this document prepared early in the course of our COVID-19 Convalescent Plasma CCP collections.  It now includes testing of specimens not only for donor marker testing but also COVID-19 antibody titers.

All blood components are considered medications and are subject to Good Manufacturing Practices as mandated by international accreditation standards.  The whole process must be done reproducibly and precisely by specific personnel trained and documented to be competent.  This includes collection of convalescent COVID-19 plasma.

Transfusion Medicine will provide staff who are deemed competent for the entire process of the collection, manufacture, and release of this unlicensed, emergency-contingency component.

It will help greatly if all candidates are prescreened to exclude the following candidates:

  1. Administrative:
    • Donors must come with a valid Qatari identity card:  no ID means no screening
  2. Sex:
    • Males only to minimize the risk for transfusion-associated lung injury TRALI
  3. Donor Feeling:
    • If the donor does not feel well, he should not come for screening/collection.
  4. Food/Drink:
    • Donor must have eaten/drunk fluids within 4 hours of arrival for screening/collection.
  5. Medication exclusions:
    • Antibiotics within the past 14 days
    • ACE inhibitors in the past 48 hours
    • Beta blockers
    • Anticoagulants
    • Anti-anxiety or other psychotropic medications
    • Other medications on the Unified Donor Questionnaire Deferral List
  6. Medical exclusions:
    • Stable vital signs
    • History of seizures
    • History of dementia or other chronic neurologic disorder
    • Family history of dementia or other chronic neurologic disorder
    • Significant cardiac arrhythmias
    • History of hepatitis B, hepatitis C, HIV, brucellosis, Ebola
  7. Travel history:
    • 5 years cumulative residence in Europe including Ireland and France 1980-2001
    • 3 months cumulative residence in the UK (and/or all its territories) 1980-1996
    • Any visit(s) to West Africa
  8. Testing:
    • Antibody titers should be performed to exclude candidates with low-titer or absence of antibodies.
    • Regular donor marker testing (excluding malaria and HTLV 1/2)

All processes will continue to be performed in the dedicated blood bank computer system. The COVID-19 antibody titers will be part of the donation record.

This is NOT a complete list of criteria.  Transfusion Medicine personnel will screen according to the full donor criteria.  Thus, donors passing the pre-screening may still be otherwise disqualified based on the detailed process.

8/11/20

COVID-19 Convalescent Plasma Revisited:

In February, 2020, I developed a program for convalescent COVID-19 plasma at Hamad Medical Corporation in Doha.  In early March, 2020, our program started collecting CCP by apheresis.  We started before the software modifications were completed since there were urgent requests by the clinicians for the product.

I proposed the software specifications and our vendor Medinfo Hematos IIG implemented them within 2-3 weeks, after which they were implemented/validated

Thus, now we have 8 month experience has been 8 months since starting manually and more than 7 months using a specific modification of our blood bank software Medinfo.

A complete manual system was implemented with quarantined registration, screening, collection, processing, and release.  Only the donor marker testing was shared with the regular donors.  This was built into the computer system.

Upon review, these are my current thoughts on our processes:

  1. Actively monitor supply requests:  Keep good communication between ordering/treating physicians and apheresis unit to optimize the stock according to patient needs.
  2. Collect/process/release separately from regular donations.
  3. Use dedicated quarantine equipment (apheresis, processing, storage refrigerators)
  4. Collect manufacturer’s recommended maximum of plasma based on body weight.
  5. Use pre-donation screening to allow quick release of components and avoid wasting apheresis kits.
  6. Repeat testing on the new specimen collected at the time of apheresis donation.
  7. Process units by same processes used for normal donations, including pathogen-inactivation.
  8. Use standard processes for release of blood components to end-users.
  9. Restrict ordering to designated treating COVID-19 physicians (enforce in computer system)
  10. Restrict release of CCP to designated non-blood bank staff from the quarantine storage location (enforce in computer system)

Notes:

  1. Include COVID-19 antibody testing and establish a threshold level (e.g. 1:128 titer) for donor qualification.  Do not collect if low-titer or absence of COVID-19 antibodies.   Store titer information with donation record.  Add antibody results to donation records that occurred before the assay was available.
  2. Review of donor criteria:  are there increased risks using these recovered donors:  cardiac or respiratory risk?  Is there a way to continuously monitor CCP donors’s vital signs during the donation?
  3. Collect apheresis components only in pre-screened donors:  Apheresis kits are expensive, use them only if the donor is prequalified, continue to retest when actual apheresis donation occurs
  4. Allow use of units directly after collection/processing as long as the other donor processing steps have been completed (allow blood bank computer system to use pre-donation specimen for marker testing criteria).

Irradiation of Blood Components

Principle:

The use of irradiated components is to inactivate antigen-processing cells, which have been implicated in transfusion-associated graft versus host disease (TAGVHD).  This condition is may be fatal and has been reported in a variety of clinical settings, both in immunocompromised and immunocompetent hosts.

Since we pathogen-inactivate platelet components, we are only irradiating RBC components.  There is no need to irradiate any plasma components (e.g. FP24, thawed plasma, cryoprecipitate, or cryo-poor plasma.)

WARNING:  Do not irradiate stem cell units!!

Policy:

  1. Irradiation of packed RBCs will be given to the following patients:
    1. All candidates for stem cell transplantation SCT or patients post-SCT
    1. All severely immunosuppressed, excluding AIDS patients including:
      1. Congenital immunodeficiency states
      1. Intrauterine (i.e. fetal) transfusions
      1. Premature (less than 1500 grams or 28 weeks gestation) infant transfusions
    1. Neonatal Intensive Care Unit patients
    1. All hematopoietic tumors, including
      1. Hodgkin’s disease/lymphoma
      1. Non-Hodgkin’s lymphomas
      1. All acute leukemias
      1. Myelodysplastic states
      1. Myeloproliferative states
      1. Histiocytosis X, Langerhans histiocytosis
      1. Aplastic anemia
    1. All recipients of directed donations of any type, i.e. apheresis or components prepared from whole blood
    1. Recipients of HLA-selected platelets or platelets known to be HLA homozygous
  2. Irradiation Specification:
    1. Irradiate just prior to release if possible to minimize potassium leakage.
    1. Target 2500 cGy (rads) of gamma irradiation to the mid-plane of the canister of a free-standing irradiator is used or to the central mid-plane of the irradiation field if a radiotherapy instrument is used
  3. Using returned irradiated RBCs:
    1. If an irradiated unit is returned and otherwise meets re-release criteria, it may be used for up to 28 days after the irradiation or the normal outdate limit, whichever is less.
    1. For pediatric use (< 20 kg.), if the component was irradiated more than 24 hours previously, wash it prior to transfusion.

If you are uncertain whether to irradiate, ask the supervisor or the transfusion medicine physician.

References:

  1. Standards for Blood Banks and Transfusion Services, Current Edition, American Association of Blood Banks, Bethesda, MD, USA.
  2. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

4/11/20