This is a revised version of a previous post.

Teaching medical and technical staff transfusion medicine
This is a revised version of a previous post.
This is a revised version of a previous post.
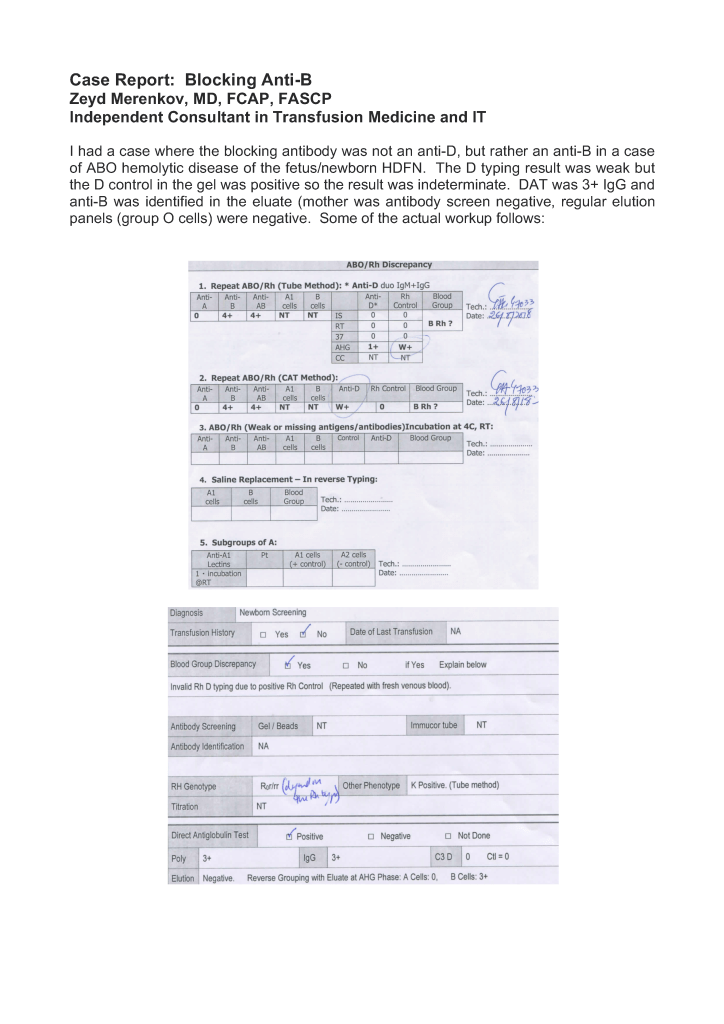
If there is strong antibody binding to an RBC, this may interfere with a typing reagent attaching to the cell and cause a false-negative, i.e. a “blocking” antibody. Such cells may interfere with the indirect antiglobulin test IAT, i.e. the antibody screen. The autocontrol and direct antiglobulin test DAT will be strongly positive.
The manufacturer’s instructions for using its reagents should be strictly followed in the presence of a strongly positive DAT. If there is no reaction with the typing reagent, the result must be indeterminate.
One could try a (relatively) nondestructive elution method such as gentle-heat elution to remove some of the antibody and then retype the cells. I have found this to be a simple and effective method for my staff to use. Just remember that despite being “gentle,” there will still be some hemolysis present, but here it is the cells we are trying to save.
Usually, we find this situation in a neonate born of a mother with anti-D. The baby has a strong DAT but the D typing is negative. Check the D control carefully: if it is positive, the result is indeterminate, try another method. Usually gel/glass bead methods are subject to less interference. Finally, there is always the classic saline anti-D!
In Medinfo software with a blocking antibody, a nonnegative control will trigger a manual review of the results. There will be no automatic release.
Here is my process for handling blocking antibodies, which I set up for HMC Doha:
INTERIM POLICY: ANTIGEN TYPINGS IN PRESENCE OF STRONGLY POSITIVE DIRECT ANTIGLOBULIN TEST (DAT): RULE OUT BLOCKING ANTIBODY
Principle:
Antigen typing of cells with large amounts of coating antibody (i.e. strongly positive DAT 3-4+) may not always be possible because the bound antibody may block available antigen sites. This policy is to clarify how to recognize and handle such situations.
Policy:
References:
One has to learn when enough is enough. There are times when there are staff shortages but the conscientious staff wants to be the Super-Tech and handle all the work, whether or not there are sufficient resources. This is a big gamble, and there may be serious consequences for the over-achiever and for the patient.
Anecdote #1: Chicago Blizzard of 1979 (13-14 January):
When I was in my residency training in Chicago, I was in the blood bank during the blizzard of January, 1979. The following tragedy occurred.
Suse was one of the best blood bank technologists that I have ever known, extremely conscientious and very meticulous—and very fast at doing things. She was a workaholic. Suse’s whole life centered on her job at our academic medical center—so much so that she had an apartment near the hospital complex. In mid-January, a snow storm was predicted with an estimated snowfall of about 5 cm. total. Actually, that night a blizzard developed and around a meter of snow fell with white-out conditions and zero visibility. Preoperative patients had been admitted the night before based on the low snowfall prediction.
The next day was chaos. Essentially only staff who lived near the hospital complex could report to work. Suse came in and saw all the pending preoperative blood requests. She decided to “double-up” and work on two cases at one time. In the rush, she mixed up test tubes and issued ABO-incompatible blood for a surgical case. The surgeon noted the abnormal oozing of blood at the operative site and stopped the transfusion. Hematuria developed, but the patient survived.
Suse was suspended pending investigation. Based on her excellent work record, she was offered to return to work. Unfortunately, she became very depressed and was afraid to return since she feared she would make another mistake. She never worked in the blood bank again.
Anecdote #2: Shortage of Blood at Major Hospital:
1991 in another country, a large hospital complex was suffering a shortage of blood. A large number of donors were called and the available staff were overwhelmed with work. One donor phlebotomist decided to collect whole blood from two different donors simultaneously and in the confusion, mixed up the sample tubes for donor marker testing.
Unfortunately, one of those donors was HBsAg positive, but with the specimen mix-up was marked as negative. The unit of blood was transfused, and the recipient developed fulminant hepatitis B and died.
Analysis:
In both these systems, there were processes in effect not to work on two patient specimens or collect two donors at one time, but the staff took short-cuts.
No one is super-human. Don’t try to cut corners and handle more than one patient at a time. Your intention may be good, but you will be judged by the consequences. No one will care about the extenuating circumstances. You will be blamed. I tell my staff that if they cannot handle the workload, they should contact me as the Division Head, Transfusion Medicine, to triage the cases for them. My role is to bring these events to the higher authorities to get the resources we need to do the work properly and safely.
This is an update of a previous post.
Principle:
All therapeutic apheresis procedures are potentially life-threatening and must only occur by an order from a transfusion medicine physician with experience/competence in such procedures.
Definitions:
Policy:
References:
This is a revision of a previous post.
Documenting Processes:
My previous post emphasized how important it is to map the current state across all processes as the first step to optimize current operations and prepare for a new computer system.
One non-blood bank vendor submitted the following as a complete representation of all current processes—across more than 4,000 tests and hundreds of instruments:
This was the same for each of the tests in the different sections of the laboratory—be it blood bank, anatomic pathology, chemistry, hematology, etc. I was flabbergasted! What were we paying for?
As Head of the Laboratory Information Systems, I rejected this. I would have been ashamed to submit this to a client as a sufficient current state. Even more astounding was the fact that that vendor actually mainly used the same four-step flow chart for the tests in their new computer build!!
As painful and time-consuming as it is, one must develop a specific flow for each process. This could include:
When we built our first dedicated blood bank computer system, the company would take a module and completely map out the current processes collaboratively with me. After this, I analyzed the critical control points and started to map out the improved computer processes that would take over. I did not want to throw out the successful manual system, just to optimize it. After that we would build that those limited processes in the software and test it. If it failed, we would correct it, and the vendor didn’t charge us extra for the corrections. It was a beautiful collaboration.
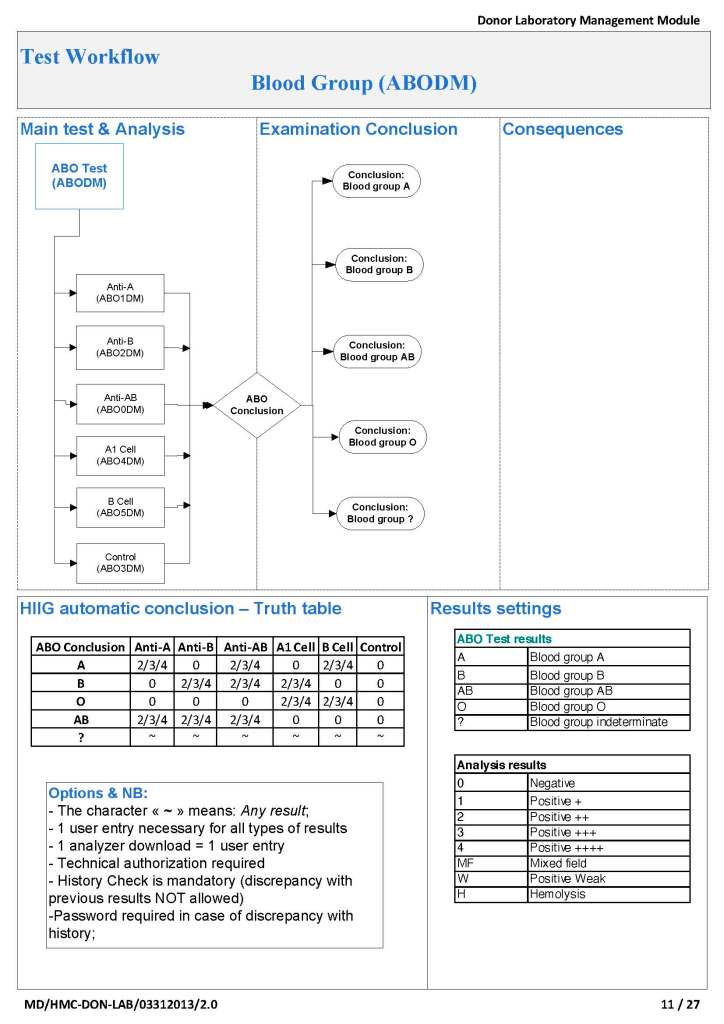
To illustrate these points, I am showing two process flows from our Medinfo Hematos IIG build: one for the ABO typing (forward and reverse) for donors and the other a complex testing algorithm flow for HCV donor marker testing. These are from previous builds and have been updated subsequently.
ABO Typing: Attachment One
This consisted of six individual tests forward (anti-A, anti-B, anti-A,B), two reverse (A1 cells and B cells) and a control. The acceptable tests for automatic typing were in {0, 2, 3, 4}, other results (mixed field, weak, 1+, hemolysis) required a manual interpretation. There is a truth table for interpretation of all six results together.
Donor HCV Testing: Attachment Two
This is a more complicated flow that includes multiple tests (HCV-antibody EIA, HCV-LIA, and HCV-NAT). Results may trigger reflex testing immediately (abnormal HCV EIA triggers HCV-LIA, abnormal HCV-NAT triggers HCV-LIA, etc.) or repeat testing after six months for indeterminate results.
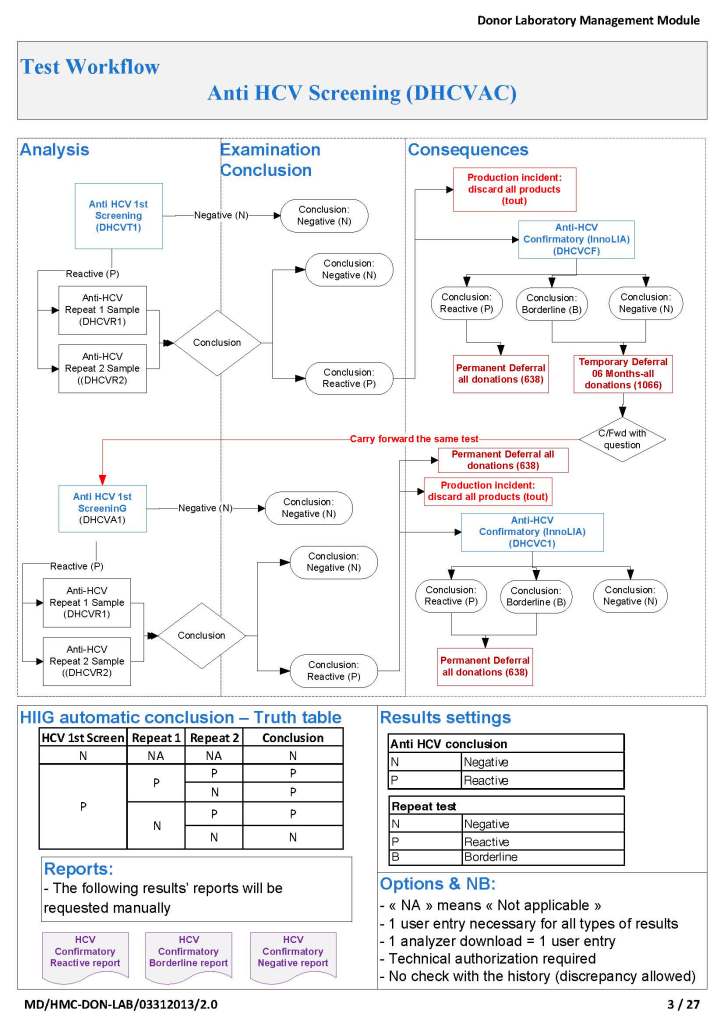
In each case, every possible result is listed and its interpretation and acceptability criteria.
In summary, it may take considerable time to map out all your processes, but this is time well spent and allows you build your system accurately. There will be few surprises this way.
Note: This is a repost.
I cannot emphasize enough proper technique in doing the washing during the elution process. We are usually concerned about too little washing and thus possibly residual reactions in the last wash. However, aggressive overwashing may remove the bound antibody resulting in a negative result.
Here is an example of anti-PP1Pk (alias anti-Tja). The mother’s panel shows an antibody to a high prevalence/incidence antigen with negative autocontrol and no lability at enzyme phase:

The neonate’s DAT was weak positive at polyspecific and IgG monospecific phases. An eluate was performed. Here is the result after washing four (4) times:
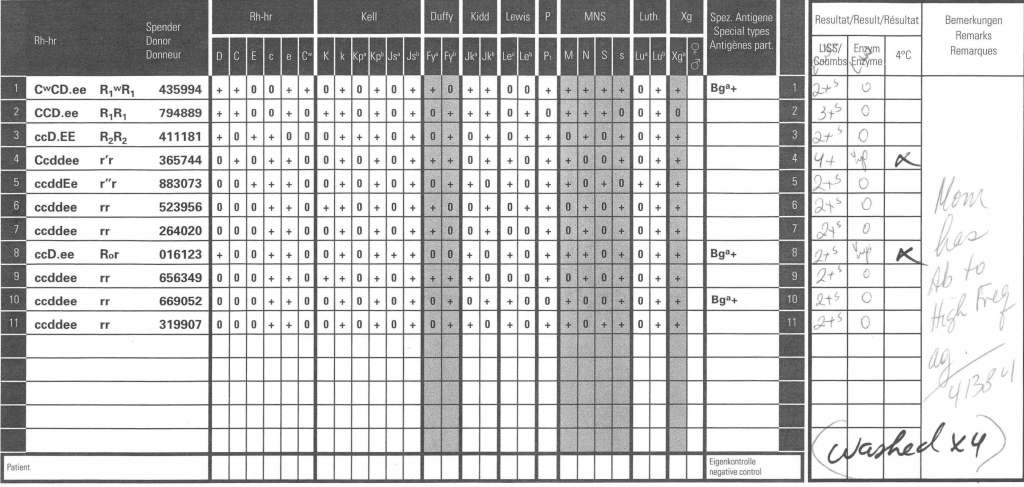
Since 2 cells in the last wash were very weakly positive, the washing was continued for a total of 9 times with the following results:
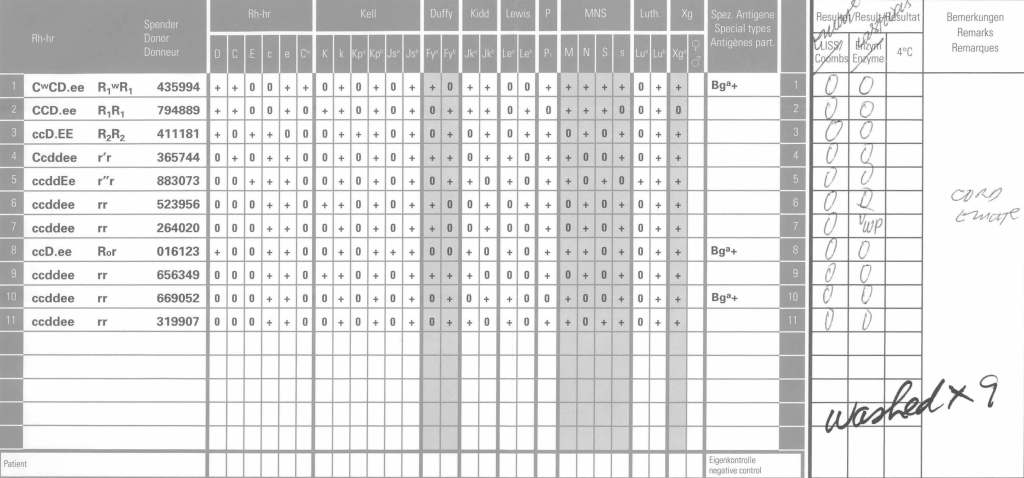
Even then there was very weak positivity in one cell, but the eluate was negative. We had washed away the attached antibodies.
My practice across the globe has exposed me different rationales to performing antibody titration. In my American training and practice (and also at international institutions following the American version of AABB accreditation), I only routinely performed titration of anti-D for Rh(D) hemolytic disease of the newborn and anti-A/anti-B for ABO-incompatible stem cell transplants AND ABO-incompatible renal transplants.
I have had heated arguments with some physicians who insisted they wanted titers for other antibodies. The AABB Standards do not require this but leave it to the discretion of the Transfusion Service Medical Director.
In my entire career, I never worked in a blood bank or blood center which had optimal staffing or resources. I focused on what was medically/technically necessary and even then still had shortages. If performing a test does not change the clinical treatment, why perform it unless you are doing a research project!
Titration is a time-consuming, and until recently, a tedious manual task. Recently some of the automated immunohematology analyzers offer a titration program. We used the Ortho Vision Max which could perform both IgG and IgM titers within one hour—walk away!! However, during that time, the titration procedure monopolized the analyzer.
Nowadays, low-anti-B-titer group A universal plasma and low-titer (anti-A and anti-B) group O whole blood may be offered as components. At HMC Qatar, a preliminary study showed about 50% of units could be classified as low-titer (defined as a saline titer <1:128). The amount of titration will require an automated analyzer.
The ABO-incompatible renal transplant program at HMC Qatar was modelled after Sweden’s Karolinska Institute. However the latter site performed manual IgG and IgM titrations using Biorad/Diamed gels.
I did not have sufficient resources to commit staff to manual titration at HMC so I did a comparison study between the Ortho Max and the Biorad manual gel methods. We were able to get good correlation and used the automated method for the transplant.
I still don not perform against performing titrations for antibodies other than anti-D. I always ask, ‘Does the titration correlate with clinical severity?’ Unlike anti-D, antibodies such as anti-Kell and anti-c may be low titer but cause death. Can anyone show me a definitive study that titers are useful except for transplants and Rh(D) hemolytic disease of the fetus/newborn?
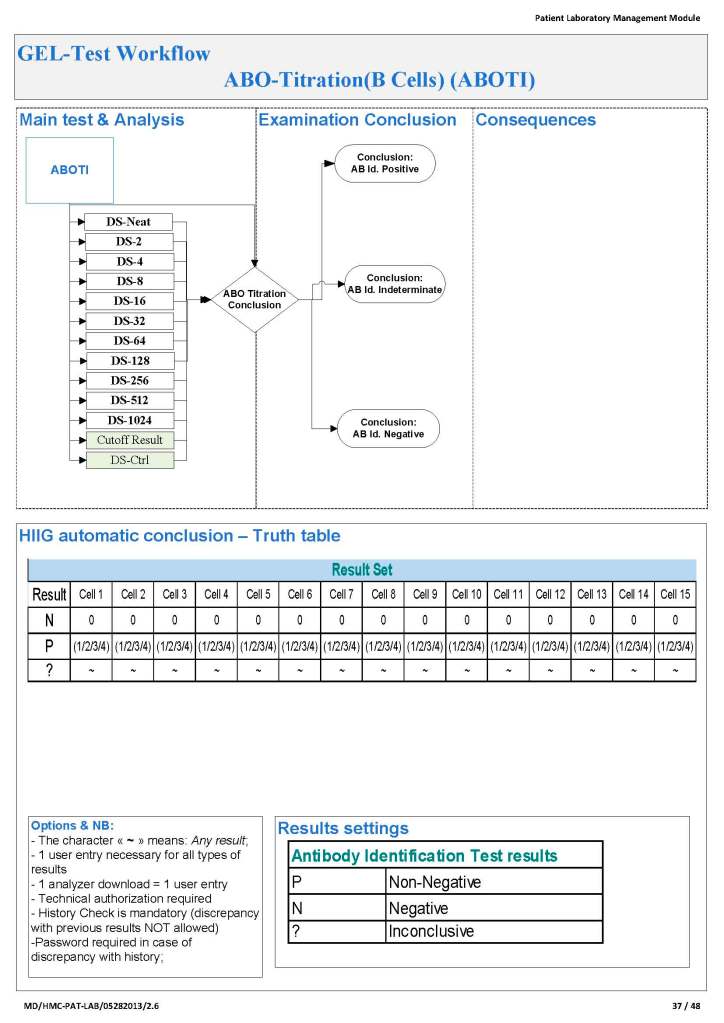
Since the method was working well on the Ortho equipment, I next established an interface to Medinfo. The test was performed separately for IgG and IgM antibodies. Medinfo recorded the reactions in all the wells. The last well showing a 1+ reaction was interpreted as the titer (e.g. if 1:64 were the last 1+ reaction, then the titer was 64 in Medinfo).
The Medinfo process is shown below.
In a series of posts, I will elaborate on how I built the processes and settings for a blood bank computer system in conjunction with the vendor’s software engineers. This also applies to other laboratory software.
If you don’t know exactly what you are doing, how can you improve it? Regardless whether you currently have laboratory software, you still need to optimize processes, determine critical control points, and plan improvements based on that. A good manual system is the foundation for a good software build.
I was never taught in medical school how to do this. I learned on-the-job at a time when software was quite rudimentary and mainly to record results.
Staffing:
For our first system, we used medical technologists to make settings for and administrate. We thought that only those with a technical background in the field could do this. It was moderately successful. There was some antagonism between the technologist computer staff and the hospital computer department. The technologists did not have a background in databases and programming; the IT staff did not know the laboratory and were frustrated in dealing with the laboratory staff.
Later, to help reconciliate the two when a new hospital system was installed, we tried a different approach. We found a database professional who was a very good listener. Although he had no blood bank technical background, he could listen and map out the processes. He was well-liked by the technologists who saw that he just wanted to understand their work and help them. He was very successful in this endeavor. I strongly recommend a software engineer as the lead in the project, one who can work with technical and medical staff to map out processes.
Unifying Processes Across Multiple Sites;
If your organization covers multiple sites, it is best to unify your processes as much as possible. We built our dedicated blood bank system AFTER we had done this so the processes (except for some equipment differences) were the same everywhere. This allowed us to move work between institutions quickly and makes system administration easy.
At one organization, I worked at, they had not done this. They built their system based on the processes at the first site to go live, which was a small hospital with less than 10% of the workload. It was not designed for the high-volume sites, and this was major problem as the larger sites were implemented.
Capturing the Current State:
Most importantly, I cannot emphasize enough the need to capture the current state. Take the time to do this properly and thoroughly. This will help you whether or not you are building a computer system or just optimizing your manual processes.
At one institution in a non-blood bank system build, the administrative decision was to rush and not wait to complete this task so the actual processes were not captured—I actually rejected the proposed current state but was overruled. The institution did not unify their processes as much as possible across sites. The result was a suboptimal system that many/most people do not like: should you blame the build or the limitations of the underlying software? In my opinion, you can’t fully blame the software itself, if you didn’t design your build properly.
This is an updated version of a previous post.
Working for many years in the Middle East/Gulf, I have encountered significant antibodies that can only be detected at enzyme phase. This is especially true of Rh system antibodies, particularly anti-c in an R1R1 patient. I have attached an example.
The reasons I strongly recommend this practice are:
It is also important to consider which enzyme to use: bromelin, ficin, or papain usually and sometimes trypsin or chymotrypsin. They do not always attack at the same site.
In addition to most common MNSs and Duffy system antibodies, many Kell antibodies (e.g. K or K1, Kpa) are labile with papain: however, with ficin they may be partially labile, unaffected, or even enhanced.
Using enzymes is a double-edged sword since they may enhance cold antibodies and thus cause nonspecific reactions. Thus, I know many of you may not routinely include them in your workups.
It is essential to follow the manufacturer’s recommendations for their use. If you make your own enzyme-treated cells and prolong the incubation, you may get false positivity. You should also be careful about using potentiators with enzyme-treated cells—normally I run them in saline.
Since anti-c may cause severe hemolysis and severe hemolytic disease of the newborn, I am especially vigilant in my R1R1 patients, particularly females of child-bearing age and all chronically transfused patients. I prophylactically match R1R1 patients with R1R1 RBCs in these categories, regardless if either anti-E or anti-c are expressed. I have seen many examples where the anti-c is only detected at enzyme phase.
It is my practice to always include an enzyme panel. I would be very interested to know your practices? When do you use enzymes?
Principle:
All donor unit mislabeling is potentially life-threatening and must be stringently investigated as soon as possible after the discrepancy is detected. Most importantly, if there is one error, there may be possibly ADDITIONAL donor unit errors (e.g. switch of donor tubes or units, etc.). All donor units processed in the same batch must be also quarantined until the discrepancies are resolved.
Definitions:
Responsible blood bank physician: specialist or consultant physician on-call at the time the discrepancy is detected
Policy Details:
The following steps MUST be performed as soon as possible:
 Dr. Zeyd Merenkov
