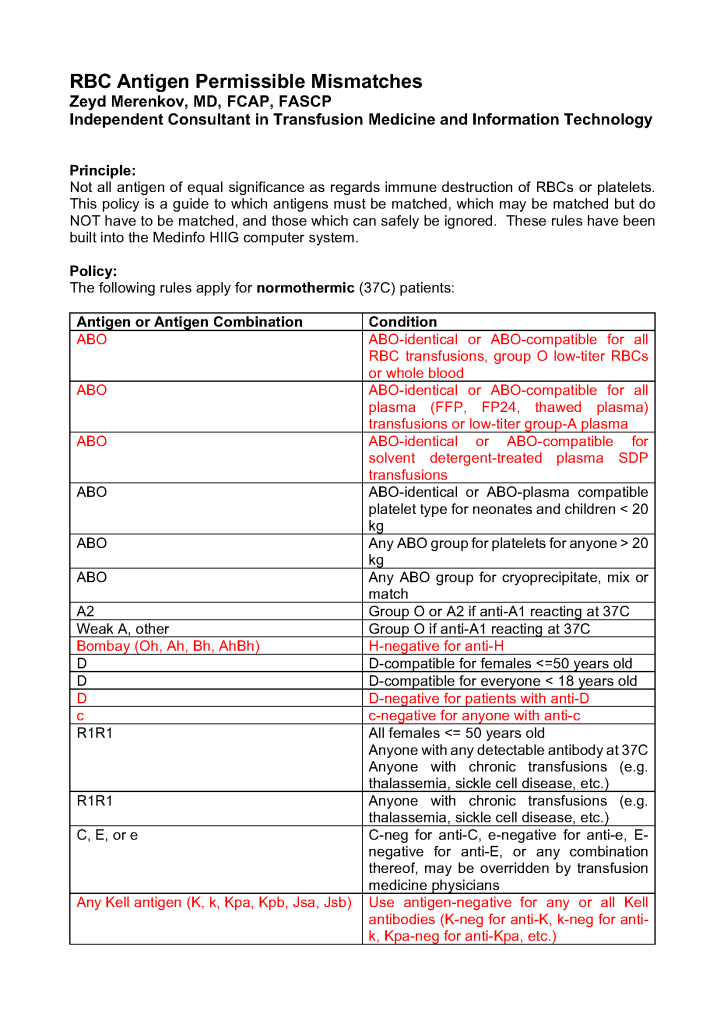
Permissible RBC Type Mismatching

The following was my interim policy at HMC for permissible matching and mismatching. This assumes that the patient is not being transfused while in a hypothermic state.

The prohibited options were blocked in the Medinfo Hematos IIG computer system. WAIHA least-incompatible release required physician approval. This protocol did not apply to low-titer group A or low-ABO-titer whole blood units, which were not available at the time.

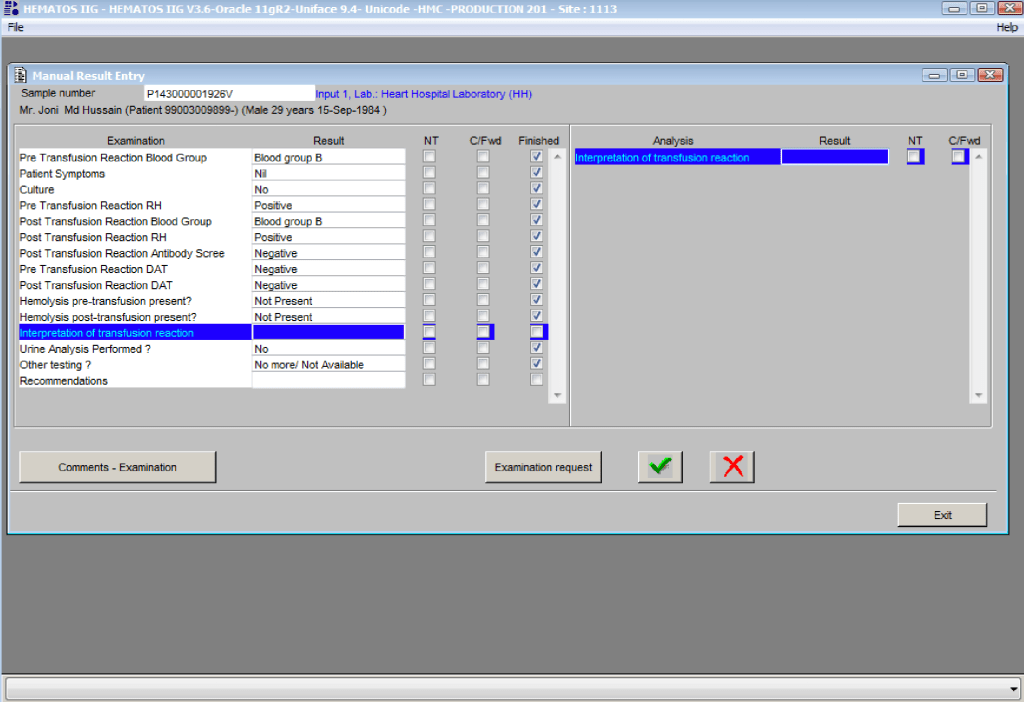
Physician Review and Data Entry of Transfusion Reactions

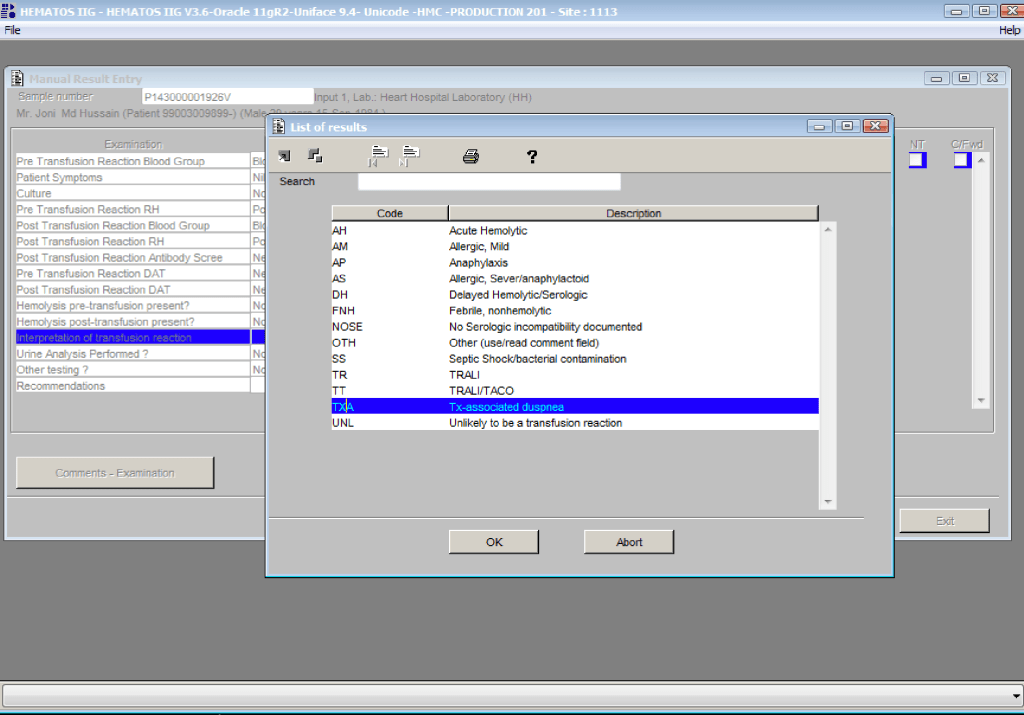
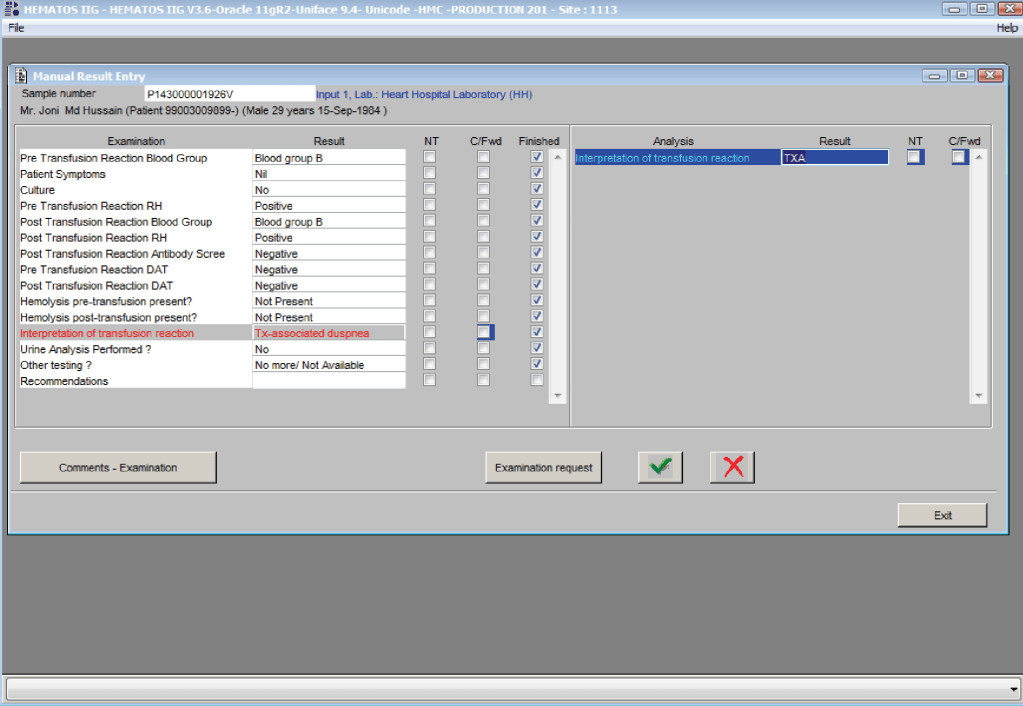
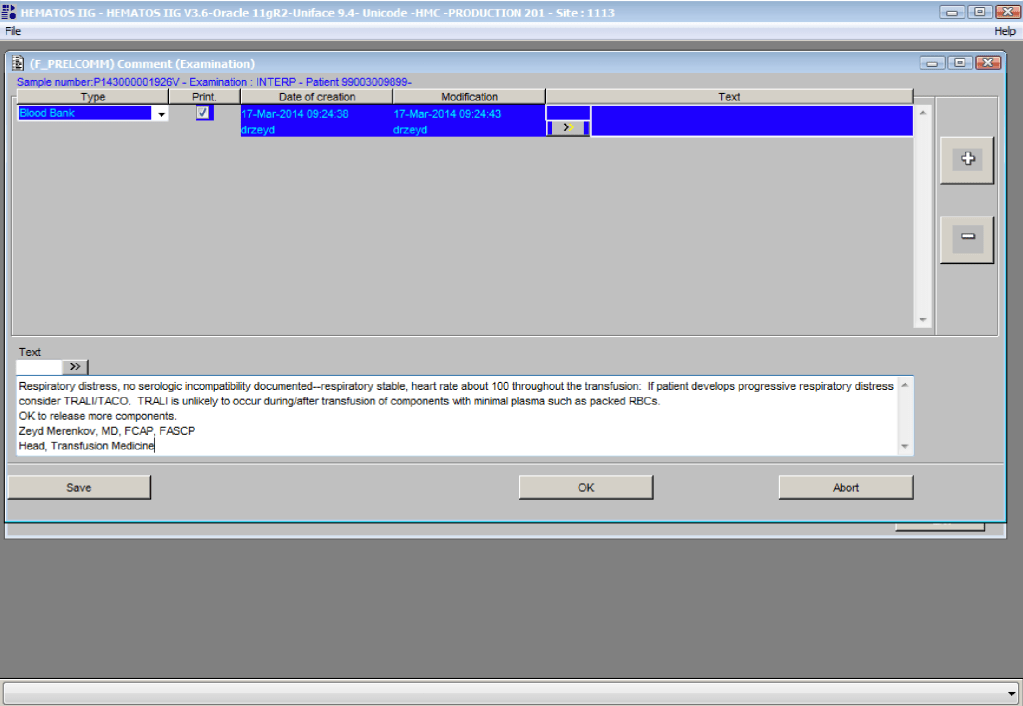
Physicians must enter their interpretations and recommendations for each transfusion reaction review.  In addition, they may enter comments against any of the data.  This post shows the process used in Medinfo Hematos IIG.

By highlighting Interpretation (left side), they then click on the Result Field (right side) and select their interpretation from the drop-down menu.  They can also select other and then enter a comment.

References:

  1. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  2. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

Clarification on Quality Control of Reagents for Antibody Screening and Identification

Principle:

This policy is a reiteration of current policy to QC reagents used for antibody screening and identification to document how current practice meets these requirements.  This policy is NOT a change from current practice.

Policy:

  1. Each cell used for antibody detection must be checked each day of use for reactivity of at least one antigen using antisera of 1+ or greater avidity:
    1. We will use reactivity encountered during the daily antibody testing:  reactions of 1+ in each screening cell will be deemed acceptable.  For panel cells, reactions of 1+ or greater for any specificity will be deemed acceptable.
  2. Typing reagents such as anti-D, anti-K, anti-Fya, etc. must be checked each day of use.
    1. Already defined explicitly in SOPs
  3. Anti-IgG reactivity of antiglobulin reagents may be checked during antibody screening and crossmatching:
    1. Currently performed as per manufacturer’s instructions (e.g., Immunocor, Biorad, Grifols, Ortho) for gel and tube reagents.
  4. Typing sera and reagent cells must be checked for reactivity and specificity on each day of use, including a check against known positive and negative cells or antisera:
    1. Already defined explicitly in SOPs

References:

  1. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  2. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition
  3. TRM.31400, CAP Checklist, current version

External Disaster Plan, Simplified

Principle:

Maintaining an adequate blood supply and expedited compatibility testing are critical in disaster planning.  Medinfo Hematos IIG allows us to get dynamic updates of our blood supply and dynamically reallocate blood components as needed.

Policy:

  1. Determinate total available blood supply across all locations by using the Cumulative Stock Display program in Medinfo Hematos IIG.
    1. Recheck stock at least every hour during the disaster.
  2. At each transfusion service site, in conjunction with a Transfusion Medicine Consultant:
    1. Cancel reservations for elective surgical and non-emergency medical cases of affected ABO/D types.
    2. Retain reservations for antigen-matched, oncology, NICU, and high-risk obstetrical cases.
  3. Inform Donor Recruitment/Logistics to send SMS, radio, and television messages for blood donors—all types.
  4. Contact ALL staff and have them report to duty.
    1. At the Blood Donor Center, the Head Nurse, Recruitment, Supervisor, Component Processing, and Supervisor, Marker Testing will contact staff.
    2. At hospital transfusion services, the site supervisor will contact all staff.
  5. Process blood components using automated component technology (Reveos).
  6. Perform all donor marker testing including single-well NAT.
    1. Abbreviation of donor marker testing is only at the discretion of the Division Head, Transfusion Medicine.
  7. Transfusion Services:
    1. Release blood component according to the various protocols as needed:
      1. Massive Transfusion Protocols
      2. Emergency release
      3. STAT
      4. Priority
      5. Routine
  8. Compatibility testing will be electronic, immediate-spin, or full AHG as per our protocols.

References:

  1. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  2. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

Data Entry Verification

Principle:

This policy outlines steps taken to minimize the risk of data entry errors and is based on a dualistic approach:  review of results by a senior technologist and/or supervisor and various computer safeguards built into the Medinfo Hematos IIG blood bank computer HIIG system.  This policy also discusses the verification (here called authorization) and purge processes of HIIG.

Policy:

  1. Review by senior technical, supervisory, or transfusion medical staff:
    1. Designated test procedures require review by a second technologist before authorization.
    2. Complex immunohematology testing and specimens showing aberrant results (e.g. ABO/D discrepancies) are reviewed by the supervisors or designates and ultimately a transfusion medicine physician before authorization.
  2. Computer system HIIG rules:
    1. Privileges:
      1. System restricts which staff can perform specific tests
    2. Patient/donor identity:
      1. System asks end-users to verify patient/donor identity before starting any access to the patient/donor record.
      2. System performs historical database checking and flags any inconsistencies (e.g. historical ABO/D typing differences, etc.)
    3. Testing:
      1. Only selected staff have privileges to authorize or purge.
      2. ABO/D testing algorithms require entry of reactions, not interpretation of results and are compared to a truth table.
        1. Aberrant results require special review before ABO/D typing results can be authorized/purged.
        2. D-controls must be negative to allow D typing results to be authorized for liquid D-typing reagents.
      3. DAT results require appropriate controls to meet truth-table criteria.
      4. Eluates require last wash to be negative before authorization
    4. Blood components:
      1. Selection of RBC or plasma units requires two independent sample determinations within 72 hours of each other.
      2. ABO-incompatible RBC or FFP/FP24 transfusions are not allowed.
      3. Donors with any detectable antibodies are permanently deferred.
      4. Depending on the patient’s antibody history, release of RBC units may require antigen-matched units.  Examples:
        1. Mandatory matching (only antigen negative matched units allowed—no antigen positive or antigen-untyped units):  Antibodies against H, D, c, K, k, Kpa, Kpb, Jsa, Jsb, Jka, Jkb antigens, anti-PP1Pk
        2. Priority matching (incompatible or untested can be approved by a transfusion medicine physician):  C,E, e, Fya, Fyb, M, S, s
        3. Antigen matching not required:  Lea, Leb, N
      5. Least-incompatible crossmatch require special authorization to release
      6. Protocols to force irradiation or other modified components can be setup in HIIG.
    5. Donors:
      1. Donor tests have same criteria as the same test used in patient testing for controls, etc.
      2. Donor demographics are read directly from the Ministry of Interior database—no manual entry (bar code only used).

References:

  1. Workflows for Hematos IIG (1001 through 1005), 2013-2020
  2. Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
  3. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

Patient Extended Rh and Kell Typing

Background:

Although we did extended Rh and Kell typing for all cases with a non-negative antibody screen, we did not routinely do this for patients with a negative antibody screen.

Principle:

Based on recent cases of rare phenotypes in the Rh system (e.g. r’r’), we will proactively test such patients most likely for this.

Policy:

Extended Rh (C, c, E, e) and Kell typing should be done on all patients meeting the any of the following criteria:

  1. D-negative phenotype
  2. Positive antibody identifications (not nonspecific)
  3. Non-negative antibody screens

Reference:

Standards for Blood Banks and Transfusion Services, AABB, Current Edition, Bethesda, MD, USA

Supervisory Candidate Examination

This is the sample examination I made for the senior-most staff and candidates. This is really a projective exercise. How far can you go with this? The candidate must specify what additional information he/she needs to complete the assessment.

Name:                                                                        Badge #:

Date of Exam:

Answer the following questions:

  1. What is the ABO blood type in each of the following results:
Anti-AAnti-BAnti-A,BA1 cellsB cellsO CellsABSType?
04+3+0000 
3+03+1+4+0Neg 
3+1+3+03+0Neg 
Weak02+04+0Neg 
0004+4+4+Pos, all cells 
Weak004+4+4+Pos, all cells 
04+3+4+2+0Pos, SCIII 
Mf0004+0Neg 

ABS = antibody screen; mf = mixed field reaction

Assume that all reactions are the same by both the tube and gel methods.

In the above table, list any discrepancies in each of the testing panels.  Describe what additional tests or information, if any, are required to resolve the type.

  1. What is ABO and D typing in each of the following results?
Anti-AAnti-BAnti-DD-controlA1 cellsB cellsO cellsABS
4+4+4+3+4+4+4+Pos All cells
Anti-AAnti-BAnti-DD-controlA1 cellsB cellsO cellsABS
004+2+4+4+00
Anti-AAnti-BAnti-DD-controlA1 cellsB cellsO cellsABS
004+2+4+4+2+2+
  1. Using anti-D antisera, explain the difference in reactivity you expect between R1R1 and R2R2 cells.
  1. Describe at least two antibody specificities associated with a mixed field reaction.
  1. Describe the discrepancy noted in the following gel reaction and provide a differential diagnosis for the possible cause(s).
  1. Describe when to use Diluent 1 versus Diluent 2 with the Diamed gel cards.
  1. There is a critical staffing shortage so you are working the bench when emergency, class I blood is released (O-positive to a 25 year old male victim of a car accident).  You receive the specimen and obtain the following set of results:

Anti-A—0, Anti-B—0, A1 cells—4+, B cells—4+, ABS—3+ in SCI/II/III

What actions will you take now?  What blood type will you release for subsequent RBC requests?  Be explicit!

  1. An extended phenotype is ordered and Diamed Profile I-II-III cards are used.  The following results are obtained on Profile Card III:
MNSSFyaFyb
000000

Interpret these results.

  1. Describe the rationale for the prophylactic use of E-c- cells in a patient only showing anti-E.
  1. A patient develops pain at the infusion site with back pain while a unit of packed RBCs is being transfused.  The following results were obtained in the subsequent workup:

Pretransfusion DAT:  negative

Post-transfusion DAT:  negative

Hemolysis Check—post-transfusion sample—strongly positive

Hemolysis check—pre-transfusion sample—negative

Clerical Check—OK

Pretransfusion ABO/D:  B-positive—reverse typing normal

Post-transfusion ABO/D:  B-positive—reverse typing normal

Returned unit ABO/D:  B-positive

Repeat crossmatch—compatible

Give possible reasons for these findings.  What further investigations would you do?

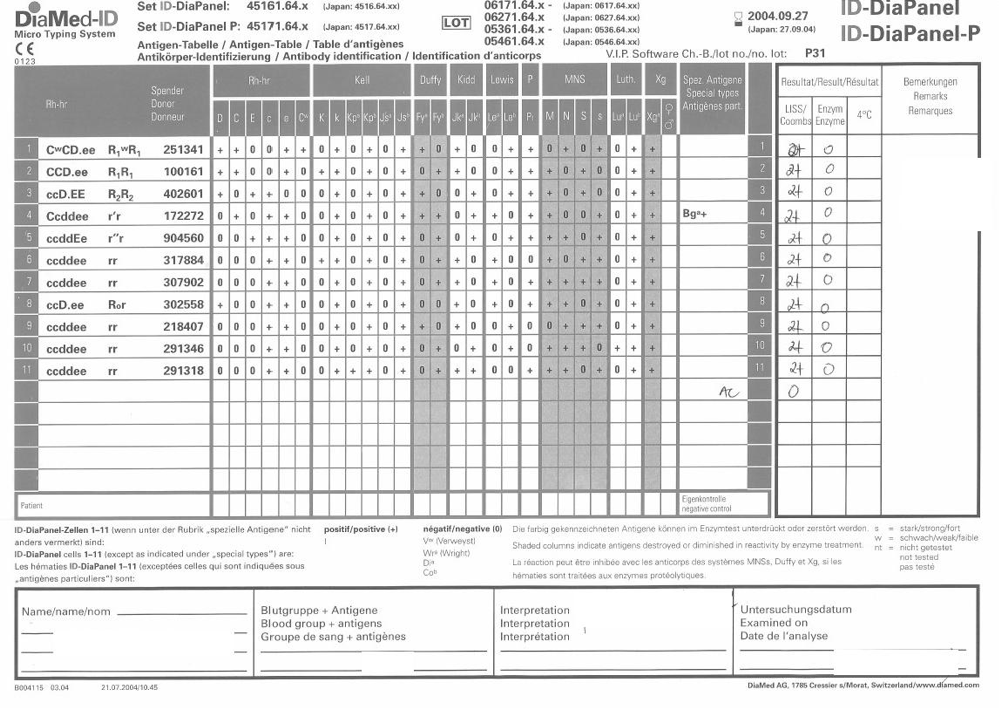
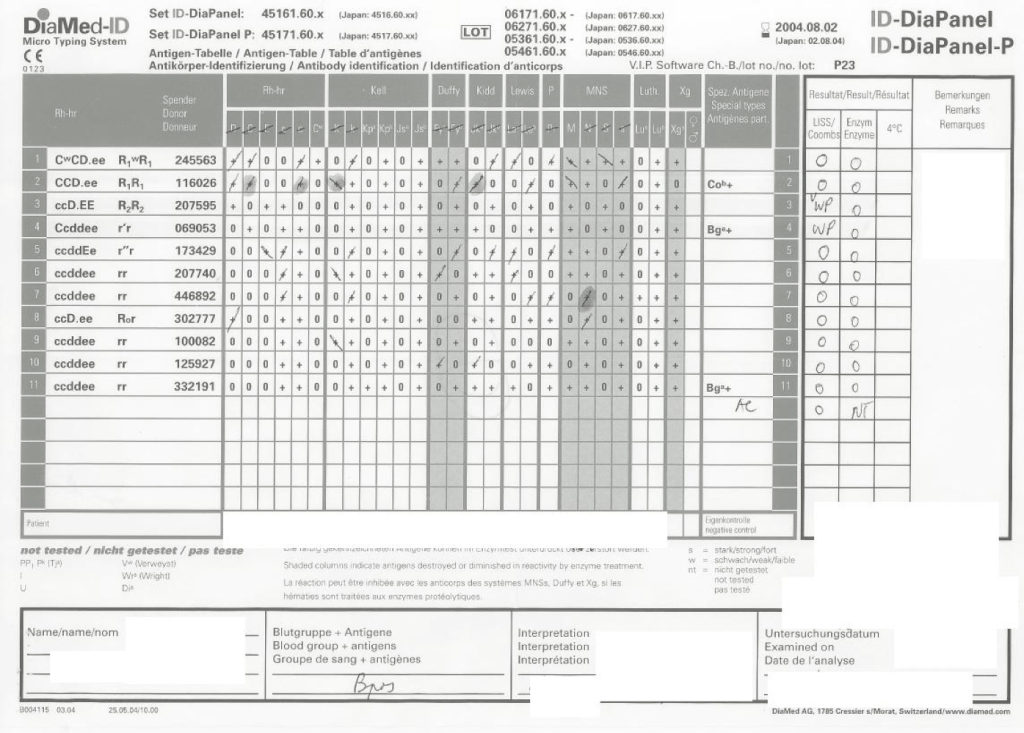
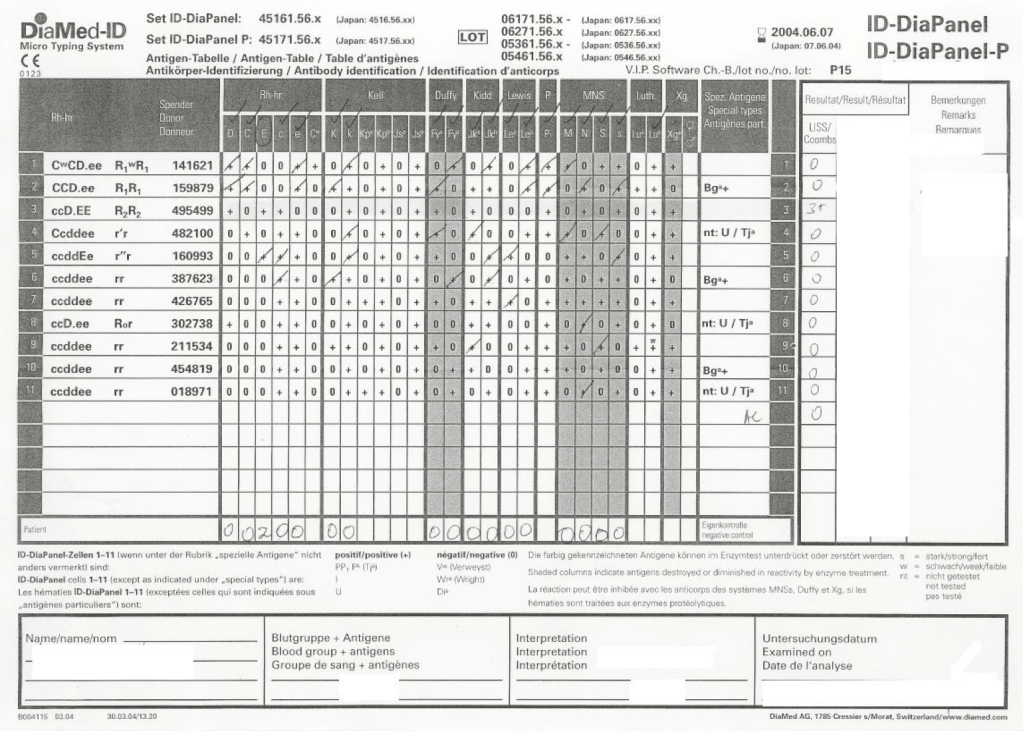
  1. Interpret the following panels:

48 year old female with septic arthritis and severe anemia (Hgb 6.9 g/dl) and positive autocontrol 2+ (Polyspecific 2+, IgG 2+, C3d nil) and negative antibody screen:

The eluate panel results follow:

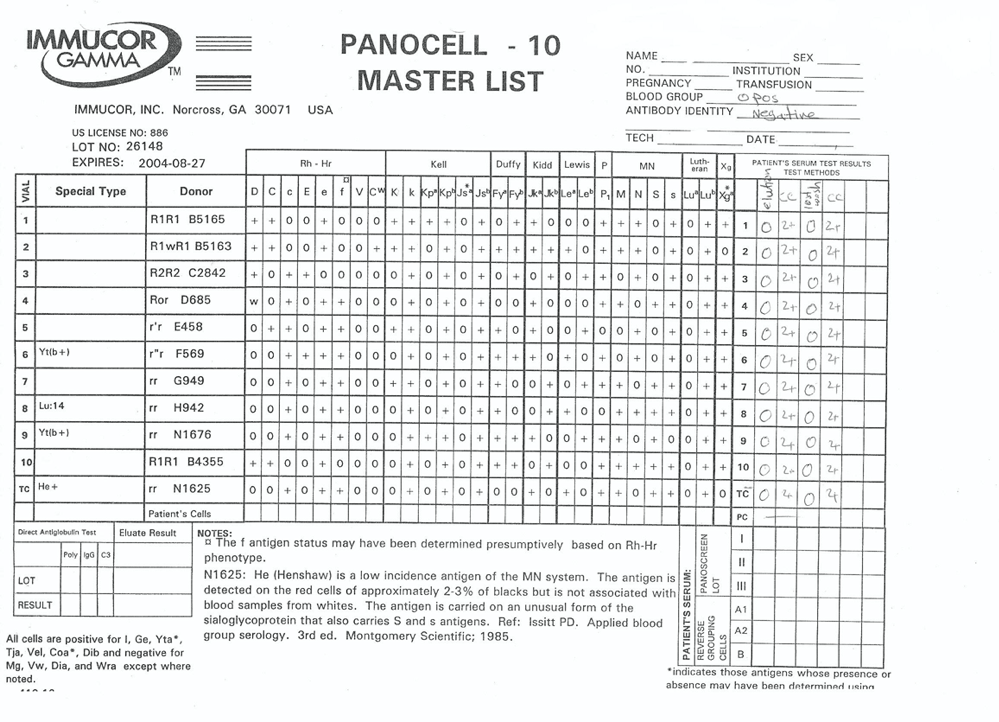
Please give your interpretation of the findings.  Be sure to specify other information you may require if any.

71 year old female with aortic stenosis admitted for surgical correction, blood type AB positive, antibody screen 2+ positive in all 3 cells, autocontrol negative, no history of recent transfusions.

Extended phenotype is:

C+E+c-e+K-k+Kpa-Kpb+Fya+Fyb-Jka-Jkb+Lea+Leb-P1+M+N-S+s-Lua-Lub+

Note:  Cell #1 reacts 2+ at LISS/Coombs using monospecific IgG IgG/Coombs Card.

60 year old male with paraplegia for surgery, B-positive, auto-control negative, no recent transfusion history:

39 year old, pregnant female—no previous history:

36 year old pregnant female, O-positive:

Interpret the panel.  What RBC phenotype would you transfuse?

60 year old male with paraplegia for surgery, B-positive, auto-control negative, no recent transfusion history:

Advice to Transfusion Medical Directors on the Selection of Blood Bank Software

Most Transfusion Medical Directors are not information technology IT people.  Still, regardless if you direct a hospital blood bank/transfusion service, a blood donor center, or both, you will still have to evaluate software for your operations.  You will probably have to sign off on the selection of a system and on the final build before going live.

This can be a formidable task, especially since none of us were trained in IT.  In my opinion, you can still do this based on your knowledge and experience and make a successful choice.

The most important thing is to KNOW YOUR OPERATIONS!!  Someone in your organization should map out all your processes, preferably as flow charts.  Optimize your manual processes.  Look at your critical control points:  How does the software enhance operations and safety?  How does the candidate system enhance security and consistency?  Does it bolster the critical control points?

My experience has been that the best software build is the one based on a good manual system.  Study the new candidates:  how do they enhance your operations?  Now reconstruct your processes with the enhanced features of the new system.

Don’t be afraid to ask for help.  Check your local resources and/or consider outside consultants if necessary.  The latter should have experience in working with blood bank systems and ideally have worked with your candidate vendors.

Human beings are not consistent creatures.  We often do not like following a series of steps in a processes, we like to skip around.  All of this is very dangerous to patient care.  The ideal system enforces consistency and integrity.  I actually like it when my staff complain that the software is merciless—they cannot take shortcuts.  They must follow each step in order!

Choosing a module from within a laboratory or hospital information system LIS/HIS will facilitate integration with the rest of system.  However, such modules (mainly limited to hospital blood banks) do not have all the features that a dedicated blood bank software has  For example, will they prevent release of unphenotyped or Kell-positive units in a patient with anti-Kell?

If you choose the dedicated system option, you must determine if a functioning interface to the LIS/HIS exists.  If not, what is the time frame to make the connection?  Very importantly, check that your specifications are actually built into the interface.  Almost every LIS/HIS vendor says that they can make an interface, but are they communicating what you need?  If you talk English and they answer you in Sanskrit, are you effectively communicating?

I prefer a dedicated blood bank system for both patients and donors, especially one that allows you to create rules to handling different situations like electronic/computer crossmatch, irradiation, etc.  Integrating both patient and donor operations will facilitate operations, especially in times of disaster and product recalls/quarantines.

Make certain that there are interfaces available for your analyzers and blood production equipment (e.g. Ortho Vision Max, Reveos, Mirasol, etc.).  Check these out on a site visit.  Many vendors promise that they can communicate with your equipment, but you must verify this yourself.

You are the pilot.  Is the transfusion or donor information organized to facilitate your decision making? Is it available all on one screen?  Do you have to flip across many screens to get the information (e.g. transfusion history, transfusion reactions, DAT, antibodies, donor history, marker testing) you need?

If you are directing a donor center, you will most likely need a separate dedicated software.  Usually, donor center software does not directly integrate into the LIS/HIS.  However, at least your patient hospital blood bank module must be able to read your ISBT labels properly.

I recommend a visit to a site comparable to your current operations.  Look for ease of use, response time, and talk privately with the end-users at the site.  Ask your IT staff to help you select a site that uses the same operating and database software (e.g. Oracle) as you will be using.

How readily can the system be modified for new practices?  With COVID-19, SARS, ZIKA, etc. there have been many changes in regulations in a short time.  How long will it take your vendor to update your system?  Is the system compliant with your local regulations and international accreditation standards?

Structurally, the optimal system is one that is a framework where almost all changes can be handled by changing settings or parameters.  The underlying structure does not change so this facilitates making the modification.  There is no need to “hard code” the changes.  You are not writing a new software structure.  Warning:  many blood bank softwares do not have this framework or flexibility—it takes a long time often even to make minor changes or updates.

Using blood bank software is like playing with fire.  Defects in design can adversely affect patient care.  The vendor will install the software with settings, but it is still YOUR responsibility to verify it works according to the specifications.

I recommend engaging computer-literate end-users (nurses, doctors, medical technologists, recruitment staff) .from the very beginning of the actual software build.  These staff can become Super Users to handle minor issues and train other staff and can help perform your software validations.

In summary, you will have to accept the choice of vendor and the final software build.  Find resources to help you with these tasks.  Never forget that what you are doing could adversely affect patient care if you are not vigilant!

4/11/20

Irradiation of Blood Components

Principle:

The use of irradiated components is to inactivate antigen-processing cells, which have been implicated in transfusion-associated graft versus host disease (TAGVHD).  This condition is may be fatal and has been reported in a variety of clinical settings, both in immunocompromised and immunocompetent hosts.

Since we pathogen-inactivate platelet components, we are only irradiating RBC components.  There is no need to irradiate any plasma components (e.g. FP24, thawed plasma, cryoprecipitate, or cryo-poor plasma.)

WARNING:  Do not irradiate stem cell units!!

Policy:

  1. Irradiation of packed RBCs will be given to the following patients:
    1. All candidates for stem cell transplantation SCT or patients post-SCT
    1. All severely immunosuppressed, excluding AIDS patients including:
      1. Congenital immunodeficiency states
      1. Intrauterine (i.e. fetal) transfusions
      1. Premature (less than 1500 grams or 28 weeks gestation) infant transfusions
    1. Neonatal Intensive Care Unit patients
    1. All hematopoietic tumors, including
      1. Hodgkin’s disease/lymphoma
      1. Non-Hodgkin’s lymphomas
      1. All acute leukemias
      1. Myelodysplastic states
      1. Myeloproliferative states
      1. Histiocytosis X, Langerhans histiocytosis
      1. Aplastic anemia
    1. All recipients of directed donations of any type, i.e. apheresis or components prepared from whole blood
    1. Recipients of HLA-selected platelets or platelets known to be HLA homozygous
  2. Irradiation Specification:
    1. Irradiate just prior to release if possible to minimize potassium leakage.
    1. Target 2500 cGy (rads) of gamma irradiation to the mid-plane of the canister of a free-standing irradiator is used or to the central mid-plane of the irradiation field if a radiotherapy instrument is used
  3. Using returned irradiated RBCs:
    1. If an irradiated unit is returned and otherwise meets re-release criteria, it may be used for up to 28 days after the irradiation or the normal outdate limit, whichever is less.
    1. For pediatric use (< 20 kg.), if the component was irradiated more than 24 hours previously, wash it prior to transfusion.

If you are uncertain whether to irradiate, ask the supervisor or the transfusion medicine physician.

References:

  1. Standards for Blood Banks and Transfusion Services, Current Edition, American Association of Blood Banks, Bethesda, MD, USA.
  2. Guidelines to the Preparation, Use, and Quality Assurance of Blood Components, European Committee (Partial Agreement) on Blood Transfusion (CD-P-TS), Current Edition

4/11/20

Blood Bank Software is Dynamic, NOT Static

I was recently talking with one of the hospital software system administrators from my previous site.  He had originally worked on building the Medinfo system, but was then reassigned to the laboratory modules of the hospital information system.

His alarming comment to me was that the Medinfo build was completed so there was no need to worry about it now—it was finished.  I guess he was looking from the perspective of the general laboratory software.  There is no need to make major changes to the build, just update interfaces and troubleshoot.

I was surprised.  He had no idea of how many times we have to update the structure for new rules and regulations, and changes in blood bank practice—let alone emerging pathogens such as ZIKA, dengue, Chikungunya, and most recently, COVID-19.

My daily morning routine was to survey several blood bank websites with changes to blood donor criteria including US FDA CBER, read the transfusion journals (Transfusion, Vox Sanguis, etc.), AABB, and ASFA.  If there were any changes pertinent to our organization, I had to make interim policies and procedures, and finally prepare specifications for changes in the Medinfo software.

The Medinfo engineers would prepare flow charts of the proposed changes and implement them in a test environment for the Super-Users to test.  I had to prepare validation protocols for the testing, and then review the validation results and finally approve the adoption of the changes.

I cannot remember even a month going by without some revision in the donor protocols.  When COVID-19 came, I had to prepare a parallel, but separate, processing and allocation/release system.

This was a never-ending story that kept the Super Users and the local Medinfo engineers busy.  I always reminded the hospital information system staff that playing with blood bank software was like playing with fire:  there is a good chance you will get burned if you do not set it up properly.

31/10/20