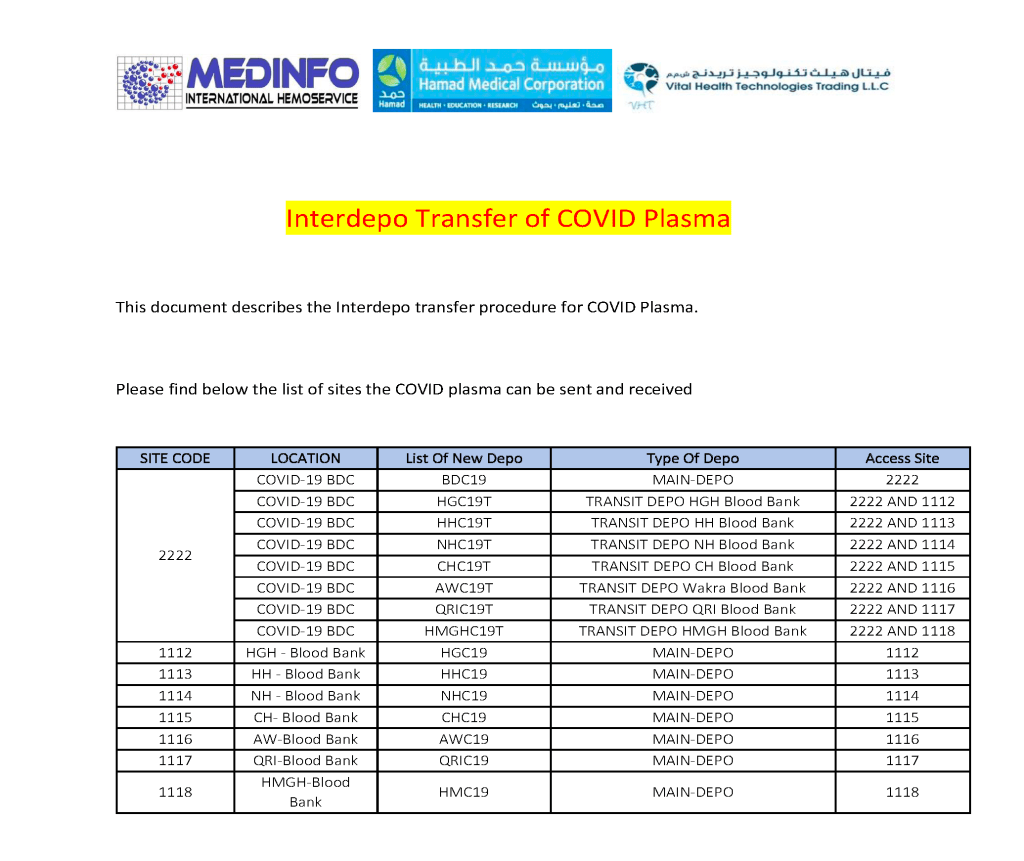
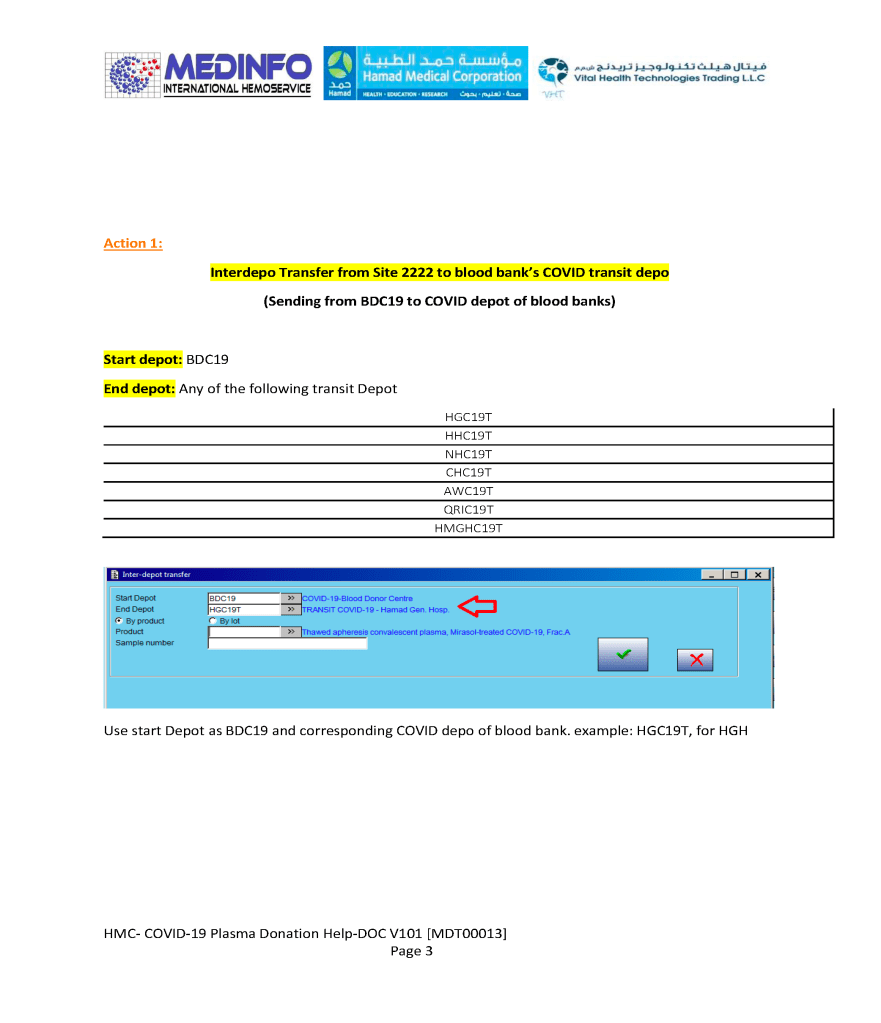
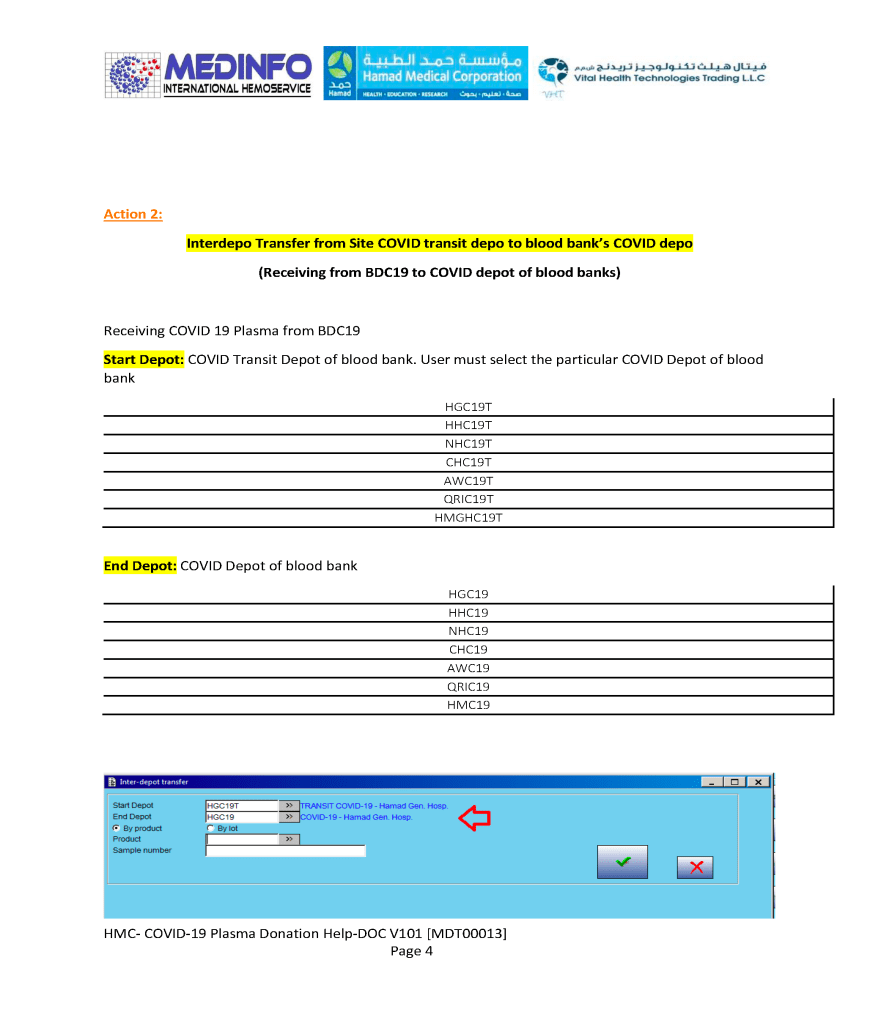
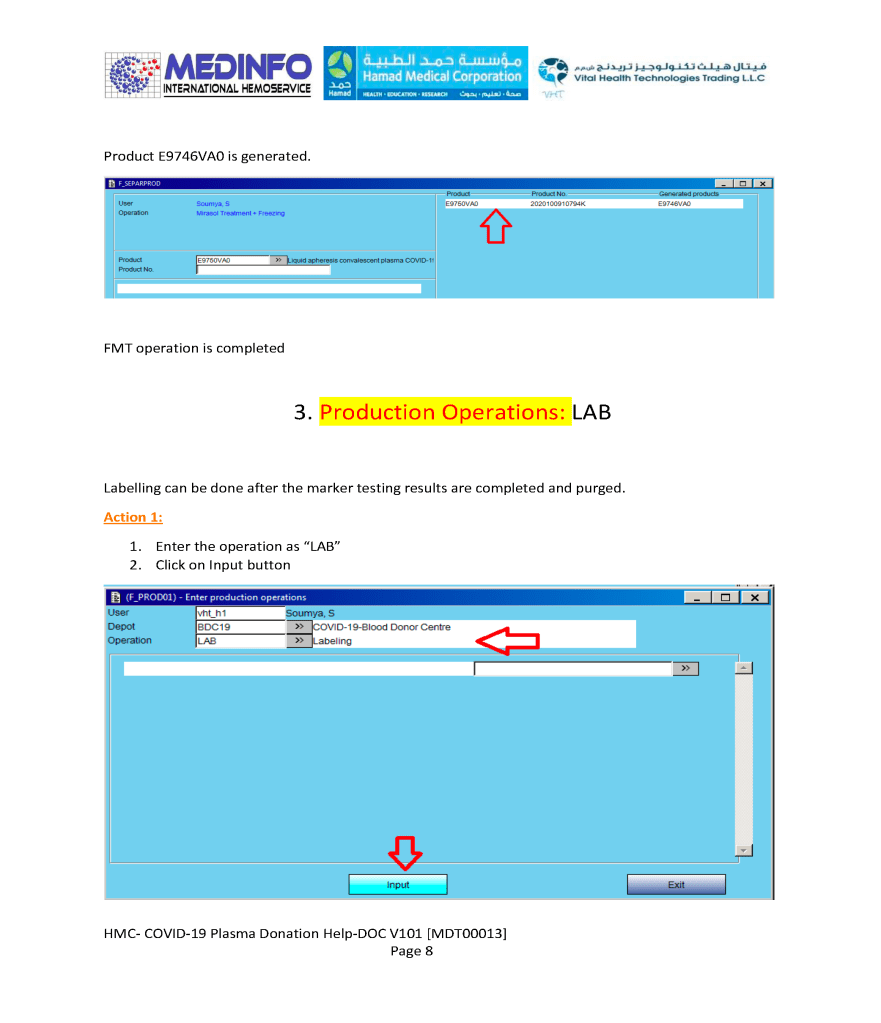
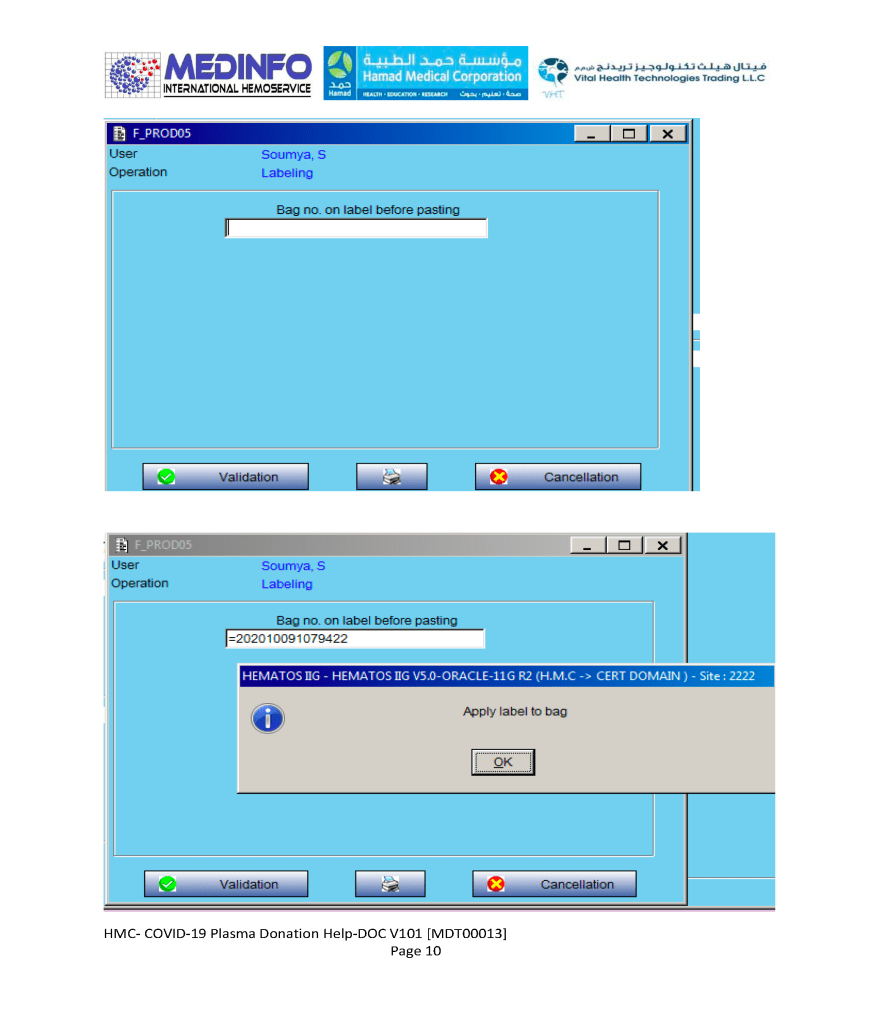
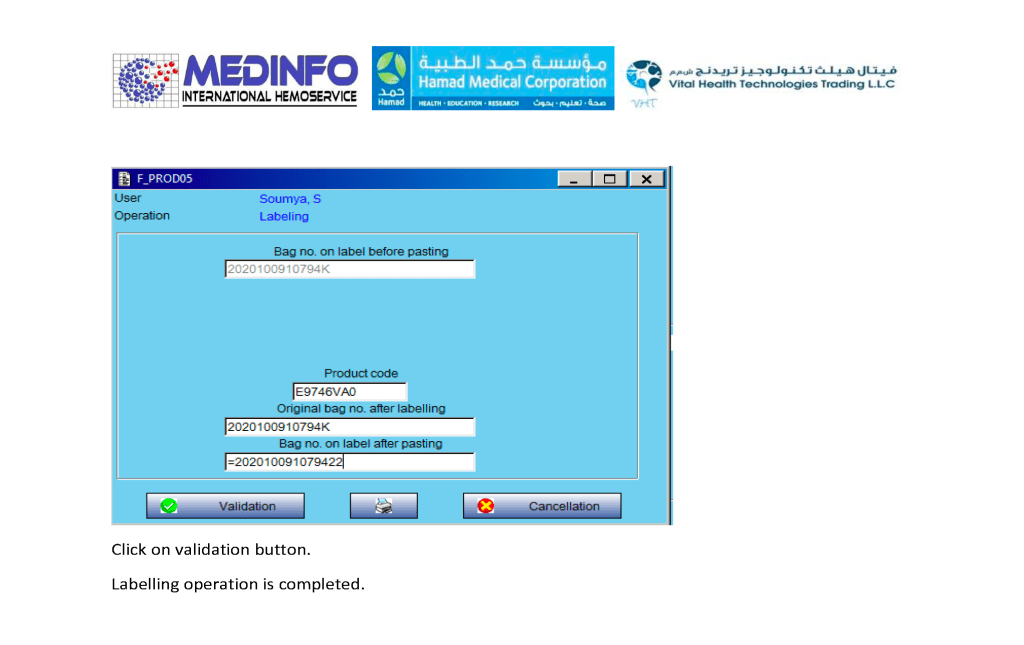
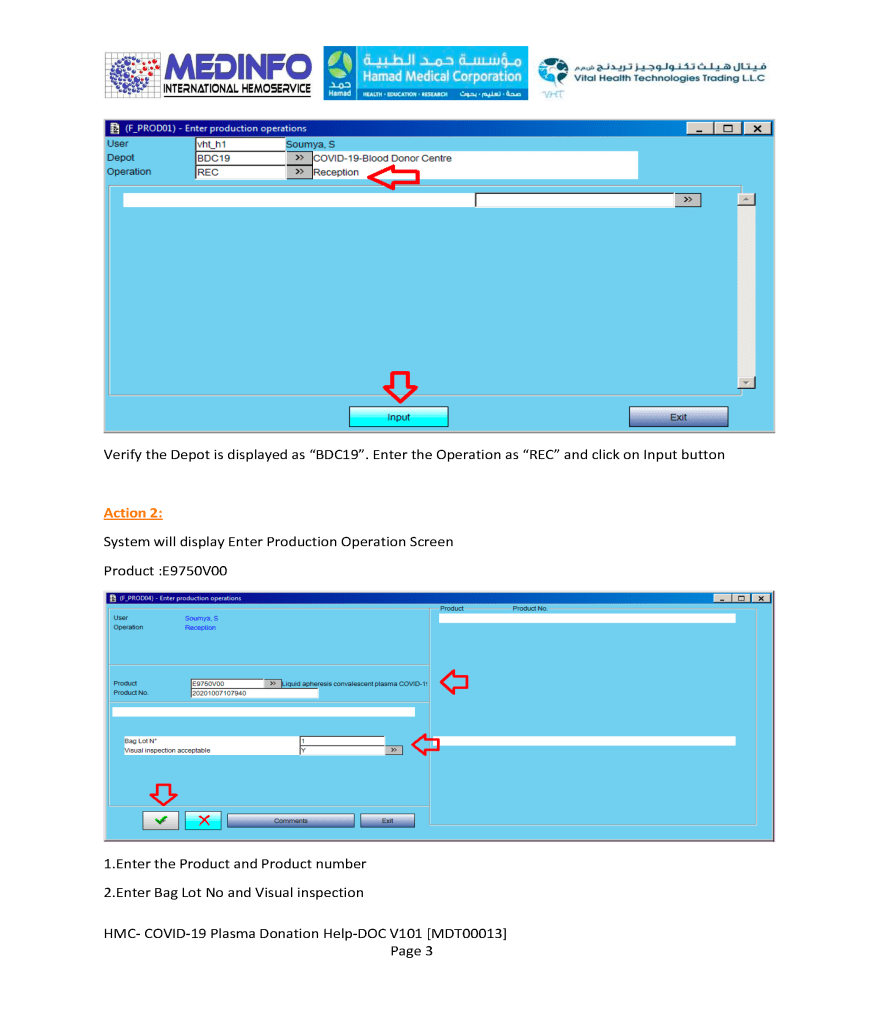
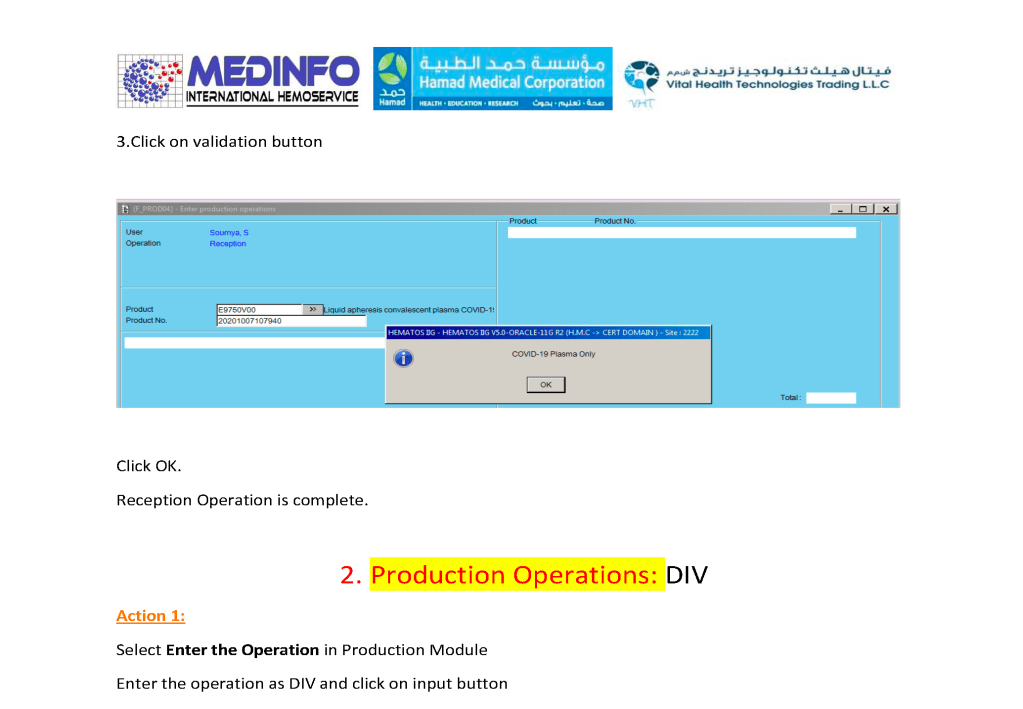
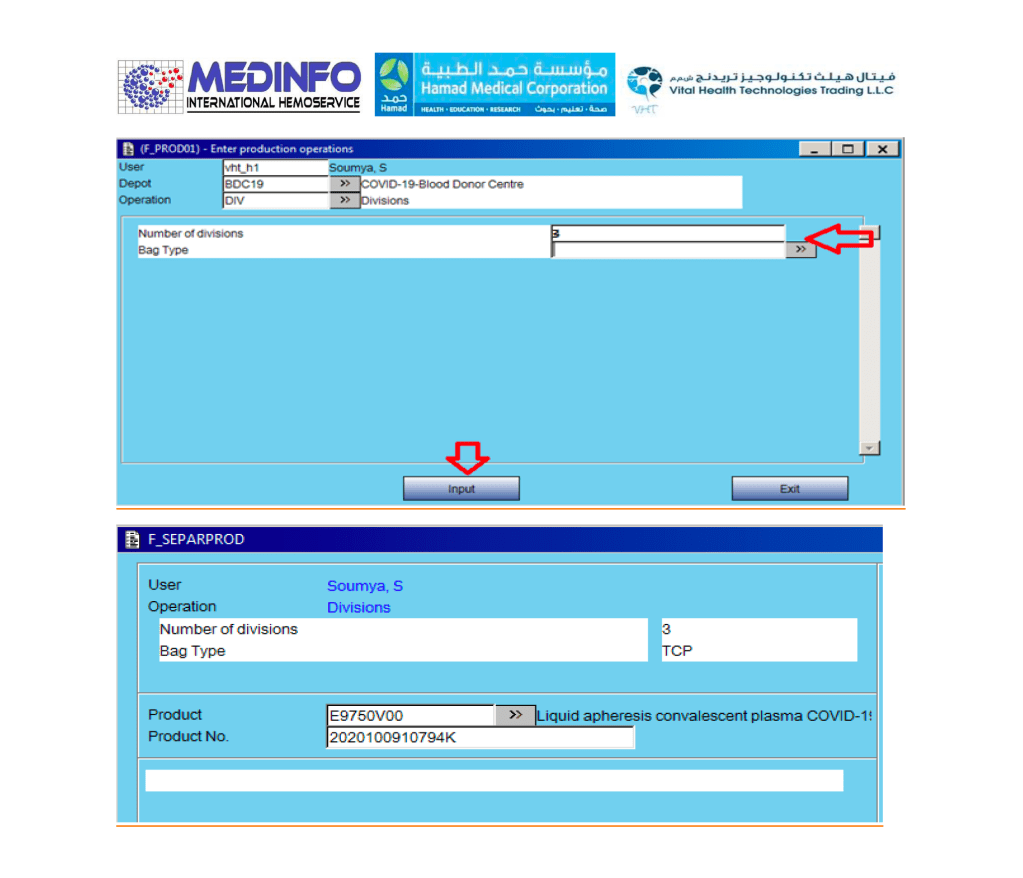
This is a part of a continuing series of posts on the actual Medinfo design of the CCP donation and release processes and covers the transfer of completed units to the hospital blood banks. It highlights specific changes made for the parallel CCP system I developed at HMC Doha.
A blood component is either located at a production site, a destination hospital blood bank site, or in transit. Here a quarantine production site is specified. The actual transfer protocols and allowable destination sites are listed for this product.
This is a teaching document for medical technology and transfusion fellows to explain the general structure of a validation.
Principle:
All validations must be planned. A validation protocol must be prepared with specific criteria for acceptance. All validations with attached evidence must approved by the Head, Transfusion Medicine.
Policy:
A written validation protocol must be prepared in the advance and at least including the following:
Specific parameters and number of iterations to be performed
Designated staff to perform validation
Documentary evidence of the testing
Specific acceptability criteria
The completed validation protocol must be submitted to the Division Head, Transfusion Medicine, or designee for review.
Once the validation plan has been reviewed, it must be performed by the designated staff.
Software validations will be performed in a specific test environment, not in the live, production system.
The completed validation document, including screenshots of the software functionality if applicable, must be submitted to the Division Head, Transfusion Medicine for review.
The equipment or software may only be used if the acceptability are met AND the validation is approved by the Division Head, Transfusion Medicine or designee.
The completed validation protocol will be stored in the document control system.
Reference:
Standards for Blood Banks and Transfusion Services, Current Edition, Bethesda, MD, USA
AABB Standards requires that all variances are documented and investigated and corrective actions taken when necessary. Any time a blood component is found to be defective (e.g. broken seal, leaking, discoloration, clots, etc.), mislabeled, or testing results incomplete or not documented, the cause should be investigated by the Donor Center and reported back to the initiator of the report in writing.
Policy:
All transfusion services must inspect all blood components upon receipt (e.g. for leakage, broken seals, improper temperature, clots, discoloration, gas, etc.).
Labels must be compared to the consignment sheet for complete concordance.
If units are found that are not listed or mislabeled, they must be reported in writing to the Donor Center and returned as-is for investigations.
If the unit is leaking or broken, ensure standard/universal precautions are taking to minimize contact with the fluids.
Damaged blood components must not be used. Units with mislabelings or other discrepancies between the labels and the consignment sheets may be used when such errors are corrected and officially reported by the Donor Center.
Use the standard incident (occurrence variance) report form (OVA) for each and every variance.
The submitting location should keep a copy of the OVA and immediately forward the original to the Transfusion Quality Section.
The Donor Center should investigate the variance and prepare a written investigative report and submit to the Division Head, Transfusion Medicine.
Donor Center investigations should be completed within one calendar week.
The Donor Center should forward a copy of the completed written investigation to the transfusion service which initiated the investigation.
The copy of the investigation report should be attached to the OVA and kept at the local site.
Transfusion Quality shall include these variances in its monthly reports.
References:
Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, Maryland, USA
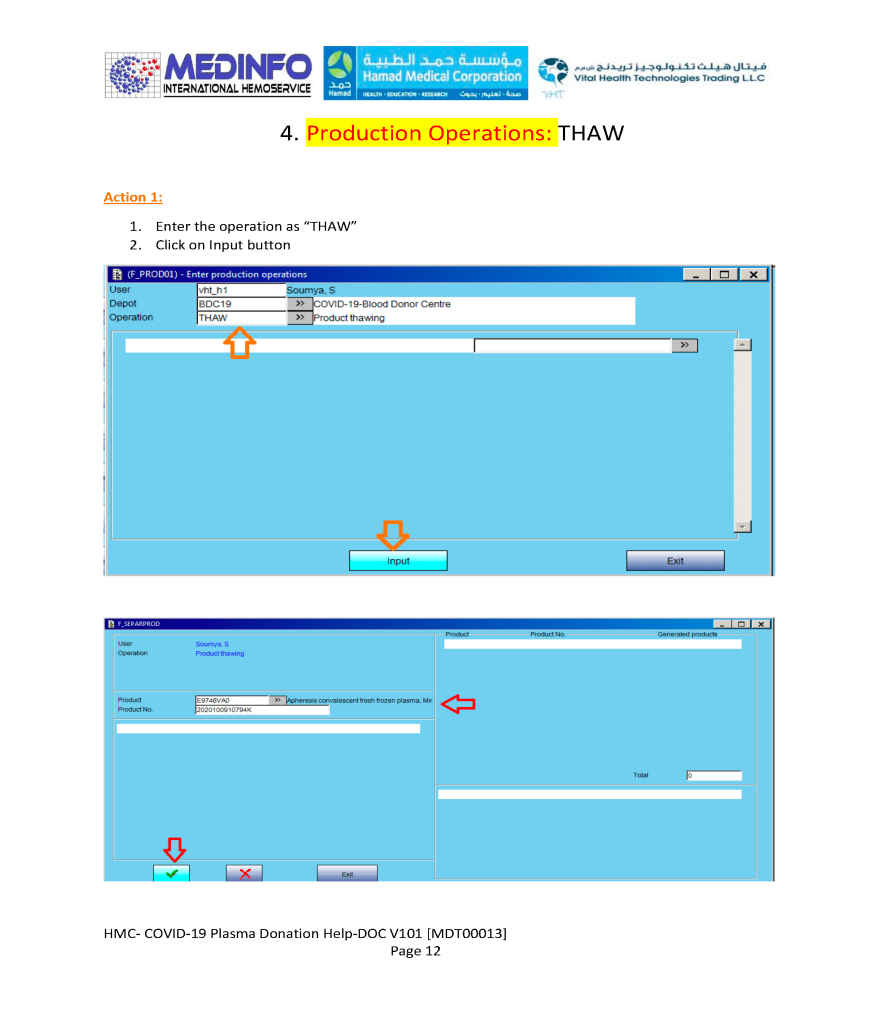
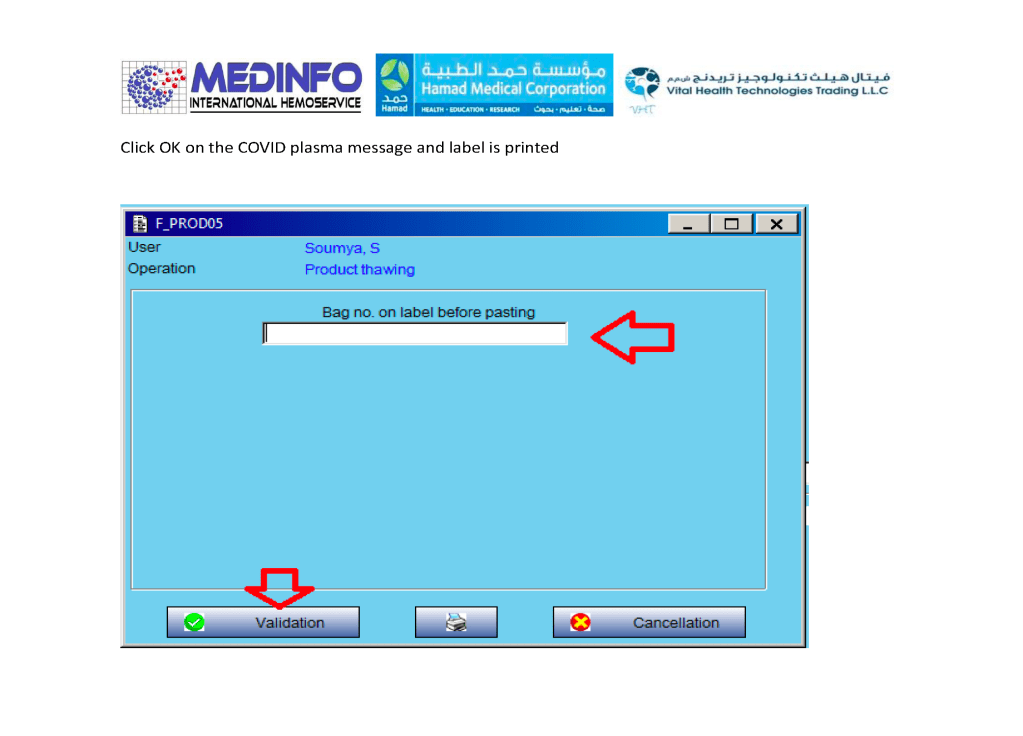
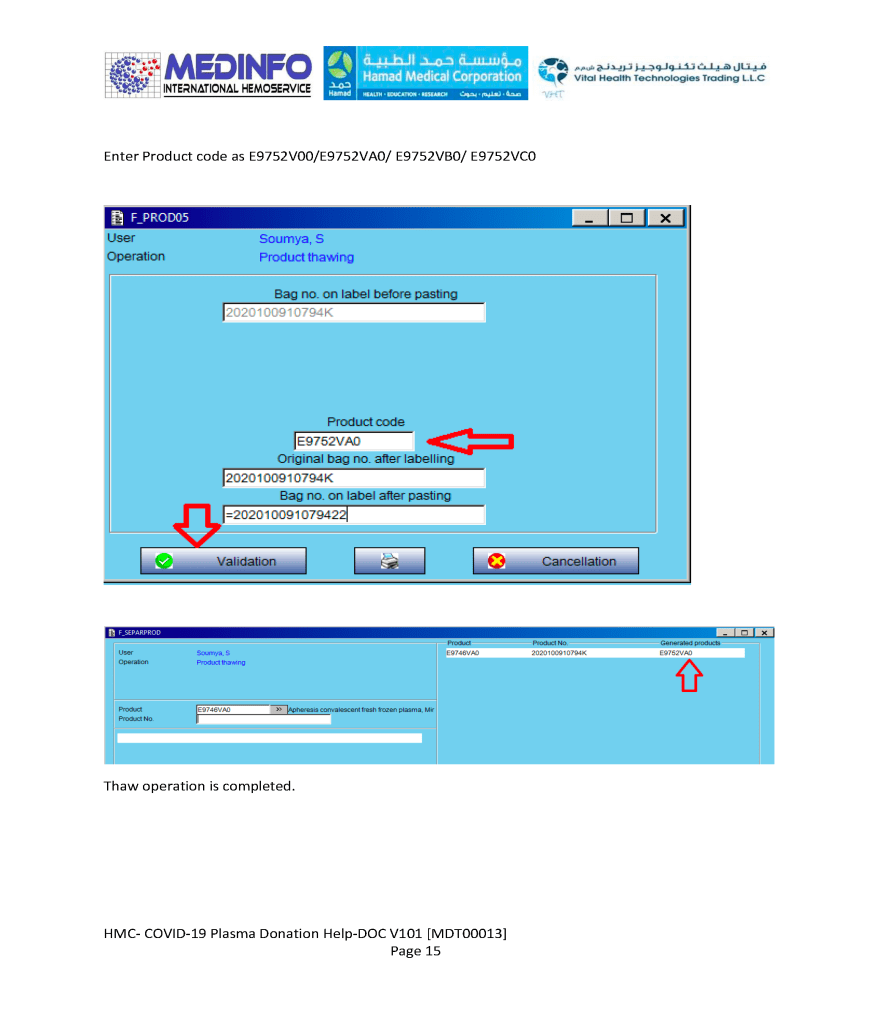
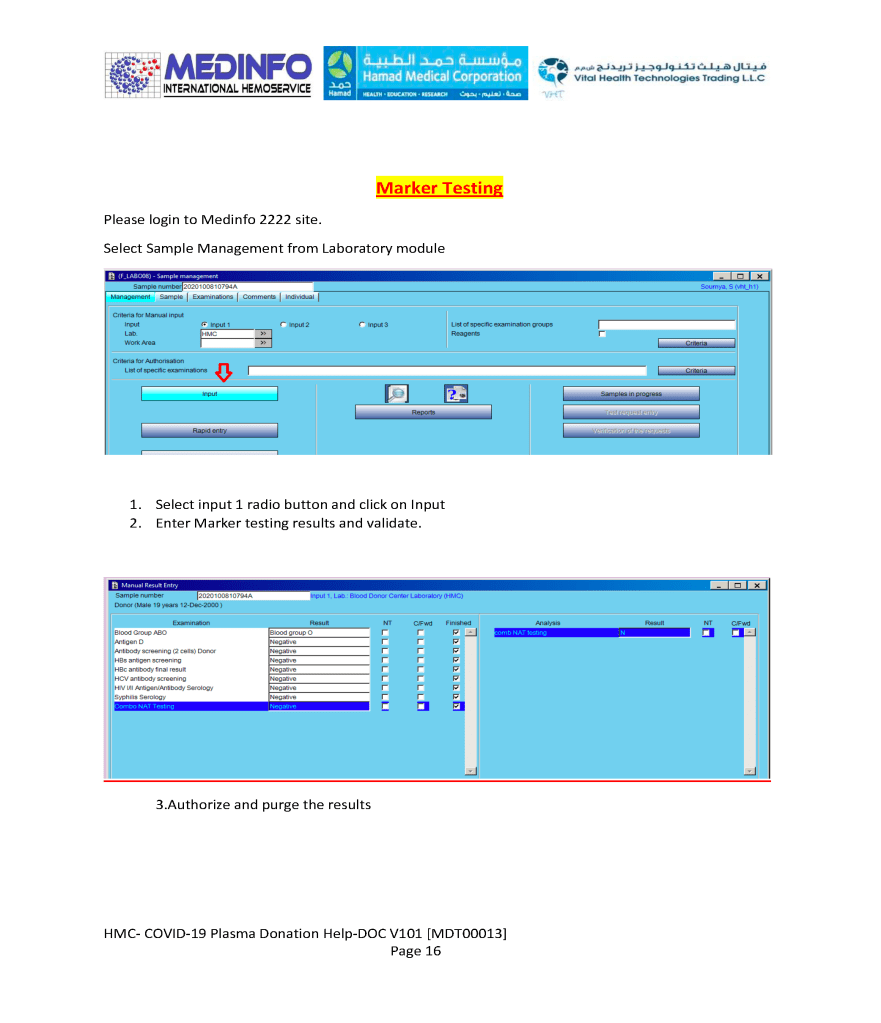
This is a part of a continuing series of posts on the actual Medinfo design of the CCP donation and release processes and covers CCP plasma thawing/labelling and donor marker testing. It highlights specific changes made for the parallel CCP system.
Thus, the machine interfaces for testing are the same as for regular testing and are not included in this document. Likewise, donor immunohematology testing is the same as for regular donors and is not addressed here
Once the blood component has left the hospital blood bank, it should be directed transported to the patient’s bedside for immediate transfusion.
At the bedside, the transfusionist (usually a nurse or doctor) must verify the information on the blood component labels (both the ISBT and specific reservation one for the patient). With a bedside device, this includes:
Scan the patient armband for hospital number
Scan ISBT label:
ABO/D type and any other antigen typings
Blood component type (RBCs, platelets, plasma, etc.)
Expiration date/time of the component
Verify Reservation Label (on back of unit)— centrally performed in blood bank computer system based on #1 and #2 above:
Intended recipient name and hospital number
Compatibility status (compatible, least-incompatible, etc.)
Expiration date/time of the compatibility testing/crossmatch
Record Documentation During Transfusion:
Physical inspection of the unit
Time stamp of transfusion start
Vital signs before starting transfusion
Periodic vital signs during transfusion
Time stamp of stopping transfusion
Any adverse effects during the transfusion
Any adverse effects after the transfusion (remote vital signs, oxygen saturation, EKG lead—if appropriate monitoring device attached to patient (e.g. Umana T1 device).
All of these parameters can be entered into a hand-held device that transmits them to the blood bank computer system (e.g. Medinfo Hemotrace.)
The Blood bank computer system (patient module) should verify that this is the proper unit for the intended recipient and that the transfusion is starting within the reservation limit of the unit and serves to verify the information on the reservation label attached on the back of the blood unit.
With a device such as the new Umana T1 device from the GPI group, the vital signs together with an EKG lead and oxygen saturation can be automatically uploaded into the handheld device that feeds into the blood bank computer system such as Medinfo Hematos IIG and/or directly transmitted to the blood bank software. This device can continuously record this information for several days and detect post-transfusion adverse effects such as TRALI/TACO and delayed hemolytic transfusion reactions.
Note:
Some other nursing hand-held devices are available for recording patient data but many cannot read the ISBT unit number or descriptor information. They also do not check with the blood bank computer system to check if the right unit of blood is being offered to the patient during the validity of the transfusion period (four hours after leaving the blood bank).
Note: This is an updated version of a previous post.
Principle:
Washing RBCs removes plasma and reduces the leukocyte count only by 1 log. For leukodepletion, we must rely on filtration to reduce the WBCs to less than 1 x 10⁶ per unit according to CE rules. Red cells or platelets in additive solution contain only minimal plasma (about 35 ml). There are few definite indications for washing RBCs and it should be rarely necessary.
Policy:
Washing RBCs should only be done in the following circumstances:
Deglycerolization of frozen RBCs.
Severe allergic or anaphylactic reactions to plasma proteins
IgA deficiency with anti-IgA
Paroxysmal nocturnal hemoglobinuria PNH—relative indication (often these patients receive RBCs before the diagnosis of PNH is confirmed)
Transfusing a previously irradiated RBC unit for pediatric use if more than 24 hours has passed since it was irradiated.
Any other time when so designated by a transfusion medicine consultant.
Note:
If anyone requests washed RBCs and it does not fit into one of the above categories, contact the transfusion medicine consultant.
Washed RBCs are NO substitute for leukodepleting RBCs by filtration NOR can they be used in place of irradiation for prophylaxis against transfusion-associated-graft-versus-host disease TAGVHD. Using the Reveos automated component processing system, all components are leukodepleted—RBCs are released in SAGM.
Reference:
Standards for Blood Banks and Transfusion Services, Current Edition, AABB, Bethesda, MD, USA
This is a part of a series of posts on the actual Medinfo design of the CCP donation and release processes. The registration of the donor and site, donor questionnaire/collection, and receipt/division of the product were covered in recent previous posts.
For the purpose of typing blood donors, we want to detect weak and partial D types and consider them as D-positive since even a portion of the D molecule is immunogenic and sensitization to it may cause anti-D hemolytic disease of the newborn.
Background:
Ortho Diagnostics Reagents use three different monoclonal antibody cocktails that react variably with the antigen D (Rh1)—these are found on TWO (2) cards: Anti-A/B/A,B/D/CDE and Anti-DVI:
Anti-D/Anti-RH1—IgM monoclonal antibody clone D7B8 can detect most examples of weak and partial D including weak D types 1, 2, 3, 4.0, and D categories II, III, IV, V, VII, DBT, and R0Har. It does NOT detect category VI. Retest positive reactions of 2+ or less by an alternate method. It may show different serologic activity compared to other D typing reagents.
Anti-CDE/Anti-RH1,2,3—IgM monoclonal blend of clone MS24 (anti-C), clone MAD2 (Anti-D), and clone C2 (Anti-E) can detect most cells expressing C, D, or E antigens. Most examples of partial D including DVI and weak D express C or E antigens and will be detected directly by the included anti-D or indirectly by the anti-C or anti-E in the cocktail. It does NOT detect Rh:33 (R0Har).
Anti-DVI/Anti-RH1 will agglutinate cells with a DVI phenotype, analogous to our previous DVI+ reagents.
Policy:
Follow the manufacturer’s instruction for storage, handling, and usage of all reagents.
If the D-control is positive, the reactions are indeterminate, repeat by another method.
For donors, run all three anti-D reagents listed—do not use the patient typing algorithm or reagents.
Use the following table for interpretation and further actions if needed:
Pattern #
Anti-D/D7B8
Anti-CDE
Anti-DVI
D-Interpretation
1
Positive
Positive
Positive
D-positive
2
Positive
Positive
Negative
Do additional testing
3
Positive
Negative
Negative
Do additional testing
4
Negative
Negative
Positive
Do additional testing
5
Positive
Negative
Positive
Do additional testing
6
Negative
Positive
Positive
D-positive, probable DVI variant
7
Negative
Positive
Negative
D-negative, probable rare genotypes r’ and/or r’’
8
Negative
Negative
Negative
D-Negative
If the reaction is 2+ or less with the Ortho anti-D/D7B8 reagent or 1+ with either the CDE or DVI reagents is patterns 2, 3, 4, or 5 above, repeat by another manufacturer’s reagents, including DVI+ and DVI- sensitivities.
Medinfo-Ortho interface settings for Blood Donor Center:
Anti-D/D7B8
Anti-CDE
D-Interpretation
3,4
1,2,3,4
D-positive
3,4
0
Indeterminate
0
0
Indeterminate
0
1,2,3,4
Do DVI REFLEX
REFLEX DVI
If DVI-pos, then D-positive
REFLEX DVI
If DVI-neg, then D-negative
0
0
D-negative
~
~
Indeterminate
~ means any other result
Note all of the following:
No reagents may be able to detect all D variants.
~ means any other value for that reagent (e.g. anti-D/D7B8 reactions 1, 2, mf, hemolyzed)
Note that this new algorithm makes a 2+ reactivity with Anti-D/D7B8 as indeterminate.
Publication J55650_EN, Instructions for Use, Blood Grouping Reagent Ortho Sera Anti-D(DVI) (Anti-RH1), Version 2.0, 2015-07-30, Alba Bioscience, Edinburgh, UK
Standards for Blood Banks and Transfusion Services, 29th Edition, AABB, Bethesda, MD, USA
This is a part of a series of posts on the actual Medinfo design of the CCP donation and release processes. The registration of the donor and site and donor questionnaire/collection were covered in recent previous posts.
\
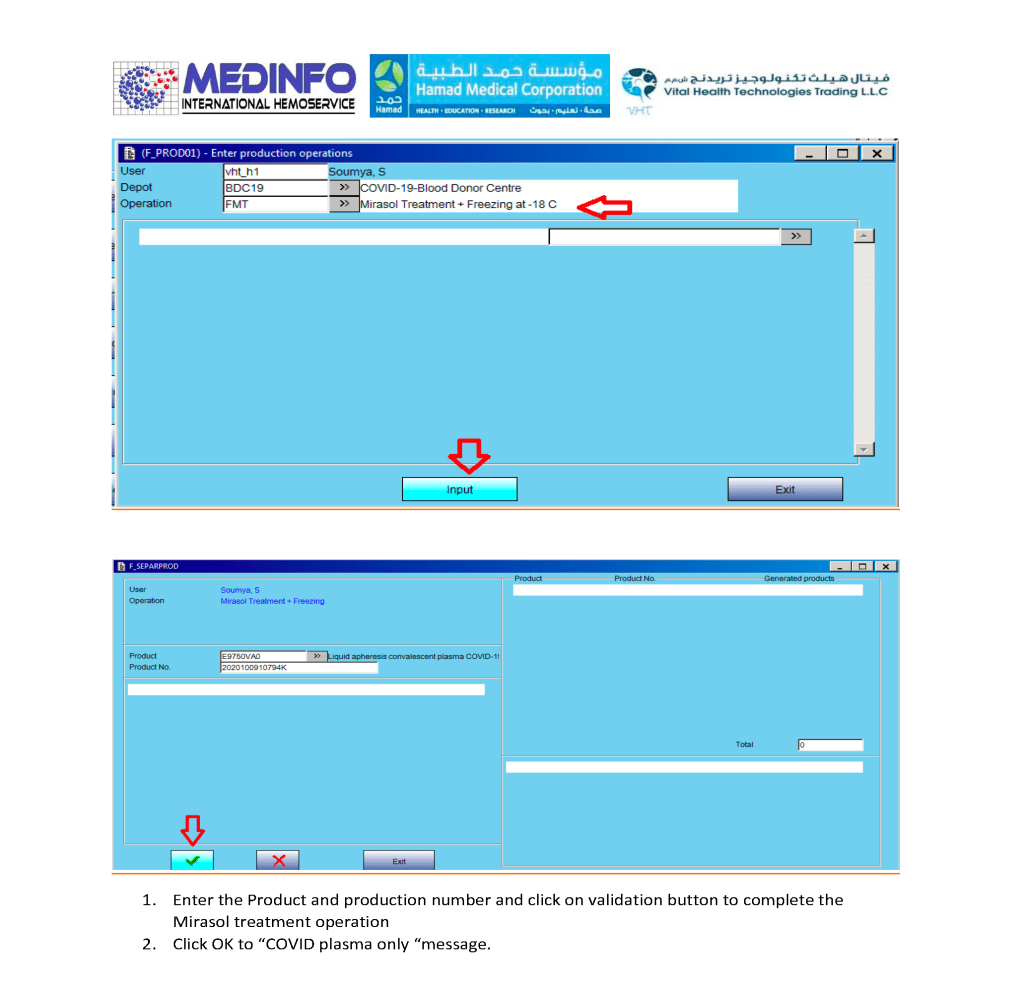
The process (pathogen-inactivation with Mirasol and freezing) wiil continue in a subsequent post.